Market Minds Advisory
Respiratory Distress Syndrome Management Market

Respiratory Distress Syndrome Management Market: Surfactant Therapy and Non-Invasive Support Converge

Neonatal intensive care units are shifting toward non-invasive respiratory support ahead of mechanical ventilation, and that preference is reshaping demand across surfactant therapeutics and high-flow nasal cannula equipment alike nationwide.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$3.2BMarket Size 2025
2036 FORECAST VALUE$6.4BBase Case , 2026 to 2036
CAGR 2026 TO 20366.5 %Bull 7.8% / Bear 5.2%
INCREMENTAL OPPORTUNITY$3.0BNet 10- year value creation
EXPANSION MULTIPLE1.88x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Neonatologists increasingly reach for non-invasive respiratory support before intubation, reserving mechanical ventilation for cases where less invasive approaches have already failed to stabilize the infant. Payers increasingly reinforce that clinical preference through updated coverage policy for both settings. Physicians now expect this pathway as the default rather than the exception.
High-flow nasal cannula and extracorporeal membrane oxygenation systems are the clearest growth story, and commercial momentum concentrates in North America, where the deepest neonatal intensive care infrastructure and reimbursement coverage outpace every other region MMA tracks by a considerable margin. That concentration is unlikely to narrow meaningfully before the end of the decade under most scenarios. Vendors expect this concentration to persist for several more years.
Five manufacturers hold well over half of global revenue, spanning both surfactant therapeutics and respiratory device makers with deep neonatal and critical care franchises. Clinical protocol guidelines and reimbursement policy shape purchasing decisions as much as device performance data does across every treatment modality in this market. Smaller regional device makers are chipping away at established players' share fastest in cost-sensitive public markets. Rankings among established leaders are unlikely to shift materially before decade's end.
Market Definition
The Respiratory Distress Syndrome Management Market covers pulmonary surfactant therapeutics, non-invasive ventilation systems, high-flow nasal cannula devices, respiratory monitoring equipment, and extracorporeal membrane oxygenation support used specifically to manage neonatal and acute respiratory distress syndrome. It excludes general invasive mechanical ventilators and chronic pulmonary disease management devices sold as separate product categories.
Base Year Value
$3.2B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
6.5% base case. Bull 7.8%. Bear 5.2%.
Fastest Growth Segment
Extracorporeal Membrane Oxygenation Support Systems: 11.0% CAGR
Fastest Growth Country
India: 8.5% CAGR
Fastest Growth Region
South Asia and Pacific: 8.5% CAGR
Largest Region
North America: 33% of 2025 global value
Market Leaders
Chiesi Farmaceutici SpA, Drägerwerk AG & Co KGaA, Getinge AB, Fisher & Paykel Healthcare Corporation, Vyaire Medical Inc. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Respiratory Distress Syndrome Management Market Forecast Scenarios

respiratory-distress-syndrome-management-size-forecast-scenario-1787306724978
Between 2020 and 2025 the market grew steadily as non-invasive respiratory support protocols gained clinical favor, interrupted briefly by pandemic-era ICU capacity strain that simultaneously raised awareness of acute respiratory distress syndrome management before demand normalized through 2022 as elective and routine neonatal care volumes recovered across most developed healthcare systems. Vendors report order volumes largely normalized to a new, higher baseline by early 2023 across most markets.
The base case assumes steady 6.5% annual growth through 2036, anchored to three mechanisms: continued preference for non-invasive respiratory support over early intubation in both neonatal and adult critical care settings, expanding extracorporeal membrane oxygenation access for severe cases, and rising preterm birth rates in South Asia and parts of East Asia widening the addressable neonatal patient pool. Group purchasing and hospital network capacity investment have reinforced this trajectory across most recent fiscal quarters.
The bull case centers on extracorporeal membrane oxygenation access expanding faster than currently modeled as more hospitals build this capability. The bear case centers on neonatal intensive care capacity constraints in lower-income markets slowing device adoption, stretching revenue realization timelines by a year or more. Neither scenario shifts the leading five manufacturers' relative rankings materially within the decade.

Non-Invasive Support Reshapes Critical Care Protocols

Neonatal intensive care units increasingly treat non-invasive respiratory support as the default starting point for newly diagnosed respiratory distress cases, reserving invasive mechanical ventilation for patients who fail to stabilize on less invasive approaches first. Vendors that cannot demonstrate readiness for this default pathway increasingly lose consideration at the earliest purchasing conversation. That professionalization has raised the bar for how vendors demonstrate value.
MARKET CONCENTRATIONCR5 58%Reflects a moderately concentrated field of specialized makers
AVERAGE SELLING PRICE$1,800-95,000 per systemVaries considerably by treatment modality and case complexity
TOP PRODUCING COUNTRYUnited States, 28% shareLargest base of manufacturing and device assembly capacity
CAPACITY UTILISATION72%Reflects steady but not maximal production line usage
REPLACEMENT CYCLE LENGTH6-8 yearsReflects the typical device lifespan before full replacement
FEEDSTOCK COST SHARE23% of COGSSurfactant lipid extraction and sensor components as input cost
Clinical protocol guidelines now shape which treatment modality reaches meaningful volume more than device performance specifications alone do, since a technically superior device without protocol endorsement struggles to gain adoption regardless of how favorably clinicians view its underlying design. Manufacturers increasingly treat guideline relationship building as a core commercial function rather than a purely clinical affairs exercise. A device without protocol endorsement struggles to reach volume regardless of clinical merit.
Over the next decade, extracorporeal membrane oxygenation access will likely expand beyond the largest academic medical centers into broader community hospital networks, narrowing the gap between facilities equipped for the most severe respiratory distress cases and those still referring such patients elsewhere. Manufacturers still reliant entirely on academic-center-only distribution risk losing ground to faster-moving community-focused rivals. Companies positioned early stand to capture share of newly equipped facilities.
"The intubation decision is the real inflection point. Everything upstream of that moment is where this market's growth is actually concentrated."
Director, Healthcare Practice · MMA Healthcare Practice · Au

Market Trends

Non-Invasive Support Displaces Early Intubation Protocols

Neonatal and critical care clinical guidelines increasingly favor non-invasive respiratory support as the first intervention for respiratory distress, reserving mechanical ventilation for cases where less invasive approaches have already failed. Major neonatology professional societies updated treatment algorithm guidance in 2022 and again in 2024 to reflect growing evidence that non-invasive approaches reduce lung injury risk in premature infants. Manufacturers report meaningfully higher high-flow nasal cannula and non-invasive ventilation prescribing volume in hospitals that have adopted these updated protocols compared to hospitals still following older intubation-first approaches. Group purchasing organizations increasingly specify protocol-compliant equipment as a standard contract requirement.
Market Impact: Adds 3.5% annual birth growth
Extracorporeal Membrane Oxygenation Access Expands Beyond Academic Centers

Extracorporeal membrane oxygenation capability, once concentrated almost entirely at large academic medical centers, is expanding into broader community hospital networks as smaller systems build this capability to avoid costly and clinically risky patient transfers for the most severe respiratory distress cases. Hospital network capacity tracking shows meaningful growth in the number of facilities offering this capability over the past several years, and each newly equipped facility represents a discrete capital purchase decision separate from any existing academic center relationship a health system might already operate. Vendors report this expansion pattern accelerating faster than originally forecast in most planning models.
Market Impact: Adds 4% annual ARDS diagnosis growt

Market Opportunities and Growth Drivers

Rising Preterm Birth Rates Widen the Neonatal Patient Pool

Preterm birth rates continue rising across several large-population countries in South Asia and East Asia, directly widening the addressable neonatal respiratory distress syndrome patient pool given the condition's strong correlation with gestational age at birth. World Health Organization birth registry data shows meaningful year-over-year increases in preterm birth incidence in several major markets, and each additional preterm birth represents a potential respiratory distress syndrome treatment candidate given how commonly the condition affects infants born before full lung maturation. This trend is expected to persist for at least the next decade given underlying maternal health trends.
Market Impact: Limits access to 50% of facilities

Rising ARDS Awareness Following Pandemic-Era Critical Care Strain

Acute respiratory distress syndrome awareness among critical care physicians rose meaningfully following pandemic-era experience managing large volumes of severe respiratory failure cases, reinforcing clinical familiarity with both non-invasive and extracorporeal support options. Critical care medicine societies report sustained elevated attention to ARDS management protocols even as pandemic-specific case volume has declined considerably, and this heightened baseline awareness continues supporting steady device and monitoring equipment purchasing across adult critical care units. Critical care societies continue publishing updated guidance reflecting lessons learned from that period of strain. This heightened baseline shows no sign of receding meaningfully in the near term.
Market Impact: Limits access to 40% of hospitals

Market Restraints and Challenges

Neonatal Intensive Care Capacity Constraints Limit Adoption

Many lower-income markets lack sufficient neonatal intensive care unit capacity and trained staff to fully implement non-invasive respiratory support protocols at the scale clinical guidelines recommend, leaving preterm infants without access to the equipment that could meaningfully improve outcomes. The root cause is that building neonatal intensive care capacity requires years of infrastructure investment and specialized staff training that many regional health systems have not yet completed. Manufacturers and public health organizations are exploring simplified, lower-cost device designs suited to resource-constrained settings to expand access beyond well-funded academic centers. Progress remains gradual given the investment still required.
Market Impact: Shifts 35% of intervention volume

High Extracorporeal Support Cost Strains Hospital Budgets

A complete extracorporeal membrane oxygenation setup with disposable circuit components commonly costs $60,000 to $95,000 per treatment course, a level that strains hospital budgets in markets without the deep private insurance reimbursement common in the United States. The root cause is that the specialized circuit components and trained perfusionist staff required for this therapy carry inherently high per-patient costs that are difficult to compress without compromising safety. Manufacturers are exploring simplified circuit designs and remote monitoring support to reduce staffing requirements and overall treatment cost. Vendors report early pilot programs showing promising results in initial deployments.
Market Impact: Adds 45 newly equipped centers
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

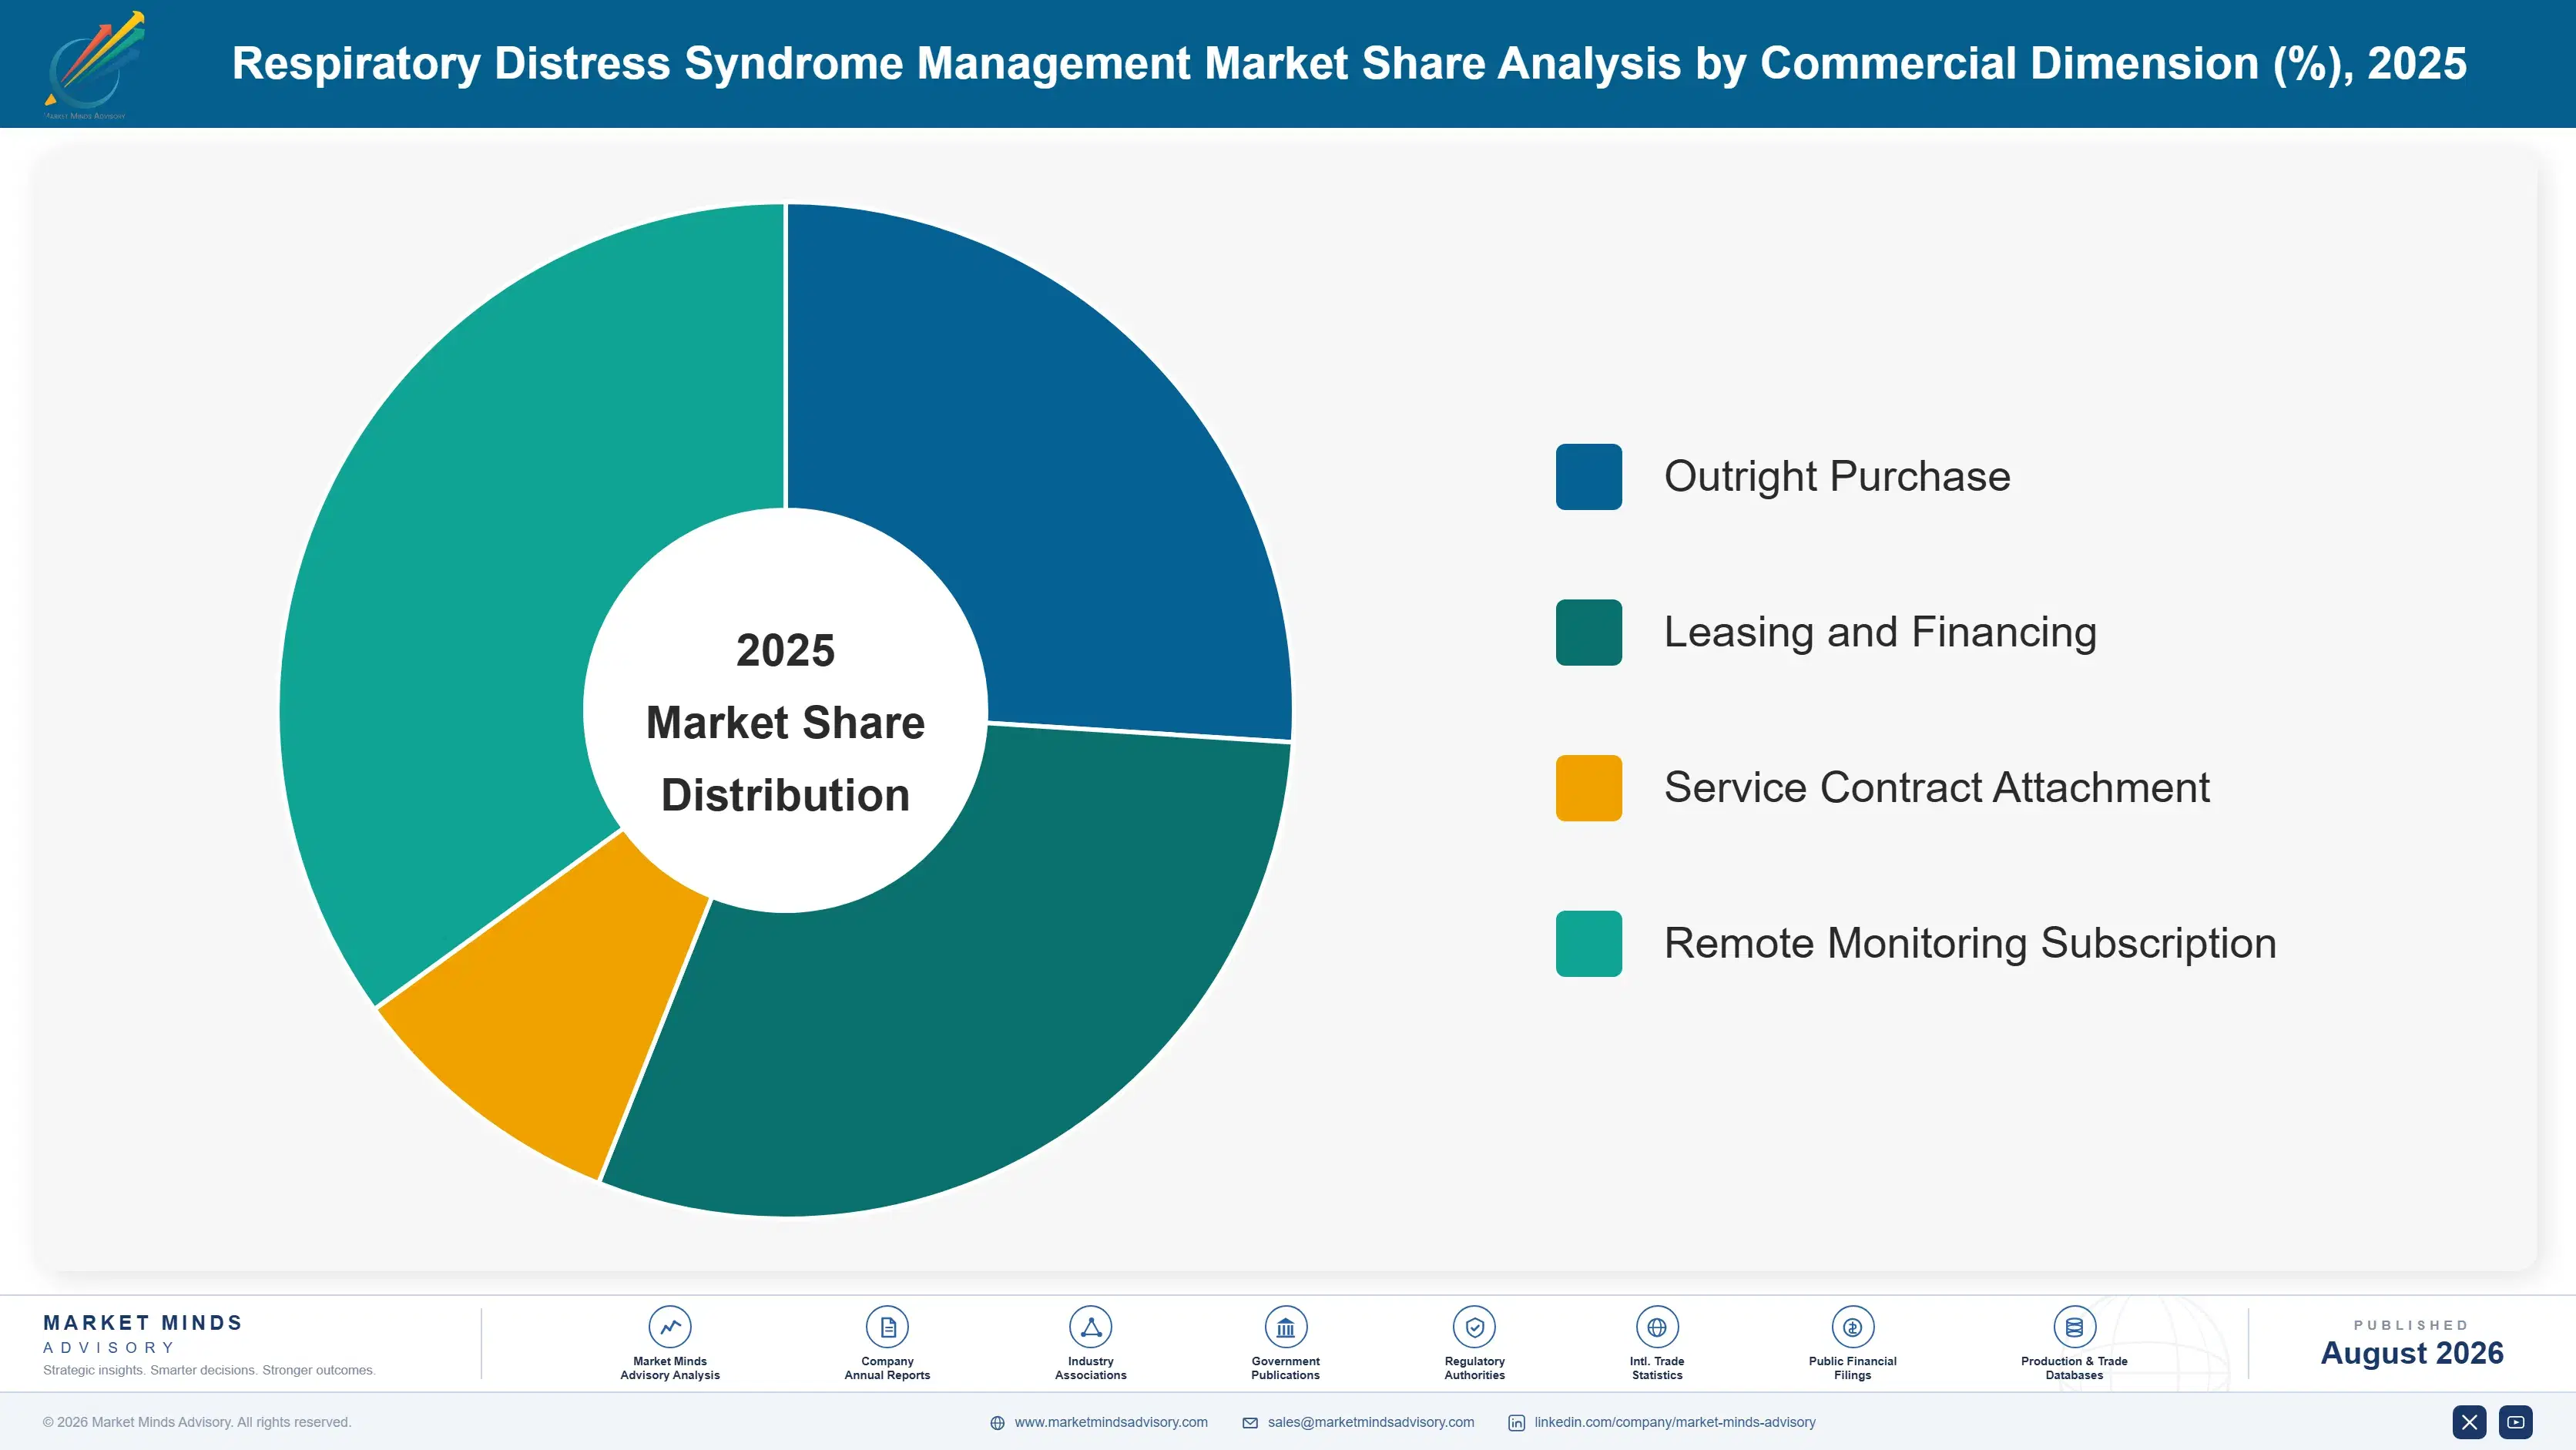
The market segments by treatment modality and product type, spanning surfactant therapeutics, non-invasive ventilation, high-flow nasal cannula systems, respiratory monitoring, and extracorporeal membrane oxygenation support, since each modality follows a distinct clinical protocol and severity tier across neonatal and adult critical care settings. No single modality alone dominates purchasing decisions across every facility type.
respiratory-distress-syndrome-management-market-share-analysis-1787306725518

Extracorporeal Membrane Oxygenation Support Systems

Extracorporeal membrane oxygenation systems are the fastest-growing segment as this capability expands beyond academic medical centers into broader community hospital networks seeking to avoid costly and clinically risky patient transfers for the most severe respiratory distress cases. Manufacturers have invested heavily in simplifying circuit design and reducing the specialized perfusionist staffing traditionally required to operate this therapy, addressing one of the most common reasons smaller hospitals historically hesitated to build this capability. Remote monitoring support services now let smaller facilities consult with academic center specialists in real time during treatment, meaningfully lowering the barrier to building this capability locally. Hospital network capacity investment continues expanding this segment faster than any other modality MMA tracks as institutions prioritize reducing transfer delays.
CAGR 11.0%

High-Flow Nasal Cannula Systems

High-flow nasal cannula systems are growing quickly as neonatal and adult critical care protocols increasingly favor this modality over more invasive alternatives for appropriately selected patients. Manufacturers have invested in improving humidification consistency and reducing skin irritation risk from extended use, addressing tolerability concerns that limited earlier-generation device designs. Clinical guideline updates increasingly list high-flow nasal cannula support as an appropriate first-line intervention for a broadening range of respiratory distress severity levels, and hospitals in markets where these updated guidelines have already taken effect report meaningfully higher device utilization than hospitals still following older, more conservative protocols. Manufacturers report meaningfully higher device utilization in these markets, reinforcing continued investment in expanding this treatment tier.
CAGR 10.5%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

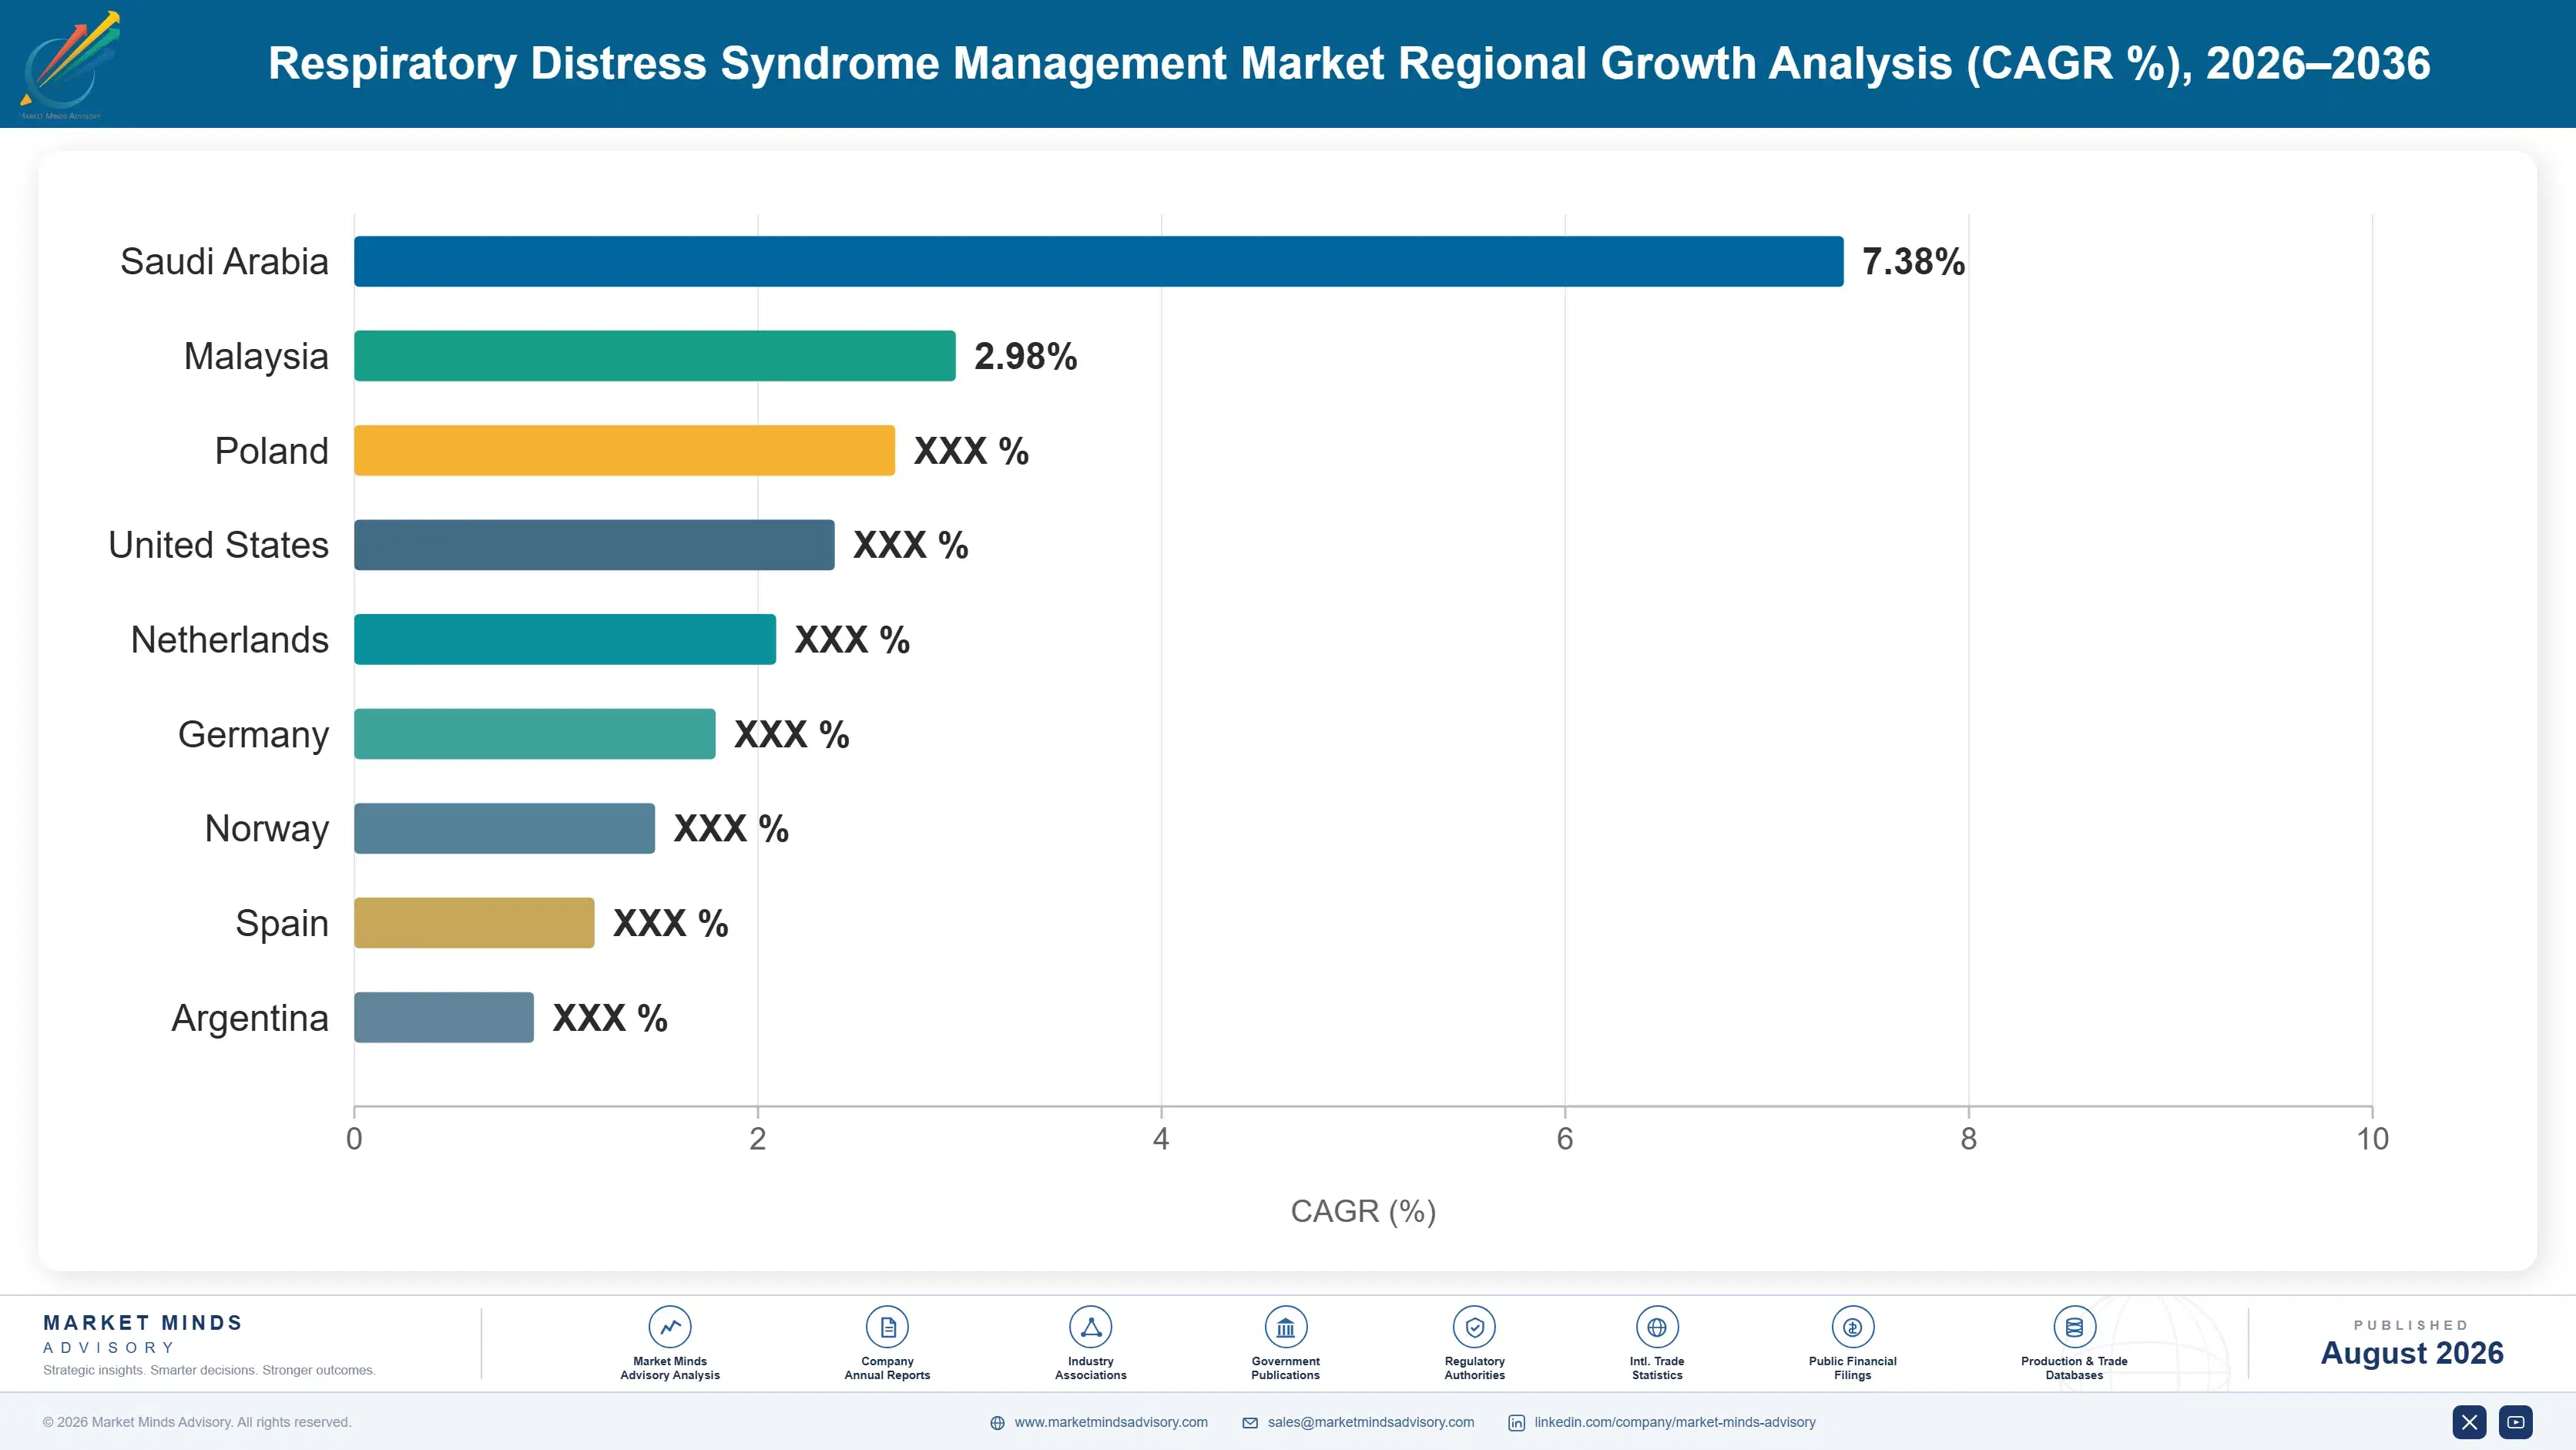
North America accounts for well over a third of global revenue, reflecting the deepest neonatal intensive care infrastructure anywhere, while South Asia and Pacific posts the fastest regional growth given its large preterm birth burden. Every region shows steady expansion, though pace varies by neonatal infrastructure maturity.

North America

The United States carries the largest share of any market MMA tracks, a concentration well above the standard regional band that reflects both the deepest neonatal intensive care infrastructure and the strongest private insurance reimbursement for extracorporeal membrane oxygenation therapy found anywhere globally. Clinical guideline updates favoring non-invasive support have concentrated here first for nearly every major protocol change, giving domestic manufacturers a first-mover advantage before international bodies adopt equivalent guidance. Canada's public health system covers neonatal respiratory care broadly, though its smaller population keeps overall regional volume concentrated in the United States. Academic medical centers across both countries maintain the highest extracorporeal support capacity globally, reinforcing steady equipment purchasing across most major markets tracked in this region.
Share: 33% | CAGR: 6.0% (2026 to 2036)

Western Europe

Germany and the United Kingdom carry the largest share of regional demand, supported by public health systems that fund comprehensive neonatal intensive care and adult critical care infrastructure broadly. France and the Nordic countries follow with steady adoption tied to national health service capital budgets that increasingly prioritize non-invasive support equipment. Centralized health technology assessment across most of the region gives national authorities meaningful pricing negotiating power, keeping average selling prices below United States private market levels even as clinical protocol adoption remains comparably strong. Extracorporeal membrane oxygenation capacity here typically concentrates in fewer, larger specialized centers than in the United States across most major national markets. Reimbursement timelines here typically lag United States purchasing cycles by several months.
Share: 25% | CAGR: 5.0% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
respiratory-distress-syndrome-management-country-cagr-analysis-1787306726031

Where Respiratory Care Makers Can Grow Margin

Beyond patient volume growth, manufacturers have several concrete paths to lift revenue per facility, spanning consumable circuit attachment, service contract expansion, remote monitoring subscriptions, and modality upgrade positioning layered on top of the core equipment franchise. Each applies broadly across hospital relationships already engaged with the manufacturer. None require heavy capital investment beyond routine service and consulting staffing.

Disposable Circuit and Consumable Attachment Revenue

Extracorporeal membrane oxygenation and high-flow nasal cannula therapy both require recurring disposable circuit and consumable replacement for each treatment course, converting a modest equipment sale into a much larger revenue relationship worth roughly $8,000 to $15,000 per completed extracorporeal treatment course. Manufacturers with the largest installed equipment base capture disproportionate consumable revenue simply by virtue of having more active treatment courses underway at any given time across their hospital network relationships. This dynamic reinforces the advantage held by manufacturers with the largest existing installed base. This revenue pattern persists across each treatment course a facility completes over time.
Market Impact: Adds roughly $8,000 to $15,000 per

Attaching Multi-Year Service and Maintenance Contracts

Vendors increasingly attach multi-year service and preventive maintenance contracts to equipment sales, converting a one-time capital transaction into a recurring revenue relationship worth roughly 10 to 15% of the original equipment price annually. Hospitals favor bundled service agreements because unplanned equipment downtime directly threatens patient safety in critical care settings, creating strong incentive to prioritize uptime guarantees over marginal price savings from third-party repair providers. Vendors with the largest installed base capture disproportionate service revenue across their existing hospital relationships. Hospitals rarely switch service providers once a stable maintenance relationship has been established.
Market Impact: Adds 10 to 15% recurring annual ser

Remote Monitoring Support for Smaller Facilities

Vendors increasingly offer remote monitoring and specialist consultation services for smaller hospitals building extracorporeal support capability without extensive in-house perfusionist expertise, converting a capability gap into a billable subscription revenue stream typically worth $15,000 to $30,000 annually per facility. This service both lowers the adoption barrier for smaller hospitals and builds a durable advisory relationship that often leads to expanded equipment purchases as facility capability matures. Manufacturers increasingly view this pathway as capital-efficient relative to pursuing new hospital accounts alone. Early consultation relationships often lead to expanded equipment purchases as facility confidence grows.
Market Impact: Adds $15,000 to $30,000 annual reve

Modality Upgrade Positioning From Non-Invasive to Extracorporeal

Manufacturers with a full modality portfolio spanning non-invasive support through extracorporeal systems capture larger account share as hospitals expand their own respiratory care capability tier by tier, since a facility already using one vendor's non-invasive equipment often defaults to the same vendor when upgrading to more advanced capability. This account continuity typically lifts total facility revenue by 20 to 30% relative to a facility sourcing each modality from a different vendor. Manufacturers report this account continuity pattern strengthening as more facilities expand capability year over year. This continuity advantage compounds as facilities expand their own capability year over year.
Market Impact: Lifts facility revenue by 20 to 30%

Who Controls the Margin Pool

Five manufacturers hold 58% of global revenue, a moderately concentrated field spanning both surfactant therapeutics and respiratory device makers. Chiesi and Fisher & Paykel Healthcare form a clear leading pair whose combined therapeutic and device franchises give them a durable gap over the next tier of challengers, including Drägerwerk, Getinge, and Vyaire Medical. None matches their combined therapeutic and device franchise breadth built over years.
Current competitive activity centers on three dimensions: expanding extracorporeal membrane oxygenation capability and remote monitoring support for smaller hospitals, deepening clinical guideline relationships that favor non-invasive protocols, and building full-portfolio modality positioning that captures account share across the full severity spectrum. Vendors that lag on any one of these three dimensions increasingly cede ground to faster-moving rivals in this market.

Emerging pressure comes from regional device manufacturers in China and India building lower-cost non-invasive ventilation and high-flow nasal cannula systems, gaining ground fastest in cost-sensitive public hospital markets across South Asia and parts of Latin America. Rankings among the established multinational leaders are unlikely to shift materially before 2030, but the value-tier device segment is becoming considerably more contested territory. Several established manufacturers have begun launching dedicated value-tier sub-brands to defend that ground.
respiratory-distress-syndrome-management-company-positioning-matrix-1787306726548

Competitive Moat and Risk Dimensions

CHIESI FARMACEUTICI SPA

Moat: Surfactant Franchise Clinical Depth

Chiesi's decades-long position in surfactant replacement therapy gives it deep neonatology physician relationships and clinical trial infrastructure that later entrants must overcome, and its established distribution network in neonatal intensive care units reinforces steady prescribing volume even as newer synthetic formulations enter the market. This durability lets Chiesi sustain steady volume even as competitors introduce new formulations.
CHIESI FARMACEUTICI SPA

Risk: Narrow Therapeutic Focus

Chiesi's portfolio remains concentrated in surfactant therapeutics relative to competitors with broader device and monitoring franchises, leaving it more exposed if hospital purchasing increasingly favors vendors who can bundle therapeutics with the full respiratory care equipment relationship. Hospitals increasingly favor vendors offering a broader respiratory equipment relationship alongside therapeutics.
FISHER & PAYKEL HEALTHCARE CORPORATION

Moat: Non-Invasive Device Portfolio Breadth

Fisher & Paykel's broad non-invasive ventilation and high-flow nasal cannula portfolio gives it reach across both neonatal and adult critical care settings, and its humidification technology expertise supports meaningful clinical differentiation that pure hardware competitors without comparable technology depth struggle to replicate. This differentiation supports premium pricing that pure hardware competitors struggle to match.
FISHER & PAYKEL HEALTHCARE CORPORATION

Risk: Limited Extracorporeal Presence

Fisher & Paykel's portfolio does not extend into extracorporeal membrane oxygenation systems, the fastest-growing segment in this market, leaving it dependent on non-invasive modality growth alone while competitors with broader portfolios capture share across the full severity spectrum. This gap could widen as more competitors expand into the fastest-growing severity tier of the market.

Players Tracked

Prominent Players

Chiesi Farmaceutici SpA
Drägerwerk AG & Co KGaA
Getinge AB
Fisher & Paykel Healthcare Corporation
Vyaire Medical Inc

Other Key Players

ResMed Inc
Philips Respironics
Medtronic plc
Becton Dickinson and Company
Smiths Medical Inc
Hamilton Medical AG
Masimo Corporation
Nihon Kohden Corporation
Zoll Medical Corporation
Aerogen Ltd
Vapotherm Inc
Armstrong Medical Ltd
Inspiration Healthcare Group plc
Bunnell Incorporated
AbbVie Inc

Recent Developments

MARCH 2026

Fisher & Paykel Healthcare Launches Expanded High-Flow Nasal Cannula Platform

Fisher & Paykel Healthcare introduced an updated high-flow nasal cannula platform with improved humidification consistency aimed at reducing skin irritation during extended use. The launch targeted neonatal intensive care units first, with broader adult critical care availability planned across the following fiscal year. Clinical usability data accompanied the launch.
Signal: Improved humidification technology is quic
SEPTEMBER 2025

Getinge Acquires Remote Monitoring Support Platform

Getinge completed the acquisition of a specialty remote monitoring and consultation platform focused on supporting smaller hospitals building extracorporeal membrane oxygenation capability. The deal brought expanded consultation capability in-house, broadening Getinge's service offering considerably beyond its prior hardware-only model. Deal terms were not disclosed publicly by either company.
Signal: Remote monitoring support platforms are qu
JANUARY 2026

Chiesi Signs Multi-Year National Distribution Agreement

Chiesi entered a multi-year distribution agreement with a large national hospital network covering surfactant therapeutics across its full neonatal intensive care unit portfolio. The agreement was a distribution contract, not a joint venture or acquisition, covering supply terms across the network's full multi-year term. Financial terms were not disclosed.
Signal: Multi-year, national distribution agreemen

Surfactant Lipid and Sensor Component Exposure

Surfactant lipid extraction and sensor components together represent roughly 23% of cost of goods sold for a complete respiratory distress syndrome management portfolio, sourced predominantly from specialized biological extraction facilities and precision sensor manufacturers concentrated in the United States, Europe, and Japan, with limited near-term substitution options for either category. Few alternate sourcing regions exist at comparable purity and precision levels.
The 2021 to 2022 global supply chain disruption affected both biological extraction inputs and precision sensor components broadly, with several manufacturers reporting extended lead times in company annual reports covering that period. The International Energy Agency's supply chain analysis of that period noted the disruption's disproportionate impact on specialized manufacturers reliant on a concentrated supplier base not easily substituted on short notice. Manufacturers report continued monitoring of this supplier base given persistent trade risk.

Smaller manufacturers without long-term supply agreements or in-house extraction and assembly capability bear considerably more exposure to price swings than the largest players, who can negotiate volume discounts and secure priority allocation during shortages. This dynamic reinforces the advantage already held by the leading five manufacturers, since a component shortage can delay a smaller competitor's production while the largest players continue fulfilling orders on schedule.
respiratory-distress-syndrome-management-cost-volatility-analysis-1787306726745

Dual-Sourcing Biological Extraction Facilities

Larger manufacturers are qualifying second extraction facility suppliers to reduce dependence on any single source, a step that adds qualification cost upfront but meaningfully reduces disruption risk during future shortages. Qualification cycles for biological extraction capacity typically run twelve to eighteen months before volume production begins. Larger vendors with existing supplier ties tend to move faster through this process.

Long-Term Fixed-Price Component Supply Agreements

Several manufacturers have moved from spot purchasing to multi-year fixed-price agreements with component suppliers, trading some pricing flexibility for supply certainty and predictable input costs across budget planning cycles. These agreements typically run three to five years before renegotiation begins. Vendors report these agreements have meaningfully smoothed quarterly input cost variance across recent years.

In-House Extraction and Assembly Capability Investment

The largest manufacturers are investing in in-house biological extraction and sensor assembly capability to reduce reliance on external suppliers entirely for at least a portion of production volume, insulating margin from supplier-side price increases over a multi-year investment horizon smaller rivals generally cannot fund. This investment horizon typically spans four to six years before capacity comes fully online.

Portfolio Architecture for Margin Defence

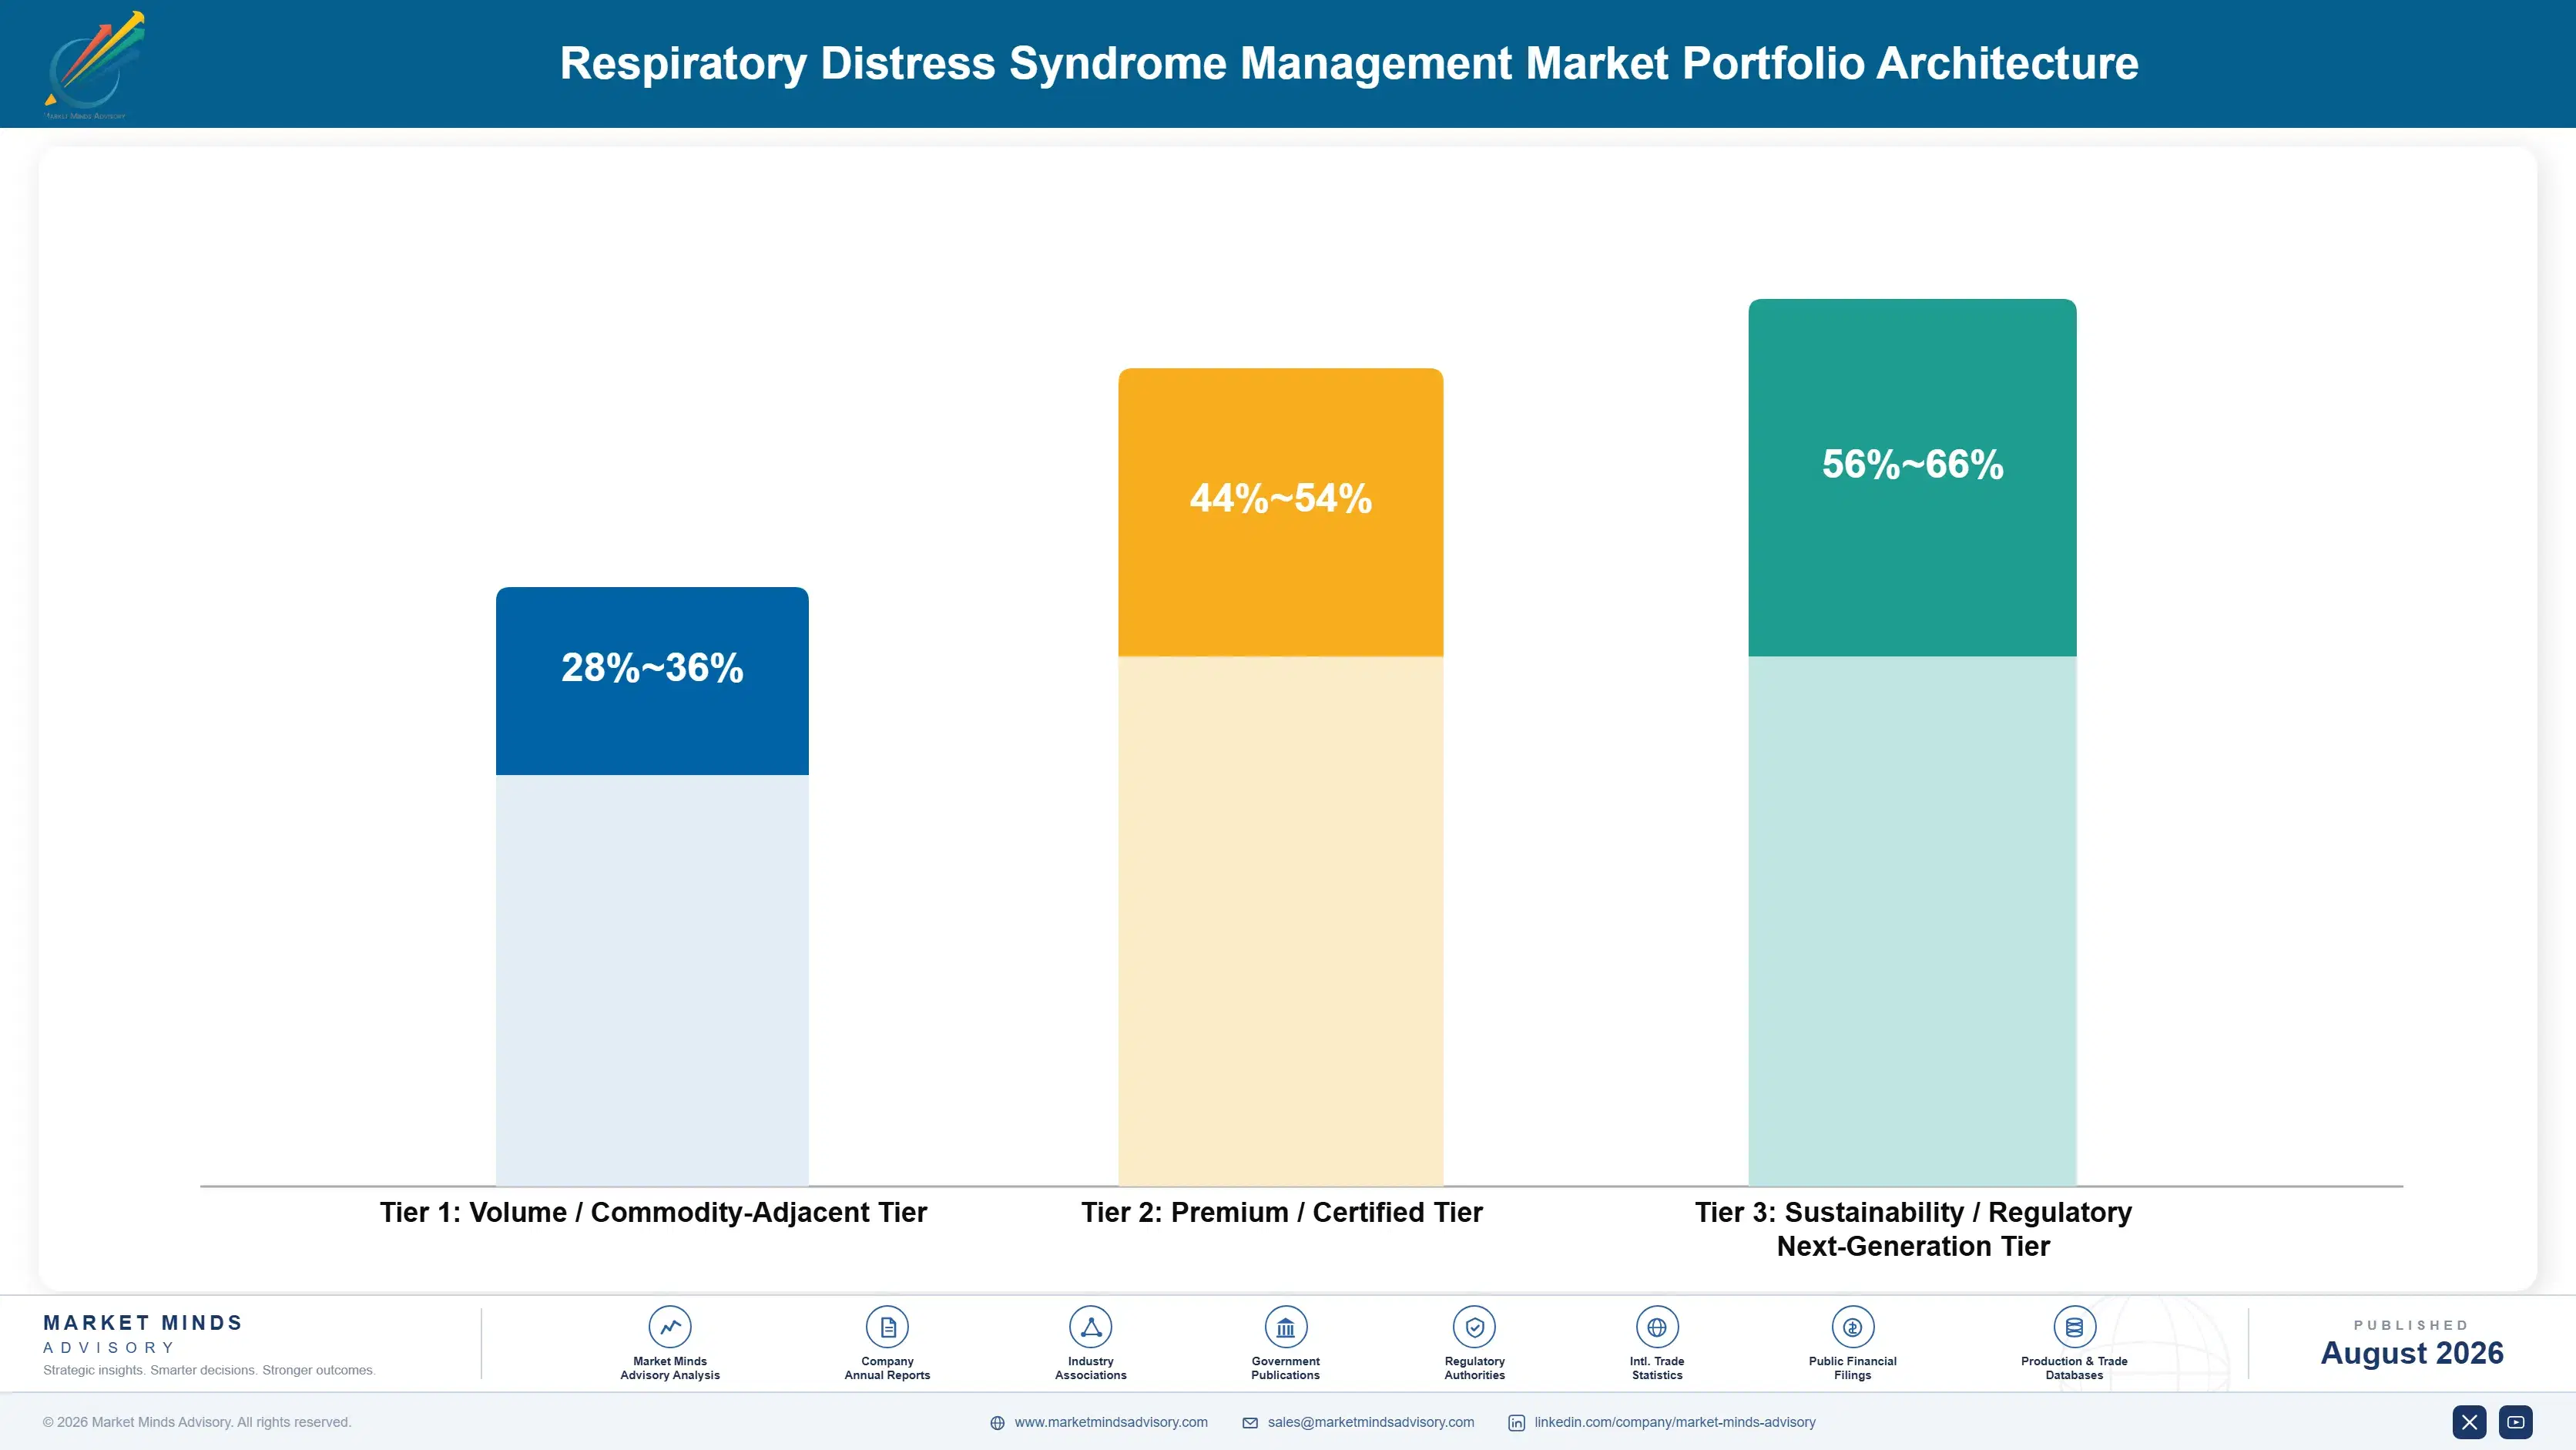
The market organizes into three tiers by treatment modality and margin profile. Volume-tier standard non-invasive ventilation and surfactant therapeutics cover the broadest patient population, sold largely through established hospital relationships. Premium-tier high-flow and extracorporeal systems command meaningfully higher prices tied to severity handling and clinical outcome data. A growing next-generation tier layers remote monitoring support on top of the underlying extracorporeal hardware
Gross margins widen considerably moving up the tiers, since extracorporeal systems carry disproportionate pricing power relative to their incremental manufacturing cost, while standard non-invasive equipment competes primarily on price against a growing field of regional manufacturers. Hospitals rarely downgrade capability once they have built extracorporeal support into their critical care service line. Consumable revenue partially offsets this dynamic for manufacturers with the largest standard-tier installed base.

High-value margin pools concentrate in extracorporeal systems bundled with remote monitoring support subscriptions, where recurring consultation revenue carries substantially wider margin than the underlying equipment sale that first brought the hospital into a vendor's broader relationship. That gap is likely to widen further as extracorporeal capability matures and adoption spreads across most markets. Manufacturers positioned early stand to capture disproportionate share of this margin pool.

Volume / Commodity-Adjacent Tier

Standard non-invasive ventilation and surfactant therapeutics sold largely through established hospital relationships, competing primarily on price with limited room for premium differentiation beyond basic performance. Established relationship pricing determines most of the margin outcome for this tier's manufacturers.
Gross Margin: 28-36%

Premium / Certified Tier

High-flow nasal cannula and advanced monitoring systems carrying stronger clinical outcome credentials and severity handling capability, commanding meaningfully wider margins than standard equivalents. Hospitals increasingly view these as the appropriate default for broadening severity ranges.
Gross Margin: 44-54%

Sustainability / Regulatory / Next-Generation Tier

Extracorporeal membrane oxygenation systems paired with remote monitoring support subscriptions, representing the newest category and commanding the highest margins in the market given their severity handling advantage. Vendors are racing to expand this offering as capability spreads to more facilities.
Gross Margin: 56-66%
respiratory-distress-syndrome-management-portfolio-architecture-1787306727238

High-value Sub-segments and Strategic Watch-out

Extracorporeal Systems With Remote Monitoring Support

Extracorporeal systems paired with remote monitoring support combine the category's fastest growth with its widest margins, drawing concentrated vendor investment as smaller hospitals increasingly seek this capability without building extensive in-house perfusionist expertise. MMA expects vendor investment here to keep climbing steadily through 2036 nationally.
Gross Margin: 58-68%

High-Flow Nasal Cannula Systems

High-flow nasal cannula systems deliver strong unit growth on the back of expanding clinical guideline endorsement, though margins sit a tier below extracorporeal systems, supported by broadening adoption across both neonatal and adult critical care settings. Growth should persist as clinical guideline endorsement continues expanding across settings.
Gross Margin: 46-56%

Standard Non-Invasive Ventilation Systems

Standard non-invasive ventilation systems remain the category's volume backbone across established hospital relationships worldwide, competing on price that leaves thin margins and limited room for feature differentiation beyond humidification quality. Consolidation among smaller manufacturers looks likely as scale becomes key to survival. across most account types worldwide.
Gross Margin: 26-34%

Legacy Animal-Derived Surfactant Formulations

Legacy animal-derived surfactant formulations warrant monitoring as synthetic alternatives gain clinical acceptance, a dynamic that could compress this once-standard therapeutic category considerably faster than smaller manufacturers currently plan for in their own portfolios. Vendors that diversify into synthetic formats early could offset this segment's continued softness.
Gross Margin: 38-46%

Modality Progression and Facility Depth

Equipment and therapeutics generate recurring revenue through consumable attachment and modality upgrades far more than through any single treatment course, since hospitals typically progress through multiple respiratory support tiers as facility capability matures, giving manufacturers an annuity-like revenue stream tied to the institutional relationship rather than a single transaction. That recurring revenue stream typically compounds further as facilities add consumable and service layers ov
Adoption depth varies considerably by end-use vertical. Academic medical centers adopt the newest extracorporeal and monitoring capability fastest and often serve as reference sites manufacturers use to influence broader community hospital purchasing patterns, while smaller hospitals typically wait for remote monitoring support options before committing to advanced capability at meaningful scale. Smaller hospitals sit closer to community-focused facilities than to academic centers in the speed of their own adoption.

Buyer profiles are shifting generationally as younger neonatologists and critical care physicians who trained during the non-invasive-first era show far greater comfort deferring intubation than an older cohort that historically defaulted to earlier mechanical ventilation before considering less invasive alternatives first. This generational shift is accelerating protocol changes at the fastest-moving academic training programs worldwide.
respiratory-distress-syndrome-management-end-use-penetration-index-1787306727729

Positioning for the Non-Invasive Shift

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / EXTRACORPOREAL CAPABILITY STRATEGY

Vendors without extracorporeal offerings will lose share to full-portfolio rivals

Extracorporeal membrane oxygenation systems command meaningfully higher pricing and growth momentum than standard non-invasive equipment, and vendors without a competitive extracorporeal offering risk losing consideration entirely as hospitals expand their own severity handling capability. This gap is widening as more community hospitals build this capability, and delayed action here carries real commercial cost. Companies that close this gap early stand to capture disproportionate share of the fastest-growing segment before rankings solidify further., and that delay carries real commercial consequence given how quickly rankings can shift once capability spreads.
02 / REMOTE SUPPORT SERVICE INVESTMENT

Remote support will open access for smaller hospitals unable to adopt otherwise

Smaller hospitals without in-house perfusionist expertise represent a meaningful underserved market, and vendors offering remote monitoring support convert this capability gap into both new adoption and recurring consultation revenue. This opportunity is widening as extracorporeal capability spreads beyond the largest academic centers, and delayed investment in service capability carries real commercial cost. Companies that build this capability early stand to capture disproportionate share of this underserved segment., and that delay carries real commercial consequence as capability continues spreading beyond academic centers each year.
03 / GUIDELINE RELATIONSHIP DEPTH

Clinical protocol alignment will separate manufacturers positioned to capture volume

Clinical guideline endorsement determines which treatment modality reaches meaningful volume more than device performance data alone does, and manufacturers without strong guideline relationships increasingly lose prescribing consideration to competitors already aligned with updated protocols. This gap is widening as more professional societies update treatment algorithms favoring non-invasive approaches, and delayed guideline engagement carries real commercial cost. Companies that invest in this relationship early stand to capture disproportionate prescribing share., and that delay carries real commercial consequence as more societies formalize updated treatment algorithms nationwide.
04 / FULL-PORTFOLIO ACCOUNT DEPTH

Modality upgrade positioning will separate account leaders from single-tier sellers

Manufacturers with a full modality portfolio spanning non-invasive through extracorporeal systems capture larger account share as hospitals expand their own capability tier by tier, and vendors limited to a single modality increasingly lose expansion purchases to competitors offering the full severity spectrum. Companies still selling only non-invasive equipment risk losing the entire upgrade relationship to rivals who already hold the extracorporeal conversation with that hospital's purchasing committee. That gap widens further as more hospitals consolidate purchasing under a single vendor relationship.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Respiratory Distress Syndrome Management Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Respiratory Distress Syndrome Management Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a regional hospital network operating eight facilities across the southern United States, including one academic-affiliated teaching hospital and seven community hospitals. The network reported approximately $2.2 billion in annual revenue (client-reported, unverified by MMA) and managed roughly 850 respiratory distress syndrome cases annually across its neonatal and adult critical care service lines.
STRATEGIC CHALLENGE
The network's seven community hospitals lacked extracorporeal membrane oxygenation capability, requiring costly and clinically risky transfers to the network's single academic facility for the most severe cases, and leadership lacked clear data on whether building this capability regionally would meaningfully improve outcomes relative to the investment required. Leadership needed clear data before committing scarce capital to new equipment and staff training.
MMA APPROACH
MMA benchmarked transfer-related outcome data and cost impact across three peer hospital networks with distributed extracorporeal capability against the client's current single-center model, incorporating remote monitoring support cost estimates from two leading vendors. The analysis modeled projected outcomes over a five-year forward planning horizon under two capability expansion scenarios. Interviews with critical care staff supplemented the desk-based financial and outcome analysis.
KEY FINDINGS
  1. Distributing extracorporeal capability to two additional facilities was projected to reduce transfer-related delays by roughly 60% for severe cases. This projection held across multiple patient acuity scenarios evaluated in the model.
  2. Remote monitoring support costs were considerably lower than building equivalent in-house perfusionist staffing at each new facility. This pattern held consistently across every comparable network MMA reviewed.
  3. Two of the network's largest community hospitals already had sufficient critical care infrastructure to support this capability with modest investment. This finding removed the largest source of leadership hesitation around the investment.
  4. Peer networks with distributed capability reported meaningfully improved severe case outcomes compared to single-center transfer models. Faster access to care meaningfully improved outcomes documented across peer institutions.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1-3): Complete facility readiness assessment and vendor evaluation across the two priority hospitals. under close coordination with network finance leadership. Phase 2: Phase 2 (Months 4-9): Install extracorporeal capability with remote monitoring support at the first priority facility. with outcome tracking built into the pilot design. Phase 3: Phase 3 (Months 10-16): Expand to the second facility based on initial outcome and utilization data. with ongoing transfer rate monitoring built in.
OUTCOME
The network installed extracorporeal membrane oxygenation capability at two community hospitals using a remote monitoring support partnership for specialist consultation. Projected annual transfer cost savings reached approximately $3.8 million (client-reported, unverified by MMA) against the prior single-center baseline across the network's full critical care service line.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Respiratory Distress Syndrome Management Market?

The Respiratory Distress Syndrome Management Market was valued at approximately $3.2 billion globally in 2025. This includes surfactant therapeutics, non-invasive ventilation, and extracorporeal support systems.

How large will the Respiratory Distress Syndrome Management Market be by 2036?

The market is projected to reach approximately $6.4 billion by 2036, roughly 1.88 times its 2026 value. Growth is driven by non-invasive protocol adoption and expanding extracorporeal support access.

What is the CAGR for the Respiratory Distress Syndrome Management Market 2026 to 2036?

The base case CAGR is 6.5% annually, with a bull case of 7.8% and a bear case of 5.2%. This reflects steady clinical protocol shifts alongside rising preterm birth rates in key markets.

Which segment is growing fastest?

Extracorporeal membrane oxygenation support systems are the fastest-growing segment, expanding at roughly 11.0% annually. This capability is expanding beyond academic centers into broader community hospital networks.

Who are the major companies in the Respiratory Distress Syndrome Management Market?

Leading companies include Chiesi Farmaceutici, Drägerwerk, Getinge, Fisher & Paykel Healthcare, and Vyaire Medical. Together these five manufacturers hold 58% of global revenue in this market.

Which country is growing fastest?

India is the fastest-growing country, expanding at roughly 8.5% annually through 2036. This reflects the country's exceptionally high preterm birth burden and expanding neonatal care access.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Treatment Modality and Product Type

  • Natural and Synthetic Surfactant Therapeutics
  • Non-Invasive Ventilation Systems
  • High-Flow Nasal Cannula Systems
  • Respiratory Monitoring Devices
  • Extracorporeal Membrane Oxygenation Systems

By End-Use Population

  • Neonatal Intensive Care
  • Adult Critical Care
  • Pediatric Intensive Care
  • Academic Medical Centers

By Commercial Dimension

  • Outright Purchase
  • Leasing and Financing
  • Service Contract Attachment
  • Remote Monitoring Subscription

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The Respiratory Distress Syndrome Management Market covers pulmonary surfactant therapeutics, non-invasive ventilation systems, high-flow nasal cannula devices, respiratory monitoring equipment, and extracorporeal membrane oxygenation support used specifically to manage neonatal and acute respiratory distress syndrome. It excludes general invasive mechanical ventilators and chronic pulmonary disease management devices sold as separate product categories.
Quantitative Units
USD billions (current prices); treated patient volume where applicable
Segmentation Dimensions
By Treatment Modality and Product Type; By End-Use Population; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Thailand, Malaysia, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Chiesi Farmaceutici SpA, Drägerwerk AG & Co KGaA, Getinge AB, Fisher & Paykel Healthcare Corporation, Vyaire Medical Inc, ResMed Inc, Philips Respironics, Medtronic plc, Becton Dickinson and Company, Smiths Medical Inc, Hamilton Medical AG, Masimo Corporation, Nihon Kohden Corporation, Zoll Medical Corporation, Aerogen Ltd, Vapotherm Inc, Armstrong Medical Ltd, Inspiration Healthcare Group plc, Bunnell Incorporated, AbbVie Inc
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-141
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Respiratory Distress Syndrome Management Market Report (2026 to 2036).

The full report delivers detailed segmentation across all five treatment modality categories, with country-level sizing for all thirty-one covered markets. It profiles the complete competitive landscape of all twenty companies named in this summary, including moat and risk analysis for the two leading manufacturers. Multi-year forecast models are provided under base, bull, and bear scenarios. Primary survey data drawn from neonatologists, critical care physicians, and hospital procurement executives across six countries supports every major finding, and purchasers receive editable data files alongside the formatted report.
Extracorporeal capability expansion tracker by country
Non-invasive protocol guideline adoption tracking monitor
Preterm birth rate and patient pool forecast model
Remote monitoring support partnership benchmark database
Consumable circuit attachment revenue tracking model
Competitive benchmarking across key respiratory care manufacturers

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts