Market Minds Advisory
Pediatric Home Healthcare Market

Pediatric Home Healthcare Market: Where Clinical Outcome Tracking Becomes the Binding Constraint

Pediatric home healthcare providers are shifting capital from standard private duty staffing toward remote patient monitoring integration, as families and payers specify validated clinical outcome tracking ahead of visit frequency for medically complex children.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$15.6BMarket Size 2025
2036 FORECAST VALUE$37.9BBase Case , 2026 to 2036
CAGR 2026 TO 20368.4 %Bull 9.7% / Bear 7.1%
INCREMENTAL OPPORTUNITY$21.0BNet 10- year value creation
EXPANSION MULTIPLE2.24x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Clinical outcome tracking, not visit frequency, is now the binding constraint on provider selection. Agencies that cannot deliver validated remote monitoring integration lose ordering care coordinators to faster-adopting competitors, pushing payers to specify proven outcome documentation capability before selecting a home care partner for a medically complex child today.
Remote patient monitoring and telehealth services are pulling the market forward fastest, as clinical outcome tracking adoption accelerates faster than any other service category worldwide. North America holds the largest share of global demand, anchored by the depth of its home healthcare reimbursement infrastructure and payer density, while South Asia and Pacific grows fast as India's expanding pediatric home care infrastructure scales rapidly across major metropolitan healthcare corridors and family care networks.
Home healthcare majors are consolidating pipelines through targeted acquisitions rather than large mergers, as established agencies add remote monitoring capability ahead of competitors still relying on standard visit-only output. Competitive pressure is intensifying as regional agencies undercut established brands on price for standard home care supply, while tightening clinical documentation certification requirements push smaller agencies to invest in compliance infrastructure they previously avoided across the wider industry.
Market Definition
The pediatric home healthcare market covers skilled nursing home care services, private duty and personal care services, durable medical equipment and home infusion services, remote patient monitoring and telehealth services, physical, occupational, and speech therapy home services, and respiratory and ventilator support services delivered to medically complex children in the home setting. It excludes adult home healthcare services, inpatient pediatric hospital care, and unrelated pediatric outpatient clinic services delivered outside the home.
Base Year Value
$15.6B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
8.4% base case. Bull 9.7%. Bear 7.1%.
Fastest Growth Segment
Remote Patient Monitoring and Telehealth Services: 13.6% CAGR
Fastest Growth Country
India: 11.4% CAGR
Fastest Growth Region
South Asia and Pacific: 10.4% CAGR
Largest Region
North America: 31% of 2025 global value
Market Leaders
Aveanna Healthcare Holdings Inc., BAYADA Home Health Care, Amedisys, Inc., Elara Caring, Enhabit Home Health & Hospice. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

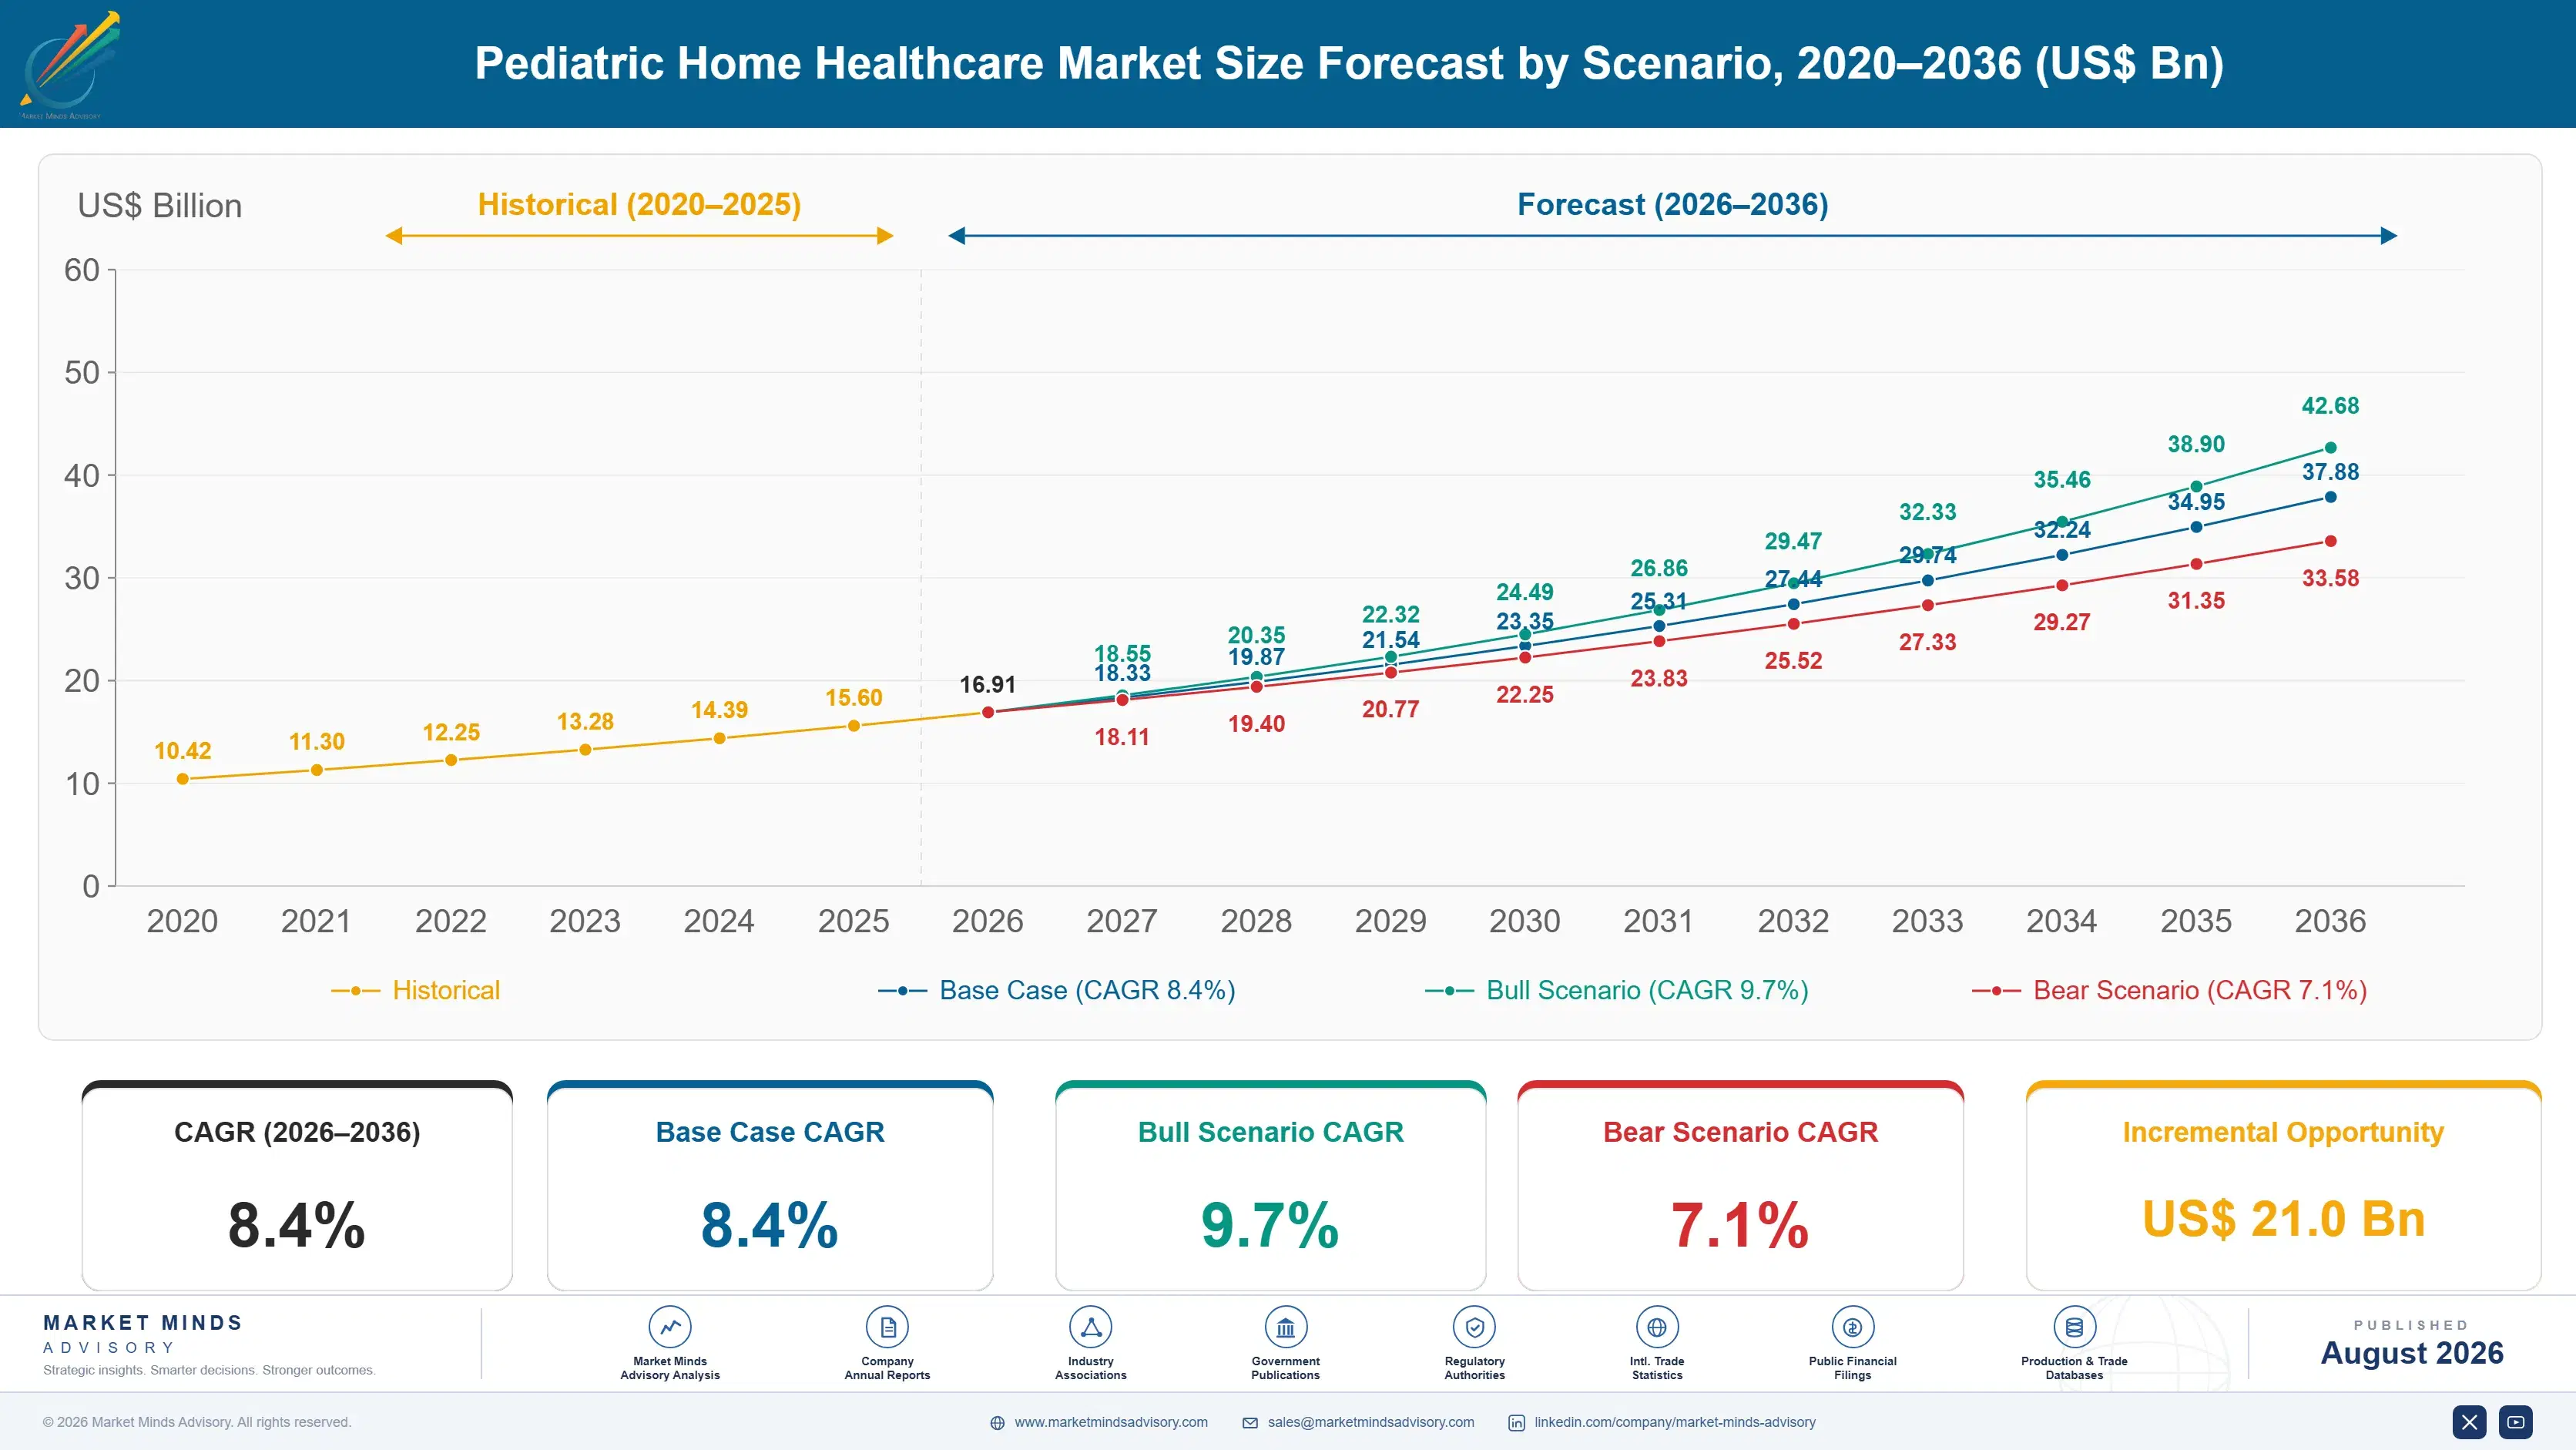
Pediatric Home Healthcare Market Forecast Scenarios

pediatric-home-healthcare-market-size-forecast-scenario-1787305619248
Between 2020 and 2025 the market grew at roughly 7.8% a year, accelerating sharply as hospital capacity constraints pushed payers to secure validated home-based care capability ahead of inpatient bed availability. Clinical documentation certification requirements introduced during these years pushed agencies toward validated quality systems, pulling compliant agencies ahead of competitors still running manual visit-only tracking.
The base case carries the market to 37.9 billion dollars by 2036 on three mechanisms. First, remote monitoring adoption is converting standard visit-only care into certified, higher-margin outcome-tracked platforms across most home healthcare networks. Second, North American home healthcare reimbursement infrastructure is scaling faster than the traditional less-developed access base that historically limited global pediatric home care access. Third, pediatric home care investment in India is creating service demand that did not previously exist at scale.
The bull case reaches roughly 9.7% annual growth if remote monitoring adoption accelerates faster than currently planned and home healthcare infrastructure expands ahead of schedule. The bear case falls near 7.1% if service demand growth slows on macroeconomic headwinds and agencies defer certification upgrades to manage capital budgets during periods of weaker home care investment nationwide across major pediatric hubs.

Where Clinical Outcome Tracking Becomes the Binding Constraint

Pediatric home healthcare used to be a straightforward staffing decision made mostly on catalog availability and visit schedule; now payers specify agency partners against documented clinical outcome reliability and validated monitoring consistency before initiating care for a newly discharged medically complex child. Every agency must demonstrate a measurable outcome improvement rate a care coordinator can verify against established benchmarks. That performance decides which agency wins a care
MARKET CONCENTRATION (CR5)28%Top five providers hold about a quarter of volume
AVERAGE SELLING PRICEUSD 185 per home visitBlended price across nursing and therapy visit categories
TOP PRODUCING COUNTRY SHAREUSA, 46% of global revenueLargest single national source of home care revenue
REMOTE MONITORING PENETRATION17% of patients enrolledShare of patients enrolled in remote monitoring programs
TRADE INTENSITY6% cross-borderAbout a seventeenth of revenue crosses national borders
FEEDSTOCK COST SHARE34% of cost of goods soldShare of production cost attributable to clinical staffing inputs
Commercially the market behaves like a specialty clinical services business wearing a basic staffing label. Clinical staffing cost is the dominant share of unit price; the outcome validation and quality infrastructure investment required to substantiate an outcome improvement claim drives most of the value premium agencies actually capture. Payers rarely switch agency partners once an agency clears their procurement qualification review, since switching means restarting a lengthy requalification process against an unproven alternative vendor.
The next decade turns on three forces: remote monitoring adoption converting standard visit-only care into certified outcome-tracked platforms, North American home healthcare infrastructure scaling ahead of less-developed access bases, and pediatric home care investment in India creating service demand that did not previously exist. Agencies positioned across all three will set the pace, while visit-only specialists fall behind.
"A home care agency that can't prove which visit actually moved the outcome isn't a care partner, it's a billing line the payer will eventually question. That's why documented outcome tracking has become the real conversation starter."
Director, Pediatric and Home Health Services Practice · MMA Healthcare - Home Ca

Market Trends

Remote Monitoring Programs Gain Broad Adoption

Remote patient monitoring and telehealth programs engineered to document validated clinical outcome tracking and consistent visit-efficiency performance have moved from specialized pilot programs into standard care protocols across respiratory, infusion, and complex-care categories. Payers now request documented outcome certificates and traceable monitoring records before selecting an agency partner for a medically complex child, converting what was once a differentiating premium feature into a baseline procurement requirement undifferentiated visit-only agencies can no longer avoid. That specification shift has compressed the timeline agencies have to build accredited clinical evidence before losing payer contracts to better-prepared competitors already holding recognized certification.
Market Impact: Adds demand from 68,000 discharged
North American Reimbursement Scale Reshapes Access

The depth of North America's home healthcare reimbursement infrastructure and payer density has scaled remote monitoring access far faster than less-developed care markets over the past five years, converting the region into the world's largest single source of both payer contracts and specialty care capacity as reimbursement investment continues expanding at scale. That access growth has let regional agencies win multi-year payer relationships directly from families that previously relied exclusively on visit-only care. Other regions are responding by expanding regional clinical trial capacity and investing more heavily in certified monitoring technology that North American agencies cannot yet replicate.
Market Impact: Adds 740 payers to compliance track

Market Opportunities and Growth Drivers

Hospital Capacity Growth Expands Home Care Demand

New hospital capacity constraints and discharge acceleration across South Asia, East Asia, and Latin America is creating home care demand that did not previously exist at meaningful commercial scale, since each new discharged child requires a complete initial specialized home care infrastructure before treatment can even begin at all. That access-driven demand behaves differently from replacement demand in mature markets, since new payers specify care protocols fresh rather than working around existing visit-only relationships built over years. Agencies with established regional distribution are capturing that new-access demand directly from global competitors still building equivalent regional infrastructure.
Market Impact: Cuts agency margins by 6 points

Clinical Documentation Policy Raises Validation Standards

Updated clinical documentation certification requirements from national and regional regulatory bodies have raised the certified outcome and safety threshold agencies must demonstrate before payers will approve continued procurement across most jurisdictions. That policy tightening has pulled a much broader share of payer capital budgets toward certified outcome-tracked supply, since procurement auditors increasingly flag uncertified visit-only agencies as a compliance risk during routine coverage reviews. Agencies with established clinical evidence and regulatory infrastructure are capturing that expanding compliance-driven budget directly from competitors still relying on legacy specifications that predate current documentation requirements.
Market Impact: Delays care access by 3 weeks

Market Restraints and Challenges

Clinical Staffing Cost Volatility Pressures Margins

Clinical staffing inputs, the base cost driver for most pediatric home healthcare services, have experienced sharp wage swings tied to specialty nursing labor markets, and that volatility has squeezed agency margins that payer procurement contracts typically fix for multi-year terms without adjustment clauses. The root cause is that most procurement contracts were negotiated before volatility became a persistent feature of specialty nursing labor markets, leaving agencies exposed to cost increases they cannot pass through until renewal. Some agencies are responding by negotiating shorter procurement terms with price adjustment clauses tied to published wage indices.
Market Impact: Cuts hospital readmission by 21%

Skilled Pediatric Nursing Capacity Limits Access Speed

Certified pediatric nursing workforce capacity remains limited relative to the pace of rising complex-care demand, and agencies serving multiple simultaneous payer qualifications face real capacity constraints whenever several major health systems require certified staffing infrastructure within the same coverage window. The root cause is that workforce training investment has not scaled as fast as procedural demand, so agencies compete directly for a limited pool of certified pediatric nurses across most regions. That capacity constraint creates real access delay risk for families working against fixed discharge windows. Some agencies are responding by investing in additional training capacity.
Market Impact: Shifts service demand 12% toward As
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows care service type, a single classification logic that groups pediatric home healthcare demand by the clinical delivery architecture an agency uses rather than by which diagnosis eventually receives the finished care plan. Each service type carries its own certification pathway, staffing requirement, and reimbursement structure, so commercial position tracks the service type rather than the clinical diagnosis.
pediatric-home-healthcare-market-market-share-analysis-1787305619781

Remote Patient Monitoring and Telehealth Services

Remote patient monitoring and telehealth services grow fastest at 13.6%, about 1.62 times the overall market rate, as clinical outcome tracking adoption accelerates faster than any other service category worldwide. Large payers and specialty home care networks dominate current commercial volume, valued for certified outcome reliability and documented monitoring data that families and payer quality teams increasingly require before approving continued reimbursement. The segment commands premium pricing relative to standard visit-only services, reflecting both the specialized technology investment involved and the certification testing agencies have made to support specific outcome claims. Agencies with early monitoring investment are winning premium payer contracts directly from competitors still relying on standard visit-only output that payers increasingly reject during procurement review.
CAGR 13.6%

Respiratory and Ventilator Support Services

Respiratory and ventilator support services grow second-fastest at 10.8%, driven by expanding demand for complex-care capability among medically fragile children that requires certified clinical reliability documented at meaningful commercial scale across a growing range of home care settings. The category uses specialized respiratory therapy technology engineered for consistent complex-care delivery compared with standard nursing visits that carry comparatively narrower clinical scope. Growth concentrates specifically among high-acuity and complex-case applications, where clinical requirements and expanding payer quality standards increasingly favor certified respiratory support over standard nursing alternatives previously deemed the only viable option. Agencies with validated respiratory certification are winning specification directly from competitors whose offerings lack comparable certified performance history.
CAGR 10.8%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Demand concentrates where home healthcare reimbursement infrastructure and payer density intersect, which currently means North America rather than any single Asian source. The depth of North America's reimbursement pipeline and payer density keeps the region largest, even as East Asia supplies meaningful volume through its own expanding pediatric care investment.

North America

North America holds the largest regional share at 31%, anchored overwhelmingly by the depth of its home healthcare reimbursement infrastructure and payer density, which enables families to access certified remote monitoring care earlier and more completely than in most other regions. Aveanna and BAYADA both maintain established regional distribution and clinical support infrastructure serving the continent's deepest pediatric and specialty care referral base directly. American payers benefit from decades of established reimbursement pathways and validated procurement protocols that specify certified outcome-tracked care as standard practice across most home healthcare networks. Growth of 9.4% outpaces the overall market rate as expanding home care access and reimbursement mandates continue pulling capital toward certified care capacity across major pediatric hubs.
Share: 31% | CAGR: 9.4% (2026 to 2036)

Western Europe

Western Europe accounts for 23% of value, a mature base shaped by some of the world's most established public healthcare reimbursement infrastructure and specialty procurement sophistication anywhere. Amedisys and Elara Caring both run substantial European-adjacent distribution and clinical support operations, positioned to serve the continent's increasingly standardized referral framework under national health service and pediatric care regulation. Regulatory scrutiny over safety confirmation and outcome documentation runs notably stricter here than in less-regulated markets, pushing agencies toward extensively documented, evidence-backed certification from the outset of any care program launch. Growth of 6.8% trails the global rate directly because the region's specialty home care market, while sophisticated, is growing more slowly than the newer care programs scaling across Asian markets.
Share: 23% | CAGR: 6.8% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
pediatric-home-healthcare-market-country-cagr-analysis-1787305620298

Where Home Healthcare Agencies Capture Premium Value

Selling pediatric home healthcare on generic visit-only volume alone leaves the highest-margin part of this market on the table. The four moves below shift revenue toward positions that command a premium over standard visit-only supply: certified outcome documentation, regional clinical trial localization, specialty nursing capacity investment, and long-term payer supply contracts that smaller competitors cannot easily replicate quickly.

Invest In Certified Outcome Documentation Systems

Agencies that invest in certified clinical outcome documentation and quality testing capability, rather than relying on generic visit records for every patient, capture a documented pricing premium of roughly 15% to 26% from payers that increasingly require certified outcome tracking and safety data before approving continued procurement. That documentation investment costs real money and takes time to build, but it converts a generic care claim into agency-specific, defensible quality evidence competitors relying on slower documentation cannot match on speed. Aveanna and BAYADA have both built specialty certification support programs to capture this premium ahead of smaller regional competitors.
Market Impact: Captures a 15% to 26% certified pri

Expand Clinical Validation Capacity For Certified Access

Agencies that invest in dedicated clinical validation capacity for certified monitoring coordination, rather than allocating generic staffing resources to payer procurement, capture faster care turnaround and reduced access delay risk that increasingly matters to payers managing fixed discharge windows against tight procurement timelines. That capacity investment typically captures 13% to 23% more coverage reimbursement value than competitors relying on shared generic resources, since payers weight coordination reliability alongside quality data when qualifying agencies for multi-year coverage. Agencies with established dedicated validation networks are winning coverage renewals directly from competitors still facing capacity allocation constraints across major procurement cycles.
Market Impact: Captures 13% to 23% more coverage r

Localize Clinical Validation Closer To Family Hubs

Agencies that build regional clinical validation capacity closer to major population and family referral hubs, rather than concentrating validation at centralized national testing centers, capture faster outcome certification and reduced qualification burden that increasingly matter to payers managing tight procurement timelines. That localized capacity typically captures 10% to 18% more procurement value than centralized validation models, since health systems increasingly weight access reliability alongside quality data when qualifying agencies for multi-year procurement contracts. Agencies with established regional validation footprints are winning procurement renewals directly from competitors still relying on distant centralized facilities with longer wait times.
Market Impact: Captures 10% to 18% more procuremen

Offer Long-Term Payer Coverage Support Contracts

Agencies that offer long-term payer coverage support contracts, rather than billing visits on a one-time transactional basis, capture recurring revenue that funds clinical validation and quality investment competitors dependent on inconsistent one-time billing cannot easily match. That contract structure typically captures 11% to 20% more lifetime payer value than transactional billing, since predictable recurring reimbursement reduces payer acquisition cost pressure and lets agencies invest further ahead of near-term billing results across the business. Agencies with established long-term contract programs are winning renewals directly from competitors billing visits without any ongoing payer support relationship in place today.
Market Impact: Captures 11% to 20% more lifetime p

Who Controls the Margin Pool

Concentration sits at a modest CR5 of 28%, split between diversified home healthcare majors with broad service reach and specialized remote monitoring operators with narrower but deeper clinical service expertise. The gap between the top five and the next tier is real but moderate: leaders combine certification depth with established payer infrastructure, while challengers typically compete only on standard visit-only supply. All participants are assessed on one basis: disclosed revenue.
Competition today runs across three dimensions. First, certified outcome tracking depth, since an agency with published quality data wins payer contracts competitors relying on unverified claims cannot match. Second, regional service capability, as agencies with localized clinical infrastructure can offer coordination speed competitors relying on distant facilities cannot sustain. Third, nursing workforce integration, since agencies with captive staffing infrastructure capture payer loyalty competitors reliant on fragmented networks cannot access.

Pressure is building from regional agencies that have closed much of the certification gap on standard access while undercutting national incumbents on price. Regional specialists are pushing into premium certified territory, competing directly against established agencies on certification positioning. Rankings will shift toward agencies who pair certification depth with genuine nursing workforce integration, since neither alone wins the largest payer relationships.
pediatric-home-healthcare-market-company-positioning-matrix-1787305620814

Competitive Moat and Risk Dimensions

AVEANNA HEALTHCARE HOLDINGS INC.

Moat: Broad Certified Care Portfolio

Aveanna operates one of the industry's most extensive pediatric home care portfolios, spanning nursing, therapy, and remote monitoring categories that smaller specialized agencies cannot replicate without years of comparable clinical investment. That portfolio breadth lets Aveanna win multi-category payer contracts that competitors selling single-format services alone cannot credibly compete for on convenience.
AVEANNA HEALTHCARE HOLDINGS INC.

Risk: Broad Focus Limits Innovation Speed

Aveanna's broad home healthcare portfolio means pediatric specific innovation investment competes internally against dozens of other care categories for capital and management attention, limiting how quickly it can respond to emerging remote monitoring specification trends. Specialized monitoring-focused competitors can move faster on innovation, potentially capturing premium payer contracts before Aveanna's broader portfolio can respond.
BAYADA HOME HEALTH CARE

Moat: Deep Payer Relationship Expertise

BAYADA operates decades-deep pediatric home care specific technical expertise spanning clinical protocol, quality assurance, and outcome monitoring practice, generating a trusted payer channel that smaller unknown developers cannot replicate without comparable relationship investment over many years. That depth lets BAYADA secure pilot payer relationships and expedited procurement review that competitors without established trust cannot credibly access.
BAYADA HOME HEALTH CARE

Risk: Premium Pricing Limits Budget Reach

BAYADA's premium pricing structure limits its addressable base among budget-constrained payers willing to sacrifice brand recognition for lower-cost visit-only alternatives offering comparable functional performance. As price-sensitive payers expand faster than premium segments across the home healthcare pipeline, BAYADA risks ceding volume growth to competitors better positioned on price.

Players Tracked

Prominent Players

Aveanna Healthcare Holdings Inc.
BAYADA Home Health Care
Amedisys, Inc.
Elara Caring
Enhabit Home Health & Hospice

Other Key Players

LHC Group, Inc.
Addus HomeCare Corporation
Interim HealthCare Inc.
Angels of Care Pediatric Home Health
Care Options for Kids
Thrive Skilled Pediatric Care
Pediatric Home Service
BrightSpring Health Services
Trinity Health At Home
CenterWell Home Health
Option Care Health, Inc.
National HealthCare Corporation
Preferred Home Health Care & Nursing Services
Almost Family Inc.
Kindred at Home

Recent Developments

MARCH 2025

Aveanna Expands Certified Remote Monitoring Service Network

Aveanna announced expanded specialized service partnerships for its certified remote monitoring program, adding dedicated coordination support to serve accelerating payer demand for validated outcome protocols. The organic expansion, not a joint venture or acquisition, followed three years of rising payer demand for certified care support nationwide.
Signal: Signals established home healthcare majors
SEPTEMBER 2024

BAYADA Acquires Regional Validation Specialist

BAYADA completed the acquisition of a regional clinical validation testing specialist for an undisclosed sum, adding dedicated outcome certification capacity to its existing home healthcare business. The deal gives BAYADA direct validation capability it previously accessed only through third-party testing agreements with outside contract partners.
Signal: Signals large home care producers increasi
JUNE 2025

Amedisys and an Indian Home Care Group Form Service Partnership

Amedisys and a major Indian home care testing group formed a partnership to supply certified remote monitoring services and quality coordination for the group's expanding payer network. The partnership targets deployment across several new care centers within three years, combining Amedisys's certification expertise with the partner's regional testing scale.
Signal: Signals global home healthcare suppliers i

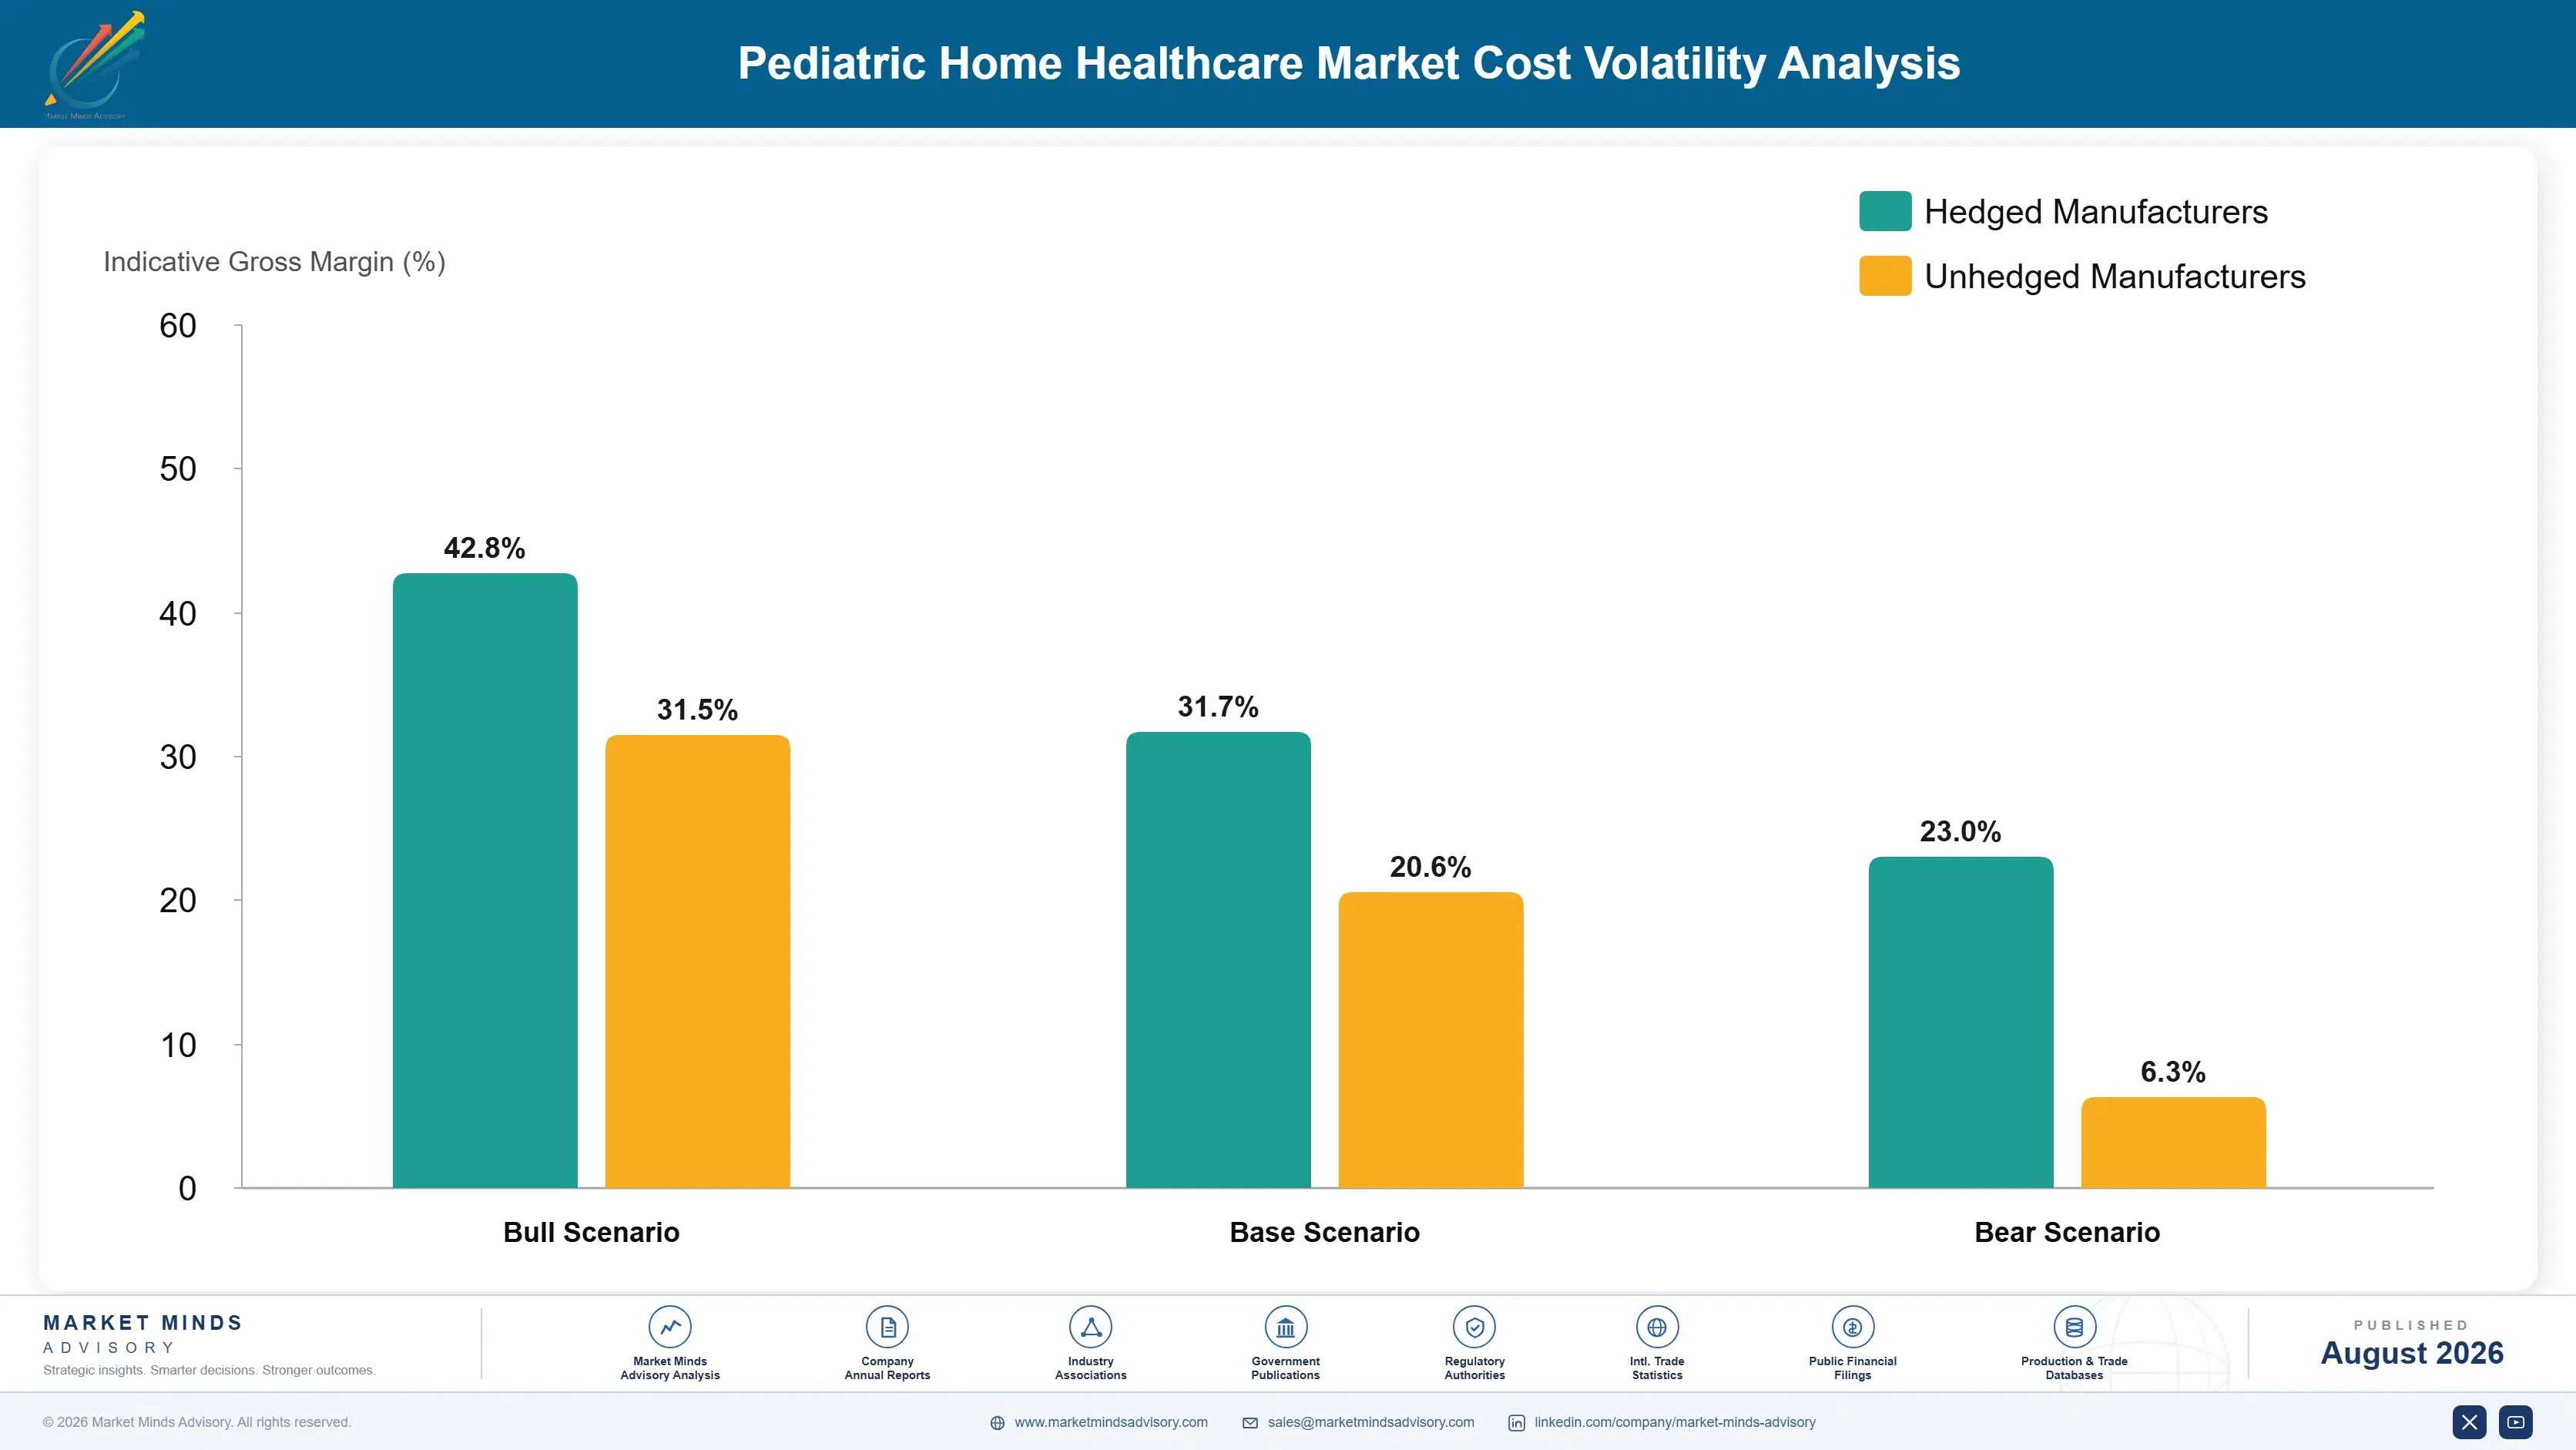
Clinical Staffing Cost Exposure

Clinical staffing inputs make up roughly 32% to 40% of cost of goods sold across pediatric home healthcare delivery, well above conventional service economics, since certified pediatric-grade nursing credentials and background testing limit supply to a smaller number of qualified providers. Labor costs trace to global specialty nursing labor market pricing, while certification costs track credentialing and regulatory supply cycles.
The 2021 to 2022 supply constraint illustrated the exposure directly. Industry data recorded specialty nursing labor costs reaching multi-year highs through 2022 as pandemic-era healthcare workforce disruption affected pediatric nursing supply capacity broadly across most regions. Aveanna's 2022 Annual Report disclosed elevated labor and recruitment costs across its home healthcare workforce, attributing margin pressure partly to wage volatility that took several quarters to ease meaningfully.

Smaller regional agencies without long-term staffing agreements absorbed the wage spike hardest, since their hiring volumes were too small to secure the favorable compensation packages that larger agencies like Aveanna and BAYADA negotiate directly with nursing labor markets. That gap compounds: large agencies can pre-recruit staffing capacity months ahead using resources smaller competitors lack, leaving regional specialists exposed every time a labor cycle repeats.
pediatric-home-healthcare-market-cost-volatility-analysis-1787305621010

Secure Multi-Year Staffing Retention Agreements

Negotiating multi-year staffing retention agreements directly with clinical workforce pools, rather than relying on the spot labor market, secures staffing priority during shortage cycles and smooths wage volatility. The approach requires committing to workforce forecasts years in advance, a real forecasting risk, but it has protected larger agencies' margins through two labor constraint cycles since 2020.

Diversify Staffing Sourcing Across Regions

Qualifying more than one regional staffing pool for key nursing inputs, rather than relying on a single labor market, reduces exposure to any single workforce disruption or allocation decision during a shortage. Requalification takes real credentialing time, so agencies are prioritizing it for their highest-volume care lines first before extending diversified sourcing across their full portfolio over time.

Pass Through Cost Via Indexed Pricing

Structuring payer procurement contracts with wage-indexed pricing clauses, rather than fixed long-term pricing, shifts some cost exposure to payer buyers who absorb labor volatility through periodic price adjustments tied to published wage indices. Agencies have increasingly negotiated indexed pricing structures to protect margin on multi-year contracts while still offering price predictability during periods of stable labor cost.

Portfolio Architecture for Margin Defence

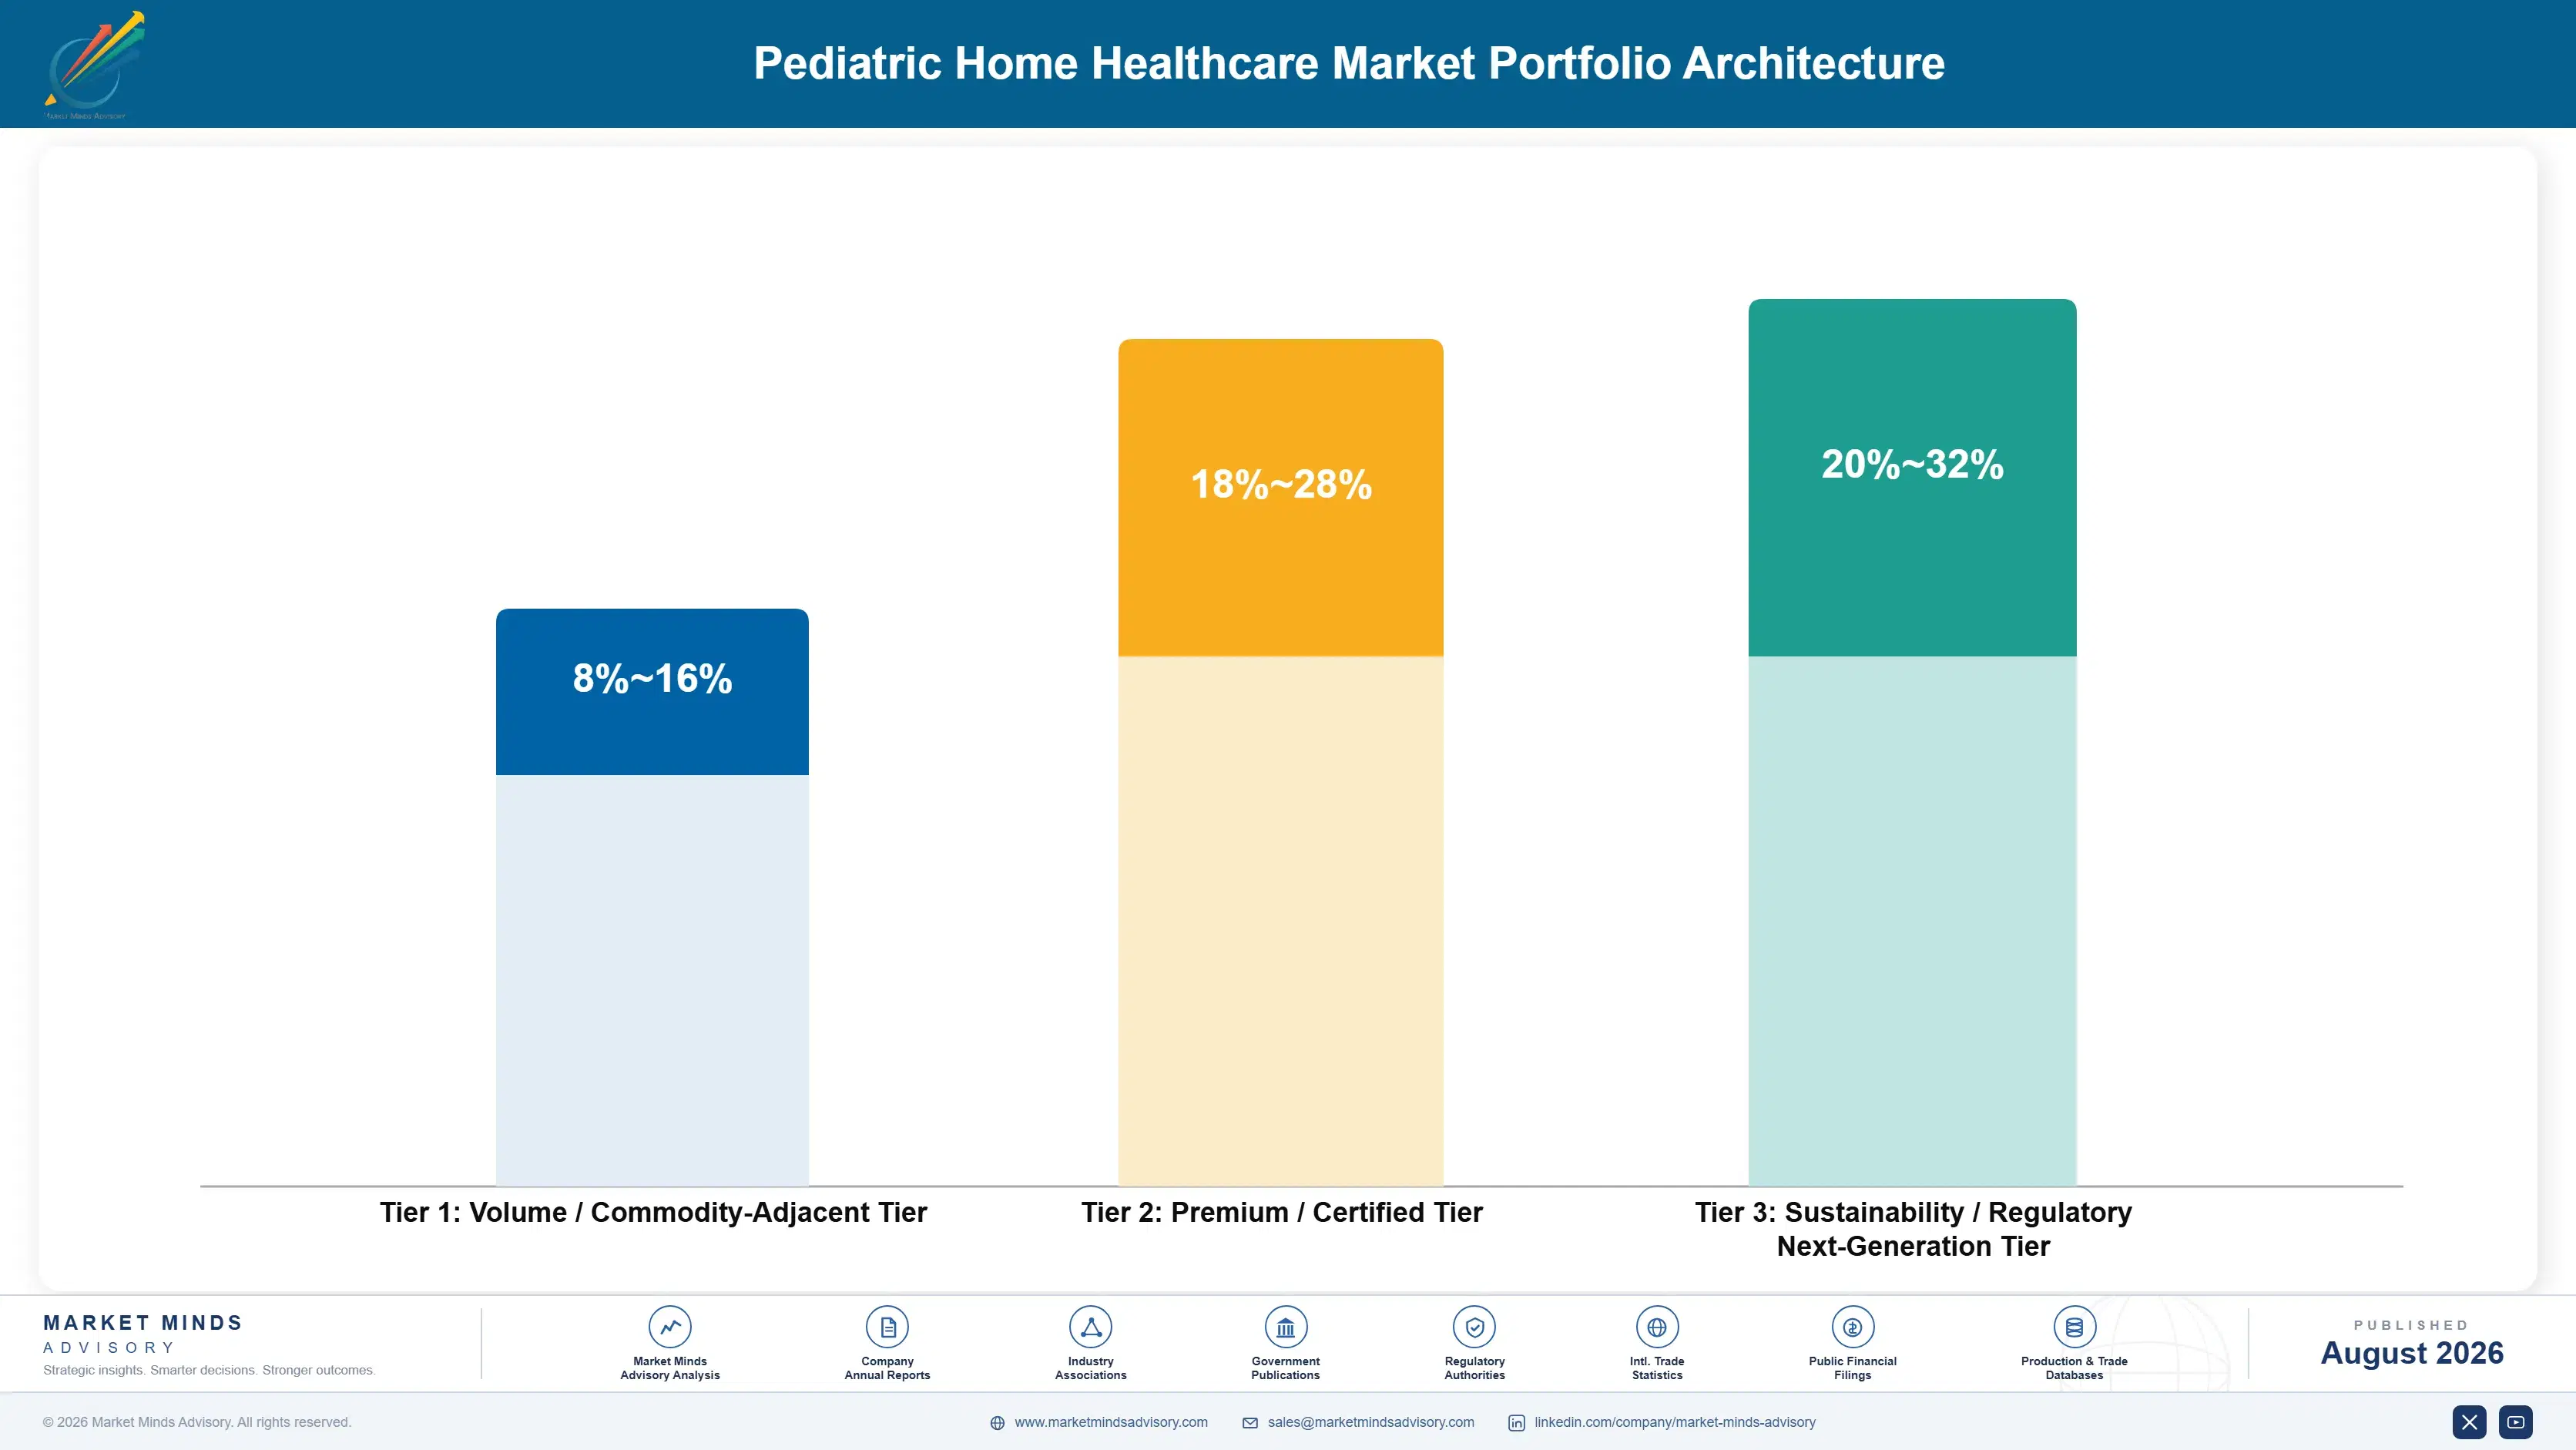
The portfolio splits into three tiers with wide margin separation tied to certification depth and clinical evidence sophistication rather than raw staffing cost alone. Standard visit-only services sold on price and basic protocol carry thin margins. Certified respiratory and remote-monitoring formulations backed by published outcome data carry the strongest margins. A third tier of next-generation AI-assisted and predictive-care formulations is still scaling toward proven, repeatable commercial
The tension between commodity access and premium certified care shapes how agencies allocate capital: visit-only sales fund the installed-base scale and distribution reach that make premium services attractive to sell against, while certification programs fund the clinical validation investment and quality engineering that create genuine competitive protection. Agencies that lean too far toward commodity access risk losing the certification depth that differentiates them; those leaning too far toward premium risk under-utilized standard installed-base capacity.

High-value pools concentrate specifically in respiratory and remote-monitoring formulations, where technical barriers and payer switching costs both run highest. Standard visit-only services used in general primary care generate volume but thin, price-competitive margins, since multiple agencies can supply functionally similar services against the same basic specification.

Volume / Commodity-Adjacent Tier

Standard visit-only services sold against several regional agencies competing primarily on price, delivery time, and basic specification across large routine primary care commodity orders placed year round across most payer distribution channels nationwide.
Gross Margin: 8-16%

Premium / Certified Tier

Certified respiratory and remote-monitoring formulations backed by published outcome data and accreditation certification that payers increasingly require before approving a new agency for any program-wide coverage deployment use across the network.
Gross Margin: 18-28%

Sustainability / Regulatory / Next-Generation Tier

Next-generation AI-assisted and predictive-care formulations still scaling toward proven, repeatable commercial economics across a broad and varied payer customer base of different application requirements and coverage thresholds right now nationwide.
Gross Margin: 20-32%
pediatric-home-healthcare-market-portfolio-architecture-1787305621516

Why Certification Locks In Payers

Demand here behaves like an annuity once an agency wins a payer's procurement qualification approval, because a payer rarely switches away from a qualified monitoring provider given the lengthy requalification process an unproven alternative would require. An agency that wins the original qualification typically retains that relationship for years of continuous coverage, converting an initial procurement win into a recurring, largely captive care relationship.
Adoption depth varies sharply by payer type. Large commercial insurers and specialty Medicaid programs switch procurement relationships rarely, given the extensive review involved in adopting a new care system and the perceived clinical risk of an unproven alternative, which makes their relationships the stickiest in the market. Smaller regional payers treat procurement decisions more like a commodity choice and switch partners more readily on price, giving them real negotiating leverage large payers typically do not exercise.

Buyer profiles are shifting generationally too. A newer cohort of care coordination leaders, trained under stricter post-pandemic outcome-tracking and evidence-based standards, now weighs an agency's certification depth and evidence transparency as heavily as price, a shift that favors agencies with genuine clinical capability over generic care providers competing purely on catalog volume.
pediatric-home-healthcare-market-end-use-penetration-index-1787305622060

Where MMA Sees This Market Heading

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / CERTIFICATION TESTING PREMIUM

Documented outcome data will separate winners from unverified suppliers

Agencies with credible, documented clinical outcome and quality certification data will keep winning payer procurement and multi-year contract relationships regardless of price, because care coordinators increasingly demand proof before committing to an agency rather than accepting unverified generic claims. Agencies without that certification depth will increasingly compete only on commoditized price against services facing genuine credibility risk in an increasingly scrutinized payer procurement environment. Expect continued investment in certification testing infrastructure as unverified agencies race to close the evidence gap before payers stop covering their programs entirely.
02 / NORTH AMERICAN REIMBURSEMENT SCALE

North America's share keeps growing as remote monitoring access expands

North America already holds the largest regional share at 31% and grows near the top of its band as the depth of its reimbursement infrastructure pulls payers toward the region at real, sustained pace year after year across every category tracked. Domestic American agencies are closing the certification and evidence gap with less-developed markets faster than most industry observers expected just a few years ago. Multinationals that fail to build direct North American payer relationships risk losing the single largest volume opportunity in the entire global market.
03 / REGIONAL VALIDATION CAPTURE

Localized clinical validation will command real premium over centralized testing

Agencies who build genuine regional clinical validation capability will capture the certification speed and procurement reliability premium that payers increasingly weight alongside quality data when selecting agencies for multi-year coverage relationships nationwide. The approach commands genuine margin precisely because it removes the approval uncertainty centralized-testing competitors would otherwise pass on to payers managing tight procurement windows from scratch and at real cost. Expect regional validation capability to become standard practice across the entire top agency tier well within the ten-year forecast window.
04 / SPECIALIZED SERVICE ADVANTAGE

Dedicated coordination capacity will keep separating credible agencies from unverified ones

Agencies who invest in genuine dedicated service coordination will keep winning trust-sensitive payers that unverified competitors simply cannot reach once outcome and access scrutiny intensifies across the broader market nationwide. That coordination depth commands genuine commercial value precisely because it removes performance-uncertainty risk payers would otherwise have to bear themselves when selecting an unverified or uncertified agency outright. Expect coordination capacity depth to become a standard differentiator across the entire top agency tier well within the ten-year forecast window that lies ahead.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Pediatric Home Healthcare Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Pediatric Home Healthcare Exposure Evaluation 2025-26
CLIENT PROFILE
A regional managed care payer covering a pediatric Medicaid population approached MMA while evaluating whether to consolidate its home healthcare agency network ahead of a planned coverage expansion. The client reported annual care and service spend near USD 45 million across six separate agencies, with growing coverage exposure tied to inconsistent outcome documentation across its existing agency network (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
Management knew consolidating the agency network would reduce coverage exposure and support the expansion but worried about disrupting existing family relationships during the transition and whether a phased consolidation approach could maintain care continuity. The clinical team wanted immediate consolidation; the member services team worried about disruption; and payer leadership needed a clear risk mitigation plan before committing.
MMA APPROACH
MMA benchmarked network consolidation practices and outcome documentation across comparable regional managed care payers, modeled the coverage risk and continuity reduction a phased consolidation could realistically deliver, and quantified the exposure the client faced without prioritizing its highest-risk care pathways first. We also assessed which of three candidate agencies held certification depth sufficient to support the expansion.
KEY FINDINGS
  1. Inconsistent outcome documentation across two existing agencies was creating measurable coverage exposure, flagged during a recent internal procurement audit review (client-reported, unverified by MMA).
  2. A phased consolidation prioritizing the highest-risk care pathways first could reduce coverage exposure meaningfully within the first seven months while limiting disruption to existing family relationships.
  3. One of the client's three candidate agencies already held certification depth sufficient to support the coverage expansion without requiring an entirely new qualification process.
  4. Comparable regional managed care payers that phased their network consolidation saw measurably lower coverage denials than payers pursuing simultaneous system-wide replacement across all agencies at once.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 3 months): Audit existing agency network outcome documentation and identify the highest-risk pathways across all six agencies. Phase 2: Phase 2 (3 to 9 months): Consolidate the highest-risk care pathways first while maintaining full care continuity throughout the transition. Phase 3: Phase 3 (9 to 15 months): Extend the standardized care protocol across remaining agencies ahead of the planned coverage expansion.
OUTCOME
The client completed its phased consolidation within fourteen months and supported its planned coverage expansion without any care continuity incidents. Coverage denials declined meaningfully following consolidation, and the client reported avoided costs worth roughly USD 3.2 million in the following year from reduced coverage denials and improved agency negotiating position (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Pediatric Home Healthcare Market?

The market stood at USD 15.6 billion in 2025, spanning nursing, personal care, equipment, monitoring, therapy, and respiratory categories. Remote patient monitoring and telehealth services are the fastest-growing segment within that base.

How large will the Pediatric Home Healthcare Market be by 2036?

The market is projected to reach USD 37.9 billion by 2036 under the base case scenario. That represents roughly 2.24 times the 2026 value of USD 16.9 billion.

What is the CAGR for the Pediatric Home Healthcare Market 2026 to 2036?

The base case CAGR is 8.4% annually through 2036. The bull case reaches 9.7% on faster remote monitoring adoption growth, while the bear case falls to 7.1%.

Which segment is growing fastest?

Remote patient monitoring and telehealth services grow fastest at 13.6% annually, well ahead of conventional visit-only categories. That pace is roughly 1.62 times the overall market growth rate through 2036.

Who are the major companies in the Pediatric Home Healthcare Market?

Aveanna, BAYADA, Amedisys, Elara Caring, and Enhabit lead the market on disclosed segment revenue worldwide, ahead of fifteen other named competitors profiled in the full report.

Which country is growing fastest?

India grows fastest among all countries at 11.4% annually, ahead of other major Asian home healthcare markets. Growth is driven by expanding pediatric home care infrastructure and specialty nursing access.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Care Service Type

  • Skilled Nursing Home Care Services
  • Private Duty/Personal Care Services
  • Durable Medical Equipment and Home Infusion Services
  • Remote Patient Monitoring and Telehealth Services
  • Physical/Occupational/Speech Therapy Home Services
  • Respiratory and Ventilator Support Services

By End-Use Payer

  • Medicaid and Government Programs
  • Private Commercial Insurance
  • Managed Care Organizations
  • Self-Pay Families
  • Employer-Sponsored Health Plans

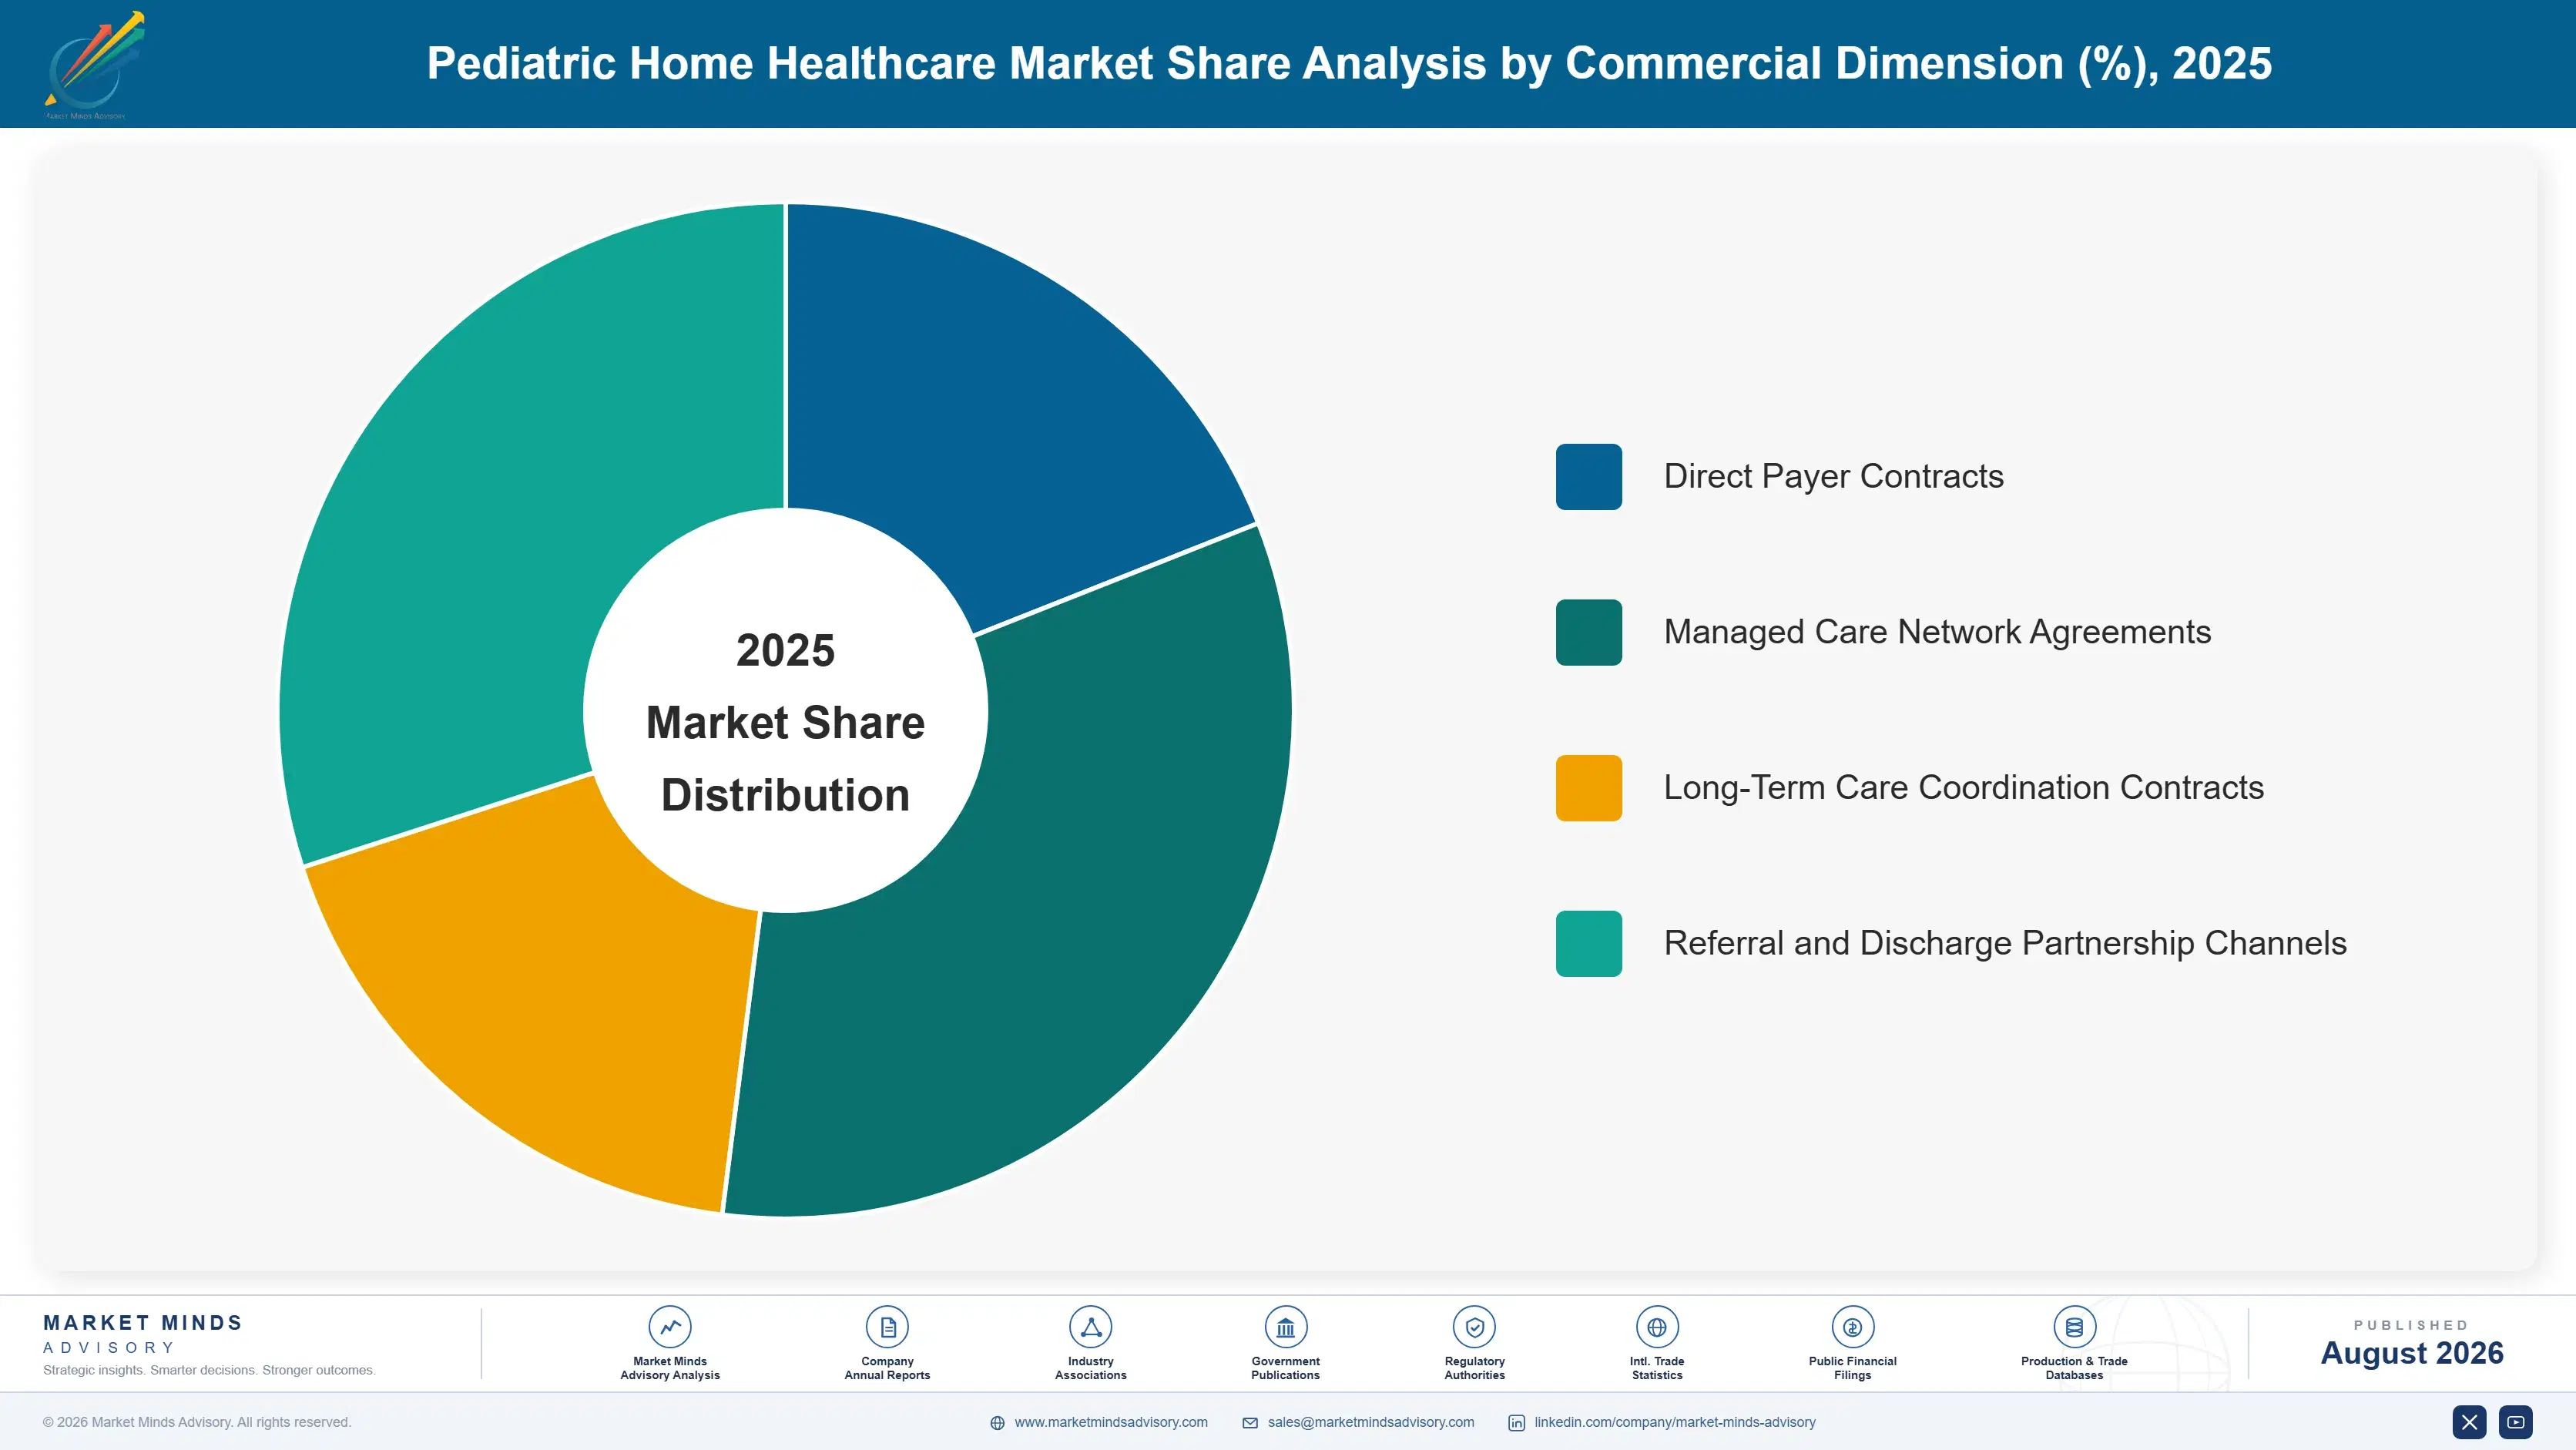
By Commercial Dimension

  • Direct Payer Contracts
  • Managed Care Network Agreements
  • Long-Term Care Coordination Contracts
  • Referral and Discharge Partnership Channels

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The pediatric home healthcare market covers skilled nursing home care services, private duty and personal care services, durable medical equipment and home infusion services, remote patient monitoring and telehealth services, physical, occupational, and speech therapy home services, and respiratory and ventilator support services delivered to medically complex children in the home setting. It excludes adult home healthcare services, inpatient pediatric hospital care, and unrelated pediatric outpatient clinic services delivered outside the home.
Quantitative Units
USD billions (current prices); million home visits delivered where applicable
Segmentation Dimensions
By Care Service Type; By End-Use Payer; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Saudi Arabia, UAE, South Africa, Nigeria, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Aveanna Healthcare Holdings Inc., BAYADA Home Health Care, Amedisys, Inc., Elara Caring, Enhabit Home Health & Hospice, LHC Group, Inc., Addus HomeCare Corporation, Interim HealthCare Inc., Angels of Care Pediatric Home Health, Care Options for Kids, Thrive Skilled Pediatric Care, Pediatric Home Service, BrightSpring Health Services, Trinity Health At Home, CenterWell Home Health, Option Care Health, Inc., National HealthCare Corporation, Preferred Home Health Care & Nursing Services, Almost Family Inc., Kindred at Home
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-230
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Pediatric Home Healthcare Market Report (2026 to 2036).

The full MMA Pediatric Home Healthcare report sizes the market across six service types, five payer categories, four commercial models, and seven regions through 2036. It profiles 20 agencies on a consistent basis of disclosed segment revenue, scoring each on certified outcome tracking depth, regional clinical trial capability, and nursing workforce integration. Scenario models quantify how remote monitoring adoption, North American reimbursement scale, and clinical documentation certification policy move both demand and realizable pricing. The report also includes clinical staffing cost modeling by category, a certified quality investment framework across major service types, and a regional clinical trial feasibility model built for clinical, payer, and care coordination strategy teams.
Six-category segmentation with cross-tabulated regional demand data
Twenty-agency competitive benchmarking on consistent revenue basis
Certified quality investment framework across major service types
Clinical staffing cost and sourcing exposure modeling by category
Scenario forecasts through 2036 under bull and bear cases
Case study on regional managed care payer network consolidation

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts