Market Minds Advisory
Obesity-Related Malnutrition Nutrition Market

Obesity-Related Malnutrition Nutrition Market: Obesity-Related Malnutrition Nutrition Market. GLP-1 Muscle Risk, Bariatric Deficiencies, and Clinic Channels Shape Nutrition Support Returns.

Obesity-related malnutrition nutrition turns on GLP-1 drug users losing muscle and micronutrients, bariatric surgery deficiency risks, clinician recommendation channels, protein and iron supply costs, and medical food rules separating clinic products from consumer supplements.

Lead Analyst

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$5.5BMarket Size 2025
2036 FORECAST VALUE$14.2BBase Case , 2026 to 2036
CAGR 2026 TO 20369.0 %Bull 10.3% / Bear 7.7%
INCREMENTAL OPPORTUNITY$8.2BNet 10- year value creation
EXPANSION MULTIPLE2.37x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory.

Obesity-related malnutrition nutrition covers protein, vitamin, mineral and medical nutrition products for people with obesity who lack key nutrients or risk muscle loss, and value depends on drug and surgery volumes, clinician recommendation, product taste and tolerance, and medical food rules. Tolerance decides repeats.
GLP-1 Companion Nutrition Products grows fastest as users of weight loss drugs eat less and need dense protein, iron, B12 and vitamin D to protect muscle and health, while bariatric vitamins and protein-fortified foods still carry much of the volume. North America holds the largest share because American obesity rates, drug use and clinic networks are the deepest. Patients judge taste, tolerance and clinician advice before they reorder.
Competition is concentrated among medical nutrition and consumer health groups: a Swiss nutrition group, an American healthcare group, a French dairy and medical nutrition group, an American direct seller and an Irish nutrition group lead, measured here on estimated obesity-related nutrition sales value, while diet programmes, clinic brands and online sellers fill gaps. Clinician trust, taste and tolerance decide who wins. Telehealth platforms add own brands, so clinic contracts, evidence and tolerance data protect share.
Market Definition
The market covers global sales of nutrition products marketed to prevent or treat nutrient gaps and muscle loss in people with obesity, valued at brand level, including GLP-1 companion nutrition products, clinic-supplied medical nutrition products, bariatric vitamin and mineral formulas, protein-fortified foods and beverages, and vitamin D, iron and B12 repletion products, sold through clinics, pharmacies, online and retail channels. The scope excludes weight loss drugs, meal replacement diet programmes without a nutrient-support claim, sports nutrition and infant formula.
Base Year Value
$5.5B in 2025 (MMA Primary Research Dataset, September 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
9.0% base case. Bull 10.3%. Bear 7.7%.
Fastest Growth Segment
GLP-1 Companion Nutrition Products: 12.6% CAGR
Fastest Growth Country
Saudi Arabia: 11.0% CAGR
Fastest Growth Region
South Asia and Pacific: 11.0% CAGR
Largest Region
North America: 38% of 2025 global value
Market Leaders
Nestlé Health Science, Abbott, Danone, Herbalife, Glanbia. Source: MMA Analysis, company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Obesity-Related Malnutrition Nutrition Market Forecast Scenarios

obesity-related-malnutrition-nutrition-market-size-forecast-scenario-1789958019072
Between 2020 and 2025, obesity-related nutrition grew steadily as bariatric surgery volumes recovered after the pandemic, clinics recognised micronutrient deficiencies in people with obesity, and GLP-1 drugs created a new group with reduced appetite. Protein and vitamin costs rose, so growth was firm but uneven across product types and regions. Telehealth programmes expanded quickly and payers began to discuss coverage.
The base case rests on three commercial mechanisms. First, GLP-1 drug prescriptions keep expanding and clinicians advise protein and micronutrient support to protect muscle and bone. Second, bariatric surgery and clinic programmes create steady demand for vitamins and medical nutrition. Third, food and beverage groups add protein and micronutrients to products aimed at small appetites. Producers plan clinical evidence, taste work and clinic partnerships around these drivers, and buyers reward tolerance and clear guidance.
The bull case needs guideline recommendations for nutrition support alongside weight loss drugs and reimbursement in some markets, which would lift clinic sales. The bear case is weaker drug persistence and price cuts on protein ingredients that reduce premiums, combined with medical food rule changes. Brands with clinical partners, tolerable products and flexible sourcing would be best placed for either outcome.

Clinician Advice, Tolerance, and Protein Cost Set Obesity Nutrition Returns

Producers formulate protein powders, ready-to-drink shakes, chewable vitamins, iron and B12 products and medical nutrition, and sell them through clinics, pharmacies, online stores and retail channels to people with obesity, drug users and surgery patients. About 1 billion people live with obesity, clinics recommend or supply about 30% of sales, and patients are often advised 60 g to 80 g of protein a day. Tolerance and advice therefore set returns.
MARKET CONCENTRATION30% CR5Top five suppliers hold a moderate combined market share
NORTH AMERICA SALES SHARE38%Portion of global sales made in North America
ADULTS LIVING WITH OBESITY1 billionApproximate number of people worldwide living with obesity
DAILY PROTEIN TARGET60-80 gTypical protein advice for patients on weight loss drugs
CLINIC CHANNEL SHARE30%Portion of sales recommended or supplied by clinics
BARIATRIC DEFICIENCY RISK30-60%Share of patients developing nutrient gaps without any supplementation
Clinician recommendation, taste, tolerance, nutrient content and price decide value. Patients judge flavour and comfort, clinicians judge evidence and dose, dietitians judge protein quality, and regulators judge medical food and supplement rules. Nestlé Health Science wins on Optifast and clinic reach, Abbott wins on medical nutrition credibility, and Danone wins on Nutricia expertise. Tolerance failures move repeat rates quickly.
Buyers judge obesity nutrition products on clinician advice, taste, protein per serving, digestive comfort and price. Drug users want small, dense servings, surgery patients want approved formulas, and general dieters want convenience. Price sensitivity is moderate. Clinic staff, online communities and reviews decide shortlists, and many trial buyers stop when shakes taste sweet, cause nausea or feel too heavy for a reduced appetite.
"People on weight loss drugs are eating a third less and many are not eating enough of the right things. The winners will be nutrition brands that clinicians trust, that patients can actually finish, and that do not pretend a shake solves the problem alone."
Senior Analyst, Medical Nutrition and Metabolic Health Practice · MMA Obesity-Related Malnutrition Nutrition Practice · September 2026

Market Trends

GLP-1 Users Need Dense Protein and Micronutrients to Protect Muscle

People taking GLP-1 medicines can lose 25% to 40% of weight as lean mass in some studies, eat less overall and may develop iron, B12 and vitamin D gaps, so clinicians advise protein targets and supplements. GLP-1 Companion Nutrition Products grows about 12.6% a year, and gross margins run 40% to 54% against 28% to 36% for general protein products. The trend needs small dense servings, gentle taste and clinical messaging, and it rewards brands that partner with clinics and telehealth providers. Telehealth providers now include nutrition advice in onboarding, which raises awareness.
Market Impact: US adult obesity reaches about 40%
Clinics and Telehealth Providers Supply Nutrition Alongside Obesity Treatment

Obesity clinics, bariatric centres and telehealth programmes increasingly bundle protein, vitamin and mineral products with prescriptions and counselling, and payers in some markets cover parts of the cost. Clinic-Supplied Medical Nutrition Products grows about 10.8% a year, and gross margins run 36% to 48%. The trend needs clinical files, dietitian support and reliable supply, and it draws medical nutrition groups and telehealth platforms into contracts that guarantee volume. Dietitians in these programmes recommend specific products and track adherence, and brands that supply patient guides and training gain preferred status in each clinic.
Market Impact: 30-60% develop deficiencies without care

Market Opportunities and Growth Drivers

Rising Obesity and Drug Use Create a Large Patient Base

About 1 billion people live with obesity worldwide, and in the United States roughly 40% of adults have obesity, while prescriptions for GLP-1 drugs have grown sharply and patients need guidance on nutrition. Clinics and pharmacies increasingly offer dietitian support. The driver sustains a large, repeat-buying patient base and rewards brands with clinician endorsement, small dense servings and clear labelling. Employers, insurers and health systems begin to fund nutrition counselling alongside drugs, and pharmacies stock dedicated shelves for patients, which raises visibility and repeat purchase among patients new to these products.
Market Impact: adherence under 50% after six months

Bariatric Surgery Guidelines and Deficiency Awareness Create Predictable Lifelong Demand

Guidelines from bariatric societies advise lifelong vitamin and mineral supplementation after surgery, and studies show that 30% to 60% of patients can develop deficiencies without it. Clinics prescribe iron, B12, folate, calcium and vitamin D. The driver creates predictable repeat demand and rewards brands with bariatric-specific formulas, chewable formats and dietitian support that improve adherence. Follow-up visits monitor blood levels of iron, B12 and vitamin D, so clinicians adjust doses and patients receive repeated prompts to renew, and chewable and liquid formats improve adherence after surgery for patients who struggle with large tablets.
Market Impact: whey costs rise 30-50% yearly

Market Restraints and Challenges

Poor Tolerance, Taste Fatigue, and Low Adherence Limit Nutrition Use

Patients on weight loss drugs or after surgery often experience nausea, early fullness and taste changes, so many stop using shakes and supplements. The root cause is altered digestion and appetite. Brands respond with smaller servings, neutral flavours and chewable formats, though adherence often falls below 50% after six months and reformulation costs $1 million to $4 million per range. Clinicians report that patients drop shakes first and vitamins second, and poor adherence leads to deficiencies that need blood tests and injections, which raises costs and opens a path for comfortable products.
Market Impact: companion products grow 12.6% yearly

Medical Food Rules, Reimbursement Gaps, and Protein Costs Squeeze Margins

Products sold through clinics may need medical food or special purpose status, and most payers do not reimburse nutrition for obesity, so patients pay out of pocket. The root cause is separate classification and limited evidence for outcomes. Brands respond with clinic partnerships and evidence programmes, though whey protein costs can rise 30% to 50% in a year and reduce margins. Consumer brands avoid medical claims to escape strict rules, while clinic brands invest in evidence, so the market splits between low-cost retail products and higher-priced clinic products when payers refuse coverage.
Market Impact: clinic-supplied products grow 10.8% yearly
3 additional market trends, 2 additional growth drivers, and 4 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

The global obesity-related malnutrition nutrition market is segmented by product type, which shows where clinician trust, tolerance and evidence create pricing power in a moderately concentrated market. Five segments cover GLP-1 companion nutrition, clinic-supplied medical nutrition, bariatric vitamin and mineral formulas, protein-fortified foods and beverages, and vitamin D, iron and B12 repletion products. Companion and clinic products grow fastest.
obesity-related-malnutrition-nutrition-market-market-share-analysis-1789958019351

GLP-1 Companion Nutrition Products

GLP-1 Companion Nutrition Products is the fastest-growing segment at 12.6% a year, about 1.40 times the overall market rate, from a small base. Users of weight loss drugs eat less and need dense protein, iron, B12 and vitamin D, so gross margins of 40% to 54% against 28% to 36% for general protein products support clinical work and marketing spend. Tolerance and taste are the main constraints, and brands that offer small, dense servings, neutral flavours and clinician guidance win repeat purchase through clinics, pharmacies and online subscriptions. Telehealth platforms linked to drug prescribers promote companion products in onboarding, and subscription sales lift retention for patients who reorder monthly. Reorders are steady.
CAGR 12.6%

Clinic-Supplied Medical Nutrition Products

Clinic-Supplied Medical Nutrition Products grows at 10.8% a year, about 1.20 times the overall market rate, because clinics, bariatric centres and telehealth providers bundle nutrition with treatment and brands accept gross margins of 36% to 48% for products with clinical files. Dietitian support and reliable supply shape entry. Brands with medical food status, clinician training and patient programmes hold price better than consumer brands, and clinic contracts create steadier volume. Bariatric centres and obesity clinics recommend specific brands, and dietitians track adherence and blood markers, so brands that supply clinician guides, patient education and reliable delivery keep accounts for years. Medical food rules and payer coverage vary by country, which favours groups with regulatory teams and clinical partners.
CAGR 10.8%
Full segment breakdown across 5 segments available in the complete report.

Regional Architecture and Country Demand Map

North America leads at 38% because American obesity rates, weight loss drug use and clinic networks are the deepest, with Western Europe at 22% on medical nutrition. South Asia and Pacific grows fastest as Indian obesity and diabetes rates rise. East Asia and Eastern Europe trail.

North America

North America holds 38% share, above its band, because American obesity rates, GLP-1 prescriptions, bariatric surgery volumes and telehealth programmes are the largest in the world, and clinics and pharmacies recommend products from Nestlé Health Science, Abbott, Premier Protein and specialist bariatric brands, which justifies the out-of-band share and puts it far ahead of other regions. Growth runs at the global rate. Payer gaps, tolerance and protein costs shape returns. Telehealth platforms, obesity clinics and bariatric centres recommend products, and Costco, Walmart, Amazon and pharmacies stock companion shakes and vitamins. State medical rules, payer gaps and the FDA supplement framework shape claims, and protein cost swings and private label pressure constrain premium growth.
Share: 38% | CAGR: 9.0% (2026 to 2036)

Western Europe

Western Europe holds 22% share, inside its band, because German, British, French and Italian clinics and dietitians recommend medical nutrition and bariatric vitamins, and Fresenius Kabi, Danone Nutricia and Nestlé Health Science hold strong positions, while EU rules on foods for special medical purposes and supplements set labels. Growth trails the global rate. Reimbursement limits, claims rules and private label pressure restrain returns. Bariatric centres in Germany, the United Kingdom, France and Italy recommend vitamin and mineral formulas, and hospital dietitians supply medical nutrition products in some health systems. National reimbursement differs by country, EU rules on foods for special medical purposes set labels and claims, and Nordic clinics adopt companion products quickly, while price pressure limits premium brands.
Share: 22% | CAGR: 7.5% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
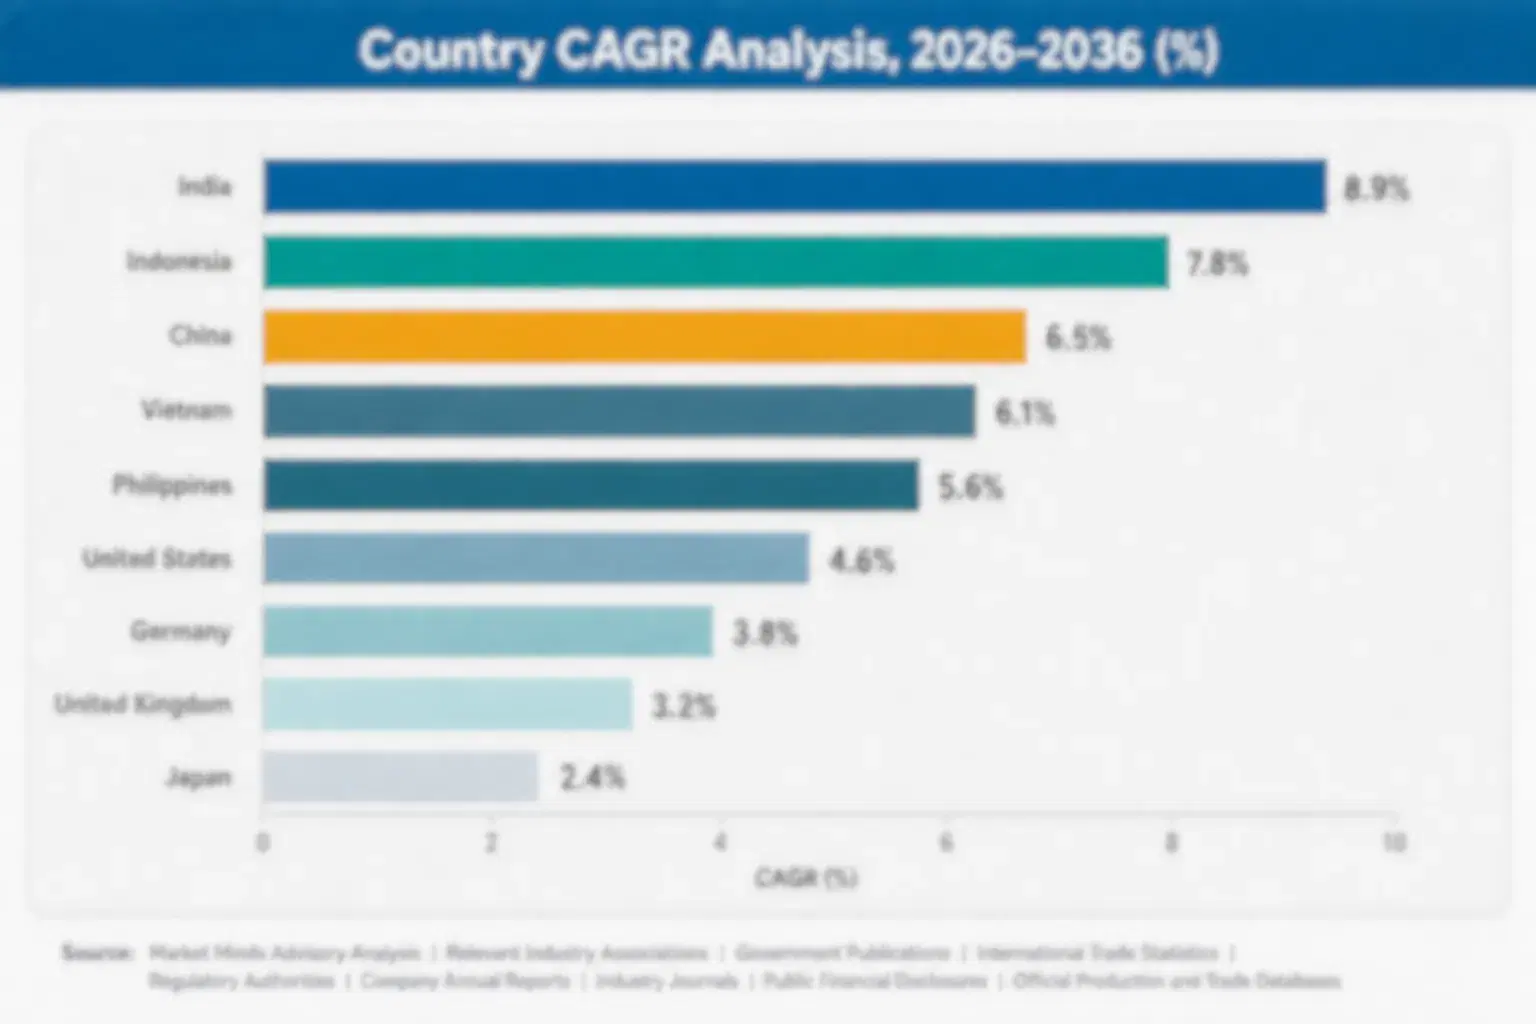
obesity-related-malnutrition-nutrition-market-country-cagr-analysis-1789958019671

Four Margin Routes for Obesity Nutrition Brands

Margin in obesity-related nutrition comes from GLP-1 companion products, clinic partnerships, tolerable formats and secure protein supply rather than plain protein powder volume. The routes below apply to medical nutrition groups, consumer brands and ingredient suppliers, and each can start inside one planning cycle, with clear measures in gross margin points, clinic accounts and repeat purchase.

Shifting General Protein Volume Into GLP-1 Companion Nutrition Products

GLP-1 companion products earn gross margins of 40% to 54% against 28% to 36% for general protein products, so brands that add small dense servings, iron, B12 and vitamin D and gentle flavours to shift 10% of volume into companion ranges report gross margin gains of three to five points on the mix. Programmes cost $8 million to $25 million. Pilots with five clinics and two telehealth providers confirm demand, and payback typically arrives within 30 months as prescriptions grow. Retailers and pharmacies give companion products dedicated shelf space when clinic demand grows.
Market Impact: companion mix shift lifts gross margin by 3-5 points

Building Clinic and Telehealth Partnerships That Supply Nutrition With Treatment

Clinics and telehealth providers steer patient purchases, so brands that offer dietitian training, patient guides and bundled supply agreements win accounts worth 10% to 16% of sales and lift repeat purchase by 10 to 16 points. Programmes cost $2 million to $8 million. Brands should start with the largest bariatric and obesity clinics, where volume is highest, and measure adherence by clinic so that support goes to partners that keep patients on nutrition plans. Clinic staff share feedback on tolerance and adherence, which helps brands refine products and keeps partners loyal through supply and price changes.
Market Impact: clinic partnerships win accounts worth 10-16% of sales

Reformulating for Tolerance With Small Servings, Neutral Flavours and Chewables

Nausea and taste fatigue drive many patients to stop, so brands that cut serving size, use neutral flavours and add chewable and powder formats lift six-month adherence by 8 to 14 points and cut churn. Programmes cost $1 million to $4 million per range. Brands should test recipes with patients on drugs and post-surgery panels first, where feedback is most valuable, and publish tolerance data so clinicians can recommend products with confidence. Patients on drugs report that smaller servings and cooler, less sweet flavours are easier to finish, which clinicians notice.
Market Impact: tolerance reformulation lifts six-month adherence by 8-14 points

Securing Whey and Micronutrient Contracts With Recipe Flexibility

Whey protein costs can rise 30% to 50% in a year, so brands that sign multi-year contracts, qualify pea, soy and collagen blends and keep alternative recipes protect margin and avoid abrupt price increases. Programmes cost $1 million to $3 million. Brands should contract the largest ingredients first, where cost exposure is highest, and share forecasts with suppliers so allocation risk falls during tight markets and demand spikes linked to new drug launches. Suppliers also give priority allocation to customers with reliable forecasts, which matters when new drug launches lift protein demand suddenly.
Market Impact: ingredient contracts protect margin against 30-50% cost spikes

Who Controls the Margin Pool

The global obesity-related malnutrition nutrition market is moderately concentrated, with a CR5 of 30%, and diet programmes, clinic brands and online sellers sit outside the leading five. This assessment measures participants on estimated obesity-related nutrition sales value, held constant across all players. Nestlé Health Science leads through Optifast and clinic reach, while Abbott, Danone, Herbalife and Glanbia follow, with a narrow gap between the leader and the challengers.
Competition runs on four dimensions today: clinician recommendation, taste and tolerance, protein and micronutrient formulation, and channel reach. Medical nutrition groups win on clinical credibility, consumer brands win on taste and online reach, and diet programmes win on adherence coaching. Imitators copy popular formats quickly, so premiums outside tolerable and clinician-recommended products erode within a year, and payers watch cost.

Emerging pressure comes from telehealth platforms with own brands, drug makers that add nutrition programmes, and regulators that define medical food status. Rankings shift where a brand wins a clinic contract, improves tolerance or wins a telehealth partnership. Challengers can move up quickly when leaders face taste complaints or supply gaps, and rankings can move within a single planning cycle.
obesity-related-malnutrition-nutrition-market-company-positioning-matrix-1789958019937

Competitive Moat and Risk Dimensions

NESTLÉ HEALTH SCIENCE

Moat: Clinic Reach and Optifast Credibility

Nestlé Health Science, a Swiss nutrition business, sells Optifast, Boost and other medical and consumer nutrition products through clinics, pharmacies and online channels, with decades of weight management experience and strong relationships with bariatric centres. Its clinic reach, credibility and range give it a market advantage, and its position supports quick launches of companion products for weight loss drug users.
NESTLÉ HEALTH SCIENCE

Risk: Consumer Taste and Price Pressure

Nestlé Health Science competes with consumer protein brands and private label products that offer lower prices and strong taste, and drug users often prefer familiar products. Clinics can choose rival suppliers, and payers rarely reimburse nutrition, so patients decide on price. Clinics may also dual-source to protect supply.
ABBOTT

Moat: Medical Nutrition Credibility and Scale

Abbott, an American healthcare group, sells Ensure, Glucerna and other adult nutrition products through hospitals, clinics, pharmacies and retail, with strong clinical evidence, large manufacturing scale and deep relationships with physicians and dietitians. Its credibility, scale and portfolio give it a market advantage, and its position supports launches of products for muscle health and metabolic conditions.
ABBOTT

Risk: Ageing Brand Perception

Abbott is often associated with older adults and hospital nutrition, so younger drug users may prefer newer consumer brands. Its products face taste criticism, and rivals with focused companion positioning can win telehealth and clinic partnerships. Investors also question its pace of innovation for younger patients.

Players Tracked

Prominent Players

Nestlé Health Science
Abbott
Danone
Herbalife
Glanbia

Other Key Players

Fresenius Kabi
BellRing Brands
Huel
WW International
Medifast
Nutrisystem
Kate Farms
Pharmavite
Bayer
Haleon
Church & Dwight
Thorne HealthTech
Nordic Naturals
Ajinomoto
Meiji Holdings

Recent Developments

JANUARY 2026

Nestlé Health Science Launches Small-Serving Protein and Micronutrient Range Designed for Weight Loss Drug Users

Nestlé Health Science launched a small-serving protein and micronutrient range designed for weight loss drug users, according to company communications. It is a product launch, not an acquisition, and it tests demand for companion nutrition. The range targets clinics and telehealth programmes. Sales terms were not disclosed.
Signal: Confirms leaders are designing products for reduced appetites because drug users need dense nutrition in small servings.
FEBRUARY 2026

Abbott Introduces Muscle Health Nutrition Line With Clinical Data for Patients on Weight Loss Medication

Abbott introduced a muscle health nutrition line with clinical data for patients on weight loss medication, according to company communications. It is a product launch, not an acquisition, and it tests evidence-led positioning. The line carries protein and vitamin D in small servings. Sales terms were not disclosed.
Signal: Suggests medical nutrition groups are publishing clinical data because clinicians want proof before recommending products to patients.
MARCH 2026

Herbalife Signs Telehealth Partnership to Supply Protein and Micronutrient Products Alongside Obesity Treatment Programmes

Herbalife signed a telehealth partnership to supply protein and micronutrient products alongside obesity treatment programmes, according to company communications. It is a distribution partnership, not an acquisition, and it tests telehealth channel demand. The partnership covers several markets. Terms were not disclosed. The partnership runs several years.
Signal: Indicates consumer brands are entering telehealth because platforms now control patient access and nutrition purchase decisions.

What Drives Obesity Nutrition Costs

Protein ingredients account for roughly 30% of product cost, vitamins, minerals and iron salts about 10%, flavours, sweeteners and texturisers about 8%, packaging about 12%, and manufacturing, clinic support, distribution and marketing about 40%. Whey and milk protein come mainly from the United States, Europe and New Zealand, iron and vitamins from China and Europe, and collagen from Brazil and Europe.
The clearest recent shock came from whey protein. Abbott Annual Report 2024 described cost inflation in nutrition inputs, and MMA Estimate from expert interviews indicates whey protein prices rose 30% to 50% as demand for protein products outran supply, so brands raised prices by 5% to 10%, cut serving sizes or blended pea and collagen protein. Clinics accepted only part of the increases. Some brands absorbed part of the difference.

The competitive disadvantage falls on small brands without ingredient contracts, clinic relationships or medical food status, which cannot absorb cost swings or fund clinician training. Large groups negotiate protein and vitamin terms and own plants. Exposure also varies by geography, since American brands buy domestic whey while Asian and Latin American brands import protein and pay for freight, duty and currency swings on every shipment.
obesity-related-malnutrition-nutrition-market-cost-volatility-analysis-1789958020246

Multi-Year Protein and Micronutrient Contracts

Brands sign multi-year contracts for whey, milk protein, iron and vitamins with two or three suppliers. Contracts cut exposure to price spikes of 30% to 50%. The main challenge is volume commitment, so larger brands lock terms first, while smaller brands buy through distributors at a premium and accept more price volatility. Contracts renew yearly.

Blended Protein Formulations and Recipe Options

Brands qualify blends of whey, milk, pea and collagen protein and keep alternative recipes ready. Blends protect margin and supply when one protein spikes. The main challenge is taste and tolerance, so brands test blends with patient panels and phase changes across ranges over about 18 months. Consumer panels confirm acceptable taste and texture before launch.

Clinician Training and Dietitian Support

Brands fund dietitian training, patient guides and clinic programmes that lift repeat purchase by 10 to 16 points. Programmes protect margin from promotion cycles. The main challenge is cost per clinic, so brands start with the largest bariatric centres and telehealth partners and use digital tools to scale support. Telehealth partners also help scale support at lower cost.

Portfolio Architecture for Margin Defence

Margins run from moderate returns on general protein foods and basic repletion products sold in volume to strong returns on GLP-1 companion and clinic-supplied products sold with clinical files, tolerance testing and dietitian support. Three tiers separate volume products, premium certified lines and next-generation solutions, and each tier draws on different clinic access, protein sourcing and evidence in a moderately concentrated market.
The tension between volume and premium is sharp. Protein-fortified foods and basic vitamin D, iron and B12 products fill large retail and pharmacy orders and serve price-driven buyers but face private label pricing and weak differentiation, while companion and clinic products earn higher margins on smaller volumes and depend on clinician trust, tolerance and evidence. Brands that run only volume struggle when prices fall, while brands that run only premium lose early volume. Mix management decides which risk dominates.

High-value pools concentrate in GLP-1 companion products sold through clinics, telehealth and online subscriptions and in clinic-supplied medical nutrition sold under long contracts. They gather where buyers pay for clinician advice and tolerance rather than price alone. Bariatric formulas add a stable pool with lifelong demand, and strong brands can hold both premiums and steady volume.

Volume / Commodity-Adjacent Tier

Protein-fortified foods and basic vitamin D, iron and B12 repletion products sold in volume to retail, pharmacy and private label buyers. Buyers focus on price and availability, and contracts renew annually.
Gross Margin: 28%-36%

Premium / Certified Tier

Bariatric vitamin and mineral formulas with clinical guideline alignment, third-party testing, chewable formats and audit files, sold to clinics, pharmacies and online buyers. Buyers value certification and steady supply. Contracts run for several years.
Gross Margin: 36%-48%

Sustainability / Regulatory / Next-Generation Tier

GLP-1 companion and clinic-supplied medical nutrition products with small dense servings, tolerance data, dietitian support and medical food status, sold through clinics and telehealth. Contracts run for several years. Volumes grow quickly online.
Gross Margin: 40%-54%
obesity-related-malnutrition-nutrition-market-portfolio-architecture-1789958020537

High-value Sub-segments and Strategic Watch-out

GLP-1 Companion Nutrition Products

GLP-1 companion nutrition products combine the fastest growth with strong pricing, since users of weight loss drugs need dense protein and micronutrients in small servings and pay for clinician-backed products at gross margins of 40% to 54%. Tolerance and evidence limit competition, and brands with clinic partners win repeat purchase.
Gross Margin: 40%-54%

Clinic-Supplied Medical Nutrition Products

Clinic-supplied medical nutrition products deliver firm growth and pricing, since clinics and telehealth providers bundle nutrition with treatment and brands earn gross margins of 36% to 48% for products with clinical files. Dietitian support and reliable supply form the entry barrier, and brands with medical food status win contracts.
Gross Margin: 36%-48%

Protein-Fortified Foods and Beverages

Protein-fortified foods and beverages are the volume core for brands with retail scale and price discipline. Value grows about 8.5% a year, and protein cost, taste and delivery reliability decide profit. Brands anchor sales on long relationships with grocers, pharmacies and online retailers, and customers renew ranges every year.
Gross Margin: 28%-36%

Vitamin D, Iron and B12 Repletion Products

Vitamin D, iron and B12 repletion products are the strategic watch-out, since growth of about 7.0% a year trails the leaders, private label competes on price and clinicians often prescribe generic supplements. Brands should manage these lines selectively and steer capacity toward companion and clinic products.
Gross Margin: 26%-36%

Why Patients Keep Reordering Nutrition Support

Obesity nutrition demand behaves like a short annuity attached to treatment plans, clinician advice and trusted brand relationships. Once a patient finds a product that fits a plan and sits comfortably, they reorder every week or month, and switching means new taste trials, nausea risk and lost momentum. Patients use last month's tolerance to fix renewals, so brands with clean records earn steadier volume. Clinic contracts often run for one to two years.
Adoption stickiness differs by end-use vertical. Bariatric surgery patients on lifelong guidelines are the deepest, since supplements are written into follow-up plans and change only when tolerance fails. Weight loss drug users follow prescriber advice and stay while they take the drug. General dieters are moderate and switch on promotion, while curious mainstream buyers are shallow. Telehealth patients follow platform recommendations closely.

Buyer profiles are shifting between generations. Older patients chose nutrition products on physician advice and hospital brands, while younger patients ask for clean labels, plant protein, creator recommendations and subscription convenience. Regulators and dietitians add a third group that sets claims and dose expectations. Brands that publish tolerance and clinical data win newer patients and clinicians.
obesity-related-malnutrition-nutrition-market-end-use-penetration-index-1789958020819

MMA Verdict on Obesity Nutrition Strategy

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / COMPANION PRODUCT STRATEGY

Shift Volume Into GLP-1 Companion Products Before Rivals Win Clinician Recommendations

GLP-1 Companion Nutrition Products grows at 12.6% a year, about 1.40 times the overall market rate, and gross margins of 40% to 54% compare with 28% to 36% for general protein products. Brands should commit $8 million to $25 million to small dense servings, micronutrients and gentle flavours, and shift 10% of volume into companion ranges to lift gross margin by three to five points. Those that stay in general protein will lose growth and pricing over the next two years, while early movers keep loyalty.
02 / CLINIC PARTNERSHIP STRATEGY

Build Clinic and Telehealth Partnerships Before Platforms Lock Patients Into Rivals

Clinics and telehealth providers steer patient purchases, clinic channels supply about 30% of sales, and brands without dietitian training and supply agreements lose accounts worth 10% to 16% of sales. Brands should invest $2 million to $8 million in training, patient guides and bundled supply, start with the largest bariatric and obesity clinics, and lift repeat purchase by 10 to 16 points. Those that delay will lose patients and margin over the next two years, while prepared brands hold premium pricing, loyalty and clinician trust across every treatment cycle.
03 / TOLERANCE DESIGN STRATEGY

Reformulate for Tolerance Before Nausea and Taste Fatigue Drive Patients Away

Nausea and taste fatigue cause adherence to fall below 50% after six months, patients on drugs and post-surgery need small servings, and brands without tolerance testing lose loyal buyers to gentler rivals. Brands should invest $1 million to $4 million per range in smaller servings, neutral flavours and chewable formats, test with patient panels first, and lift six-month adherence by 8 to 14 points. Those that delay will lose customers and shelf space over the next two years, while prepared brands hold premium pricing and clinician confidence.
04 / INGREDIENT SECURITY STRATEGY

Secure Whey and Micronutrient Contracts Before Protein Cost Spikes Erode Nutrition Margins

Whey protein costs can rise 30% to 50% in a year, demand for protein products keeps growing, and brands without contracts and recipe flexibility face margin cuts and abrupt price increases at shelf. Brands should invest $1 million to $3 million in multi-year contracts with two or three suppliers, blended protein qualification and alternative recipes, contract the largest ingredients first, and share forecasts with suppliers. Those that delay will lose margin and pricing over the next two years, while prepared brands hold volume and customer trust.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Obesity-Related Malnutrition Nutrition Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Obesity-Related Malnutrition Nutrition Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-sized American nutrition brand with annual sales near $310 million (client-reported, unverified by MMA), selling protein shakes, bars and vitamins through grocery, pharmacy and online channels. It offered no bariatric or companion products, relied on whey-heavy recipes, and had seen sales fall 4% as rivals launched products for weight loss drug users. Clinics kept asking for dense small-serving formats.
STRATEGIC CHALLENGE
Rivals launched companion products with clinical data, clinics asked for small dense servings, and whey costs squeezed margins on the client's large shakes. Management needed to decide whether to launch a companion range, build clinic partnerships, or reformulate for tolerance, with limited capital and dependence on whey-heavy recipes. Clinic buyers wanted answers within six months.
MMA APPROACH
MMA analysed sales, cost and review data across 30 products, interviewed 10 clinicians, dietitians and ingredient suppliers, and ran a patient survey on taste, tolerance and price across three regions. It modelled margin by range and scenario and ranked options by payback and execution risk, and tested each option against protein cost swings.
KEY FINDINGS
  1. A companion range would earn gross margins near 48% against 30% for existing shakes and cost about $12 million to launch (client-reported, unverified by MMA).
  2. Clinic and telehealth partnerships would cost about $3 million and open accounts worth about 12% of sales. The partnerships could start with six clinics.
  3. Reformulating three shakes for tolerance would cost about $2 million and lift six-month adherence by about 10 points. Patient panels supported the recipe changes.
  4. Multi-year protein contracts and blended recipes would cost about $1.5 million and cut exposure to price spikes of about 40%. Suppliers were identified through audits.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1-6): Sign protein contracts, reformulate three shakes for tolerance and open clinic and telehealth talks. Assign a project lead. Phase 2: Phase 2 (Months 7-24): Launch the companion range, start clinic training programmes and track adherence by clinic monthly. Report results to the board. Phase 3: Phase 3 (Months 25-42): Grow clinic accounts, review supplier terms yearly and drop products that lack a clear premium. Report to the board.
OUTCOME
Within 42 months, companion and clinic products reached 30% of sales, six-month adherence rose above 55%, and protein cost swings were absorbed without price shocks (client-reported, unverified by MMA). Gross margin rose by four points, profit exceeded plan by about 3%, and four clinic groups signed multi-year supply agreements.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Obesity-Related Malnutrition Nutrition Market?

The global obesity-related malnutrition nutrition market was valued at $5.50 billion in 2025 on a brand-value basis. Growth is supported by weight loss drug use and bariatric surgery, offset by tolerance problems and protein cost swings.

How large will the Obesity-Related Malnutrition Nutrition Market be by 2036?

The market is projected to reach $14.19 billion by 2036, up from $6.00 billion in 2026. The increase of $8.20 billion reflects companion products, clinic nutrition and Asian growth.

What is the CAGR for the Obesity-Related Malnutrition Nutrition Market 2026 to 2036?

The market is forecast to grow at a 9.0% CAGR from 2026 to 2036. The bull case reaches 10.3% and the bear case 7.7%, depending on drug persistence, guidelines and protein costs.

Which segment is growing fastest?

GLP-1 Companion Nutrition Products is the fastest-growing segment at 12.6% CAGR, roughly 1.40 times the overall market rate. Clinic-Supplied Medical Nutrition Products follows at 10.8% CAGR each year.

Who are the major companies in the Obesity-Related Malnutrition Nutrition Market?

Major companies include Nestlé Health Science, Abbott, Danone, Herbalife and Glanbia. Fresenius Kabi, BellRing Brands, Huel, WW International and Medifast also hold positions in obesity nutrition.

Which country is growing fastest?

Saudi Arabia is growing fastest at about 11.0% CAGR, because high obesity rates, widespread bariatric surgery and private clinic networks are widening nutrition support use. India and Mexico follow as obesity rises.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Primary Market Dimension

  • GLP-1 Companion Nutrition Products
  • Clinic-Supplied Medical Nutrition Products
  • Bariatric Vitamin and Mineral Formulas
  • Protein-Fortified Foods and Beverages
  • Vitamin D, Iron and B12 Repletion Products

By End-Use Industry

  • Weight Loss Drug Users
  • Bariatric Surgery Patients
  • General Obesity Management
  • Older Adults With Obesity
  • Metabolic and Diabetes Care

By Commercial Dimension

  • Clinics and Bariatric Centres
  • Telehealth Platforms
  • Pharmacies and Drugstores
  • Online and Subscription Sales
  • Grocery and Mass Retail

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, September 2026)
Market Definition
The market covers global sales of nutrition products marketed to prevent or treat nutrient gaps and muscle loss in people with obesity, valued at brand level, including GLP-1 companion nutrition products, clinic-supplied medical nutrition products, bariatric vitamin and mineral formulas, protein-fortified foods and beverages, and vitamin D, iron and B12 repletion products, sold through clinics, pharmacies, online and retail channels. The scope excludes weight loss drugs, meal replacement diet programmes without a nutrient-support claim, sports nutrition and infant formula.
Quantitative Units
USD billions (brand value); millions of servings for volume references
Segmentation Dimensions
By Product Type; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
United States, Canada, United Kingdom, Germany, France, Italy, Japan, South Korea, China, India, Australia, Indonesia, Brazil, Mexico, Chile, United Arab Emirates, Saudi Arabia, Kuwait, Egypt, Poland, and additional markets relevant to this sector
Key Companies Profiled
Nestlé Health Science, Abbott, Danone, Herbalife, Glanbia, Fresenius Kabi, BellRing Brands, Huel, WW International, Medifast, Nutrisystem, Kate Farms, Pharmavite, Bayer, Haleon, Church & Dwight, Thorne HealthTech, Nordic Naturals, Ajinomoto, Meiji Holdings
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-159
Published
September 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Obesity-Related Malnutrition Nutrition Market Report (2026 to 2036).

The full report delivers a detailed assessment of the obesity-related malnutrition nutrition market through 2036, covering product type, end-use and regional forecasts, competitive benchmarking of leading brands, and input cost analysis. It combines MMA primary research, including a six-country survey of 3,800 respondents and 47 expert interviews, with public statistical and company data. Analysts also model drug persistence scenarios, guideline outcomes and protein cost paths. Clients receive segment margin ranges, supply maps and a case study on product strategy. Supplier programme and contract frameworks are also included for planning.
Ten-year product type demand forecasts by region
Protein, vitamin, and packaging cost tracking
Competitive benchmarking of leading obesity nutrition brands
Medical food and guideline rule tracker
Regional market comparative analysis and forecasts included
Quarterly primary survey data update access

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts