Market Minds Advisory
North America Injectable Drug Market

North America Injectable Drug Market: GLP-1 Demand Reshapes Biologics Sourcing

Surging GLP-1 metabolic disease demand and expanding biosimilar competition are pushing payers toward differentiated injectable formularies, pressuring legacy monoclonal antibody franchises whose patent exclusivity increasingly conflicts with tightening reimbursement negotiation pressure.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$185.0BMarket Size 2025
2036 FORECAST VALUE$517.4BBase Case , 2026 to 2036
CAGR 2026 TO 20369.8 %Bull 11.0% / Bear 8.4%
INCREMENTAL OPPORTUNITY$314.2BNet 10- year value creation
EXPANSION MULTIPLE2.55x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Eli Lilly and Novo Nordisk built the modern injectable drug category on monoclonal antibody formats, and GLP-1 metabolic disease injectables are now the fastest growing answer to payers facing chronic weight management demand that legacy biologics cannot satisfy across most major North American healthcare systems today overall and every cycle.
Eli Lilly and Novo Nordisk still command meaningful combined share of the category through decades of clinical development investment and established payer relationships, while surging metabolic disease demand keeps expanding the addressable market pool each year. GLP-1 and biosimilar formats have pulled prescribing decisions firmly toward differentiated construction across endocrinology and specialty care programmes, concentrated heavily in the United States' dense branded biologics prescribing base.
Five companies hold under a third of category revenue, a fragmented structure built on specialized clinical development that smaller manufacturers struggle to replicate, and the order shifts more often than in mature pharmaceutical categories since payers frequently renegotiate formulary contracts across annual rebate cycles. Rising GLP-1 and biosimilar demand will determine how quickly differentiated products displace legacy monoclonal incumbents across every major North American healthcare channel each ongoing budget cycle overall.
Market Definition
This market covers pharmaceutical products administered by injection and sold across the United States, Canada, and Mexico, including monoclonal antibody injectables, GLP-1 and metabolic disease injectables, biosimilar injectables, vaccine injectables, and insulin and diabetes injectables. It excludes oral and topical pharmaceutical formulations and injectable drug delivery devices sold separately from the pharmaceutical product itself.
Base Year Value
$185.0B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
9.8% base case. Bull 11.0%. Bear 8.4%.
Fastest Growth Segment
GLP-1 and Metabolic Disease Injectables: 22.4% CAGR
Fastest Growth Country
United States: 10.2% CAGR
Fastest Growth Region
South Asia and Pacific: 11.8% CAGR
Largest Region
North America: 38% of 2025 global value
Market Leaders
Eli Lilly and Company, Novo Nordisk A/S, AbbVie Inc, Pfizer Inc, Johnson & Johnson. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

North America Injectable Drug Market Forecast Scenarios

north-america-injectable-drug-market-size-forecast-scenario-1787300250477
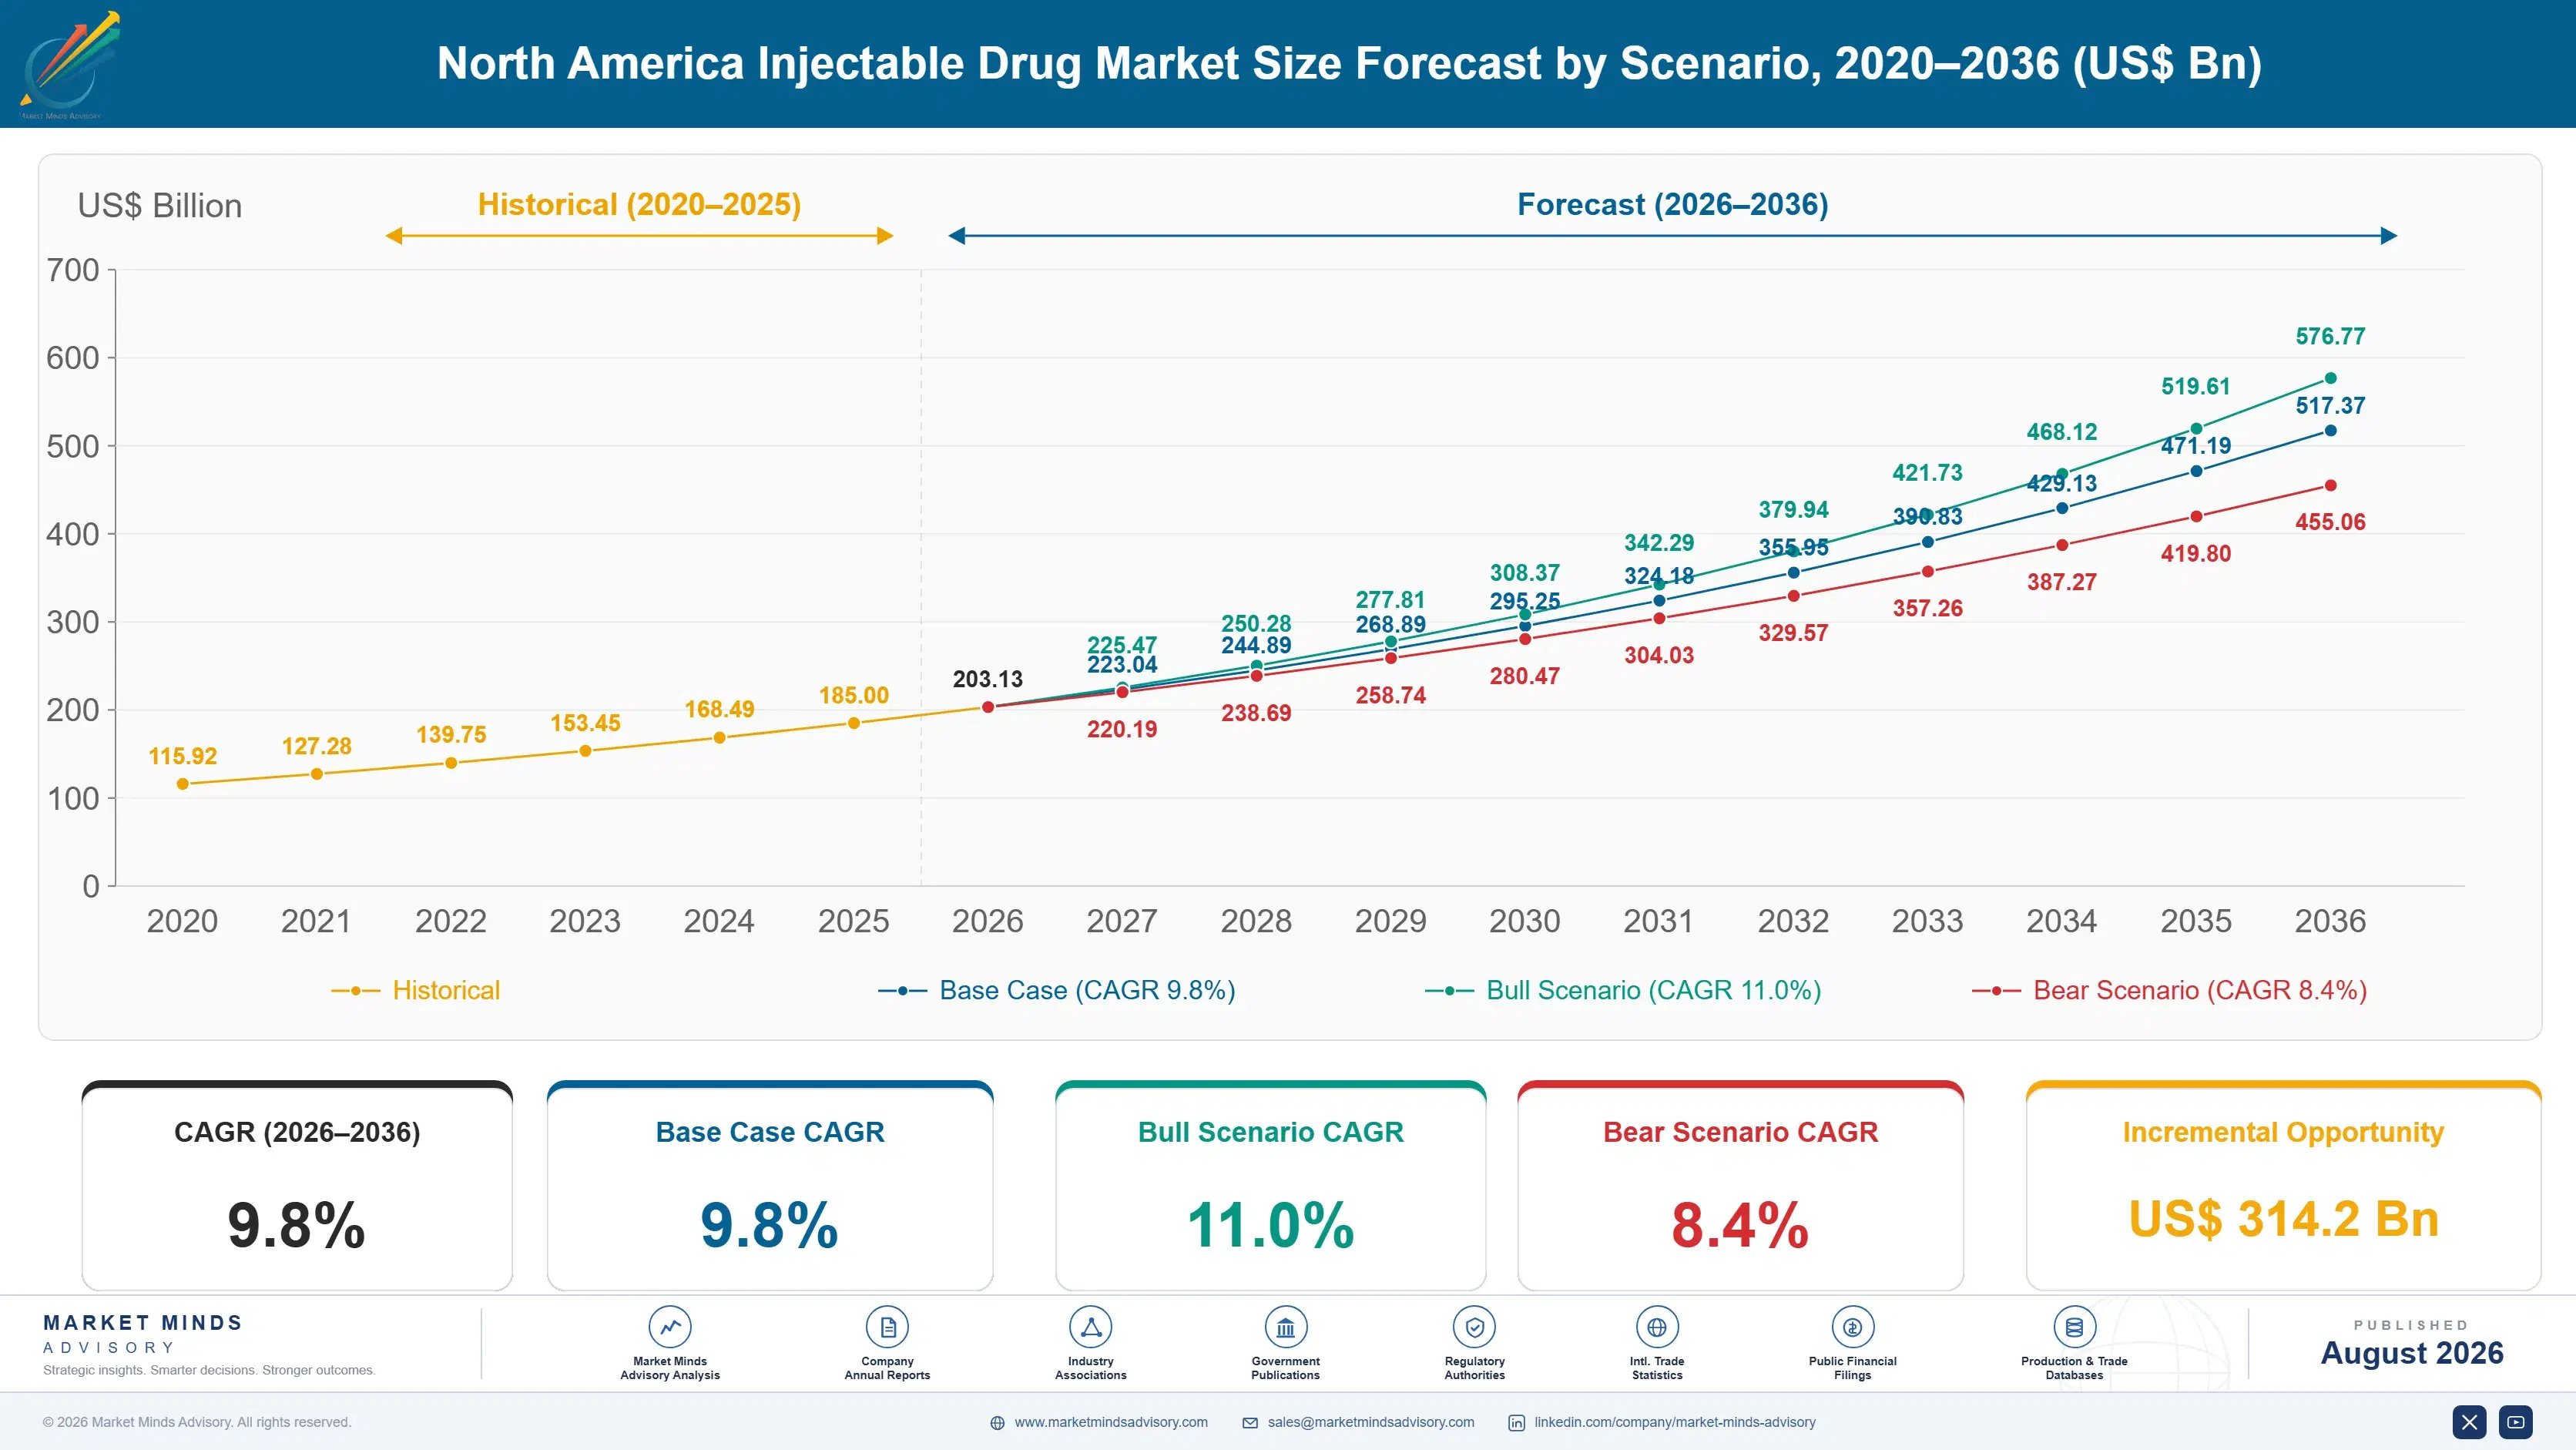
Between 2020 and 2025, the market grew at a historical rate near 8.2 percent, reflecting steady prescribing demand for established monoclonal antibody formats and gradual GLP-1 adoption across endocrinology programmes, with biosimilar injectables remaining a comparatively small share of total volume through most of this recovery period as conventional branded biologics still dominated most payer formularies.
The base case assumes 9.8 percent annual growth through 2036, built on three mechanisms: surging GLP-1 metabolic disease demand driving prescribing volume, expanding biosimilar competition supporting cost-efficient format growth, and manufacturing capacity expansion pulling forward volume well ahead of comparable prior decade cycles still under gradual modernisation across most major producing regions nationwide, tracked closely by payer procurement teams reviewing formulary cycles each year and every fiscal review cycle overall.
A bull case near 11.0 percent depends on obesity treatment insurance coverage expansion holding firm across major markets still finalizing reimbursement policy for GLP-1 formats today. The bear case near 8.4 percent reflects continued payer budget caution around premium branded price differentials pushing some prescribing toward biosimilar alternatives in cost constrained healthcare markets each ongoing annual budget cycle overall.

Monoclonal Legacy Meets GLP-1 Demand Surge

Injectable drug procurement has quietly become a differentiation depth and payer negotiation leverage specification decision as much as a formulary sourcing one. The core function, delivering therapeutic proteins and biologics through injection, has not changed, but payers increasingly weigh differentiation depth alongside rebate economics when planning new formulary protocols across every affected endocrinology and specialty care category nationwide. That shift already shapes new formulary eval
TOP 5 CONCENTRATION32% CR5revenue share held by five largest North American drug manufacturers
AVERAGE ANNUAL TREATMENT VALUE$14,200 per patienttypical annual injectable therapy cost across major payer formularies
LEADING PRODUCING COUNTRYUSA, 33%share of North American product value, by manufacturer home country
GLP-1 REVENUE SHARE24% of revenueshare of category revenue from metabolic disease injectable formats
SPECIALTY PHARMACY VOLUME SHARE52% of prescriptionsshare of prescription volume dispensed through specialty pharmacy channels
BIOLOGIC MANUFACTURING COST SHARE44% of COGSinput cost weight from cell culture and purification process sourcing
Commercial behaviour splits by payer tier and clinical criticality. Standard commercial formularies still rely heavily on established monoclonal antibody formats that have performed reliably for years, while specialty and metabolic disease programmes increasingly specify GLP-1 and biosimilar formats where differentiation carries meaningfully higher practical value than marginal cost savings. Distributors report this split sharpening recently across major payer networks.
The next decade turns on whether monoclonal-focused manufacturers can build sufficient GLP-1 depth to compete for demand-driven payer formulary placement while defending their core biologics relationships against rising specialty competitors. Manufacturers that solve both problems stand to capture share from a monoclonal installed base that has dominated injectable therapeutics for more than two decades of continuous clinical use nationwide. That transition will not happen overnight.
"Nobody switches formulary placement because the pitch deck is compelling. They switch because the rebate math on GLP-1 volume just changed the whole negotiation."
Director, Pharmaceutical Market Access Practice · MMA Healthcare Practice

Market Trends

GLP-1 Metabolic Disease Adoption Accelerates Conversion

GLP-1 metabolic disease adoption has expanded considerably as payers increasingly favor differentiated weight management formats that conventional monoclonal biologics struggle to support against advanced alternatives offering meaningfully higher patient demand and reduced formulary substitution pressure. Eli Lilly and Novo Nordisk have both reported expanded order books for GLP-1 injectables from major payer networks in recent years, driven by commercial teams specifically seeking products that reduce prior authorization denial rates. Payer data has documented meaningfully higher patient retention versus comparable monoclonal-only programmes across audited comparisons reviewed by MMA analysts. Payer networks across Canada and Mexico have announced comparable expansions recently.
Market Impact: Reaches 29% of capacity investment
Biosimilar Competition Expands National Formulary Demand

Biosimilar competition adoption has expanded considerably as health systems increasingly source cost-efficient alternatives that legacy branded-only formularies could not support at required budget management levels. AbbVie and Pfizer have both expanded dedicated biosimilar-defensive portfolios targeting the more than 480 health system formulary committees adopting standardised biosimilar substitution protocols annually according to trade association data reviewed by MMA analysts. Programmes across Canada and Mexico have announced comparable adoption expansions over the past two years, reflecting the trend's broadening reach across multiple healthcare systems nationwide, tracked closely by procurement teams each cycle.
Market Impact: Adds 8,400-plus enrollment-ready formularies

Market Opportunities and Growth Drivers

Expanding Specialty Pharmacy Network Drives Volume

North American specialty pharmacy network capacity continues expanding considerably across major healthcare systems, a shift that has fundamentally changed injectable drug demand patterns since new specialty pharmacy launches command meaningfully higher per-patient dispensing volume than routine retail pharmacy purchasing historically generated. Manufacturers have responded with dedicated specialty-ready product bundles specifically engineered for these higher-volume requirements. An estimated 29 percent of new injectable drug purchasing now targets new specialty pharmacy network launches, up considerably from a meaningfully smaller share just a decade earlier, reflecting accelerating healthcare investment across major markets, tracked closely by procurement teams.
Market Impact: Loses 5 to 8% share

Rising Obesity Prevalence Volume Expands Demand

North American obesity prevalence volume has risen considerably in recent years, driven by rising demand for effective, injectable weight management therapy offering higher clinical outcome value and reduced comorbidity treatment costs than conventional lifestyle-only alternatives historically delivered. Manufacturers have responded by developing dedicated obesity-ready product lines specifically engineered for these tighter clinical requirements. New payer procurement capacity is projected to grow considerably across major markets through the coming decade, each payer requiring formulary capability capable of sustaining faster patient enrollment than conventional systems allow, across nearly every major healthcare network nationwide, reviewed closely by procurement analysts each year.
Market Impact: Limits adoption to 25% of systems

Market Restraints and Challenges

High GLP-1 Cost Slows Budget Constrained Adoption

Many payers in budget-constrained categories find the cost of GLP-1 injectables over conventional monoclonal formats economically difficult, even where the demand case is well documented. The root cause is that annual formulary budget cycles, not clinical outcome data, drive most prescribing decisions, and lower-resource payers see meaningfully slower GLP-1 adoption than higher-resource payers facing the same prescribing decision. Manufacturers have responded by developing tiered pricing programmes and simplified access designs specifically intended to narrow the cost gap across multiple budget-constrained healthcare markets, each year and every ongoing budget review cycle.
Market Impact: Lifts GLP-1 format share 24%

Fragmented Regulatory Approval Standards Slow Adoption

Injectable biologic regulatory approval compliance requires jurisdiction-specific clinical validation data and testing infrastructure that many smaller manufacturers lack capacity to maintain, since multi-jurisdiction compliance differs meaningfully from single-market drug production most manufacturers already manage. This restricts advanced product adoption among smaller regional manufacturers serving fragmented, resource-constrained healthcare markets rather than large multinational pharmaceutical companies. Manufacturers have responded by developing simplified approval lookup tools and dedicated compliance support programmes specifically intended to lower the adoption barrier across multiple underserved regional markets, particularly among smaller manufacturers with limited compliance staff available today, reviewed each fiscal cycle by regional teams overall.
Market Impact: Covers 480-plus adopting formulary committees
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

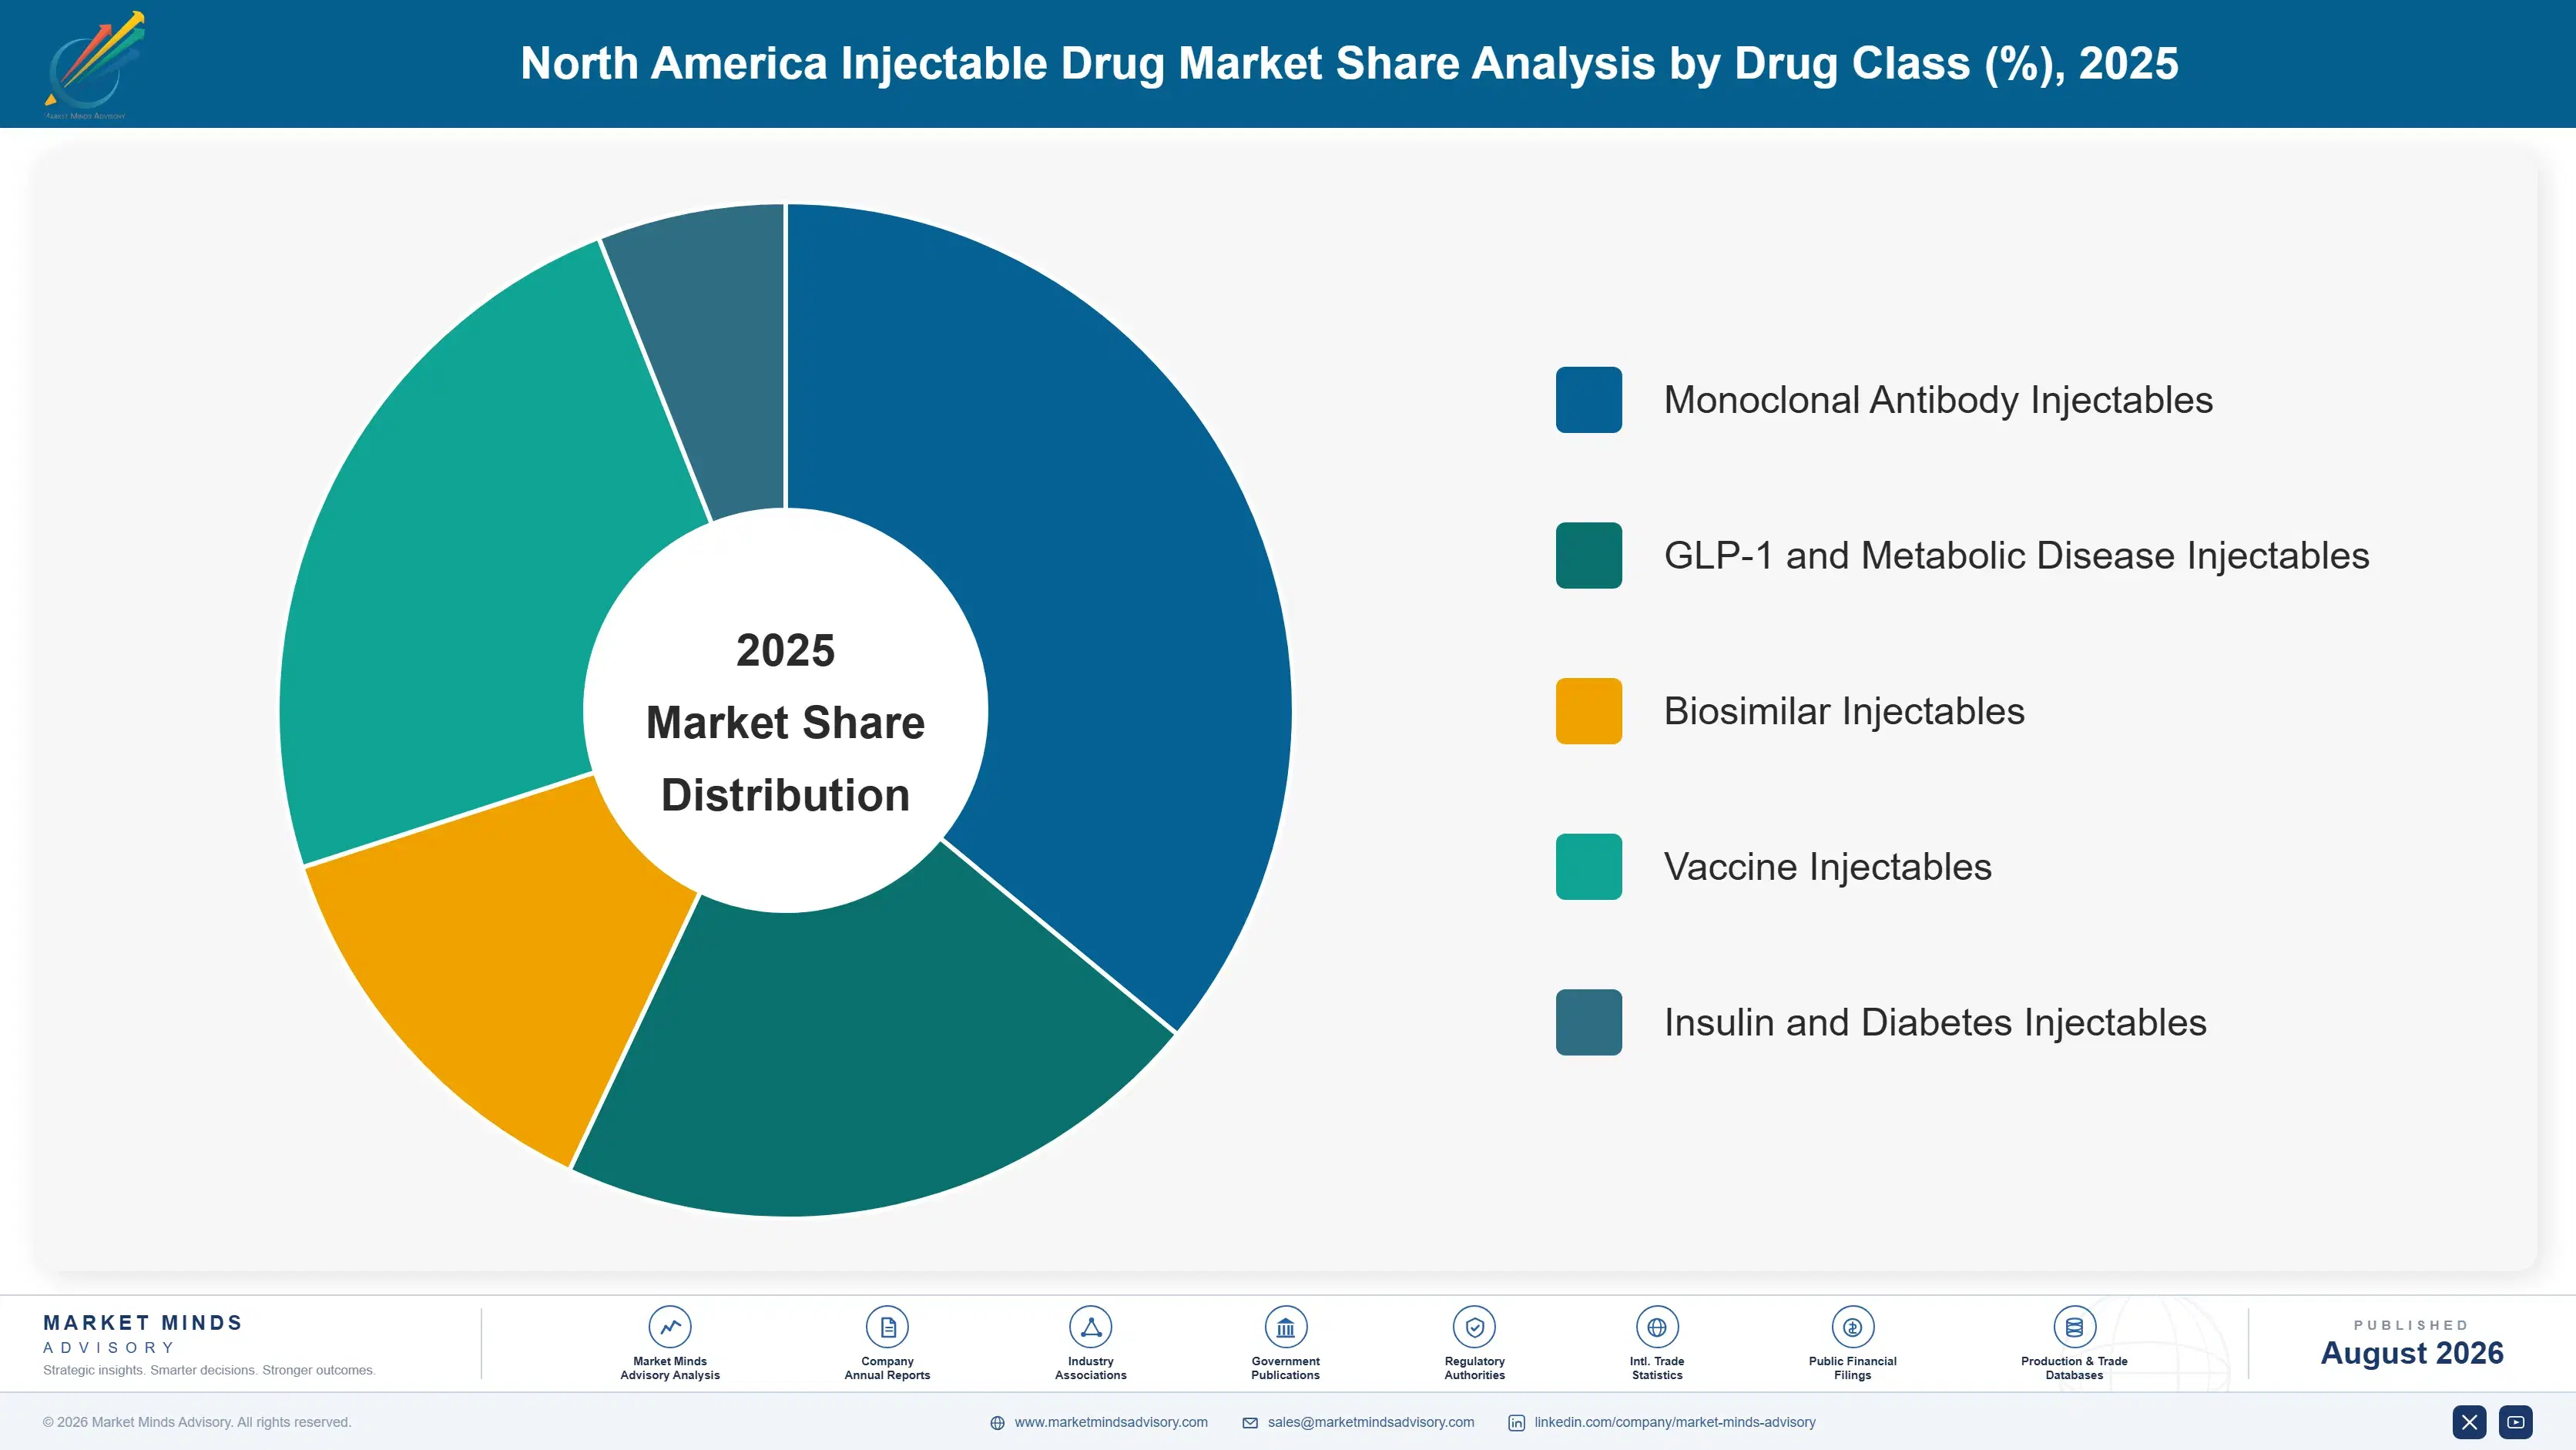
Segmentation follows drug class, the classification payers, health system formulary committees, and specialty pharmacy buyers already use to distinguish monoclonal, GLP-1, biosimilar, and vaccine categories across every product type this report covers, spanning both established monoclonal and rapidly emerging GLP-1 categories, from routine chronic disease use through next-generation metabolic formats now scaling nationwide each year across major markets.
north-america-injectable-drug-market-market-share-analysis-1787300251017

GLP-1 and Metabolic Disease Injectables

GLP-1 and metabolic disease injectables are the fastest-growing category as payers increasingly specify differentiated weight management formats to enable chronic disease control across endocrinology and specialty care settings. The mechanism uses incretin receptor agonism rather than immune-target monoclonal binding, delivering meaningfully higher patient demand than conventional alternatives typically achieve. Eli Lilly and Novo Nordisk both compete directly in this segment, each pursuing expanded distribution relationships with payer networks nationwide. Growth concentrates among payers serving high obesity and diabetes prevalence demand, though broader adoption still depends on closing the remaining cost gap with established monoclonal alternatives each year. Manufacturers investing early in this transition stand to capture disproportionate share as obesity coverage mandates broaden across markets.
CAGR 22.4%

Biosimilar Injectables

Biosimilar injectables grow fastest among established categories as payers increasingly specify cost-efficient reference-product-equivalent formats for applications requiring greater budget management than branded-only methods provide. AbbVie and Pfizer both hold significant positions in this segment, backed by years of manufacturing scale investment and established payer relationships across major healthcare systems nationwide. Growth concentrates among payers specifically expanding biosimilar substitution programmes, though manufacturers face rising competitive pressure from GLP-1 alternatives in applications where clinical differentiation weighs more heavily than cost efficiency on formulary decisions. Manufacturers with compact, lower-cost biosimilar designs increasingly win these smaller-scale deployments ahead of larger legacy competitors, particularly across regional health systems still building out dedicated biosimilar substitution relationships each year.
CAGR 14.8%
Full segment breakdown across 5 segments available in the complete report.

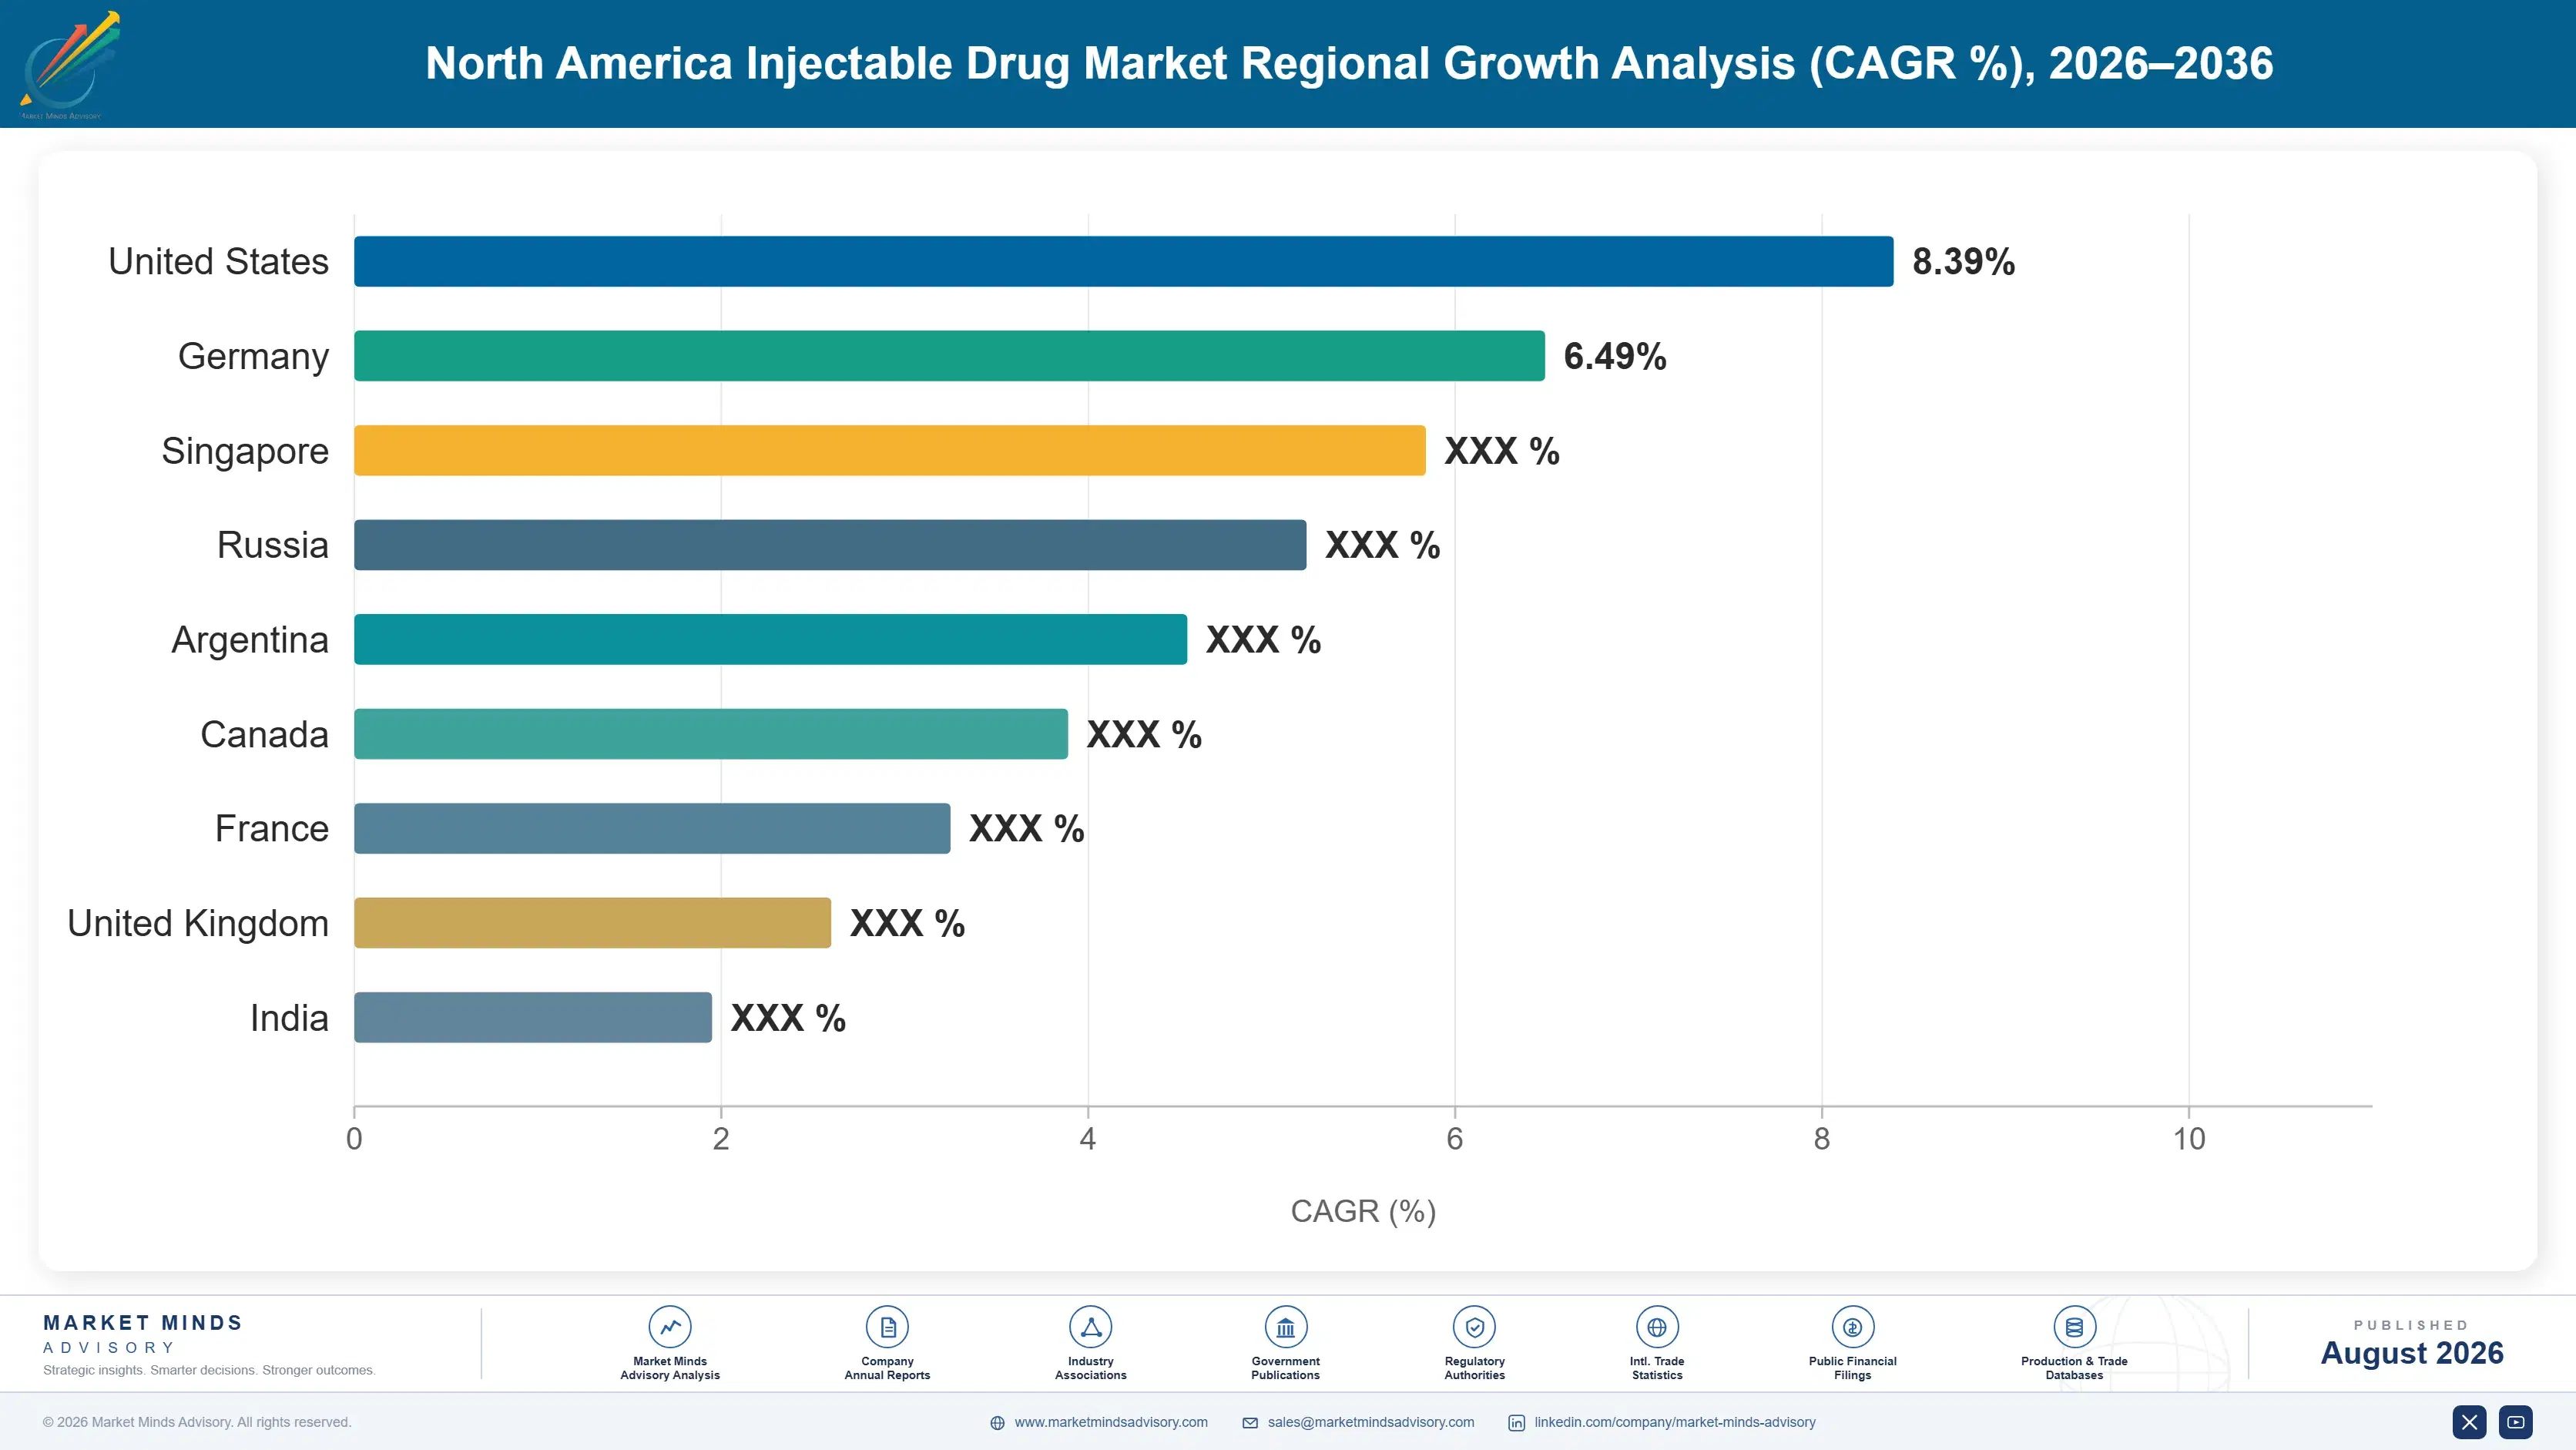
Regional Architecture and Country Demand Map

North America accounts for a dominant share of category revenue given this report's national scope and the region's outsized branded biologics prescribing base, while South Asia and Pacific posts the fastest regional growth on expanding manufacturing capacity nationwide each year across the region's major purchasing markets and networks.

North America

The United States drives the overwhelming majority of regional demand through its concentration of branded biologics prescribing activity and its position as home base for Eli Lilly's and Novo Nordisk's commercial operations. North America's share sits above the standard band because this report is scoped to the North American injectable drug market, reflecting the region's outsized branded GLP-1 spend relative to global peers. Eli Lilly and Novo Nordisk both maintain domestic distribution and payer support presence serving this demand directly. Rising GLP-1 adoption has expanded demand for injectables across regional payer networks. Canada contributes a smaller but stable share, with formulary systems gradually expanding coverage. Mexico's demand ties to cross-border pharmaceutical distribution networks serving domestic and North American payer programmes.
Share: 38% | CAGR: 10.6% (2026 to 2036)

Western Europe

Germany anchors regional demand through its well-established pharmaceutical manufacturing infrastructure and long-standing payer distributor relationships built over decades of continuous product development. The United Kingdom follows closely, with National Health Service reimbursement compliance commitments driving sustained product procurement across healthcare networks nationwide. France and Switzerland contribute meaningful shares tied to established pharmaceutical manufacturing clusters supplying domestic and wider European purchasing networks. Regional growth trails East Asia and South Asia because much of Western Europe's injectable drug base is already relatively mature, a pattern regional manufacturers expect to persist through continued gradual modernisation each fiscal year across most national markets and affiliated distribution channels monitored closely by regional procurement authorities each year overall.
Share: 21% | CAGR: 8.2% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
north-america-injectable-drug-market-country-cagr-analysis-1787300251533

Where Injectable Drug Margin Concentrates

Margin follows differentiation depth and payer relationship positioning, not prescription volume alone. Manufacturers who win early payer formulary relationships lock in multi-year prescribing streams that generic manufacturers struggle to match once the relationship is fully established across the payer's entire covered population, a dynamic reshaping how manufacturers prioritise clinical investment planning each budget year overall.

Winning Early Payer Formulary Design Relationships

Manufacturers who secure product specification during a payer's early formulary planning phase typically retain that payer's prescribing volume across successive contract cycles, since switching manufacturers mid-programme requires costly clinical revalidation and prior authorization redesign that payers avoid wherever possible across every affected therapeutic category. Eli Lilly and Novo Nordisk have both invested heavily in early engagement with payer formulary teams specifically to secure these relationships ahead of formal contract competitions. Early-established manufacturers typically capture pricing 8 to 13 percent above what competitive late-stage positioning would produce, reflecting the switching-cost advantage built into the relationship timing itself.
Market Impact: Adds an 8 to 13% pricing edge overall

Building Extended Clinical Outcome Support Programmes

Manufacturers who pair products with proprietary clinical outcome and adherence tracking programmes capture higher-margin recurring prescribing beyond the unit cost itself, since payer quality teams increasingly value integrated outcome support when justifying premium product specification internally to formulary committees each budget cycle. AbbVie and Pfizer both run dedicated outcome documentation teams that work directly with customer quality departments throughout the specification process. This outcome layer has widened effective programme margins by an estimated 10 to 17 percentage points versus product-only supply agreements documented in recent investor materials, across multiple major markets.
Market Impact: Widens margins by 10 to 17 points overall

Regional Manufacturing Capacity for Local Content Eligibility

Manufacturers establishing local manufacturing capacity in markets with national pharmaceutical content requirements, notably Canada's domestic manufacturing preference programme, secure preferential access to formulary decisions tied to those same requirements set by policy and periodically revised over time. Several global manufacturers have expanded North American manufacturing specifically to capture this advantage ahead of competitors still supplying from import-based positions and lacking comparable local presence of their own. Local manufacturers report winning an estimated 17 to 24 percent more formulary decisions in content-linked markets than comparable import-dependent competitors face each year, across multiple product categories.
Market Impact: Wins 17 to 24% more formulary decisions overall

Building Structured Real-World Clinical Evidence Programmes

Manufacturers who develop structured real-world evidence programmes documenting adherence and outcome data capture higher-margin premium product revenue while shortening the evidence-gathering timeline for payers otherwise facing lengthy independent clinical studies entirely on their own. Eli Lilly and AbbVie both maintain dedicated clinical research teams that work directly with payer investigators throughout the evidence generation and publication process. Data-backed products have historically captured 18 to 25 percent higher formulary approval rates than products lacking comparable published clinical data, based on comparable prior programme patterns MMA has tracked closely across multiple recent evidence cycles.
Market Impact: Lifts approval rate 18 to 25% overall each cycle

Who Controls the Margin Pool

CR5 sits at 32 percent, moderately fragmented for a specialty pharmaceutical category this size, reflecting the substantial clinical development barriers and specialized payer relationships that keep new entrants from challenging incumbents quickly. Eli Lilly and Novo Nordisk hold the largest positions, with a meaningful gap to AbbVie and Pfizer in the next tier of established challengers across most North American regions today.
Current competitive activity centres on three fronts: established monoclonal-focused manufacturers defending specialty relationships while expanding into higher-margin GLP-1 formats, biosimilar firms racing to expand cost evidence ahead of incumbent responses, and all major players investing in outcome support programmes targeting rapidly tightening payer quality requirements nationwide each cycle.

Emerging pressure comes from biosimilar manufacturers, who have moved from basic reference-product supply toward broader GLP-1 ambitions as domestic manufacturing incentive programmes create a genuine opening against established incumbents defending their core franchise across every major product category. Rankings shift most at the payer-tier level rather than nationally: a manufacturer's dominant position in premium specialty formularies carries limited weight in value-tier plans, where price and rebate speed increasingly determine outcomes each ongoing budget cycle overall.
north-america-injectable-drug-market-company-positioning-matrix-1787300252058

Competitive Moat and Risk Dimensions

ELI LILLY AND COMPANY

Moat: Full-Portfolio Format Coverage

Eli Lilly's full-portfolio product line, spanning monoclonal through GLP-1 and biosimilar-defensive formats, lets it win comprehensive payer-wide formulary agreements that single-application competitors cannot match, giving it a durable revenue base across nearly every applicable therapeutic category and payer tier nationwide, reinforced by decades of accumulated clinical trust and formulary relationship continuity.
ELI LILLY AND COMPANY

Risk: GLP-1 Capacity Underexposure

Eli Lilly's comparatively constrained manufacturing capacity for GLP-1 formats leaves it exposed to Novo Nordisk capturing the fastest-growing segment of category demand, a gap that could widen as GLP-1 prescribing continues expanding faster than Eli Lilly's core monoclonal franchise grows each year. That gap has widened noticeably in recent tender cycles.
NOVO NORDISK A/S

Moat: North American Payer Distribution Scale

Novo Nordisk's North American payer distribution scale and long-standing relationships with formulary procurement departments give it a cost and rebate-speed advantage in mainstream injectable products that specialty-focused competitors have struggled to match on comparable large payer tenders across multiple developed markets, reinforced by decades of accumulated payer trust.
NOVO NORDISK A/S

Risk: Limited Asian Manufacturing Exposure

Novo Nordisk's North America and Europe centered commercial strategy leaves it comparatively less exposed to Asian domestic manufacturing revenue than diversified rivals, a gap that could widen as Asian demand continues expanding faster than the traditional markets Novo Nordisk has prioritised historically each year going forward. That gap has already attracted scrutiny from investors monitoring regional exposure closely.

Players Tracked

Prominent Players

Eli Lilly and Company
Novo Nordisk A/S
AbbVie Inc
Pfizer Inc
Johnson & Johnson

Other Key Players

Merck & Co Inc
Bristol Myers Squibb Company
Sanofi SA
Amgen Inc
Regeneron Pharmaceuticals Inc
Roche Holding AG
Novartis AG
GSK plc
Teva Pharmaceutical Industries Ltd
Viatris Inc
Fresenius Kabi AG
Hikma Pharmaceuticals plc
Baxter International Inc
Samsung Bioepis Co Ltd
Sandoz Group AG

Recent Developments

MARCH 2026

Eli Lilly Opens Dedicated GLP-1 Manufacturing Facility

Eli Lilly completed construction of a dedicated manufacturing facility for GLP-1 injectables, adding capacity equivalent to roughly 18 percent of its existing annual GLP-1 format volume. The expansion targets rising demand from payer networks seeking qualified metabolic disease suppliers across multiple regional distribution networks and clinical programmes.
Signal: Established monoclonal-focused manufacturers are dedicating standalone capacity to GLP-1 injectables as demand diverges sharply from legacy volume.
OCTOBER 2025

Novo Nordisk Acquires Specialty Formulation Technology Company

Novo Nordisk completed an acquisition of a specialty formulation technology company, strengthening its next-generation delivery portfolio ahead of rising demand. The deal covers exclusive access to specific extended-release technology developed by the acquired company, alongside shared future improvement rights under terms disclosed only partially and pending regulatory review.
Signal: Established injectable drug manufacturers are acquiring specialty formulation technology to defend against convenience-focused competitors emerging quickly.
JUNE 2025

AbbVie Signs Multi-Year Supply Agreement With Regional Health System Network

AbbVie signed a multi-year supply agreement with a major regional health system network, covering an estimated 420,000 additional prescriptions across the network's formulary expansion programme. The agreement followed extensive evaluation of clinical outcome and delivery reliability data across participating health systems reviewed closely by MMA analysts.
Signal: Health system networks are standardising formulary procurement around fewer qualified suppliers to simplify multi-site compliance nationwide.

Cell Culture and Purification Process Costs

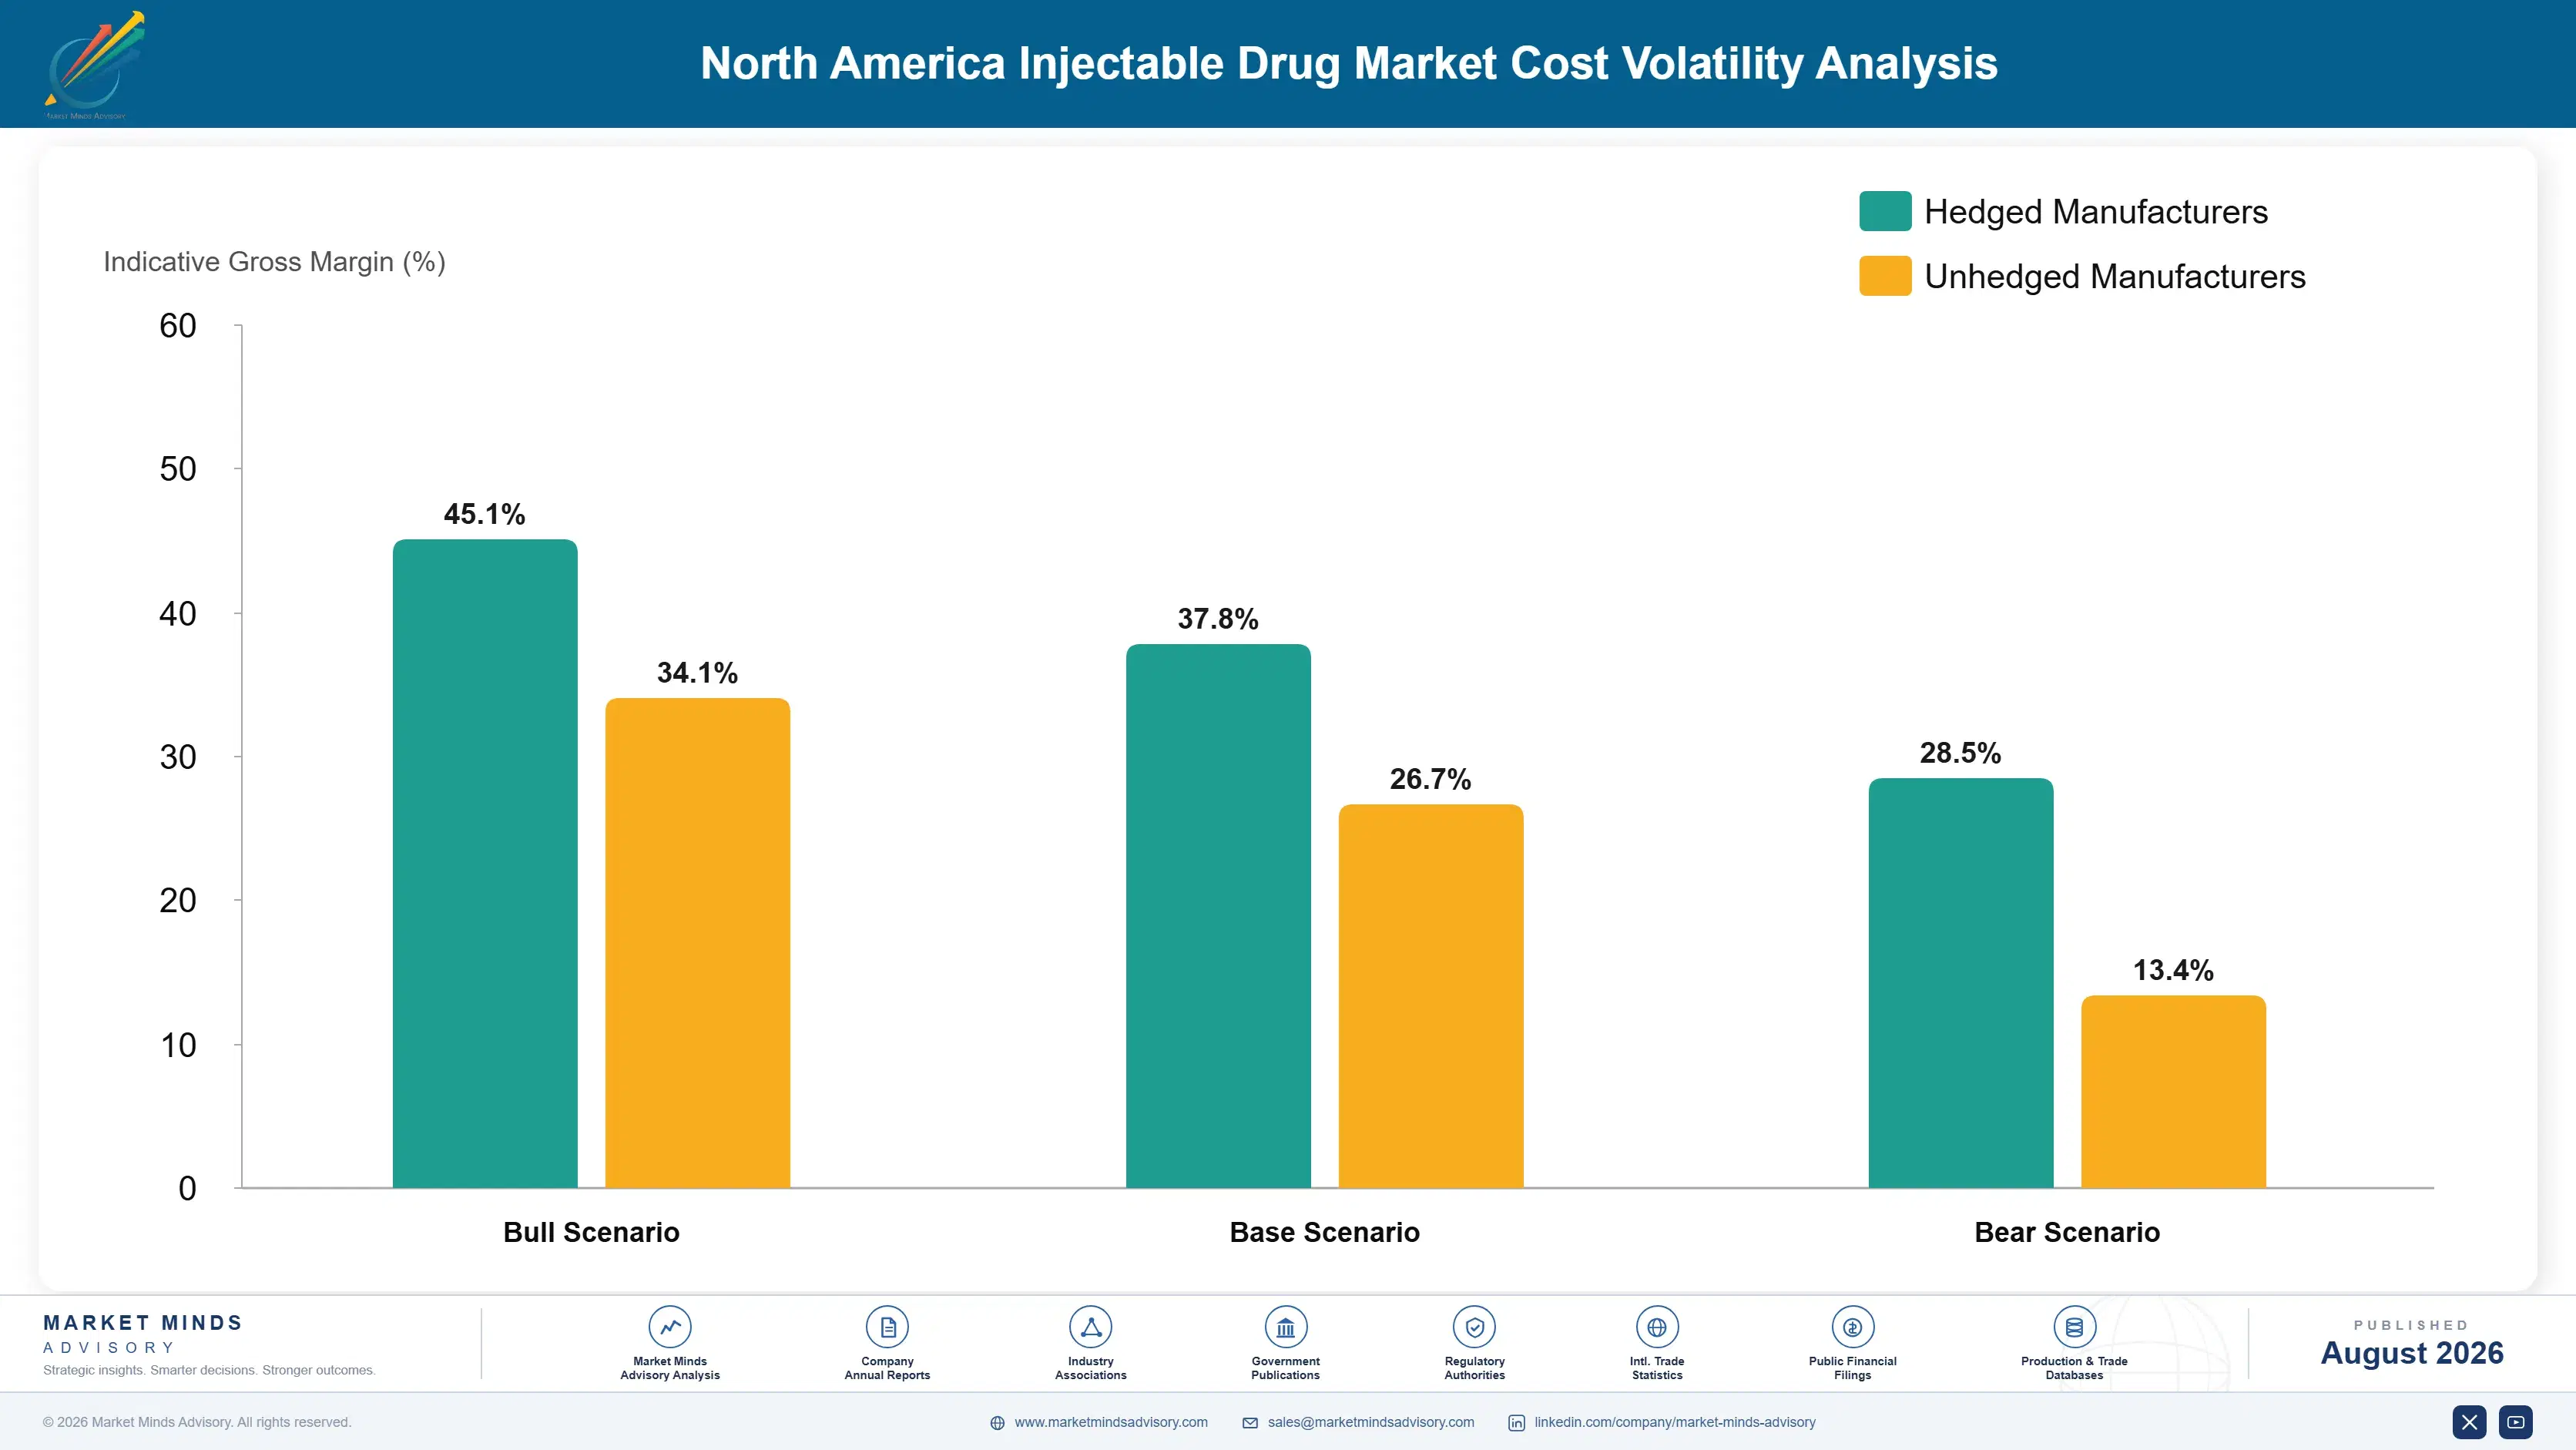
Cell culture media and downstream purification processes together represent roughly 44 percent of injectable drug manufacturing COGS, sourced from a global base of specialized bioprocessing suppliers and a smaller set of purification resin manufacturers qualified to pharmaceutical-grade reliability specifications required across every major product segment, particularly for GLP-1 grades, across every major manufacturing hub tracked closely each fiscal year.
Bioprocessing input pricing volatility during 2021 and 2022 pushed manufacturing costs up a documented 23 percent according to industry supplier disclosures, forcing several manufacturers to renegotiate multi-year fixed-price payer contracts signed before the increase took hold across the industry. Purification resin pricing, particularly relevant to premium biologics grades, has added further cost pressure given periodic tightness in specialized chromatography capacity shared with broader biopharmaceutical end markets.

Exposure varies by manufacturer scale and product mix. Smaller manufacturers reliant on spot bioprocessing purchases remain most exposed to price swings given limited hedging capacity, while larger integrated manufacturers with long-term supplier contracts face comparatively more stable input costs tied to supply flexibility that has expanded considerably over recent years of contract structuring across the industry each fiscal cycle overall.
north-america-injectable-drug-market-cost-volatility-analysis-1787300252255

Long-Term Bioprocessing Supply Agreements

Larger manufacturers now lock in multi-year bioprocessing media supply agreements with fixed volume commitments, insulating unit pricing from short-term commodity swings that previously forced costly mid-contract renegotiations with payer customers across the industry and delayed delivery schedules considerably each production cycle observed across multiple manufacturing regions and supplier tiers each fiscal year of ongoing review.

In-House Purification Capability

Several leading manufacturers have built internal purification and quality control capability specifically to reduce dependence on external suppliers for standard and premium applications, trading higher fixed capital investment for greater supply certainty during periods of industry-wide demand and constrained resin availability across the entire supply chain each fiscal year overall and well beyond consistently across the wider industry.

Dual-Sourcing Bioprocessing Suppliers

Manufacturers increasingly qualify two bioprocessing suppliers per product line rather than one, adding validation cost upfront but avoiding single-supplier exposure during periods of raw material tightness affecting the broader biopharmaceutical supply chain simultaneously across multiple concurrent production and testing programmes each cycle of ongoing procurement planning and annual budget review across every major supplier region.

Portfolio Architecture for Margin Defence

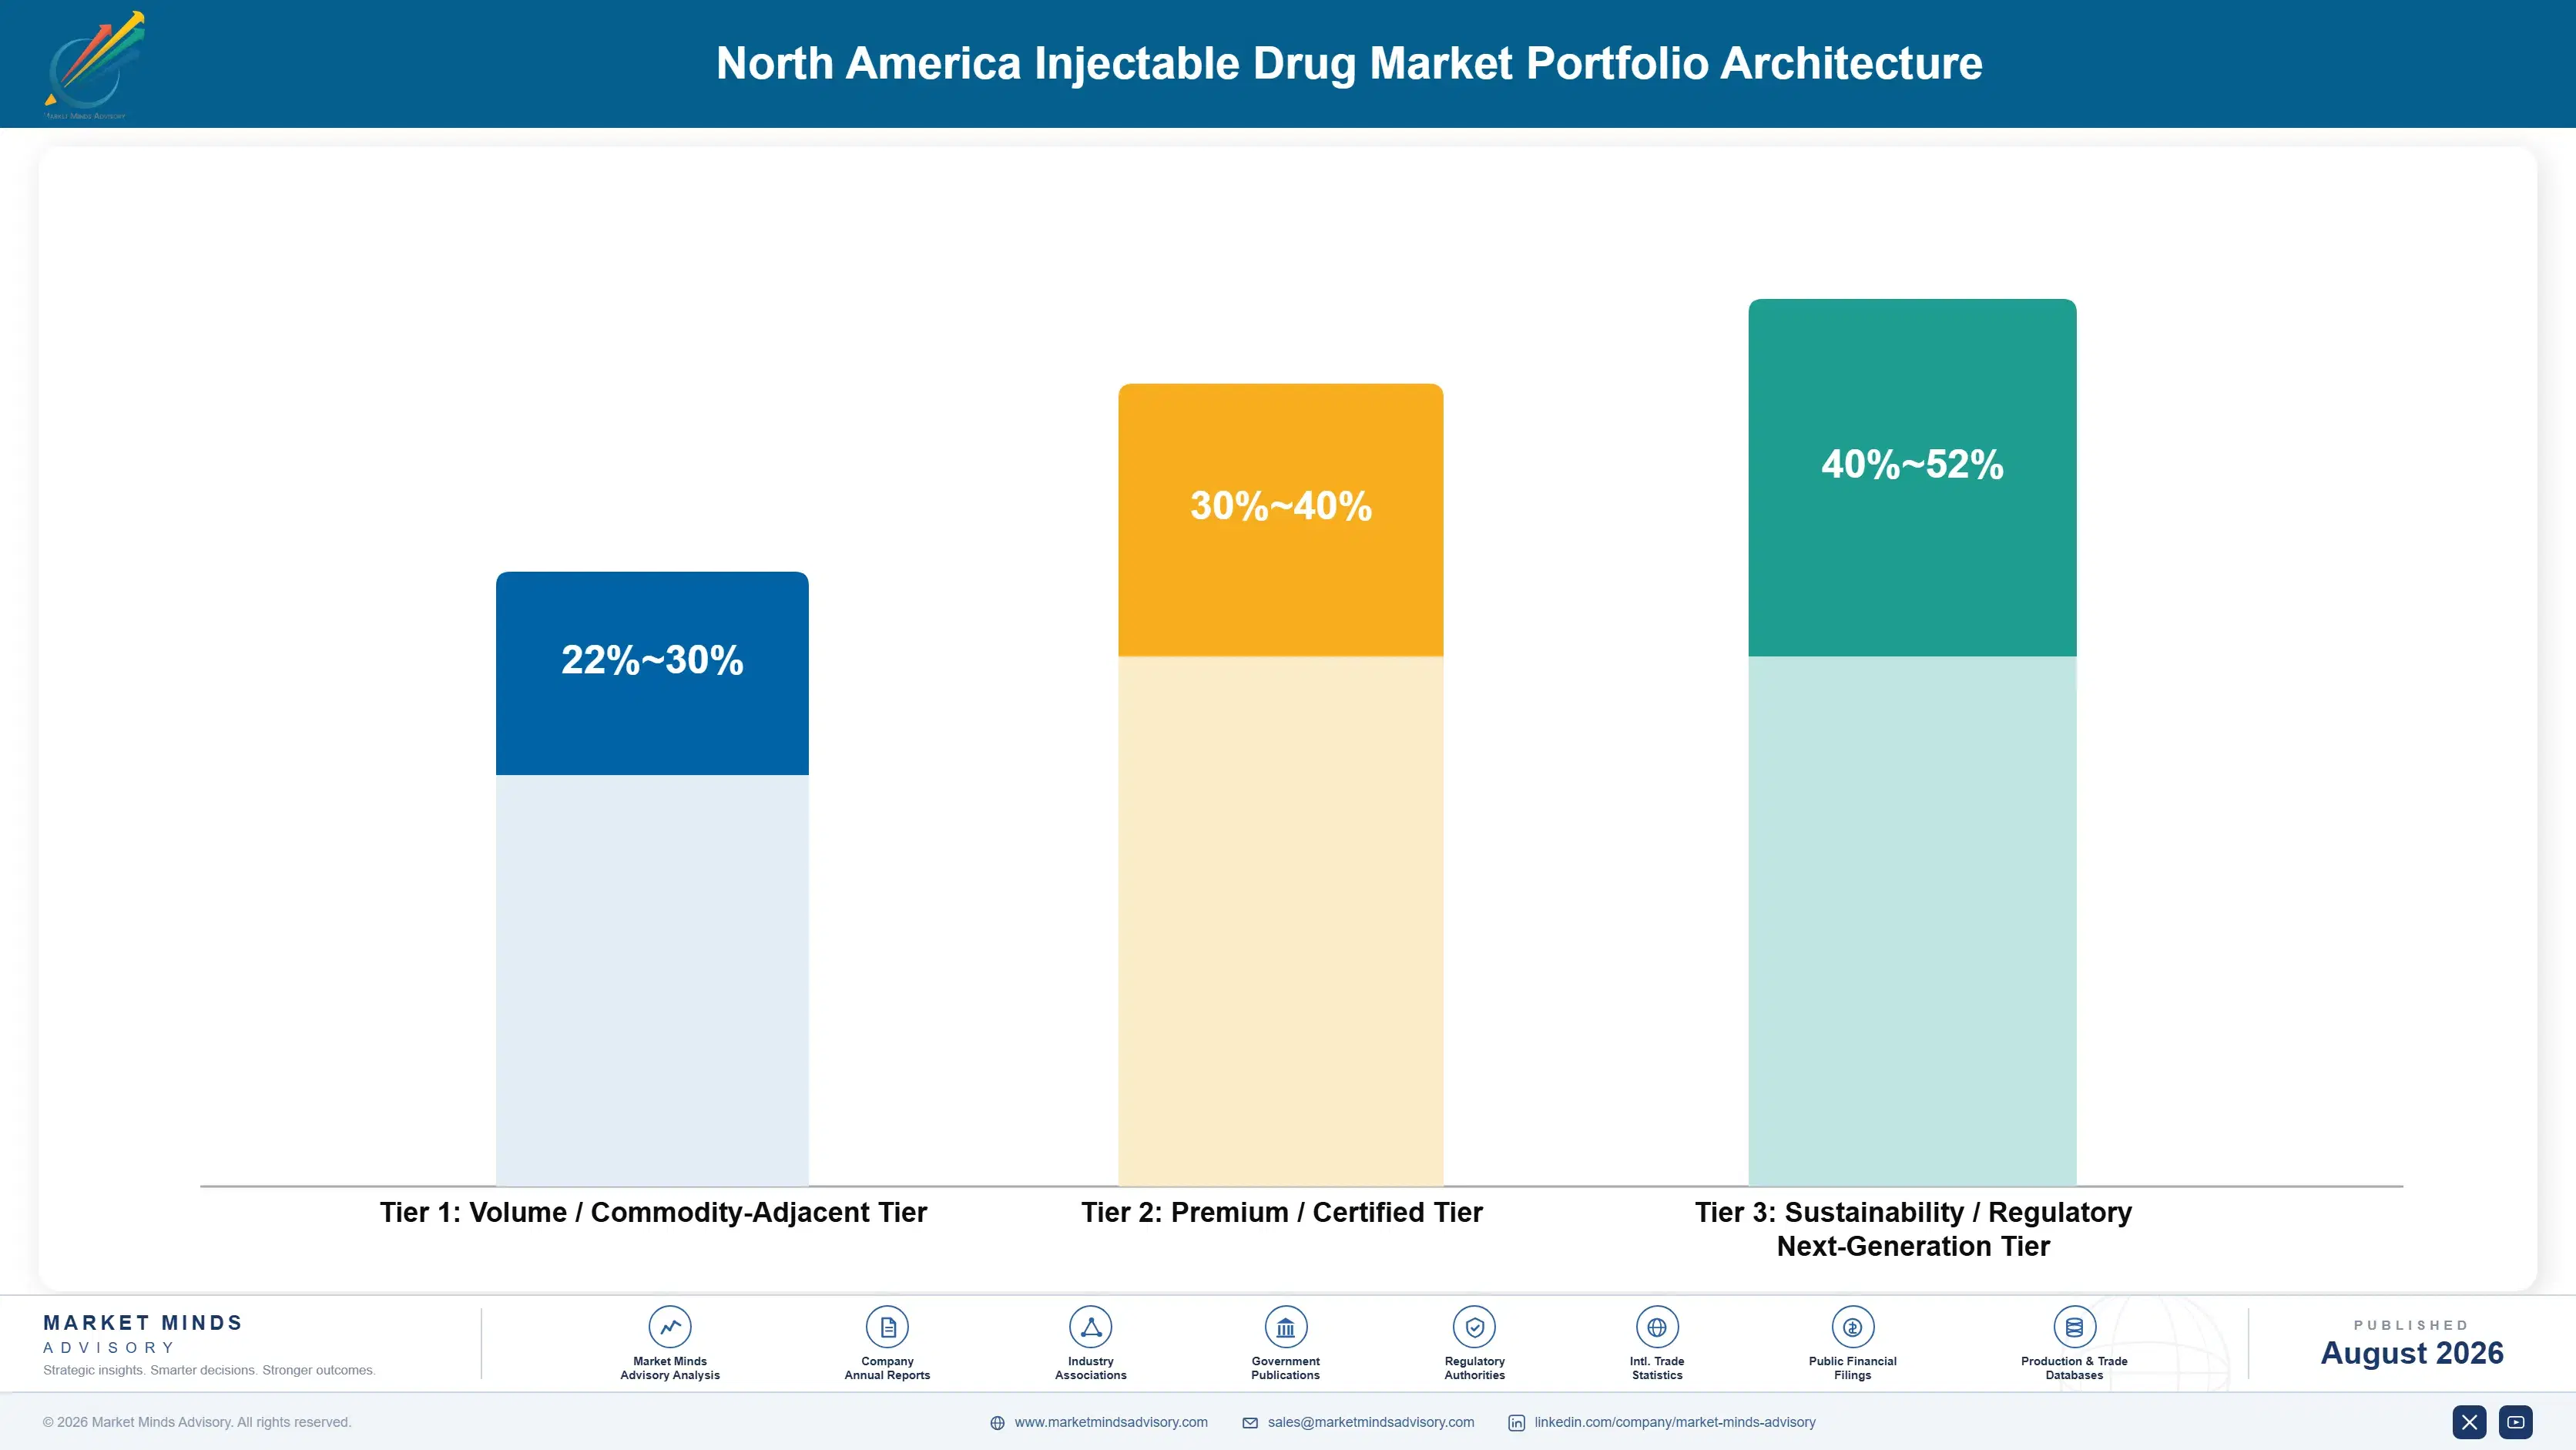
Portfolio economics split across three tiers. Standard monoclonal antibody products for established specialty programmes compete mainly on price in a moderately fragmented market shaped by years of manufacturing efficiency gains, while GLP-1 and biosimilar-defensive products command the highest margins, reflecting the clinical premium payers pay for capabilities standard products cannot deliver in high-value, differentiation-constrained applications built around modern metabolic disease requirem
The tension between volume and premium plays out most visibly in the transition period underway right now, where manufacturers must simultaneously defend mature monoclonal business generating predictable cash flow while investing heavily in GLP-1 capacity that may not reach profitable scale for several more years of platform ramp-up and payer qualification testing across multiple production programmes still working through clinical validation processes.

High-value margin pools concentrate in early payer formulary relationships and clinical outcome support programmes, where limited qualified competition keeps pricing power intact well past what the mature monoclonal segment retains after years of established, price-competitive manufacturing among a stable group of global manufacturers serving nearly every major application, across nearly every prescribing channel available today and every fiscal cycle beyond overall each year.

Volume / Commodity-Adjacent Tier

Standard monoclonal antibody products for established specialty programmes, competing primarily on price against multiple qualified global manufacturers with comparable manufacturing scale, delivery reliability, and payer network coverage nationwide each fiscal year.
Gross Margin: 22%-30%

Premium / Certified Tier

Standard GLP-1 and clinical-grade biosimilar products carrying established brand equity or proven reliability credentials across multiple payer and specialty prescribing platforms sold nationwide each year and every affected region and market segment today.
Gross Margin: 30%-40%

Sustainability / Regulatory / Next-Generation Tier

Differentiated, next-generation GLP-1 formats with integrated clinical outcome tracking capturing premium pricing during this early commercial adoption phase across leading payer platforms and mandate-driven segments today and every fiscal year beyond that as well.
Gross Margin: 40%-52%
north-america-injectable-drug-market-portfolio-architecture-1787300252768

High-value Sub-segments and Strategic Watch-out

Payer GLP-1 Formulary Design Wins

Early GLP-1 supply contracts on major payer formulary platforms combine high per-prescription value with the fastest specification growth in the category, as payers commit to the format across successive contract generations following initial validation and extended clinical testing programmes across multiple markets and customer segments each year.
Gross Margin: 38%-48%

Canada Domestic Manufacturing Infrastructure Contracts

Product supply agreements tied to Canada's national domestic manufacturing preference programme carry solid margins with a growth curve still accelerating rapidly, as domestic payers scale prescribing volume faster than most prior modernisation programmes have managed to date across comparable timelines now firmly in place today.
Gross Margin: 25%-35%

Established Monoclonal Specialty Base

Long-established monoclonal antibody demand generates steady, predictable revenue tied to product replacement cycles but carries thin margins after years of price-competitive manufacturing among a stable group of qualified manufacturers competing mainly on price and delivery reliability offered nationwide each year and abroad overall today across the industry.
Gross Margin: 22%-30%

Oral GLP-1 Substitution Platforms

Oral GLP-1 substitution platforms designed to replace injectable delivery with pill-based formats represent a strategic watch-out: it remains unclear how quickly payer acceptance and prescribing recognition will accumulate given unresolved validation questions tracked closely by MMA analysts across multiple regional jurisdictions and product categories each year.
Gross Margin: N/A pre-validation

Payer Formulary Cycle Economics

Injectable drug demand behaves like a per-payer formulary annuity rather than a purely discretionary purchase, since every operating covered population consumes prescribing resources regardless of how long that payer has followed prior formulary patterns, generating predictable recurring revenue tied directly to enrollment cycle volume rather than a one-time product sale negotiated and forgotten across every major healthcare network nationwide.
Adoption depth varies considerably by payer tier and clinical exposure. Specialty and metabolic disease programmes adopt GLP-1 formats fastest, since differentiation in these categories carries meaningfully higher practical consequence than in routine chronic disease management. Smaller regional payers and value-focused markets show far slower adoption, as budget constraints and functional standard products keep conventional monoclonal formats the default choice until demand pressure forces change.

A generational shift is underway in pharmacy benefit and formulary training programmes. Managers trained on demand-focused guidance after 2015 show meaningfully more comfort specifying GLP-1, technology-driven products than predecessors trained purely on conventional monoclonal technique, a shift that should widen GLP-1 adoption further as this cohort gains seniority within payer and pharmacy benefit organisations over the next decade across every major prescribing market nationwide.
north-america-injectable-drug-market-end-use-penetration-index-1787300253258

Positioning for the GLP-1 Transition

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / PAYER RELATIONSHIP TIMING

Engage formulary teams years before formal contract decisions

Manufacturers who wait for formal contract decisions to begin lose relationship opportunities to rivals who engaged payer formulary teams during early planning, well before any competitive bidding process starts. Eli Lilly's prescribing win success traces directly to years of early engagement with formulary teams that competitors are now scrambling to replicate across comparable programmes. Manufacturers without comparable early relationships face a lasting competitive disadvantage in payer sourcing that formal competitive bidding alone cannot fully overcome once contract decisions are already locked in for the coming budget cycle.
02 / TECHNOLOGY BRIDGE STRATEGY

Offer both monoclonal and GLP-1 options across tiers

Payer networks remain genuinely divided on whether to adopt full GLP-1 programmes immediately or continue relying on proven monoclonal formats for lower-risk populations. Manufacturers offering only one technology risk losing formulary decisions to buyers whose risk tolerance does not match that single technology choice at this particular point in the budget cycle. The most successful manufacturers maintain both monoclonal and GLP-1 product lines simultaneously, letting buyer risk assessment rather than manufacturer limitation determine which technology ultimately wins each formulary decision made across the payer.
03 / REGIONAL MANUFACTURING STRATEGY

Build local capacity ahead of content-linked pharmaceutical deadlines

Content-linked pharmaceutical investment programmes like Canada's domestic manufacturing preference increasingly determine which manufacturers win formulary decisions in fast-growing markets, yet several established manufacturers still treat regional manufacturing as a secondary consideration rather than a near-mandatory market entry requirement worth prioritising early on. That sequencing costs real formulary share during a market's critical early growth phase, when procurement moves fastest and decisions lock in for years. Manufacturers who establish local capacity ahead of infrastructure deadlines consistently outperform import-dependent competitors on formulary win rates.
04 / INPUT COST RESILIENCE STRATEGY

Diversify bioprocessing exposure before commodity volatility returns

Bioprocessing input price volatility during 2021 and 2022 forced several manufacturers to renegotiate fixed-price payer contracts at a loss, and bioprocessing exposure tied to standard-grade production now presents a comparable emerging risk few manufacturers have fully hedged against. Manufacturers still buying bioprocessing inputs on unhedged spot-market terms remain exposed to the same risk as production volume scales considerably over the coming years across major producing regions. Bioprocessing hedging has already proven its value for manufacturers who adopted it ahead of recent price volatility cycles.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
North America Injectable Drug Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on North America Injectable Drug Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-size regional health system network preparing for expanded GLP-1 formulary coverage across three specialty pharmacies, with annual prescription volume reported in the 82,000 to 116,000 prescription range (client-reported, unverified by MMA), evaluating supplier sourcing options ahead of a binding contract renewal deadline across multiple therapeutic categories and affiliated distribution partners nationwide.
STRATEGIC CHALLENGE
The network's pharmacy benefit team was divided between committing to a single premium manufacturer for maximum rebate consistency or running competitive tenders across multiple qualified suppliers for potentially lower unit cost, given internal disagreement over total cost of ownership across the network's expected multi-year contract timeline and validation cost assumptions used in financial modelling.
MMA APPROACH
MMA benchmarked comparable regional health system network sourcing decisions made by four networks over the prior three years, analysing product reliability, clinical outcomes, and total system cost across both procurement approaches under consideration. The team conducted primary interviews with pharmacy benefit staff and manufacturers actively bidding both contract structures in parallel across the industry.
KEY FINDINGS
  1. Single-supplier framework contracts offered meaningfully better clinical outcomes than multi-supplier tenders across every comparable therapeutic scenario reviewed in detail by the team.
  2. Three of four benchmarked networks had experienced at least one significant outcome gap under multi-supplier tendering due to formulary inconsistency outside their control.
  3. Multi-supplier tenders carried a 7 to 11 percent lower average unit cost given competitive pressure across multiple bidding rounds already proven at scale.
  4. Single-supplier mobilisation times ran approximately two months faster than multi-supplier alternatives across the benchmarked comparable programmes reviewed by the team overall each year.
CLIENT PROFILE
The client is a mid-size regional health system network preparing for expanded GLP-1 formulary coverage across three specialty pharmacies, with annual prescription volume reported in the 82,000 to 116,000 prescription range (client-reported, unverified by MMA), evaluating supplier sourcing options ahead of a binding contract renewal deadline across multiple therapeutic categories and affiliated distribution partners nationwide.
STRATEGIC CHALLENGE
The network's pharmacy benefit team was divided between committing to a single premium manufacturer for maximum rebate consistency or running competitive tenders across multiple qualified suppliers for potentially lower unit cost, given internal disagreement over total cost of ownership across the network's expected multi-year contract timeline and validation cost assumptions used in financial modelling.
MMA APPROACH
MMA benchmarked comparable regional health system network sourcing decisions made by four networks over the prior three years, analysing product reliability, clinical outcomes, and total system cost across both procurement approaches under consideration. The team conducted primary interviews with pharmacy benefit staff and manufacturers actively bidding both contract structures in parallel across the industry.
KEY FINDINGS
  1. Single-supplier framework contracts offered meaningfully better clinical outcomes than multi-supplier tenders across every comparable therapeutic scenario reviewed in detail by the team.
  2. Three of four benchmarked networks had experienced at least one significant outcome gap under multi-supplier tendering due to formulary inconsistency outside their control.
  3. Multi-supplier tenders carried a 7 to 11 percent lower average unit cost given competitive pressure across multiple bidding rounds already proven at scale.
  4. Single-supplier mobilisation times ran approximately two months faster than multi-supplier alternatives across the benchmarked comparable programmes reviewed by the team overall each year.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1 to 4): Finalise target therapeutic formulary requirements and confirm launch budget approval by category and site. Phase 2: Phase 2 (Months 5 to 10): Select a single-supplier framework for flagship specialty pharmacies while maintaining competitive tendering for lower-priority categories. Phase 3: Phase 3 (Months 11 to 18): Execute distribution mobilisation and begin formulary rollout ahead of the network's later renewal phases.
OUTCOME
The network selected a hybrid approach combining a single-supplier framework for flagship specialty pharmacies with competitive tendering for lower-priority categories, avoiding an estimated three to five month renewal delay across its initial deadline (client-reported, unverified by MMA). The decision reduced near-term outcome risk while preserving competitive pricing pressure on non-critical work.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the North America Injectable Drug Market?

The market reached an estimated 185.0 billion dollars in 2025, anchored by a mature monoclonal antibody base. Growth is concentrated in GLP-1 and biosimilar segments.

How large will the North America Injectable Drug Market be by 2036?

MMA projects the market will reach approximately 517.37 billion dollars by 2036 under the base-case forecast scenario. This reflects surging GLP-1 demand and biosimilar competition.

What is the CAGR for the North America Injectable Drug Market 2026 to 2036?

The base-case compound annual growth rate is 9.8 percent across the full ten-year forecast period. Bull and bear scenarios range from 8.4 to 11.0 percent.

Which segment is growing fastest?

GLP-1 and metabolic disease injectables lead at a 22.4 percent CAGR, roughly 2.29 times the overall market rate. Biosimilar injectables follow as the second-fastest segment.

Who are the major companies in the North America Injectable Drug Market?

Eli Lilly, Novo Nordisk, AbbVie, Pfizer, and Johnson & Johnson hold the top five positions by revenue. Biosimilar manufacturers are closing the GLP-1 gap each year.

Which country is growing fastest?

The United States leads at an estimated 10.2 percent CAGR, driven by its exceptionally large branded biologics prescribing base and growing metabolic disease demand. Dense specialty pharmacy infrastructure supports continued adoption.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Drug Class

  • Monoclonal Antibody Injectables
  • GLP-1 and Metabolic Disease Injectables
  • Biosimilar Injectables
  • Vaccine Injectables
  • Insulin and Diabetes Injectables

By End-Use Industry

  • Endocrinology and Metabolic Disease Care
  • Oncology and Specialty Care
  • Immunology and Autoimmune Disease Care
  • Preventive Medicine and Vaccination Programmes

By Commercial Dimension

  • Commercial Health Plan Formularies
  • Government and Public Health Programmes
  • Specialty Pharmacy Distribution Channel
  • Health System and Hospital Contracts

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
This market covers pharmaceutical products administered by injection and sold across the United States, Canada, and Mexico, including monoclonal antibody injectables, GLP-1 and metabolic disease injectables, biosimilar injectables, vaccine injectables, and insulin and diabetes injectables. It excludes oral and topical pharmaceutical formulations and injectable drug delivery devices sold separately from the pharmaceutical product itself.
Quantitative Units
USD billions (current prices); prescription volume by application where applicable
Segmentation Dimensions
By Drug Class; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Mexico, China, Germany, France, Switzerland, UK, Japan, South Korea, India, Australia, Brazil, Indonesia, Vietnam, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Russia, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Eli Lilly and Company, Novo Nordisk A/S, AbbVie Inc, Pfizer Inc, Johnson & Johnson, Merck & Co Inc, Bristol Myers Squibb Company, Sanofi SA, Amgen Inc, Regeneron Pharmaceuticals Inc, Roche Holding AG, Novartis AG, GSK plc, Teva Pharmaceutical Industries Ltd, Viatris Inc, Fresenius Kabi AG, Hikma Pharmaceuticals plc, Baxter International Inc, Samsung Bioepis Co Ltd, Sandoz Group AG
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-501
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full North America Injectable Drug Market Report (2026 to 2036).

The full report delivers a company-by-company pipeline tracker covering every major North American injectable drug manufacturer through 2030 with disclosed development timelines and anticipated regulatory milestones. It includes a payer reimbursement and clinical clearance policy tracker mapping coverage requirements across every profiled therapeutic category and region. Payer and pharmacy benefit manager adoption survey data is provided from MMA's primary research programme, alongside manufacturing cost benchmarking across major producing regions tracked closely. Buyers also receive a company-level financial and pipeline-milestone model updated quarterly throughout the subscription period each year.
Company-by-company clinical pipeline and development tracker
Payer reimbursement and clinical clearance policy database
Payer and pharmacy benefit manager survey data
Quarterly competitor financial and milestone model updates
Manufacturing cost benchmark and comparison data set
Custom sourcing strategy and procurement workshops

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts