Market Minds Advisory
Lumbosacral Radicular Pain Management Market

Lumbosacral Radicular Pain Management Market: Neurostimulation Redraws Chronic Pain Care

Spinal cord stimulation is displacing long-term opioid regimens for chronic radicular pain as coverage policy shifts toward device-based alternatives, forcing legacy pharmacological makers to defend volume against interventional neurostimulation platforms.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$4.4BMarket Size 2025
2036 FORECAST VALUE$10.2BBase Case , 2026 to 2036
CAGR 2026 TO 20368.0 %Bull 9.3% / Bear 6.7%
INCREMENTAL OPPORTUNITY$5.5BNet 10- year value creation
EXPANSION MULTIPLE2.16x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Lumbosacral radicular pain management has moved past long-term pharmacological regimens, as spinal cord stimulation and radiofrequency ablation let interventional pain physicians target nerve root pain directly rather than relying on systemic opioid therapy alone for years across a patient's full treatment course.
Spinal cord stimulation and radiofrequency ablation platforms are pulling ahead of every other product category, growing considerably faster than pharmacological pain management as physicians increasingly prioritise targeted neuromodulation over systemic drug therapy alone. Medtronic and Abbott still anchor much of the installed interventional pain relationships on decades of neurostimulation trust, but Nevro is undercutting integration complexity to win accounts across several categories, and North America consumes the largest share given the region's device reimbursement depth.
Competitive character splits between diversified neuromodulation majors defending broad device portfolios and specialist interventional pain makers competing on lead placement precision and clinical outcome depth. Regulatory clearance pathways for new stimulation waveforms remain more predictable than payer reimbursement cycles, which still vary considerably by individual country in how aggressively they cover device-based alternatives to opioid therapy across their national drug budget, annual review cycle, and long-term policy priorities.
Market Definition
The lumbosacral radicular pain management market covers devices, procedures, and products used to diagnose and treat radicular pain originating from lumbosacral nerve root compression or irritation, including spinal cord stimulation devices, radiofrequency ablation systems, epidural steroid injection products, minimally invasive lumbar decompression devices, nerve block and peripheral nerve stimulation devices, and pharmacological pain management products. It excludes general chronic pain management unrelated to lumbosacral radicular origin, spinal fusion surgical hardware, and diagnostic imaging equipment used for spine assessment.
Base Year Value
$4.4B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
8.0% base case. Bull 9.3%. Bear 6.7%.
Fastest Growth Segment
Spinal Cord Stimulation Devices: 12.5% CAGR
Fastest Growth Country
India: 11.5% CAGR
Fastest Growth Region
South Asia and Pacific: 10.0% CAGR
Largest Region
North America: 40% of 2025 global value
Market Leaders
Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Nevro Corp., Stryker Corporation. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Lumbosacral Radicular Pain Management Market Forecast Scenarios

lumbosacral-radicular-pain-management-market-size-forecast-scenario-1787306010707
Between 2020 and 2025 the market grew at a 7.0% historical CAGR, tracking general interventional pain device demand closely through most of the period. Spinal cord stimulation adoption only gained real momentum from 2023 onward as opioid alternative policy and payer coverage both expanded across major markets. Reporting that period remained limited given fragmented payer disclosure practices.
The base case carries the market to an 8.0% CAGR through 2036 on three mechanisms. First, interventional pain physicians increasingly specify spinal cord stimulation and radiofrequency ablation over long-term pharmacological therapy as targeted efficacy and safety both improve considerably across available platforms. Second, rising global chronic radicular pain diagnosis rates keep expanding the underlying treated patient pool. Third, expanding interventional pain infrastructure in developing markets keeps pulling new demand into standardised, device-based treatment formats.
The bull case reaches 9.3% if additional national health systems expand device reimbursement faster than currently modelled, pulling forward treatment adoption across a compressed access timeline. The bear case falls to 6.7% if device cost premiums stay elevated, keeping demand tied mostly to standard pharmacological replacement rather than new device specification across the broader category.

Why Neurostimulation Adoption Is Redrawing Treatment Pathways

Three forces converge on lumbosacral radicular pain management demand at once. Interventional pain physicians increasingly specify spinal cord stimulation and radiofrequency ablation over long-term pharmacological therapy as targeted efficacy and safety both improve across available neuromodulation platforms. Rising global chronic radicular pain diagnosis rates keep expanding the underlying treated patient pool. And expanding interventional pain infrastructure in developing markets keeps pulling
MARKET CONCENTRATIONCR5: 56%A handful of majors hold most interventional device share
AVERAGE SELLING PRICEUSD 850 to 32,000 per procedurePricing spans injections to full stimulation system implants
TOP PRODUCING COUNTRY SHAREUSA: 37% of device manufacturingDevice manufacturing keeps concentrating in this domestic base
CAPACITY UTILISATION70 to 82%Certified production lines run near committed capacity levels
INPUT COST SHARE28 to 36% of COGSBattery components and lead assemblies dominate recurring cost
REPLACEMENT CYCLE LENGTH5 to 9 years device lifecycleImplanted systems undergo staged battery replacement over time
Commercially, the market behaves like specialised neuromodulation device manufacturing rather than generic pain management hardware. Buyers specify by lead placement precision, stimulation waveform efficacy, and long-term outcome data rather than by price alone, because a device requiring early revision damages both patient outcomes and a physician's referral pipeline. That specification discipline protects margin for makers with genuine engineering depth and keeps generic device makers out of premium interventional pain contracts.
Over the next decade, stimulation waveform efficacy becomes the real differentiator between makers. Makers that combine neuromodulation engineering with verified long-term outcome data are capturing the premium interventional pain contracts increasingly dominating new specification spending, while pharmacological-only makers lose ground even where basic pain relief performance remains broadly comparable across most categories and geographies they serve.
"A stimulation system that needs an unplanned lead revision doesn't just cost a physician one procedure, it costs the practice's referral pipeline with the primary care doctors who send the next chronic pain patient, so buyers pay up for lead placement reliability long before they ever compare unit price."
Director, Interventional Pain and Neuromodulation Practice · MMA Medical Devices

Market Trends

Spinal Cord Stimulation Replaces Long-Term Opioid Regimens

Interventional pain physicians increasingly specify spinal cord stimulation over long-term opioid therapy for chronic radicular pain, since targeted neuromodulation delivers pain relief without the dependency and systemic side effect risk that opioid regimens carry across a patient's full treatment course and daily activity level. That clinical preference is pulling prescribing toward stimulation device makers even where procedure cost runs considerably higher than comparable pharmacological regimens, because payers increasingly recognise reduced long-term opioid dependency as offsetting device implant cost. Medtronic and Abbott have both expanded stimulation device indications specifically to capture patients previously managed on opioid-only regimens.
Market Impact: Requires 60%+ non-opioid pathway ac
Long-Term Outcome Data Becomes A Payer Coverage Requirement

Major national health systems increasingly require documented long-term outcome data before approving device-based pain therapy for full reimbursement, since unverified efficacy claims expose payers to genuine budget liability under tightening health technology assessment regulation across multiple jurisdictions worldwide and every device category considered today. That data requirement has converted outcome tracking from a scientific milestone into a standing procurement compliance line item that device makers cannot easily avoid at any meaningful scale. Boston Scientific and Nevro have both expanded outcome registry participation specifically to serve payers navigating tightening coverage decision requirements.
Market Impact: Expands treated pool 8-12% yearly

Market Opportunities and Growth Drivers

Opioid Alternative Policy Mandates Device-Based Treatment Access

Major national health systems and insurers in multiple markets increasingly enact binding opioid reduction policies that require pain management programmes to demonstrate measurable progress toward non-opioid treatment pathways, moving neurostimulation from a discretionary treatment option into a standing clinical requirement that pain programmes cannot avoid regardless of patient volume, budget cycle, or geographic footprint. That policy mandate has converted treatment protocol design from a physician preference into a standing regulatory compliance obligation that pain programmes must satisfy before accreditation renewal. Programmes increasingly build device access planning around opioid reduction target projections.
Market Impact: Raises procedure cost 300-450%

Rising Global Chronic Pain Diagnosis Expands The Treated Pool

Global chronic radicular pain diagnosis keeps expanding as rising imaging access and expanding interventional pain infrastructure pull more patients into formal device-based treatment pathways rather than delayed or undertreated chronic pain, particularly across markets where formal interventional pain infrastructure is still developing rapidly and unevenly across most regions and economies. That volume growth is considerably less cyclical than most device categories, since chronic pain treatment demand persists regardless of broader economic conditions or discretionary spending pressure. Health systems increasingly build interventional pain capacity planning around diagnosis and demographic trend projections.
Market Impact: Limits use to 55% of implants

Market Restraints and Challenges

Device Cost Premium Limits Adoption In Smaller Health Systems

Spinal cord stimulation systems cost considerably more per implant than conventional pharmacological regimens, a price gap that smaller and rural health systems absorb poorly across thin interventional pain budgets, the root cause being that implantable neurostimulation devices require meaningfully more precision engineering investment and battery technology than standard injection-based treatments. That cost gap keeps device adoption concentrated in well-reimbursed developed health systems, leaving smaller markets dependent on pharmacological therapy regardless of clinical preference. Makers are responding with tiered access programmes aimed specifically at closing that gap for smaller health systems.
Market Impact: Cuts opioid dependency risk 55-70%

Lead Migration Concerns Still Limit Long-Term Device Trust

Spinal cord stimulation leads still face genuine migration and mechanical reliability concerns among some physicians regarding sustained pain relief consistency over years of patient movement and daily activity across a full implant lifecycle and multiple battery replacement cycles that patients experience over their lifetime. That reliability concern limits adoption regardless of the targeted relief benefit physicians generally value, the root cause being that implanted leads experience considerably more mechanical stress than externally delivered treatments over comparable timeframes. Makers are responding by developing improved lead anchoring and migration-resistant designs across their full product range.
Market Impact: Requires registry data on 65%+ appr
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows product and technology type, the single clinical logic that determines treatment mechanism, invasiveness, and duration of effect of each product across the full category as a whole. Stimulation devices, ablation systems, injections, decompression devices, and pharmacological products each carry genuinely distinct treatment roles that are evaluated consistently throughout this entire report and framework.
lumbosacral-radicular-pain-management-market-market-share-analysis-1787306011240

Spinal Cord Stimulation Devices

Spinal cord stimulation devices grow fastest at 12.5%, about 1.56 times the market's 8.0% overall rate, as interventional pain physicians increasingly specify targeted neuromodulation over long-term opioid therapy across their full chronic pain patient panel and referral network. Medtronic still commands the largest share of stimulation device installations on established interventional pain relationships, but Abbott and Nevro are expanding competing platforms into overlapping premium hospital contract categories once considered defensible territory. Falling manufacturing costs are letting more mid-size pain programmes justify their first stimulation adoption without waiting for large academic centre capital commitments. Adoption concentrates first among academic interventional pain programmes before spreading into broader community pain clinic portfolios across every reimbursed market they serve.
CAGR 12.5%

Radiofrequency Ablation Systems

Radiofrequency ablation systems grow second-fastest at 10.0%, driven by physicians seeking a less invasive alternative to permanent implant therapy for patients with facet-mediated or nerve root pain that responds well to targeted thermal denervation across a broader range of pain presentations than stimulation devices typically address. Rather than requiring permanent device implantation, ablation systems let physicians deliver targeted nerve treatment through a temporary outpatient procedure with a faster recovery timeline. Boston Scientific and Stryker have both expanded radiofrequency ablation product lines specifically to serve physicians treating patients where permanent implant therapy carries unnecessary procedural risk. Adoption is fastest among patients with facet-mediated pain where ablation carries the highest clinical success rate.
CAGR 10.0%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Global demand concentrates where interventional pain infrastructure and overall opioid alternative policy depth run deepest today. North America leads by a very wide margin, Western Europe follows closely behind on established device demand, and East Asia trails given its considerably less mature device reimbursement overall.

North America

The United States drives regional demand through the world's deepest interventional pain device reimbursement coverage combined with the strongest opioid alternative policy push of any tracked market. Medtronic's domestic manufacturing base gives it genuine incumbency advantage in academic pain programme replacement tenders, competing against Abbott's broader neuromodulation technology positioning. Canada contributes a smaller layer through comparable interventional pain demand tied closely to shared clinical training networks. Growth of 8.0% reflects continued device adoption and expanding diagnosed treatment pool across the region's major pain management centres. This region's share sits above the standard band because the United States concentrates the deepest device reimbursement access and strongest opioid policy push of any market tracked.
Share: 40% | CAGR: 8.0% (2026 to 2036)

Western Europe

Germany, France, and the United Kingdom anchor demand through established interventional pain programme infrastructure and national health system coverage that continues expanding across device categories and treatment settings. Boston Scientific's regional manufacturing partnerships give it genuine advantage across German and broader European academic accounts, competing against Nevro's chronic pain positioning in adjacent categories. National reimbursement timelines vary considerably by country, with larger economies moving faster than smaller markets working through longer technology assessment cycles. Growth of 6.5% trails the market's overall rate as the region's device coverage is already relatively advanced, shifting emphasis toward incremental outcome improvement. Cross-border health technology assessment alignment keeps device standards broadly consistent across neighbouring national systems and payer bodies.
Share: 26% | CAGR: 6.5% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
lumbosacral-radicular-pain-management-market-country-cagr-analysis-1787306011745

Where Interventional Pain Makers Can Defend Margin

Payer negotiation increasingly favours makers who can demonstrate both lead placement precision and long-term clinical outcome data across their full treated population and reimbursement history. The four levers below capture revenue before a reimbursement cycle locks national coverage terms rather than after, rewarding makers who prove clinical value credibly across a payer's full diagnosed population.

Bundle Devices With Patient Trial Programme Contracts

Device specification increasingly happens during initial national reimbursement negotiation rather than during later individual patient trial requests, when coverage terms and support commitments are already fixed and costly to change midstream once locked in place permanently and irreversibly. Makers that place clinical support specialists inside reimbursement negotiation teams from the outset capture the full diagnosed population scope rather than competing for smaller individual exception approvals later. Medtronic reports that national agreements bundling devices with patient trial programmes carry realised revenue roughly 20% higher than exception-based access on comparable diagnosed populations.
Market Impact: Lifts realised revenue roughly 20%

Sell Long-Term Outcome Registry Data Alongside Device Launches

National payers increasingly want documented, longitudinal outcome data before committing to full national device reimbursement at scale, and makers offering outcome registry support are capturing recurring reimbursement renewal loyalty worth 9 to 15% more in realised revenue per national market compared with launches lacking registry commitments across comparable countries and populations facing similar budget constraints and negotiation timelines each renewal cycle. That registry commitment extends payer relationships across multiple reimbursement renewal cycles rather than a single negotiation. Abbott has expanded its outcome registry programme specifically to capture this loyalty layer.
Market Impact: Adds 9-15% more revenue per nationa

Build Tiered Access Programmes For Smaller Pain Centres

Smaller regional pain centres cannot justify full list price device access at the scale of the largest academic programmes, yet they represent a large, historically underserved diagnosed population that the leading device makers previously found less economical to pursue directly at scale. Makers offering tiered pricing programmes with income-adjusted access capture this segment at a fraction of the full list price cost, cutting the effective entry price by roughly 33% for smaller, budget-constrained centres entering reimbursement negotiations. Nevro has scaled exactly this tiered approach across smaller pain centres since 2023.
Market Impact: Cuts entry price by roughly 33% for

Target National Pain Management Programme Framework Agreements

National pain management programmes coordinating reimbursement standards across dozens of treatment centres increasingly want one negotiated national framework rather than a different access pathway at every centre, which shifts the purchasing decision upstream to a small number of national health authority negotiators making one decision at once across the network and its annual budget cycle. Securing a framework agreement covering a country's full diagnosed population delivers revenue that no number of individual centre negotiations can match. Boston Scientific has pursued exactly this framework approach with several national pain programmes since 2022.
Market Impact: Locks in reimbursement across 100%

Who Controls the Margin Pool

Concentration sits at CR5 56%, moderately consolidated for a category built on established neuromodulation franchises with meaningful clinical trial investment behind each. Medtronic and Abbott lead on manufacturing scale and interventional pain relationships, while the gap to challengers like Nevro is more about outcome data depth than manufacturing scale. All participants are assessed on one consistent basis, interventional pain device revenue.
Current competitive activity runs across three dimensions. Product development concentrates on stimulation waveform efficacy to close the gap with pharmacological therapy. Outcome data investment focuses on verified long-term pain relief rather than launch trial data alone. And account structure centres on national pain management programme framework agreements rather than one-off centre negotiations, a shift that rewards makers with genuine multi-country reimbursement capability.

Emerging pressure comes from specialist neuromodulation biotechs targeting the lead-migration-sensitive patient minority that leading platforms' mechanisms still struggle to serve confidently, a segment global payers once assumed would remain permanently uncertain. Rankings will shift toward makers who combine stimulation depth with proven long-term outcome credentials, since that combination is what national health authorities increasingly require for full reimbursement. Makers without a credible outcome data pipeline face the sharpest exposure ahead.
lumbosacral-radicular-pain-management-market-company-positioning-matrix-1787306012259

Competitive Moat and Risk Dimensions

MEDTRONIC PLC

Moat: Deep clinical trial scale

Medtronic holds a well-established neuromodulation franchise built on over a decade of accumulated clinical trial data and interventional pain relationship history, giving it a genuine credibility advantage that newer entrants without comparable regulatory history cannot easily replicate quickly, even with substantial capital investment behind them.
MEDTRONIC PLC

Risk: Exposed to ablation substitution pressure

Medtronic's core stimulation implant franchise faces increasing competition from radiofrequency ablation platforms that address a broader lower-invasiveness patient population, since those emerging mechanisms work through fundamentally different commercial pathways across a growing pipeline of competing programmes, payer negotiations, clinical trial designs, and various reimbursement models.
ABBOTT LABORATORIES

Moat: Deep neuromodulation channel reach

Abbott draws on decades of accumulated neuromodulation commercialisation and interventional pain physician relationship depth from its wider diagnostics business, giving it a genuine advantage reaching payer formulary committees that competitors without comparable channel infrastructure cannot easily replicate quickly across comparable price tiers and account sizes.
ABBOTT LABORATORIES

Risk: Exposed to reimbursement negotiation pressure

Abbott's broad neuromodulation portfolio sometimes trades off against the reimbursement negotiation leverage that fast-scaling specialist platforms increasingly demand, leaving open room for smaller competitors to win narrow neuromodulation niches purely on clinical differentiation alone in several developing regions, mid-tier accounts, and various academic research partnerships.

Players Tracked

Prominent Players

Medtronic plc
Abbott Laboratories
Boston Scientific Corporation
Nevro Corp.
Stryker Corporation

Other Key Players

Saluda Medical Pty Ltd
Nalu Medical Inc.
SPR Therapeutics Inc.
Avanos Medical Inc.
Diros Technology Inc.
Vertos Medical Inc.
Relievant Medsystems Inc.
Persica Pharmaceuticals Ltd
Cerebral Therapeutics Inc.
PainTEQ LLC
Cirtec Medical Corporation
Xalud Therapeutics Inc.
DiscGenics Inc.
SI-BONE Inc.
Ethos Laboratories

Recent Developments

FEBRUARY 2025

Medtronic launches next-generation closed-loop spinal cord stimulation system

Medtronic introduced a new closed-loop spinal cord stimulation system with automated dose adjustment addressing variable pain intensity across patient movement and daily activity levels and every clinical setting. This was an organic product launch rather than an acquisition, extending Medtronic's addressable chronic pain patient coverage into new segments.
Signal: Closed-loop dose adjustment is quickly bec
AUGUST 2025

Abbott acquires specialty outcome analytics technology company

Abbott completed the acquisition of a specialty outcome analytics technology company with proprietary long-term pain tracking software built for payer reimbursement decision teams and broader clinical reporting systems worldwide. The deal brought advanced analytics capability in-house, expanding Abbott's offering considerably beyond its prior hardware-only product line.
Signal: Outcome analytics technology is becoming a
MAY 2025

Nevro signs national reimbursement framework agreement with pain programme

Nevro entered a multi-year reimbursement framework agreement with a national pain management programme covering stimulation device access across the country's full diagnosed patient population. The agreement was a commercial reimbursement contract, not a joint venture or equity transaction, covering coverage across the programme's full patient roster.
Signal: Multi-year, national reimbursement framewo

Battery Component And Lead Assembly Exposure

Battery components and implantable power systems run 28 to 36% of COGS, sourced from a concentrated set of specialty medical battery manufacturers that also supply the wider implantable device industry across multiple product categories and geographies. Lead assemblies and precision electrode components add a further 20 to 28%, with quality certification and testing accounting for most of the remainder.
The global battery supply disruption running through 2021 and 2022 hit implantable device production directly, since specialty medical battery cells, sourced substantially from a concentrated set of manufacturers, faced extended shortages that rippled through downstream device makers. Medtronic's 2022 Annual Report disclosed elevated component costs and extended lead times across its neuromodulation segment, attributing part of the pressure to battery allocation constraints that persisted through much of the year overall.

Exposure varies sharply by player type. Vertically integrated majors like Medtronic manufacture much of their own battery formulation in-house, insulating them from the worst allocation constraints, while smaller specialists depend on third-party battery suppliers and absorb price spikes directly into thinner margins. Geography matters too, since makers sourcing components domestically face meaningfully different exposure than those depending on imported material.
lumbosacral-radicular-pain-management-market-cost-volatility-analysis-1787306012454

Dual-Source Battery Components From Separate Suppliers

Qualifying device designs against battery components from two separate suppliers, rather than one, keeps a shortage at either supplier from halting production entirely across the whole manufacturing network worldwide and across every product line and region. Several makers adopted dual-sourcing as standard practice after the 2021 disruption exposed how concentrated their supply chains genuinely were.

Vertically Integrate Battery Formulation Where Feasible

Manufacturing battery formulation in-house rather than sourcing it externally insulates the very largest makers from allocation shortages during industry-wide supply disruptions and price spikes alike across most product categories and geographies. Smaller specialists lacking that scale have instead pursued long-term supply agreements with established battery manufacturers to secure priority allocation, considerably reducing spot-market exposure.

Shift Product Mix Toward Value-Added Stimulation Systems

Premium stimulation and closed-loop systems carry considerably better margin resilience against battery price volatility than standard ablation formats, giving makers a durable way to protect blended margin over time by shifting revenue mix toward differentiated products across their portfolio. That shift has meaningfully improved margin stability across portfolios facing sustained feedstock pressure this decade.

Portfolio Architecture for Margin Defence

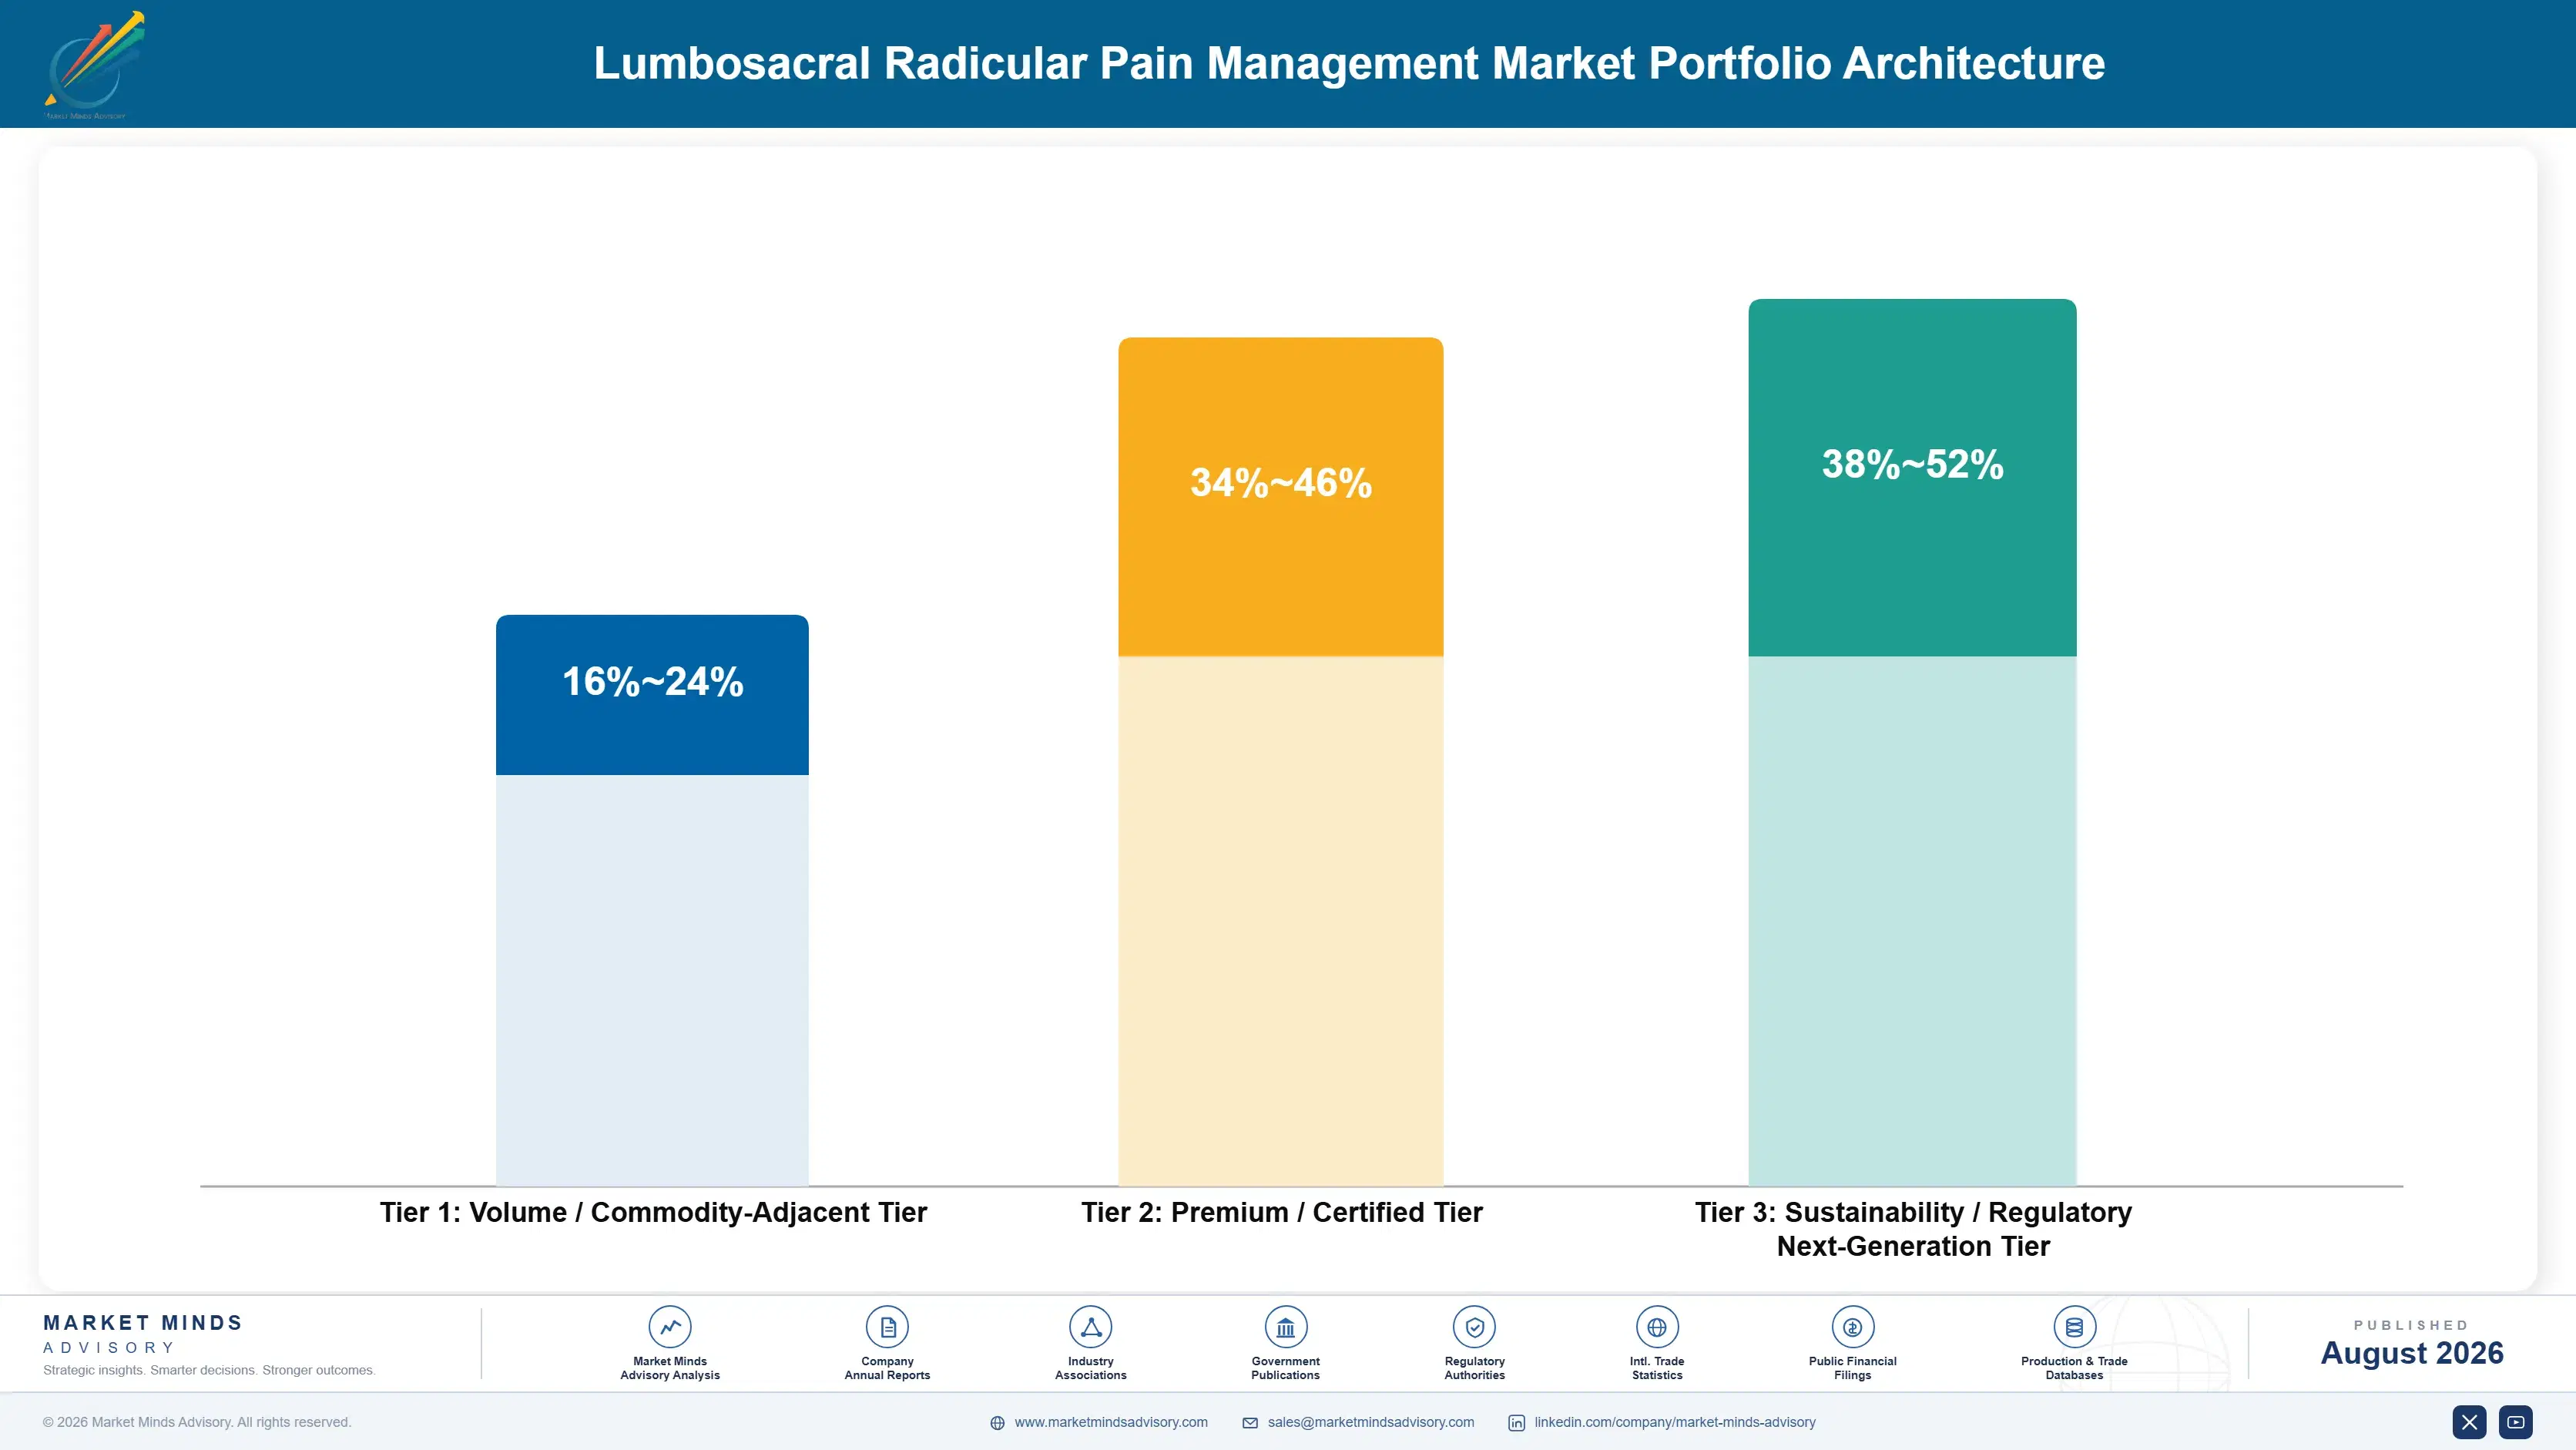
The portfolio splits into three tiers with real margin separation, and the gap between tiers has widened as outcome data depth becomes a genuine differentiator rather than an incremental feature. Volume-tier pharmacological products compete on price against generic manufacturers and earn modestly. Premium stimulation and framework-negotiated formats earn considerably more because they solve a genuine chronic pain problem that payers cannot engineer around cheaply.
The tension is between pharmacological volume and per-country negotiated device margin. Makers selling pharmacological products in bulk push hard on unit price, while national pain management programmes standardising on device framework agreements pay for lead placement precision and outcome data depth rather than negotiating down to the last dollar on every single prescription. Makers serving both categories run genuinely different commercial motions under one broader disease area.

High-value pools concentrate in stimulation and ablation formats sold with outcome registry programmes and national framework agreements, where switching cost runs highest and price sensitivity lowest given the differentiated clinical evidence base. Legacy pharmacological business remains meaningful in volume but persistently thin in margin, as payers increasingly treat it as a supportive-care purchase rather than a differentiated one worth defending.

Volume / Commodity-Adjacent Tier

Pharmacological products sold into routine supportive care regimens, priced against generic manufacturers on thin margin. Payers negotiate primarily on unit price rather than disease-modifying differentiation, keeping this tier's margin persistently compressed.
Gross Margin: 16-24%

Premium / Certified Tier

Stimulation and framework-negotiated formats sold into national programmes standardising reimbursement protocols across their full diagnosed population and treatment centres. Payers pay for lead placement precision and outcome data depth rather than for chemistry alone.
Gross Margin: 34-46%

Sustainability / Regulatory / Next-Generation Tier

Advanced closed-loop and ablation systems bundled with outcome registry support sold to national pain programmes and specialty centres seeking documented compliance. Margin reflects both technology differentiation and recurring specification loyalty over time.
Gross Margin: 38-52%
lumbosacral-radicular-pain-management-market-portfolio-architecture-1787306012954

High-value Sub-segments and Strategic Watch-out

Spinal Cord Stimulation Devices

High value and high growth at 12.5%, the fastest segment, as physicians increasingly specify targeted neuromodulation over long-term opioid therapy across their full chronic pain patient panel and referral network. Medtronic and Abbott dominate current manufacturing scale, though challengers are closing the gap fast this cycle.
Gross Margin: 38-52%

Radiofrequency Ablation Systems

High value with strong growth at 10.0%, favoured wherever physicians need a less invasive alternative to permanent implant therapy for facet-mediated pain across every treatment setting, referral pathway, and payer system. Boston Scientific and Stryker lead current ablation adoption broadly across mainstream and premium accounts alike.
Gross Margin: 34-46%

Epidural Steroid Injection Products

The volume core, well established across standard treatment pathways, competing on price against generic manufacturers in most non-specialised applications and contract categories across every major market and geography worldwide today. Growth here tracks standard replacement volume broadly rather than any new demand or premium upgrades.
Gross Margin: 16-24%

Pharmacological Pain Management Products

The strategic watch-out. Commoditisation and clinical substitution toward device-based therapy threaten a persistent margin decline as opioid alternative policy increasingly reduces reliance on systemic drug regimens across most reimbursed patient populations, geographies, account tiers, national drug budgets, and annual reimbursement negotiation cycles going forward considerably.

Recurring Device Follow-Up Revenue

Demand behaves like an annuity once a patient receives an implanted device, because chronic radicular pain management remains an ongoing clinical need requiring continuing device programming and battery replacement throughout a patient's treatment journey and requires renewed reimbursement alongside continuing outcome monitoring. That continuity, plus the underlying diagnosed pool expansion demand it eventually triggers, gives makers a predictable revenue tail well beyond any single implant sale
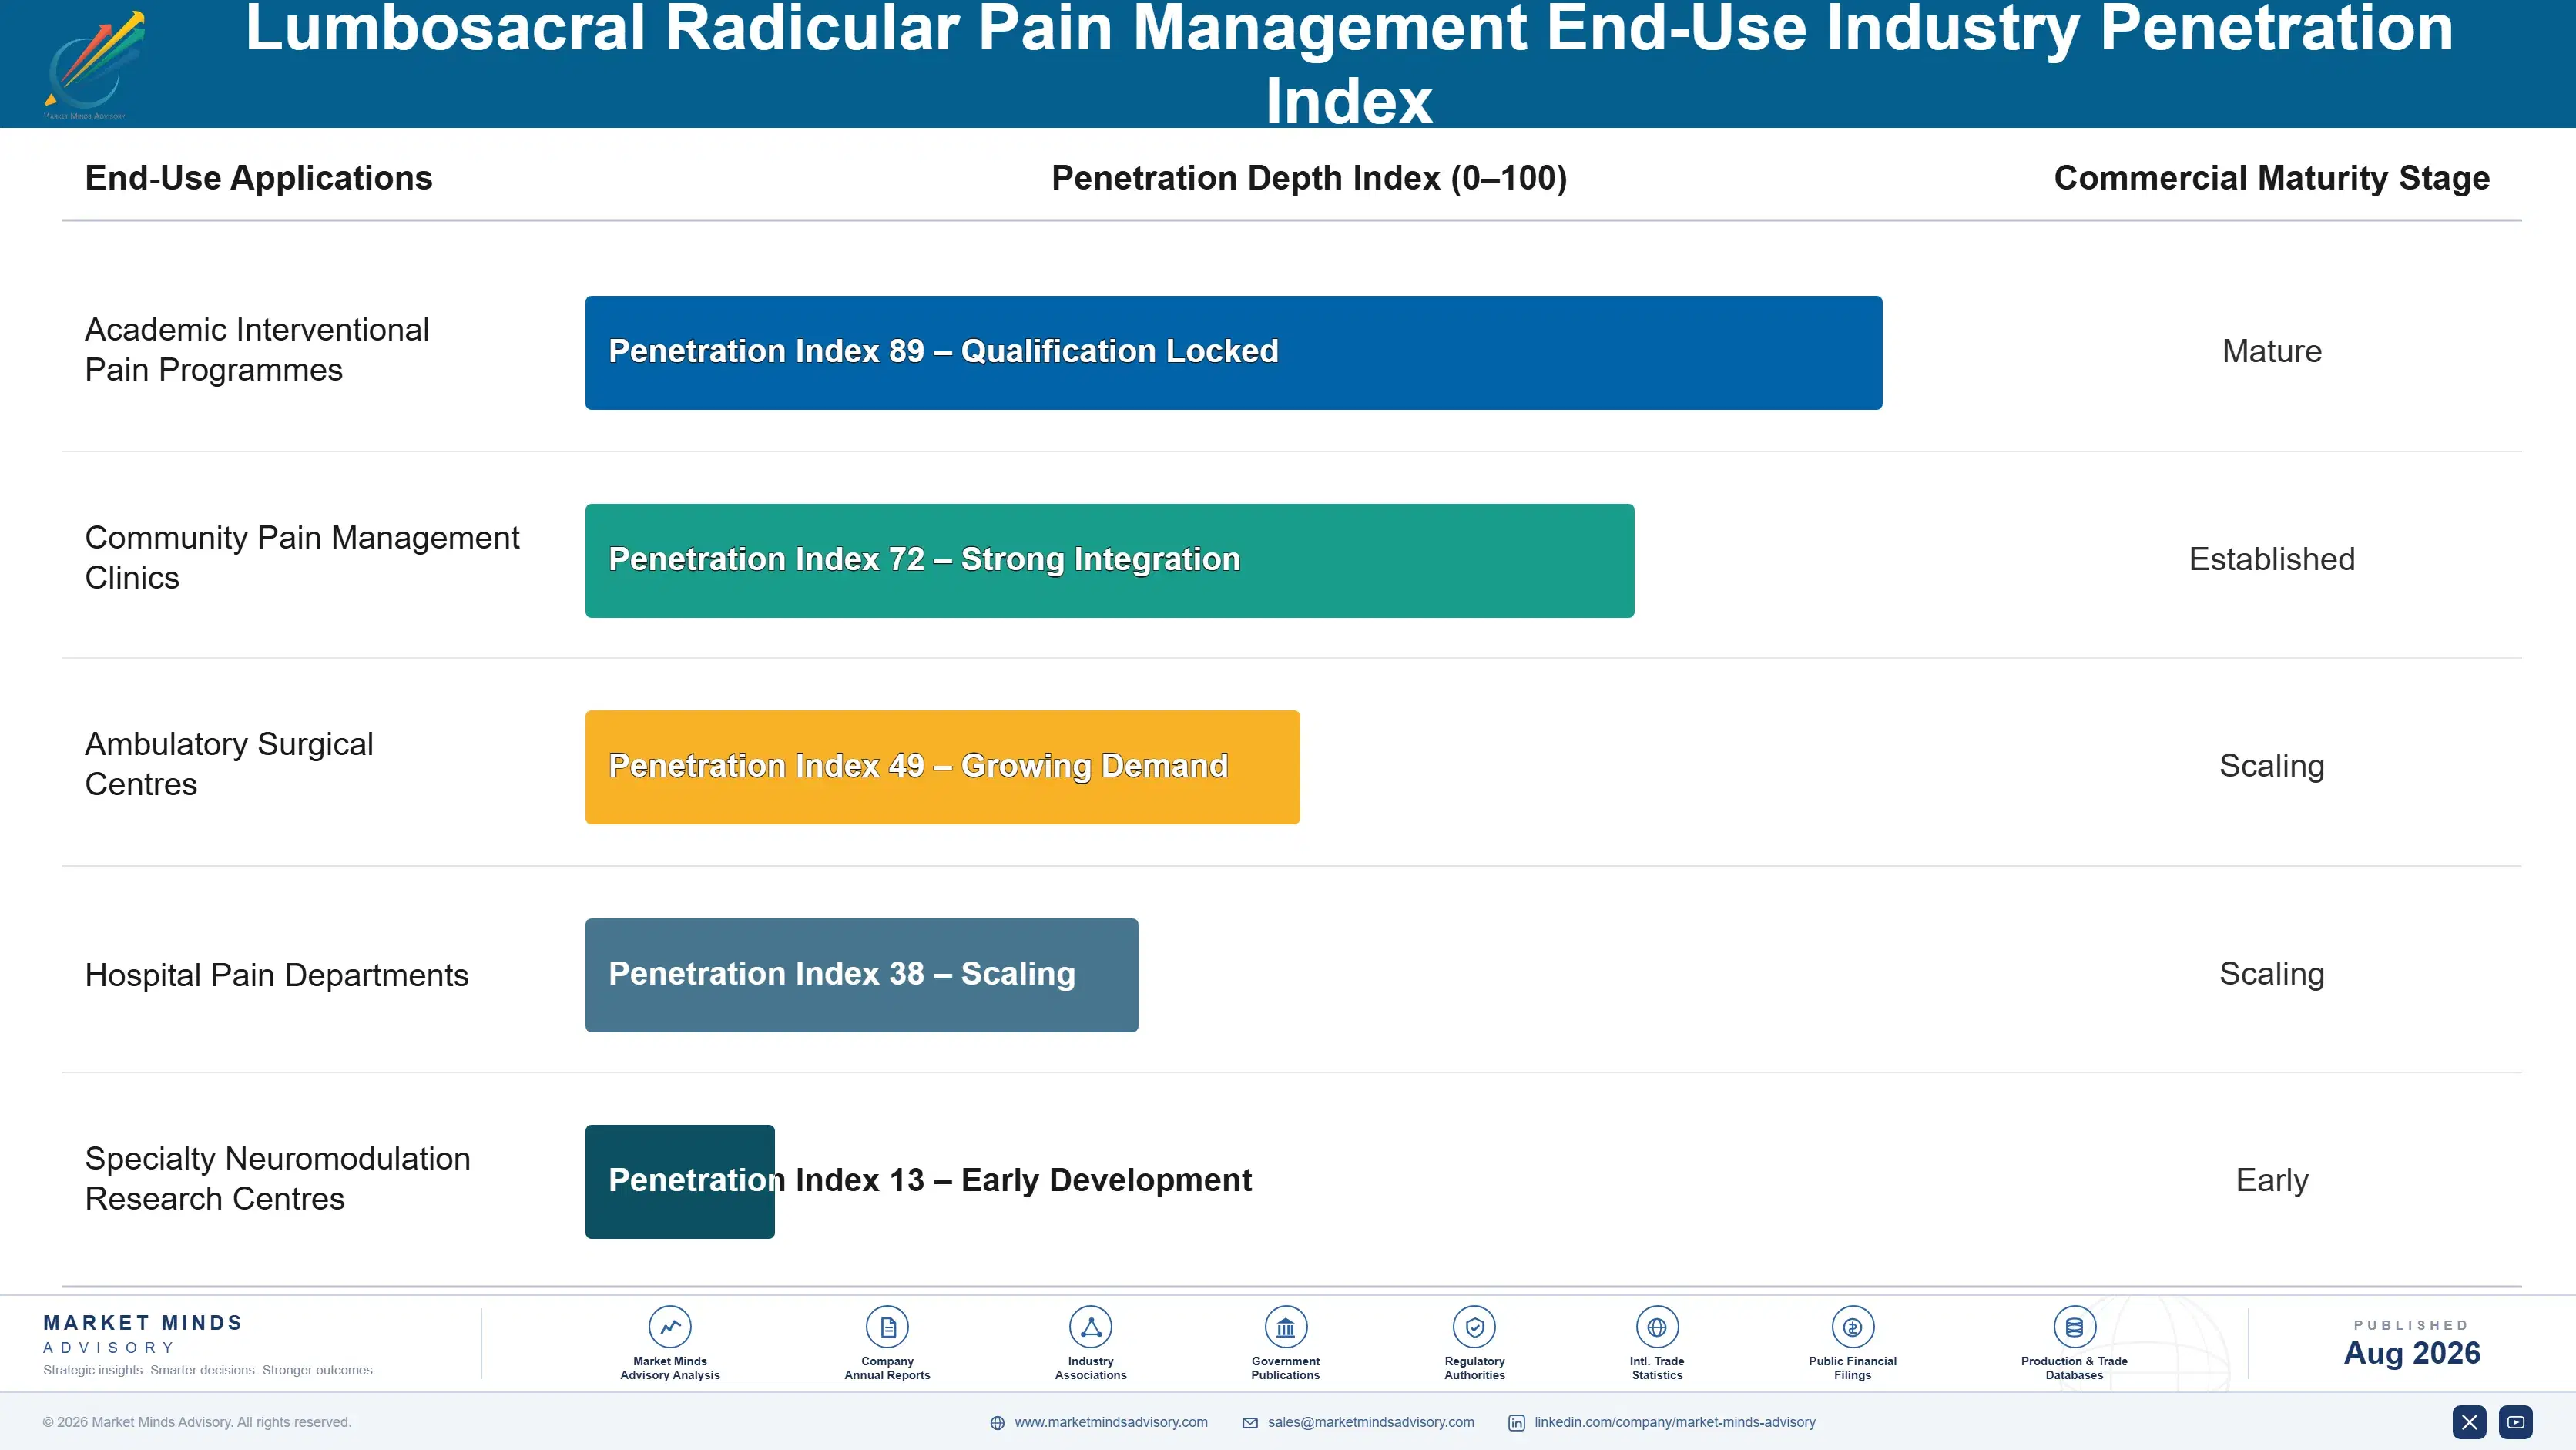
Adoption depth varies sharply by patient vertical. Newly diagnosed chronic pain patients adopt stimulation therapy fastest and deepest, since earlier device implantation directly improves long-term pain control outcomes across their full treatment journey. Post-surgical patients follow closely on ablation adoption, chasing comparable outcomes at a somewhat slower pace given established pharmacological treatment habits. Opioid-dependent patients adopt more slowly, often waiting for a payer coverage decision or physician recommendation to force the treatment decision.

Buyer profiles are shifting generationally. Prescribing once sat with individual physicians evaluating single treatment platforms on their own; it now increasingly involves national health authority reimbursement committees who specify coverage standards before a single physician orders a device at all. That shift moves the real access decision earlier into the national negotiation cycle, well ahead of any single patient's treatment order.
lumbosacral-radicular-pain-management-market-end-use-penetration-index-1787306013444

Where Radicular Pain Management Value Concentrates

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / NEUROMODULATION ADOPTION STRATEGY

Targeted Stimulation Now Decides Patient Share

Spinal cord stimulation devices are growing at 12.5%, about 1.56 times the market's 8.0% overall rate, and that gap is widening as physicians increasingly specify targeted neuromodulation over long-term opioid therapy across their full chronic pain patient panel. Makers still anchored on pharmacological therapy alone risk losing the fastest-growing, highest-margin national framework contracts to rivals offering proven stimulation capability already deployed at scale. The window to build credible neuromodulation capability is closing within this forecast period, and makers who act now capture the largest contracts.
02 / OUTCOME DATA STRATEGY

Verified Long-Term Data Is Becoming Table Stakes

National pain management programmes increasingly refuse to commit full reimbursement without documented, longitudinal outcome registry data, since unverified launch trial claims represent a genuine budget liability risk under tightening health technology assessment regulation across multiple jurisdictions worldwide today. Makers who build this registry capability capture recurring reimbursement renewal loyalty and preferred-therapy status that launch-data-only competitors cannot easily replicate at comparable scale. Those without a credible outcome registry programme will find themselves facing renewal negotiation risk, losing meaningful value to better-equipped rivals.
03 / NATIONAL PROGRAMME CHANNEL

National Frameworks Will Outgrow Centre-By-Centre Access

National pain management programmes are increasingly folding reimbursement negotiation into corporate health authority standards rather than leaving it to individual physicians, concentrating real purchasing power in a small number of framework decisions that smaller makers cannot easily access at scale. Makers who secure framework status with major national programmes capture revenue across an entire diagnosed population that no number of individual centre negotiations can replicate on comparable terms. Those still negotiating purely centre by centre risk being locked out of this fastest-growing channel entirely and permanently.
04 / REGIONAL MANUFACTURER PRICING

Regional Device Makers Will Keep Pressuring Standard Pricing

Regional device manufacturers have scaled fast enough to attract meaningful clinical trial investment for patients that leading platforms once assumed would remain permanently underserved, and that competitive pressure is starting to spread into broader neuromodulation categories as device technology matures. Makers competing purely on price against regional manufacturer scale will struggle to hold long-term category leadership. The more durable response is competing on outcome data depth and validation credentials, categories where the leading platforms still hold a meaningful lead today.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Lumbosacral Radicular Pain Management Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Lumbosacral Radicular Pain Management Exposure Evaluation 2025-26
CLIENT PROFILE
A national pain management programme covering a mid-size country's full eligible chronic pain population approached MMA after facing budget pressure to expand spinal cord stimulation reimbursement to newly eligible patient subgroups. The client reported that inconsistent access criteria across its regional health authorities was creating equity and budget forecasting risk that leadership considered urgent to resolve before the next budget cycle (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
The programme had negotiated device access for its original approved high-severity population years earlier without a structured plan for absorbing subsequent coverage expansions, assuming gradual case-by-case exception approval would suffice. The accelerating pace of clinical validation data and physician demand forced leadership to confront how far behind current budget forecasting models its programme had fallen, with a fixed annual device budget.
MMA APPROACH
MMA benchmarked the programme's reimbursement readiness against comparable national programmes already absorbing multiple coverage expansions, quantifying the budget impact a structured multi-year framework would realistically require. We evaluated tiered access options sized to each patient subgroup's clinical priority, and modelled a phased reimbursement schedule against the programme's fixed annual budget.
KEY FINDINGS
  1. The programme's existing case-by-case exception process showed considerably longer patient access timelines than comparable programmes already working with structured multi-year frameworks, based on benchmarking performed during the review.
  2. A tiered reimbursement approach concentrated on the programme's highest-severity patient subgroup addressed most of the equity risk without requiring simultaneous coverage of every severity category immediately.
  3. Modelling showed the programme's fixed budget could absorb high-severity expansion within twelve months but would require phased moderate-severity coverage to avoid an immediate budget overrun.
  4. Phasing reimbursement by patient subgroup rather than attempting simultaneous full coverage considerably improved the programme's budget forecasting accuracy during the review window (client-reported, unverified by MMA).
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 6 months): Extend reimbursement to the programme's highest-severity patient subgroup first, prioritising those facing the most time-sensitive treatment windows. Phase 2: Phase 2 (6 to 18 months): Extend coverage to remaining moderate-severity patient subgroups across the programme's full population, validating budget forecasting accuracy at each stage. Phase 3: Phase 3 (18 to 36 months): Fold the phased reimbursement approach into the programme's standing device budget process going forward, reviewing coverage decisions annually.
OUTCOME
The programme extended reimbursement to its highest-severity patient subgroup ahead of its budget deadline and reported no equity gaps during the following review period. The phased reimbursement approach has since extended to its remaining moderate-severity patient subgroups facing later coverage decisions (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Lumbosacral Radicular Pain Management Market?

The market was valued at USD 4.4 billion in 2025, with demand concentrated in stimulation and pharmacological therapy formats across major interventional pain markets worldwide.

How large will the Lumbosacral Radicular Pain Management Market be by 2036?

The market is projected to reach USD 10.25 billion by 2036, an expansion multiple of 2.16 times its 2026 value. Neuromodulation adoption drives much of that growth.

What is the CAGR for the Lumbosacral Radicular Pain Management Market 2026 to 2036?

The base case CAGR is 8.0%, with a bull case of 9.3% and a bear case of 6.7%. The range reflects uncertainty around national device reimbursement decisions.

Which segment is growing fastest?

Spinal cord stimulation devices grow fastest at 12.5%, about 1.56 times the overall market rate, as physicians favour targeted neuromodulation over long-term opioid therapy for chronic pain.

Who are the major companies in the Lumbosacral Radicular Pain Management Market?

Medtronic, Abbott, Boston Scientific, Nevro, and Stryker lead the moderately consolidated market at CR5 56%, reflecting deep clinical trial and payer relationship history across every region.

Which country is growing fastest?

India grows fastest at 11.5%, driven by rapidly expanding private healthcare access and rising interventional pain infrastructure. The United States remains the largest treated market.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Product and Technology Type

  • Spinal Cord Stimulation Devices
  • Radiofrequency Ablation Systems
  • Epidural Steroid Injection Products
  • Minimally Invasive Lumbar Decompression Devices
  • Nerve Block and Peripheral Nerve Stimulation Devices
  • Pharmacological Pain Management Products

By End-Use Industry

  • Academic Interventional Pain Programmes
  • Community Pain Management Clinics
  • Ambulatory Surgical Centres
  • Hospital Pain Departments
  • Specialty Neuromodulation Research Centres

By Commercial Dimension

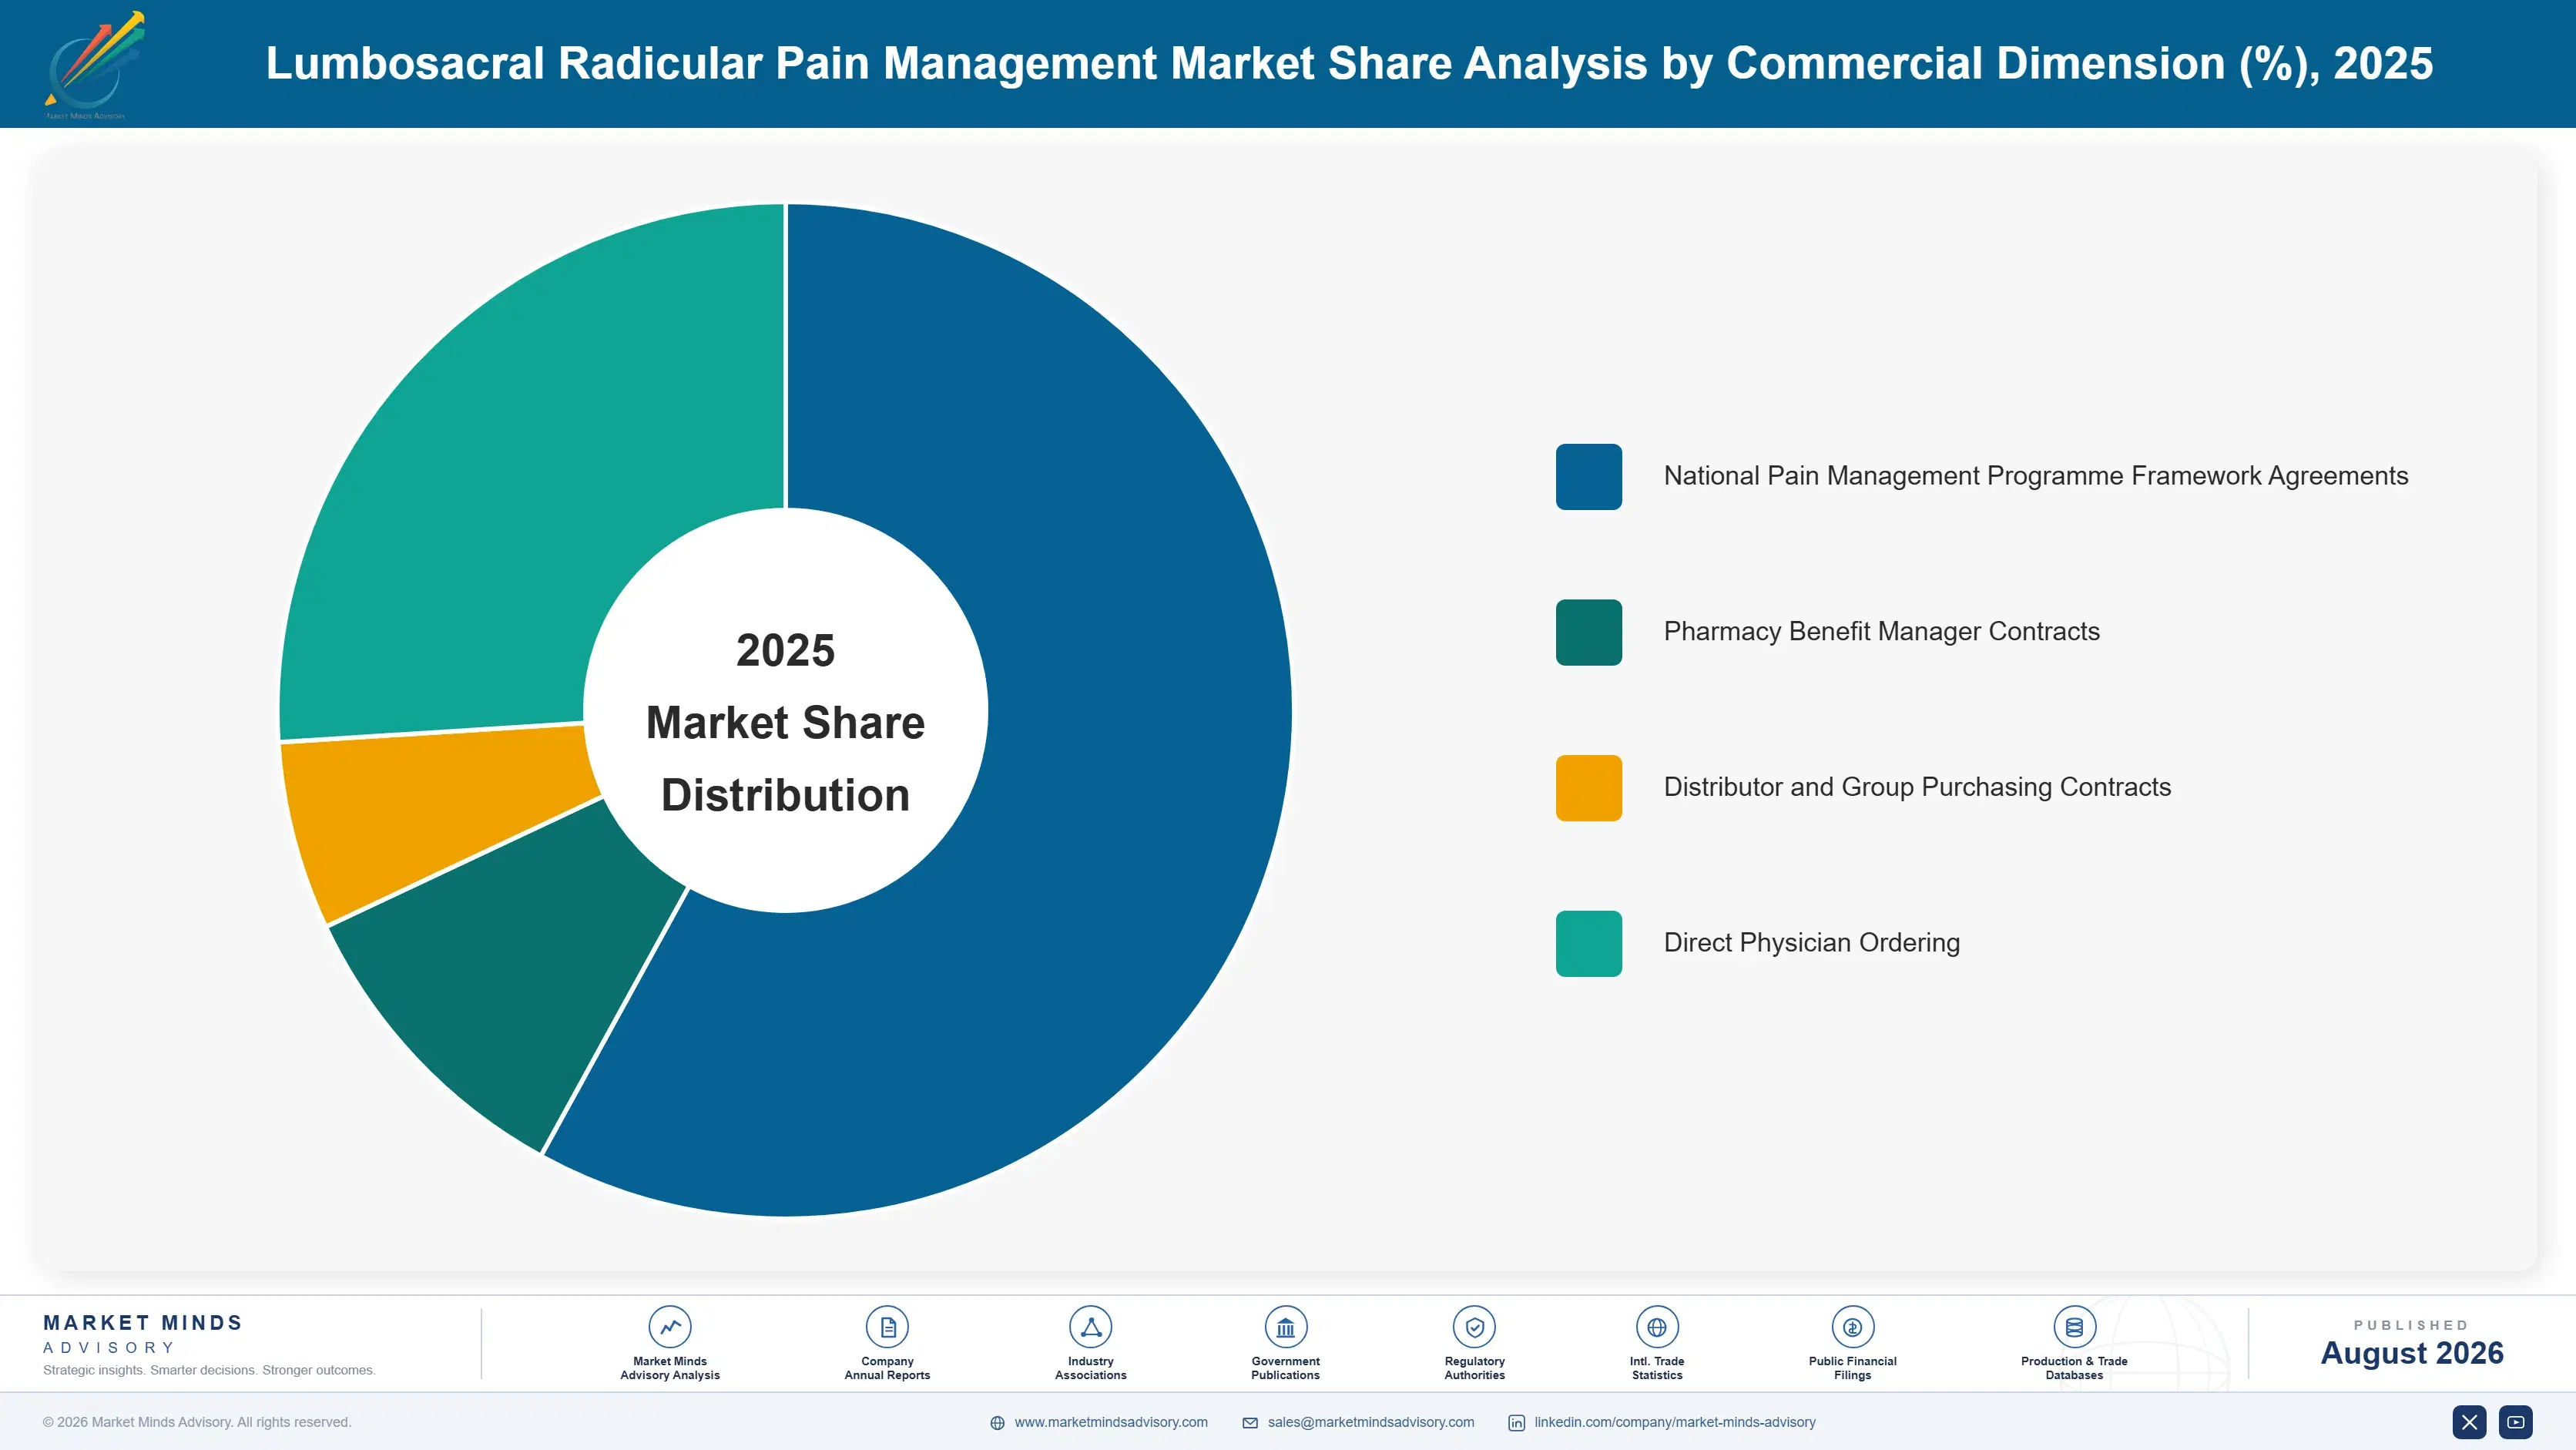
  • National Pain Management Programme Framework Agreements
  • Pharmacy Benefit Manager Contracts
  • Distributor and Group Purchasing Contracts
  • Direct Physician Ordering

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The lumbosacral radicular pain management market comprises devices, procedures, and products used to diagnose and treat radicular pain originating from lumbosacral nerve root compression or irritation, spanning spinal cord stimulation devices, radiofrequency ablation systems, epidural steroid injection products, minimally invasive lumbar decompression devices, nerve block and peripheral nerve stimulation devices, and pharmacological pain management products. General chronic pain management unrelated to lumbosacral radicular origin, spinal fusion surgical hardware, and diagnostic imaging equipment used for spine assessment are excluded.
Quantitative Units
USD billions (current prices); treated patient volume where applicable
Segmentation Dimensions
By Product and Technology Type; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Thailand, Malaysia, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Nevro Corp., Stryker Corporation, Saluda Medical Pty Ltd, Nalu Medical Inc., SPR Therapeutics Inc., Avanos Medical Inc., Diros Technology Inc., Vertos Medical Inc., Relievant Medsystems Inc., Persica Pharmaceuticals Ltd, Cerebral Therapeutics Inc., PainTEQ LLC, Cirtec Medical Corporation, Xalud Therapeutics Inc., DiscGenics Inc., SI-BONE Inc., Ethos Laboratories
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-MED-130
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Lumbosacral Radicular Pain Management Market Report (2026 to 2036).

The full MMA Lumbosacral Radicular Pain Management report sizes the market across six product and technology types, five end-use verticals, four commercial dimensions, and seven regions through 2036. It profiles twenty participants on a consistent device revenue basis, scoring each on lead placement precision, outcome data depth, and multi-country reimbursement reach. Scenario models quantify how opioid alternative policy, chronic pain diagnosis growth, and neuromodulation adoption move both demand and realised pricing. The report also includes delivered-cost modelling by product type and a national pain management programme benchmarking tool built for market access and device strategy teams.
Product type cost and outcome data benchmarking
Diagnosed patient pool and adoption tracker by region
National framework agreement structure and pricing tracker
Opioid alternative policy comparison by country
Battery component supply chain risk screen
Outcome registry revenue forecasting and modelling

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts