Market Minds Advisory
Liquid Biopsy Market

Liquid Biopsy Market: Early Detection Screening Redraws Cancer Diagnostics Economics

Multi-cancer early detection screening is pulling liquid biopsy beyond treatment selection into population-level testing, forcing legacy tissue biopsy pathology labs to defend diagnostic volume against blood-based molecular platforms across most regions.

Lead Analyst

Alice Ballenger

Published

August 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$6.5BMarket Size 2025
2036 FORECAST VALUE$20.5BBase Case , 2026 to 2036
CAGR 2026 TO 203611.0 %Bull 12.3% / Bear 9.7%
INCREMENTAL OPPORTUNITY$13.3BNet 10- year value creation
EXPANSION MULTIPLE2.84x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Liquid biopsy has moved past treatment selection alone, as multi-cancer early detection screening lets asymptomatic patients get tested for dozens of cancer types from a single blood draw, years before conventional imaging would ever catch disease at a genuinely treatable stage.
Multi-cancer early detection and minimal residual disease platforms are pulling ahead of every other product category, growing considerably faster than companion diagnostic testing as oncologists increasingly prioritise earlier detection and recurrence monitoring over treatment selection alone. Guardant Health and Exact Sciences still anchor much of the installed oncology relationships on decades of molecular testing trust, but Natera is undercutting integration complexity across several categories, and North America consumes the largest share given its reimbursement depth.
Competitive character splits between diversified molecular diagnostics majors defending broad oncology testing portfolios and specialist screening platform makers competing on detection sensitivity and clinical validation depth. Regulatory clearance pathways for new biomarker panels remain more predictable than payer reimbursement cycles, which still vary considerably by individual country in how aggressively they cover screening tests without a confirmed diagnosis across every national drug budget and annual health authority review cycle.
Market Definition
The liquid biopsy market covers minimally invasive diagnostic tests that analyze circulating tumor DNA, circulating tumor cells, exosomes, and other tumor-derived biomarkers from blood and body fluid samples, including multi-cancer early detection screening, minimal residual disease monitoring, companion diagnostic and treatment selection testing, cancer recurrence monitoring, circulating tumor cell analysis platforms, and exosome and extracellular vesicle analysis. It excludes tissue biopsy diagnostics, general blood chemistry panels unrelated to cancer biomarkers, and germline genetic testing for inherited cancer risk performed without tumor-derived biomarker analysis.
Base Year Value
$6.5B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
11.0% base case. Bull 12.3%. Bear 9.7%.
Fastest Growth Segment
Multi-Cancer Early Detection Screening: 18.0% CAGR
Fastest Growth Country
India: 14.5% CAGR
Fastest Growth Region
South Asia and Pacific: 13.0% CAGR
Largest Region
North America: 40% of 2025 global value
Market Leaders
Guardant Health Inc., Exact Sciences Corporation, Illumina Inc., Natera Inc., Foundation Medicine Inc. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Liquid Biopsy Market Forecast Scenarios

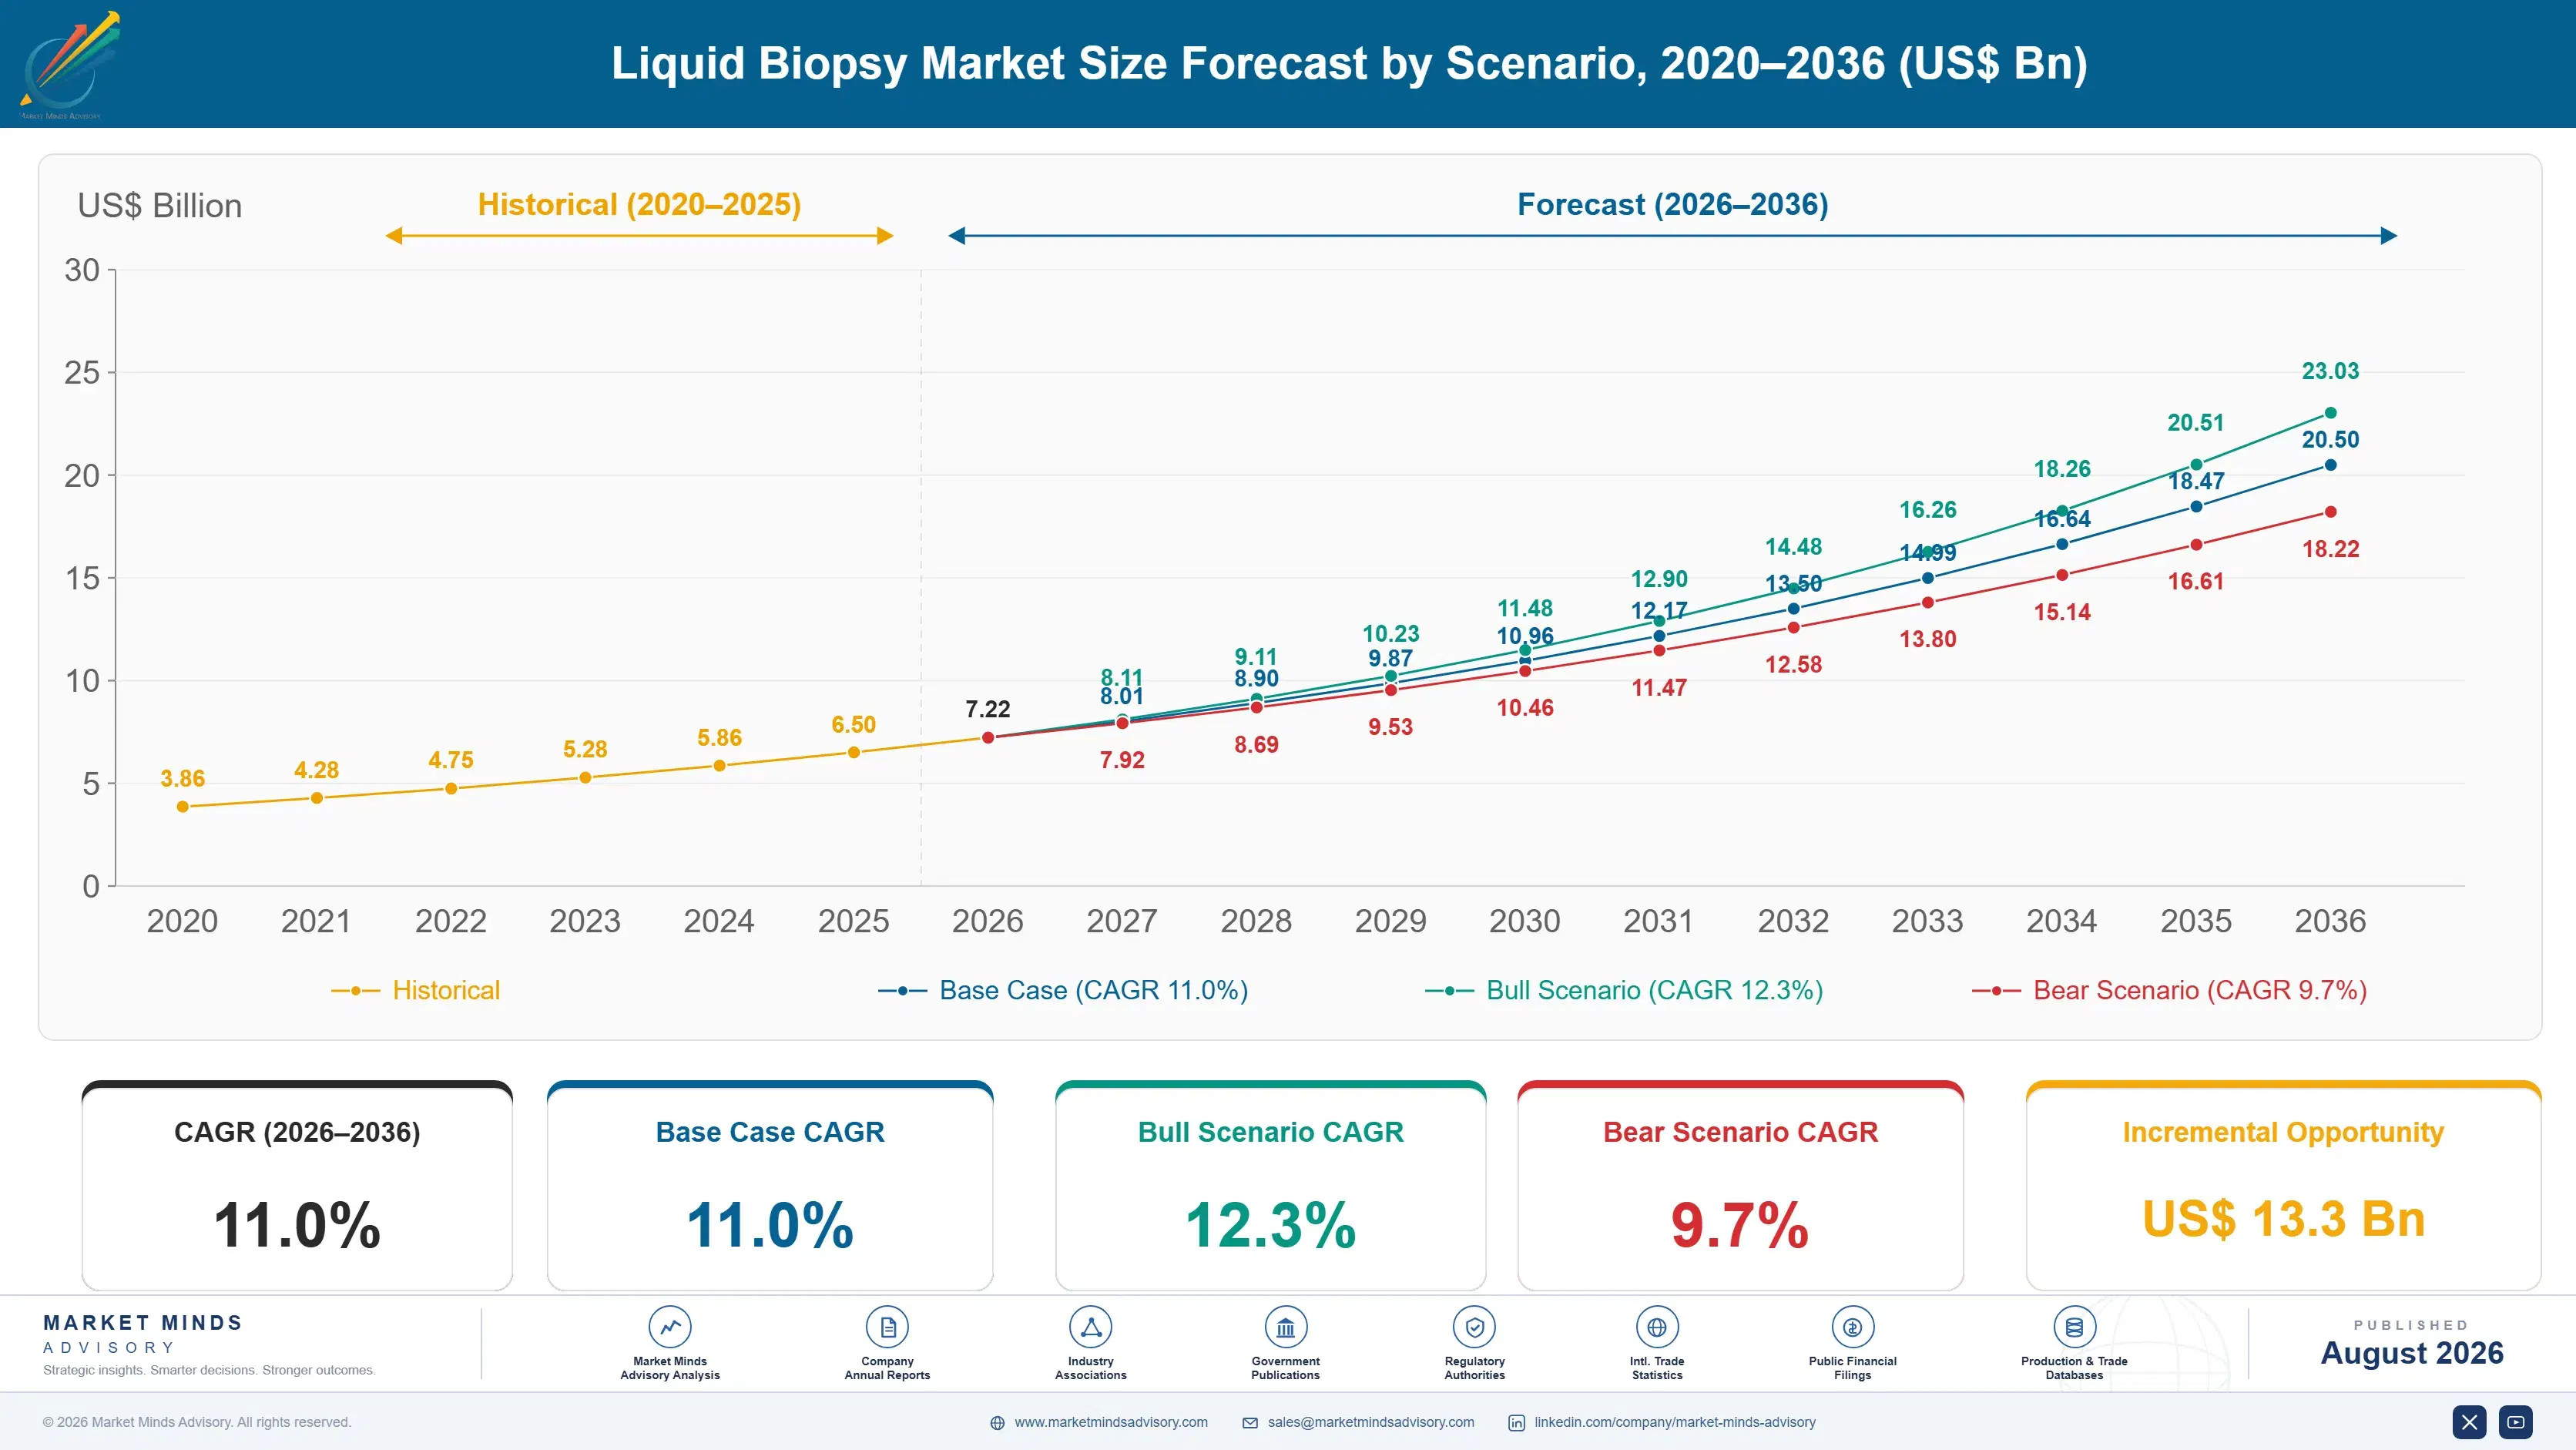
liquid-biopsy-market-size-forecast-scenario-1787306004049
Between 2020 and 2025 the market grew at a 10.0% historical CAGR, tracking companion diagnostic and recurrence monitoring demand closely through most of the period. Multi-cancer early detection adoption only gained real momentum from 2023 onward as clinical validation data and payer pilot programmes both expanded across major markets. Reporting that period remained limited given fragmented payer disclosure practices.
The base case carries the market to an 11.0% CAGR through 2036 on three mechanisms. First, oncologists increasingly order liquid biopsy testing over tissue biopsy alone as detection sensitivity and turnaround speed both improve considerably across available platforms and clinical settings. Second, rising global cancer incidence keeps expanding the underlying tested patient pool. Third, expanding screening reimbursement access in developing markets keeps pulling new demand into standardised, validated testing formats and specification standards.
The bull case reaches 12.3% if additional national health systems expand screening reimbursement faster than currently modelled, pulling forward test adoption across a compressed access timeline. The bear case falls to 9.7% if payer coverage decisions stay conservative, keeping demand tied mostly to confirmed-diagnosis monitoring rather than new screening specification across the broader category and its subsegments.

Why Early Detection Screening Is Redrawing Testing Volume

Three forces converge on liquid biopsy demand at once. Oncologists increasingly order testing over tissue biopsy alone as detection sensitivity and turnaround speed both improve across available molecular platforms and clinical settings. Rising global cancer incidence keeps expanding the underlying tested patient pool. And expanding screening reimbursement access in developing markets keeps pulling new demand into standardised, validated testing formats rather than invasive tissue sampling alone
MARKET CONCENTRATIONCR5: 52%A handful of majors hold most oncology testing share
AVERAGE SELLING PRICEUSD 350 to 3,200 per testPricing spans companion diagnostics to screening panel formats
TOP PRODUCING COUNTRY SHAREUSA: 41% of tests processedReimbursement coverage stays concentrated in this domestic base
PAYER COVERAGE RATE55 to 85% across reimbursed marketsCoverage varies considerably by each national negotiation outcome
R&D INVESTMENT SHARE30 to 38% of revenueClinical validation and screening panel expansion dominate spending
TEST TURNAROUND TIME5 to 14 days per resultTurnaround varies by panel complexity and laboratory location
Commercially, the market behaves like a concentrated precision diagnostics category rather than a diversified laboratory service. Payers negotiate by clinical validation depth, detection sensitivity, and reimbursement precedent rather than by price alone, because a single coverage decision affects an entire national screening population at once. That concentration protects margin for makers with genuine clinical trial depth and keeps unvalidated entrants largely absent from national screening contracts.
Over the next decade, clinical validation depth becomes the real differentiator between makers. Makers that combine screening sensitivity engineering with verified outcome data are capturing the reimbursement decisions increasingly dominating new test volume, while validation-light makers lose ground even where basic detection performance remains broadly comparable across most categories and geographies they serve.
"A screening test that isn't validated against a proper clinical outcome study doesn't just cost a payer one coverage denial, it costs the manufacturer years of lost adoption while competitors with real data capture the reimbursement decision, so buyers watch validation depth long before they ever discuss price."
Director, Precision Oncology and Molecular Diagnostics Practice · MMA Healthcare

Market Trends

Multi-Cancer Screening Replaces Single-Cancer Testing Protocols

Oncologists and primary care physicians increasingly specify multi-cancer early detection panels over single-cancer testing protocols, since blood-based screening detects dozens of cancer types from a single draw rather than requiring separate organ-specific tests across a patient's full annual screening visit. That clinical preference is pulling procurement toward multi-cancer platform makers even where panel cost runs considerably higher than comparable single-cancer tests, because payers increasingly recognise earlier detection as offsetting long-term treatment cost. Guardant Health and Exact Sciences have both expanded multi-cancer panel capacity specifically to capture patients replacing single-cancer testing programmes.
Market Impact: Expands tested pool 10-15% yearly
Minimal Residual Disease Monitoring Becomes A Treatment Standard

Major oncology networks increasingly require documented minimal residual disease monitoring before confirming remission status, since imaging-only surveillance misses molecular recurrence signals that liquid biopsy detects months earlier across multiple cancer types and treatment settings worldwide and every clinical protocol currently in wide use today. That monitoring requirement has converted recurrence surveillance from an optional add-on into a standing clinical protocol line item that oncology networks cannot easily avoid at any meaningful scale. Natera and Foundation Medicine have both expanded MRD monitoring capacity specifically to serve networks navigating tightening surveillance protocol requirements.
Market Impact: Adds coverage across 50%+ of payers

Market Opportunities and Growth Drivers

Rising Global Cancer Incidence Expands The Tested Patient Pool

Improved cancer screening infrastructure and broader clinical awareness in multiple developed markets are catching cancer diagnoses earlier, moving detection from a delayed symptomatic presentation into a standing primary care screening pathway that physicians increasingly follow as routine practice across their full patient panels, annual checkup schedules, and every referral network they participate in. That earlier detection has converted cancer diagnosis from an occasional specialist finding into a standing screening result that treatment pathways cannot avoid processing early. Health systems increasingly build oncology programme capacity around rising screening volume projections year over year.
Market Impact: Raises annual screening cost 250-40

Reimbursement Coverage Expansion Supports Screening Adoption

Major health insurers and national health systems in multiple markets increasingly cover multi-cancer early detection screening at parity with confirmed-diagnosis monitoring, removing a cost barrier that previously limited access to patients able to pay considerable out-of-pocket premiums for preventive testing and follow-up procedures they might otherwise choose to decline entirely. That coverage expansion is considerably less cyclical than most diagnostic categories, since cancer testing demand persists regardless of broader economic conditions or discretionary healthcare spending. Health systems increasingly build oncology diagnostic budgets around expanding reimbursement parity projections each fiscal year.
Market Impact: Limits confidence to 60% of results

Market Restraints and Challenges

Screening Test Cost Premium Limits Adoption In Smaller Health Systems

Multi-cancer early detection screening costs considerably more per test than conventional single-cancer diagnostics, a price gap that smaller and developing health systems absorb poorly across thin preventive care budgets, the root cause being that multi-cancer panel development required meaningfully more precision biomarker research investment and large-population clinical validation than standard single-cancer assays. That cost gap keeps screening adoption concentrated in well-reimbursed developed health systems, leaving smaller markets dependent on confirmed-diagnosis testing regardless of screening interest. Makers are responding with tiered access programmes aimed specifically at closing that gap for smaller health systems.
Market Impact: Screens 50+ cancer types per draw

False Positive Concerns Still Limit Confidence In Screening Results

Multi-cancer early detection screening still faces genuine false positive concerns among some clinicians regarding unnecessary follow-up imaging and biopsy procedures triggered by unconfirmed molecular signals across large asymptomatic screening populations tested annually and across multiple screening cycles and follow-up visits. That confidence concern limits adoption regardless of the early detection benefit clinicians generally value, the root cause being that population-level screening inherently produces some false signals that individual diagnostic tests targeting confirmed disease rarely encounter at all. Makers are responding by developing improved confirmatory testing pathways that reduce unnecessary follow-up procedures.
Market Impact: Detects recurrence 6-12 months earl
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

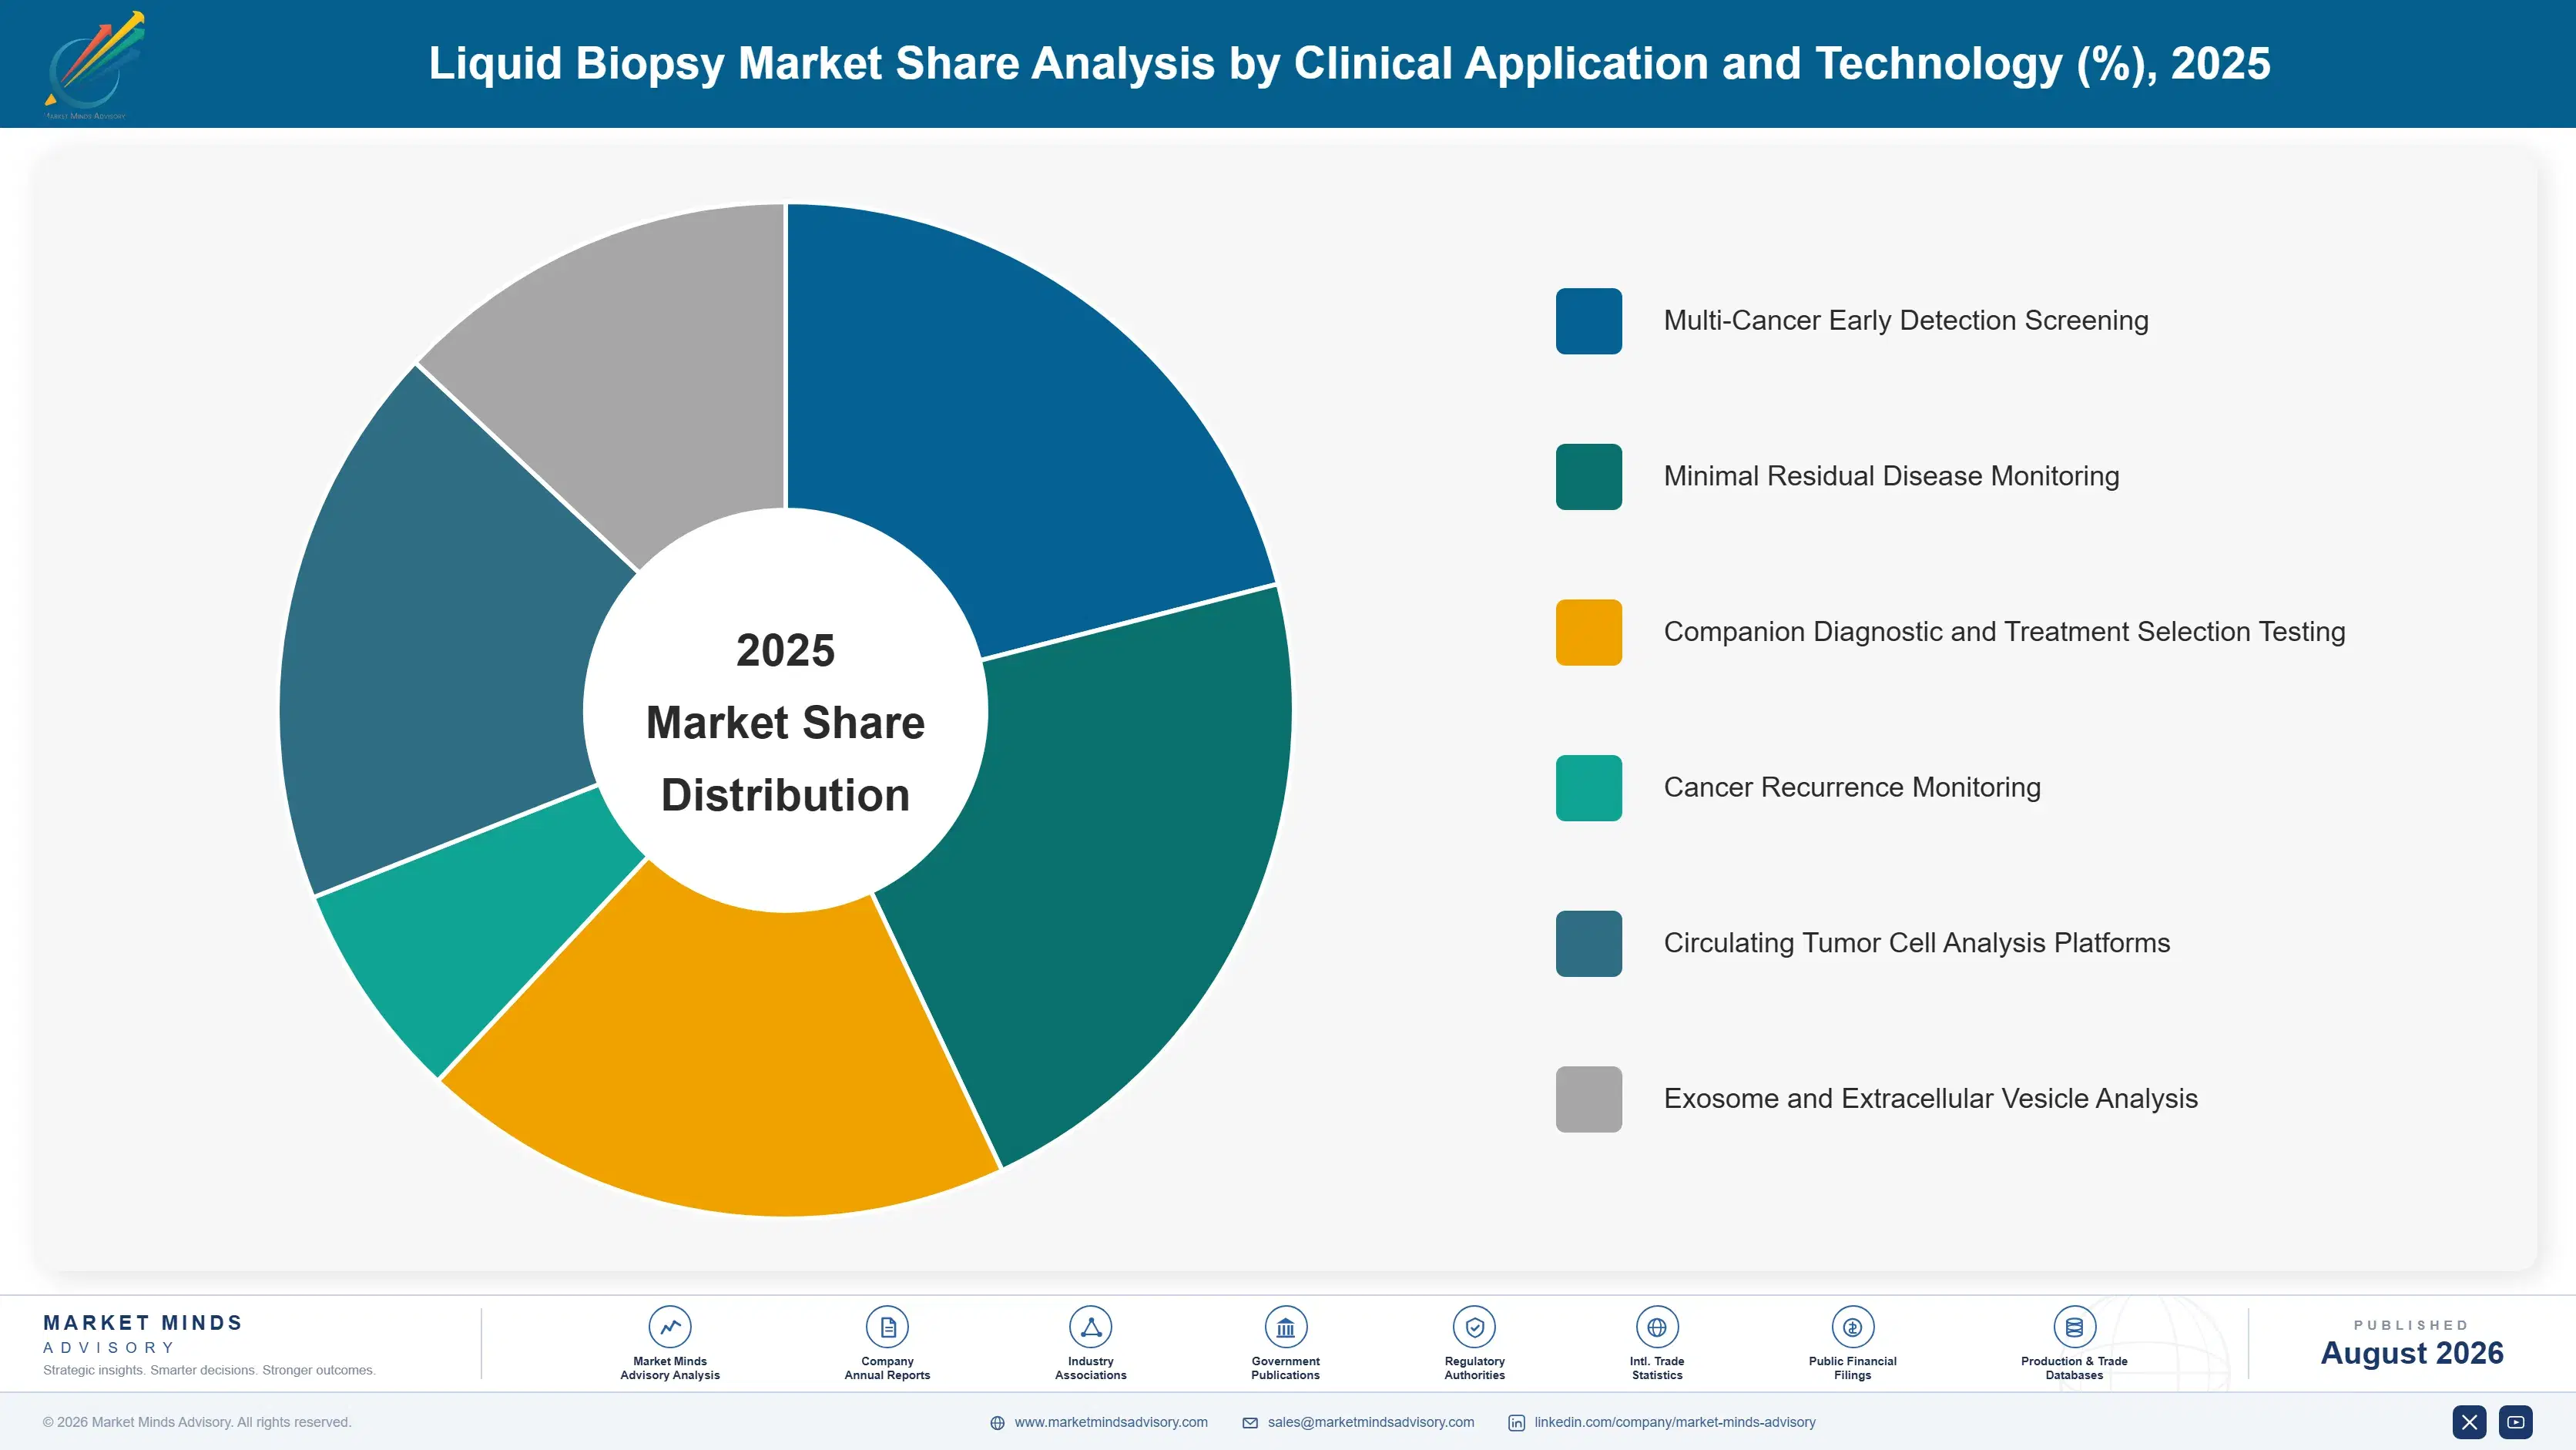
Segmentation follows clinical application and technology type, the single diagnostic logic that determines biomarker target, testing stage, and overall clinical use of each platform across the full category as a whole. Screening, MRD monitoring, companion diagnostics, recurrence testing, and cell analysis each carry genuinely distinct clinical roles that are evaluated consistently throughout this report.
liquid-biopsy-market-market-share-analysis-1787306004580

Multi-Cancer Early Detection Screening

Multi-cancer early detection screening grows fastest at 18.0%, about 1.64 times the market's 11.0% overall rate, as asymptomatic patients increasingly seek blood-based screening covering dozens of cancer types from a single annual draw across every eligible age cohort. Illumina's Grail platform still commands the largest share of multi-cancer screening installations on established clinical validation depth, but Exact Sciences and Guardant Health are expanding competing platforms into overlapping premium payer contract categories once considered defensible territory. Falling sequencing costs are letting more mid-size health systems justify their first screening programme without waiting for large national reimbursement negotiations. Adoption concentrates first among high-risk patient populations before spreading into broader average-risk screening cohorts.
CAGR 18.0%

Minimal Residual Disease Monitoring

Minimal residual disease monitoring grows second-fastest at 15.0%, driven by oncologists seeking molecular recurrence signals months before imaging surveillance would detect relapse across every major cancer type and treatment protocol currently in use across academic and community oncology practices alike. Rather than relying solely on periodic imaging, MRD monitoring lets oncology teams detect recurrence at the molecular level and intervene earlier in a patient's treatment pathway and overall care plan. Natera and Foundation Medicine have both expanded MRD monitoring product lines specifically to serve oncology networks requiring documented surveillance protocol compliance. Adoption is fastest among post-treatment patients where earlier recurrence detection carries genuine survival benefit across every treatment protocol currently studied.
CAGR 15.0%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Global demand concentrates heavily where precision oncology reimbursement depth and overall screening adoption maturity run deepest today. North America leads by a very wide margin, Western Europe follows closely behind on established coverage, and East Asia trails given its considerably less mature screening reimbursement overall.

North America

The United States drives regional demand through the world's deepest precision oncology reimbursement coverage combined with strong commercial insurance access that prioritises screening and monitoring test adoption. Guardant Health's domestic commercial infrastructure gives it genuine incumbency advantage across nearly every academic oncology programme relationship, with several direct multi-cancer screening competitors now challenging that position at comparable scale. Canada contributes a smaller layer through comparable oncology testing demand tied closely to shared clinical treatment guidelines. Growth of 11.0% reflects continued screening adoption and expanding diagnosed patient pool across the region's major cancer treatment centres. This region's share sits above the standard band because the United States concentrates the deepest precision oncology reimbursement access of any market tracked.
Share: 40% | CAGR: 11.0% (2026 to 2036)

Western Europe

Germany, France, and the United Kingdom anchor demand through established national health system reimbursement and large diagnosed patient populations that continue expanding screening access across age categories and treatment centres. Foundation Medicine's regional commercial partnerships give it genuine advantage across German and broader European national payer accounts, though negotiated pricing runs considerably below US commercial rates. National reimbursement timelines vary considerably by country, with larger economies moving faster than smaller markets working through longer health technology assessment cycles. Growth of 9.5% trails the market's overall rate as the region's coverage is already relatively advanced, shifting emphasis toward pediatric and elderly patient expansion. Cross-border health technology assessment alignment keeps testing standards broadly consistent across neighbouring national systems.
Share: 24% | CAGR: 9.5% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
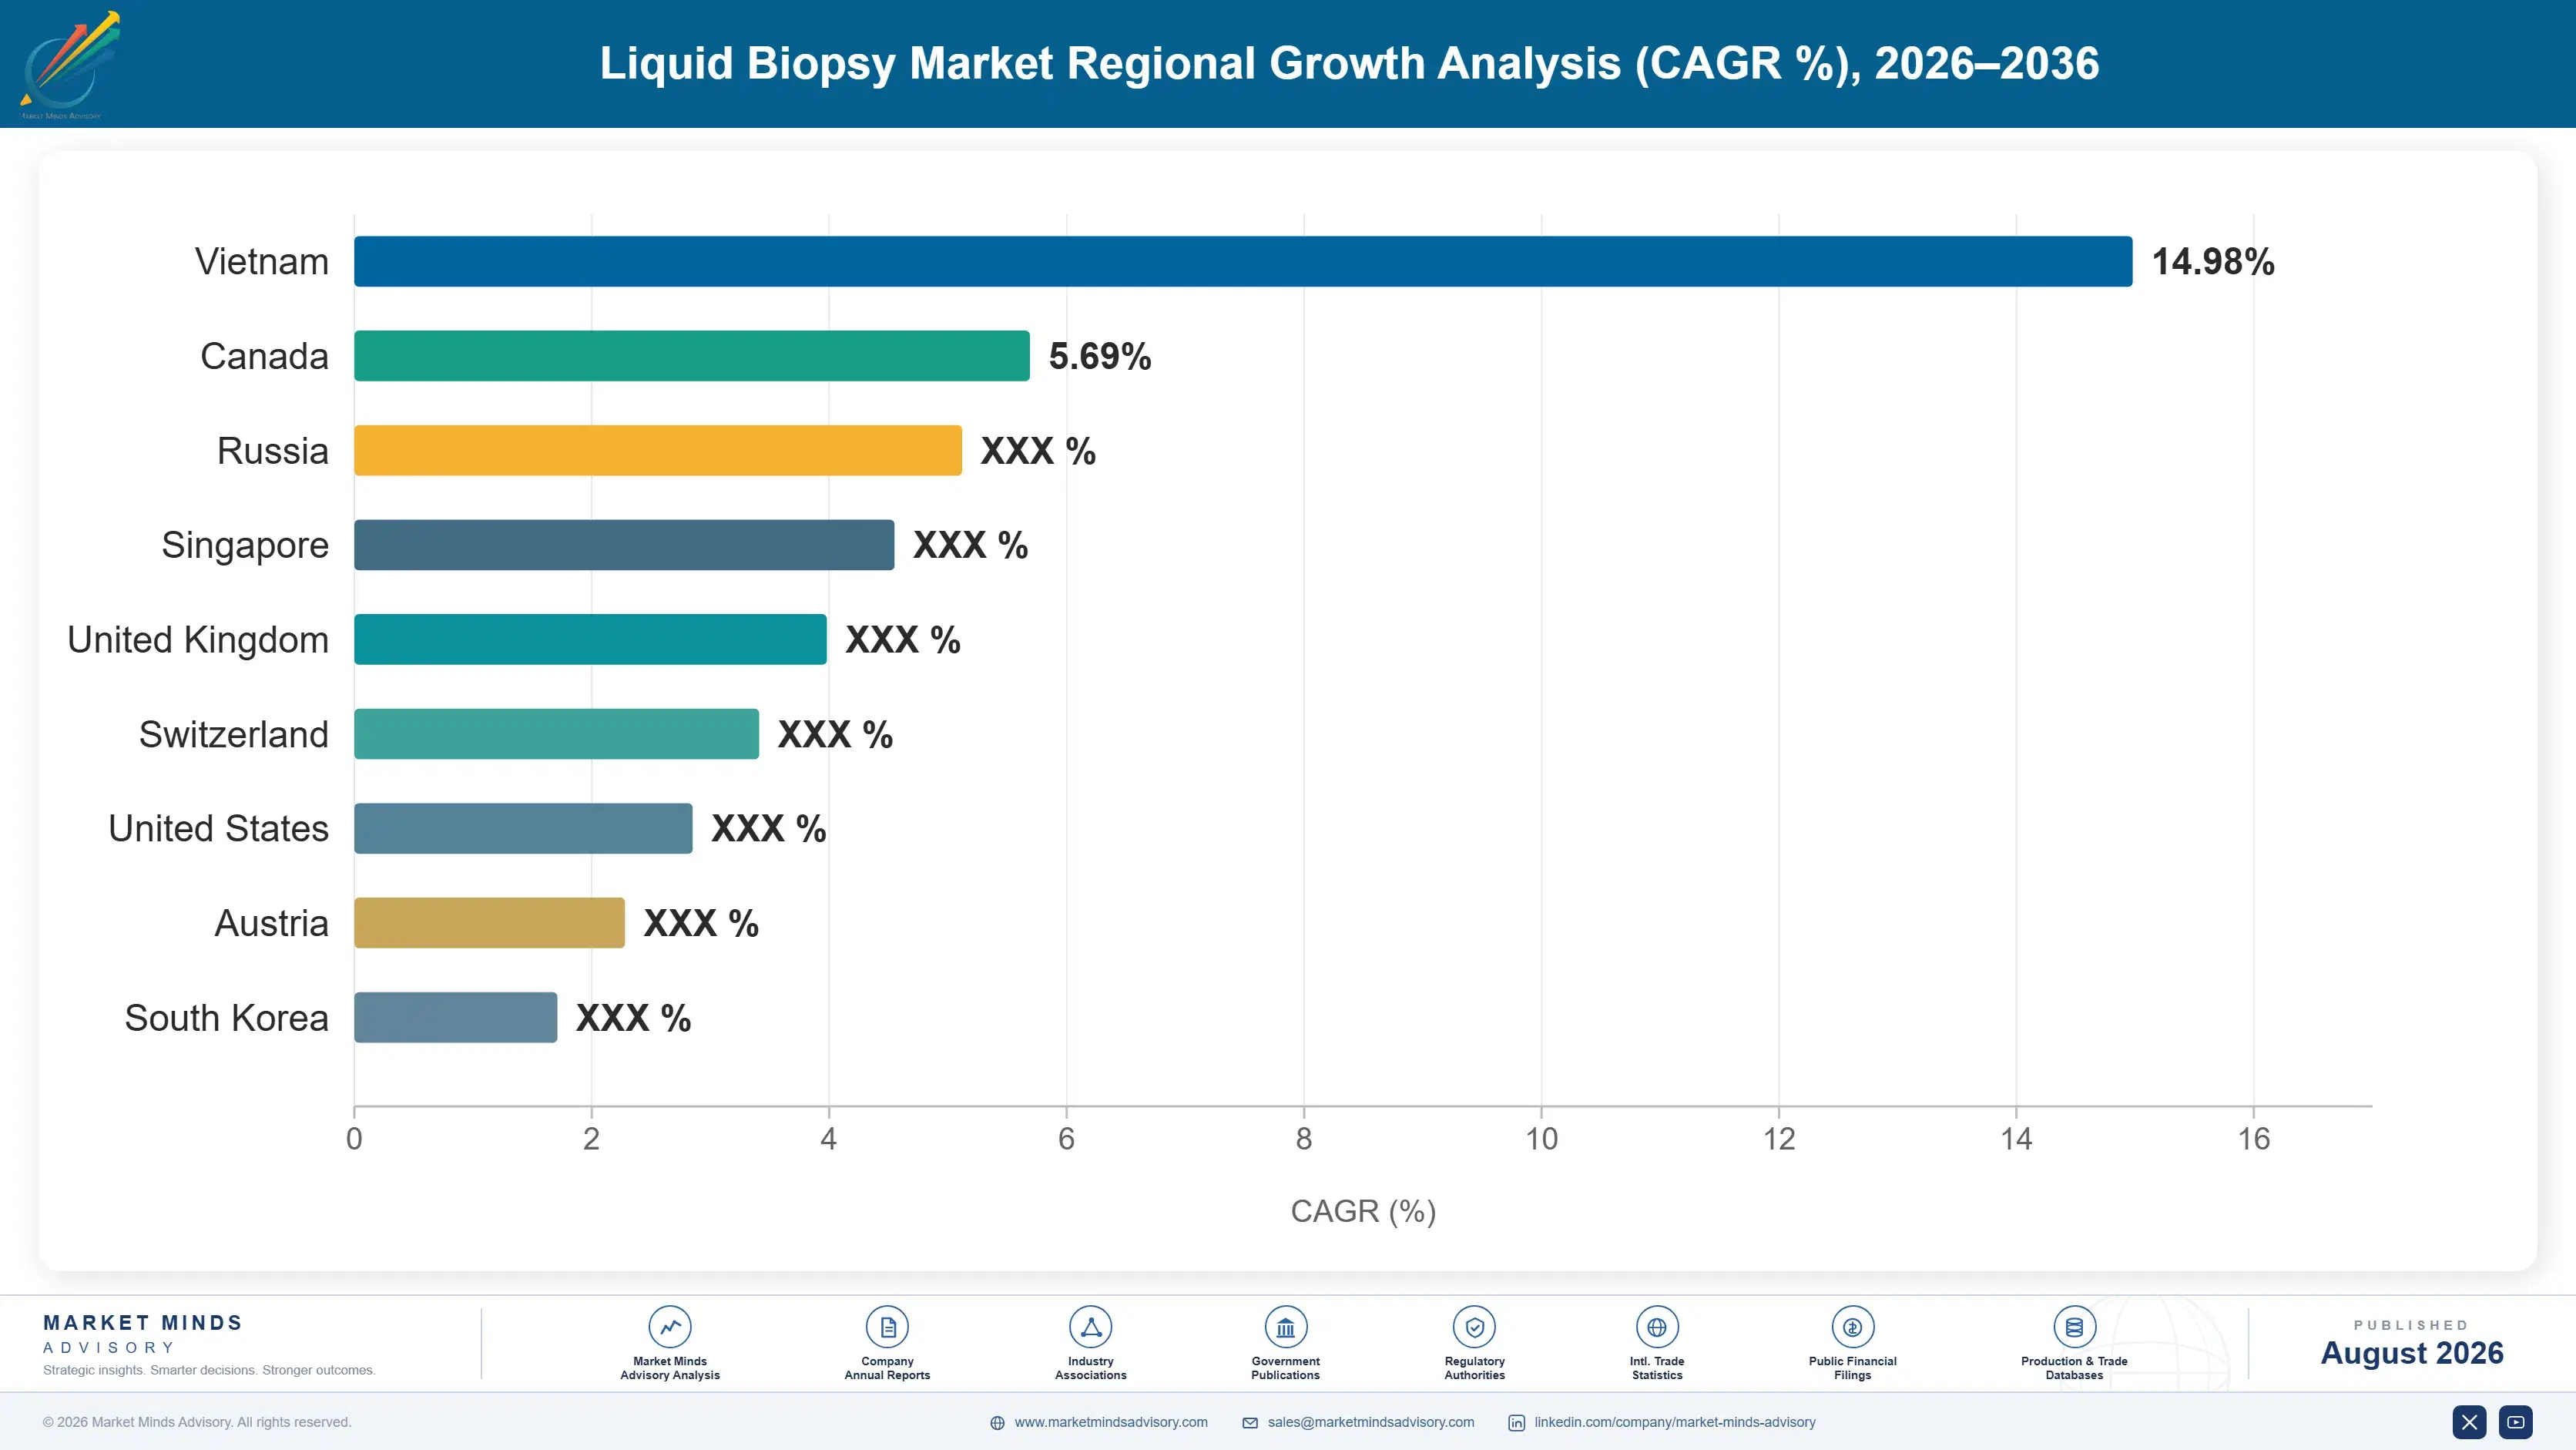
liquid-biopsy-market-country-cagr-analysis-1787306005093

Where Precision Oncology Makers Can Defend Margin

Payer negotiation increasingly favours makers who can demonstrate both detection sensitivity and long-term clinical outcome data across their full tested population and reimbursement history. The four levers below capture revenue before a reimbursement cycle locks national coverage terms rather than after, rewarding makers who prove clinical value credibly across a payer's full diagnosed population.

Bundle Screening Access With Patient Navigation Programmes

Testing specification increasingly happens during initial national reimbursement negotiation rather than during later individual patient access requests, when coverage terms and support commitments are already fixed and costly to change midstream once locked in place permanently. Makers that place patient navigation specialists inside reimbursement negotiation teams from the outset capture the full diagnosed population scope rather than competing for smaller individual exception approvals later. Guardant Health reports that national agreements bundling screening access with patient navigation programmes carry realised revenue roughly 19% higher than exception-based access on comparable diagnosed populations.
Market Impact: Lifts realised revenue roughly 19%

Sell Long-Term Outcome Registry Data Alongside Screening Launches

National payers increasingly want documented, longitudinal outcome data before committing to full national screening reimbursement at scale, and makers offering outcome registry support are capturing recurring reimbursement renewal loyalty worth 10 to 16% more in realised revenue per national market compared with launches lacking registry commitments across comparable countries and populations facing similar budget constraints and negotiation timelines. That registry commitment extends payer relationships across multiple reimbursement renewal cycles rather than a single negotiation, deepening the relationship over time. Exact Sciences has expanded its outcome registry programme specifically to capture this loyalty layer.
Market Impact: Adds 10-16% more revenue per nation

Build Tiered Access Programmes For Smaller Health Systems

Smaller national health systems cannot justify full list price screening access at the scale of the largest developed markets, yet they represent a large, historically underserved diagnosed population that the leading platforms previously found less economical to pursue directly across every income bracket. Makers offering tiered pricing programmes with income-adjusted access capture this segment at a fraction of the full list price cost, cutting the effective entry price by roughly 38% for smaller, budget-constrained health systems entering reimbursement negotiations. Natera has scaled exactly this tiered approach across smaller health systems since 2023.
Market Impact: Cuts entry price by roughly 38% for

Target National Cancer Programme Framework Agreements

National cancer screening programmes coordinating reimbursement standards across dozens of treatment centres increasingly want one negotiated national framework rather than a different access pathway at every centre, which shifts the purchasing decision upstream to a small number of national health authority negotiators making one decision at once across the full diagnosed population and national drug budget. Securing a framework agreement covering a country's full diagnosed population delivers revenue that no number of individual centre negotiations can match. Foundation Medicine has pursued exactly this framework approach with several national cancer programmes since 2022.
Market Impact: Locks in reimbursement across 100%

Who Controls the Margin Pool

Concentration sits at CR5 52%, notably consolidated for a category built on several competing screening and monitoring franchises with meaningful clinical trial investment behind each. Guardant Health and Exact Sciences lead on manufacturing scale and payer relationships, while the gap to challengers like Natera is more about clinical validation depth than manufacturing scale. All participants are assessed on one consistent basis, liquid biopsy testing revenue.
Current competitive activity runs across three dimensions. Product development concentrates on screening panel sensitivity expansion to close the detection gap with tissue biopsy. Outcome data investment focuses on verified long-term survival benefit rather than launch trial data alone. And account structure centres on national cancer programme framework agreements rather than one-off centre negotiations, a shift that rewards makers with genuine multi-country reimbursement capability.

Emerging pressure comes from academic and biotech entrants targeting the false-positive-sensitive patient minority that leading platforms' mechanisms still struggle to serve confidently, a segment global payers once assumed would remain permanently uncertain. Rankings will shift toward makers who combine screening breadth with proven long-term outcome credentials, since that combination is what national health authorities increasingly require for full reimbursement. Makers without a credible outcome data pipeline face the sharpest exposure ahead.
liquid-biopsy-market-company-positioning-matrix-1787306005615

Competitive Moat and Risk Dimensions

GUARDANT HEALTH INC.

Moat: Deep clinical trial scale

Guardant Health holds a well-established testing franchise built on over a decade of accumulated clinical trial data and oncology relationship history, giving it a genuine credibility advantage that newer entrants without comparable regulatory history cannot easily replicate quickly, even with substantial capital investment behind them.
GUARDANT HEALTH INC.

Risk: Exposed to screening platform competition

Guardant Health's core companion diagnostic franchise faces increasing competition from multi-cancer screening platforms that address a broader asymptomatic patient population, since those emerging mechanisms work through fundamentally different commercial pathways across a growing pipeline of competing programmes, payer negotiations, clinical trial designs, and reimbursement models.
EXACT SCIENCES CORPORATION

Moat: Deep screening and channel reach

Exact Sciences draws on decades of accumulated screening test commercialisation and primary care physician relationship depth from its wider diagnostics business, giving it a genuine advantage reaching payer formulary committees that competitors without comparable channel infrastructure cannot easily replicate quickly across comparable price tiers and account sizes.
EXACT SCIENCES CORPORATION

Risk: Exposed to reimbursement negotiation pressure

Exact Sciences's broad screening portfolio sometimes trades off against the reimbursement negotiation leverage that fast-scaling specialist platforms increasingly demand, leaving open room for smaller competitors to win narrow screening niches purely on clinical differentiation alone in several developing regions, mid-tier accounts, and various academic partnerships.

Players Tracked

Prominent Players

Guardant Health Inc.
Exact Sciences Corporation
Illumina Inc.
Natera Inc.
Foundation Medicine Inc.

Other Key Players

Bio-Rad Laboratories Inc.
Thermo Fisher Scientific Inc.
QIAGEN N.V.
Menarini Silicon Biosystems S.p.A.
ANGLE plc
Biodesix Inc.
Personalis Inc.
Adaptive Biotechnologies Corporation
Freenome Holdings Inc.
Delfi Diagnostics Inc.
Burning Rock Biotech Limited
NeoGenomics Laboratories Inc.
Myriad Genetics Inc.
Bio-Techne Corporation
Twist Bioscience Corporation

Recent Developments

FEBRUARY 2025

Guardant Health secures expanded coverage for multi-cancer screening panel

Guardant Health received expanded national payer coverage for its multi-cancer screening panel, extending reimbursed access across several new state and employer health plans nationwide and every major account it currently serves. This was a coverage expansion rather than a new product launch, extending Guardant Health's addressable reimbursed population.
Signal: Payer coverage expansion is quickly becomi
AUGUST 2025

Exact Sciences acquires specialty MRD monitoring technology company

Exact Sciences completed the acquisition of a specialty minimal residual disease monitoring technology company with proprietary ultra-sensitive detection chemistry built for post-treatment surveillance and broader clinical reporting systems worldwide. The deal brought advanced monitoring capability in-house, expanding Exact Sciences's offering considerably beyond its prior screening-only product line.
Signal: MRD monitoring technology is becoming a ge
MAY 2025

Natera signs national reimbursement framework agreement with cancer programme

Natera entered a multi-year reimbursement framework agreement with a national cancer screening programme covering MRD monitoring access across the country's full diagnosed patient population. The agreement was a commercial reimbursement contract, not a joint venture or equity transaction, covering coverage across the programme's full patient roster.
Signal: Multi-year, national reimbursement framewo

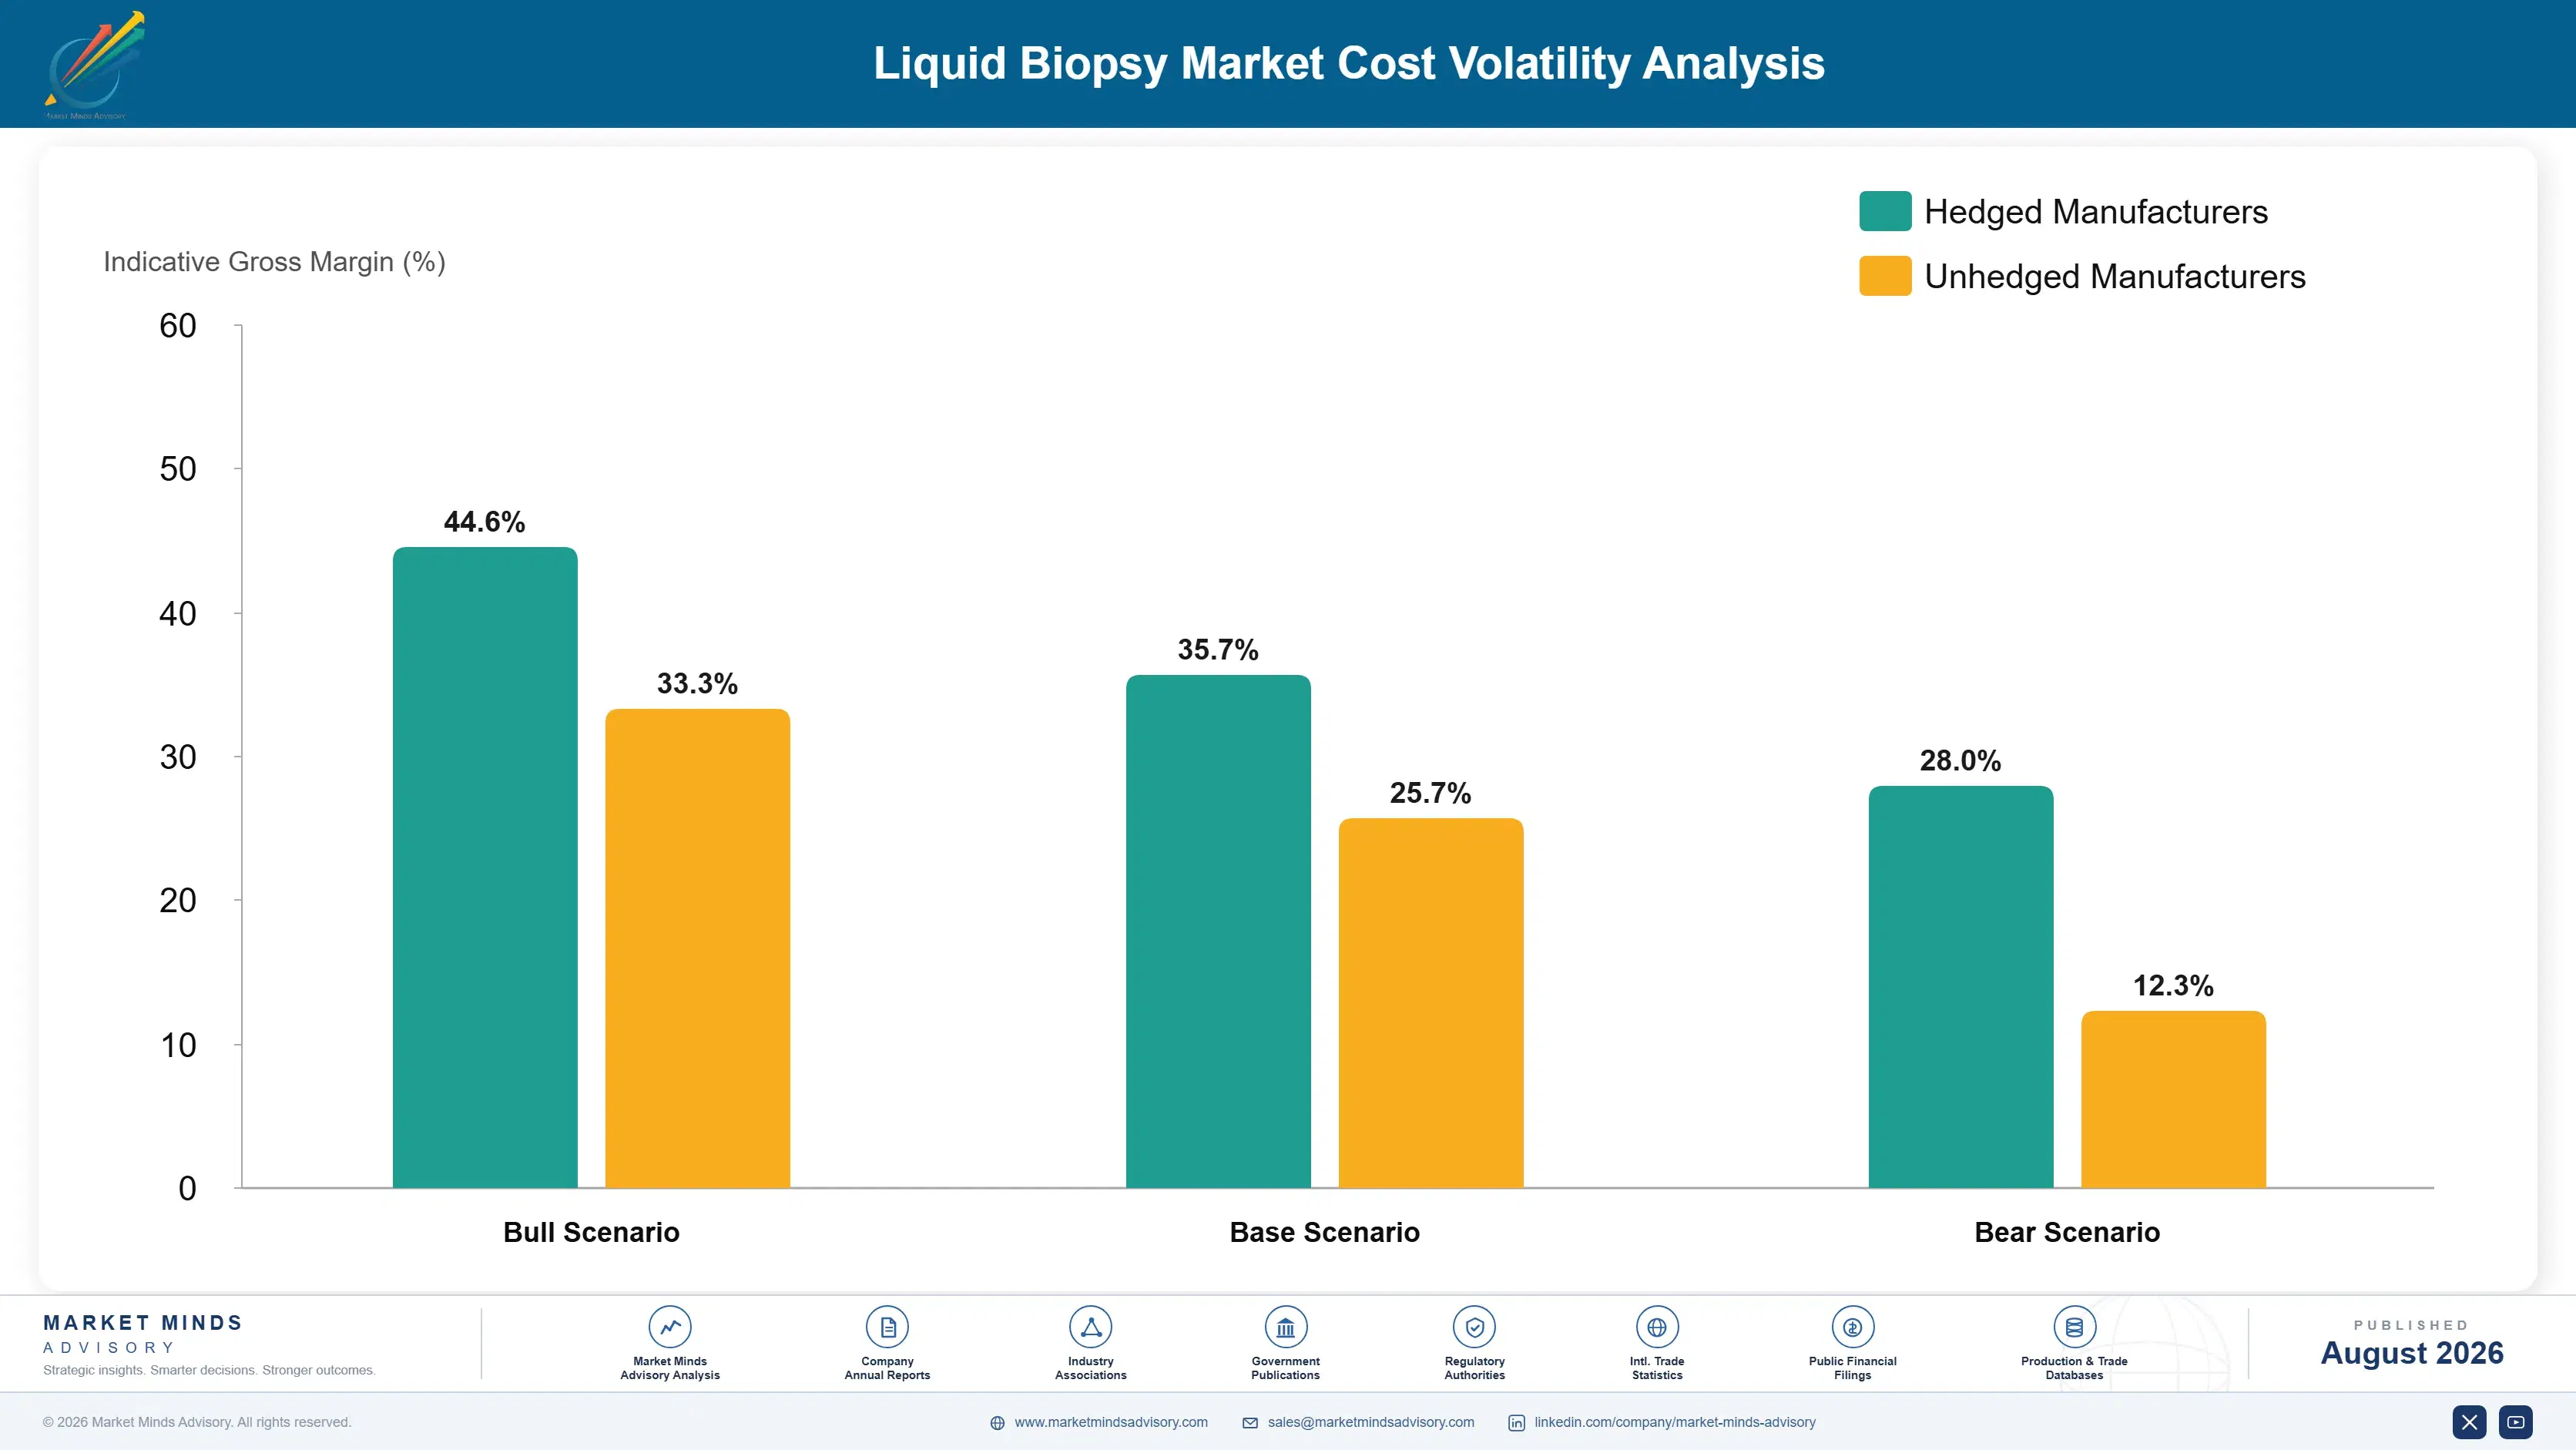
Sequencing Reagent And Assay Development Exposure

Next-generation sequencing reagents and library preparation consumables run 30 to 38% of COGS, sourced from a concentrated set of specialty sequencing manufacturers that also supply the wider genomics industry across multiple product categories and geographies. Clinical trial and assay validation investment add a further 20 to 28%, with regulatory compliance and quality certification accounting for most of the remainder.
The global sequencing reagent supply disruption running through 2021 and 2022 hit molecular diagnostics production directly, since certain sequencing chemistry components, sourced substantially from a concentrated set of specialty manufacturers, faced extended shortages that rippled through downstream testing laboratories. Illumina's 2022 Annual Report disclosed elevated reagent costs and extended lead times across its sequencing segment, attributing part of the pressure to component allocation constraints that persisted through much of the year overall.

Exposure varies sharply by player type. Vertically integrated majors like Illumina manufacture much of their own sequencing chemistry in-house, insulating them from the worst allocation constraints, while smaller specialists depend on third-party reagent suppliers and absorb price spikes directly into thinner margins. Geography matters too, since makers sourcing components domestically face meaningfully different exposure than those depending on imported material.
liquid-biopsy-market-cost-volatility-analysis-1787306005811

Dual-Source Sequencing Reagents From Separate Suppliers

Qualifying assays against sequencing reagents from two separate suppliers, rather than one, keeps a shortage at either supplier from halting production entirely across the whole laboratory network worldwide and across every panel type and product line. Several makers adopted dual-sourcing as standard practice after the 2021 disruption exposed how concentrated their supply chains genuinely were.

Vertically Integrate Sequencing Chemistry Where Feasible

Manufacturing sequencing chemistry in-house rather than sourcing it externally insulates the very largest makers from allocation shortages during industry-wide supply disruptions and price spikes alike across most product categories and geographies. Smaller specialists lacking that scale have instead pursued long-term supply agreements with established reagent manufacturers to secure priority allocation, considerably reducing spot-market exposure.

Shift Product Mix Toward Value-Added Screening Panels

Premium screening and MRD monitoring panels carry considerably better margin resilience against reagent price volatility than standard companion diagnostic formats, giving makers a durable way to protect blended margin over time by shifting revenue mix toward differentiated products across their portfolio. That shift has meaningfully improved margin stability across portfolios facing sustained feedstock pressure this decade.

Portfolio Architecture for Margin Defence

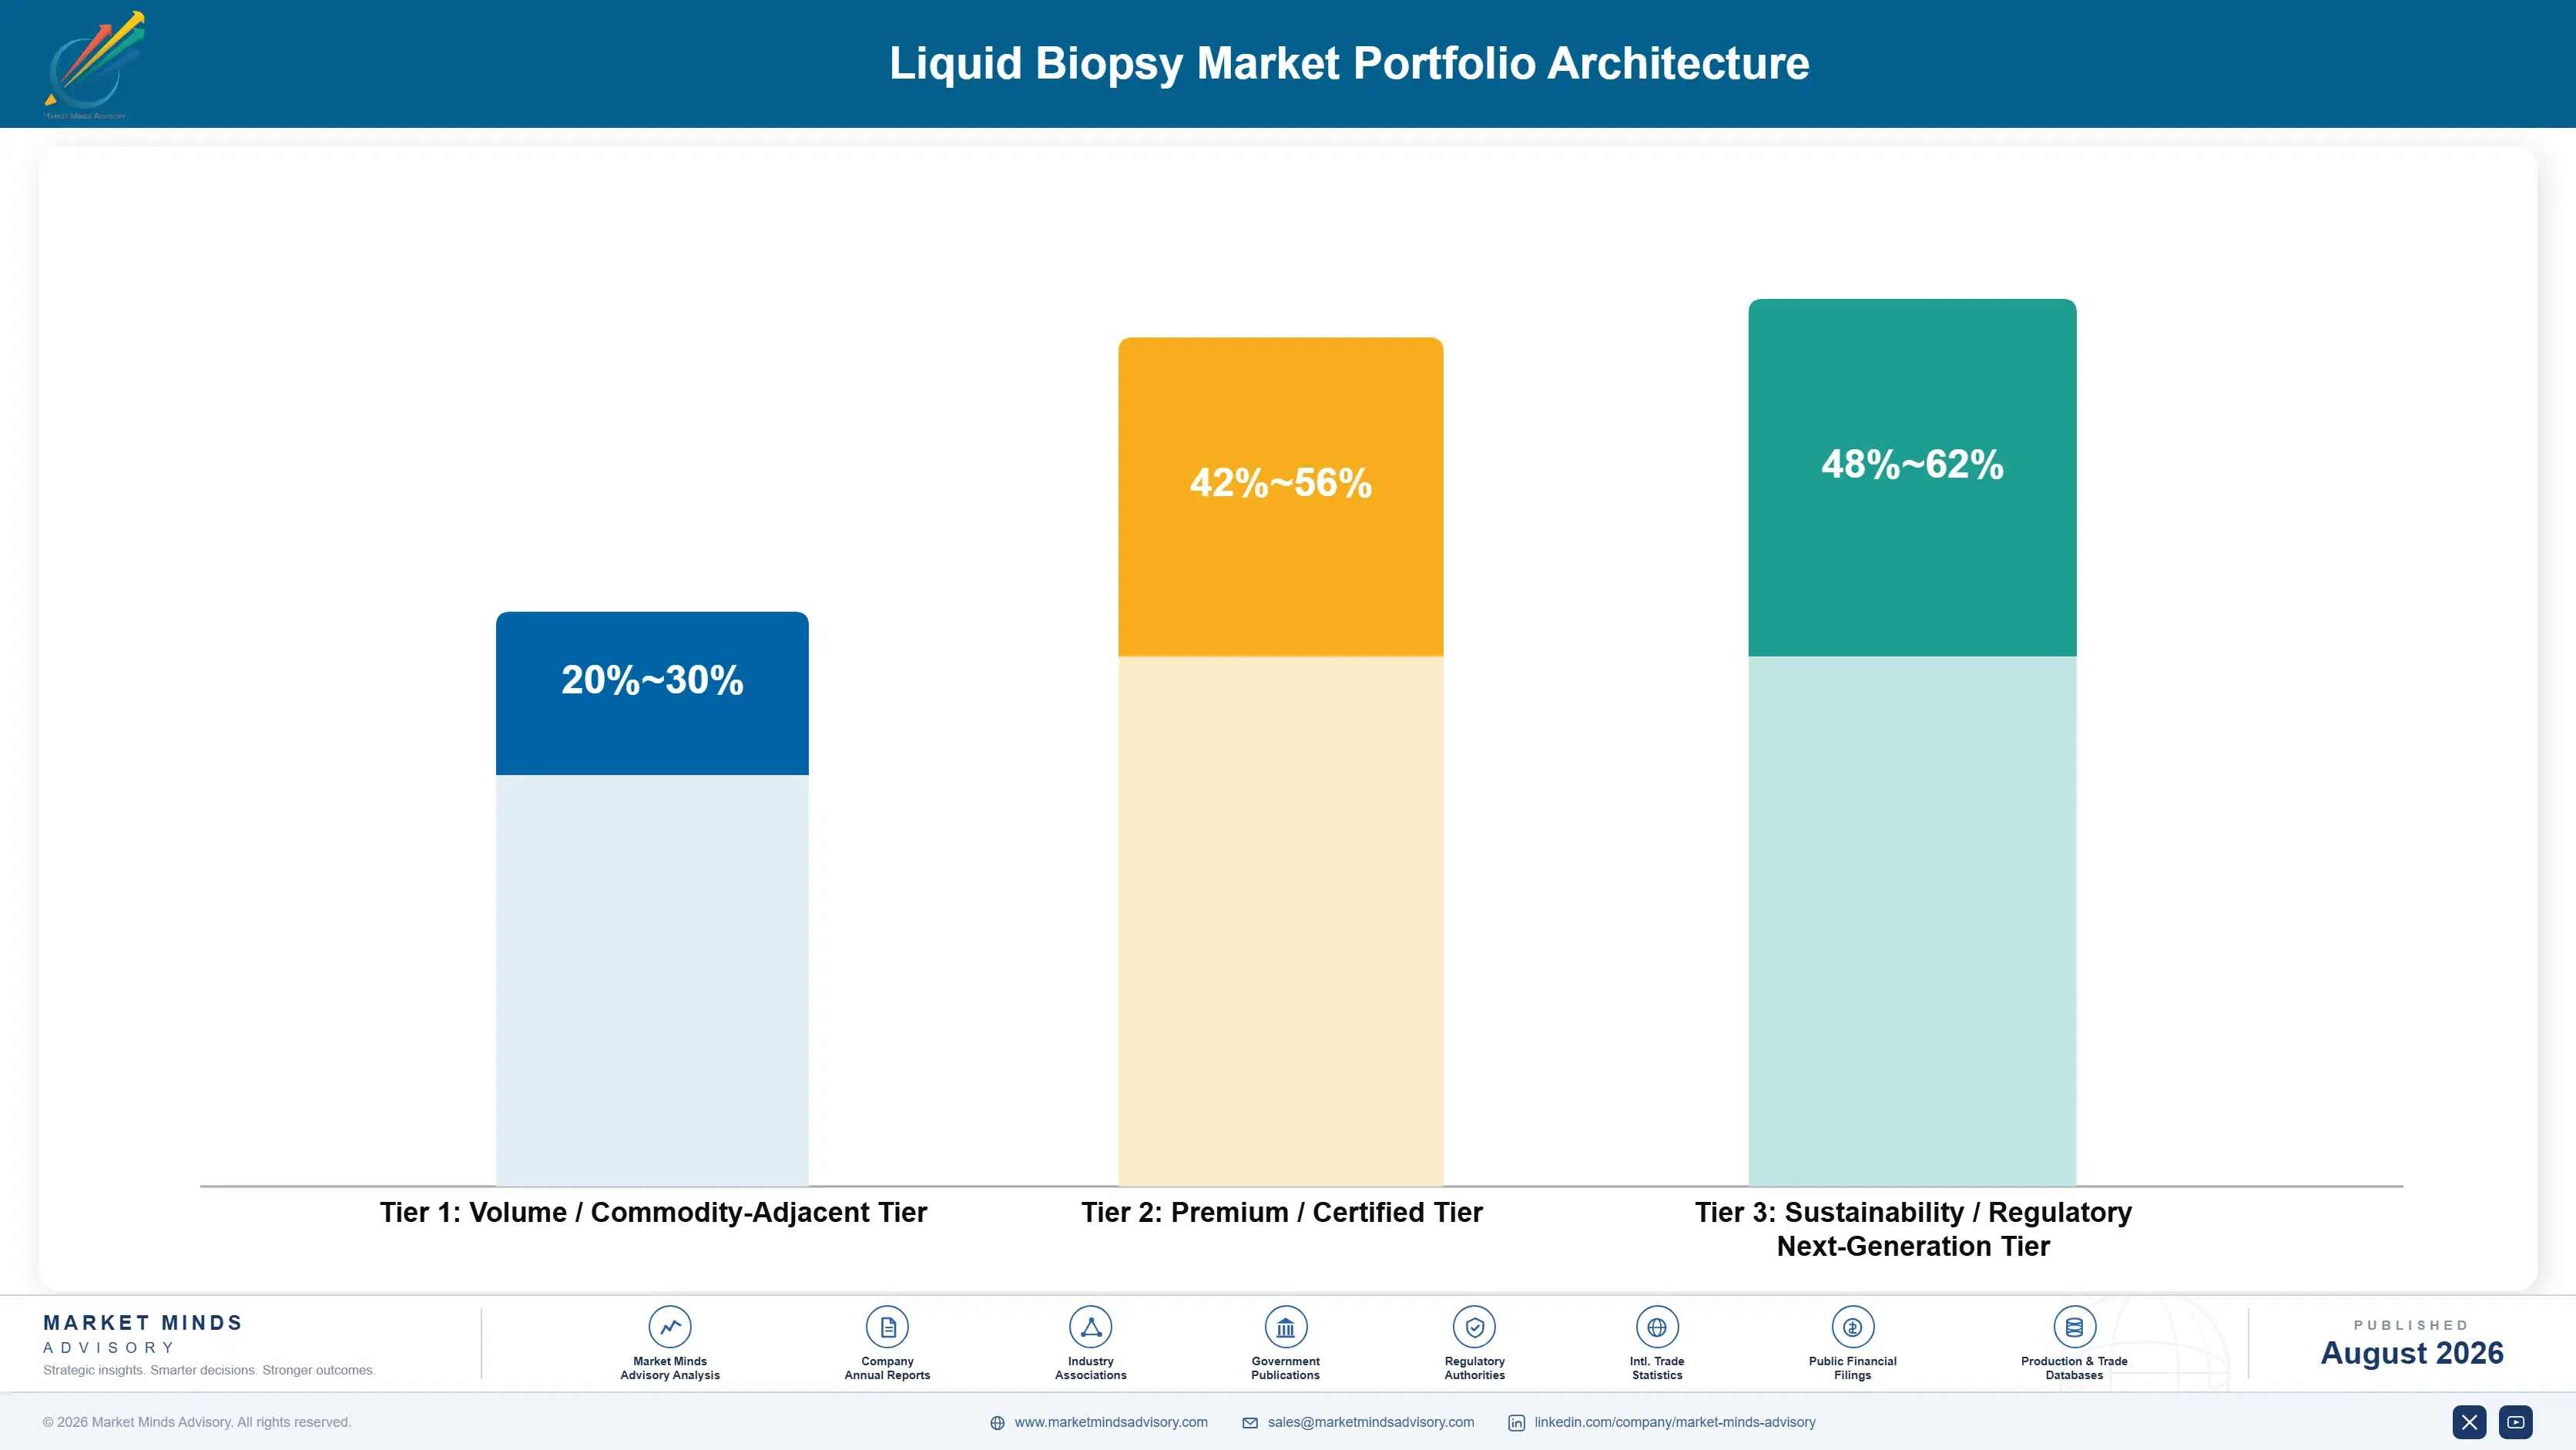
The portfolio splits into three tiers with real margin separation, and the gap between tiers has widened as clinical validation depth becomes a genuine differentiator rather than an incremental feature. Volume-tier companion diagnostic testing competes on price against generic laboratories and earns modestly. Premium screening and framework-negotiated formats earn considerably more because they solve a genuine early detection problem that payers cannot engineer around cheaply.
The tension is between companion diagnostic volume and per-country negotiated screening margin. Makers selling companion diagnostics in bulk push hard on unit price, while national cancer programmes standardising on screening framework agreements pay for detection sensitivity and outcome data depth rather than negotiating down to the last dollar on every single test. Makers serving both categories run genuinely different commercial motions under one broader disease area.

High-value pools concentrate in screening and MRD monitoring formats sold with outcome registry programmes and national framework agreements, where switching cost runs highest and price sensitivity lowest given the differentiated clinical evidence base. Legacy companion diagnostic business remains meaningful in volume but persistently thin in margin, as payers increasingly treat it as a standard-of-care purchase rather than a differentiated one worth defending.

Volume / Commodity-Adjacent Tier

Companion diagnostic testing sold into routine treatment selection, priced against generic laboratories on thin margin. Payers negotiate primarily on unit price rather than screening differentiation, keeping this tier's margin persistently compressed.
Gross Margin: 20-30%

Premium / Certified Tier

Screening and framework-negotiated formats sold into national programmes standardising reimbursement protocols across their full diagnosed population and treatment centres. Payers pay for detection sensitivity and outcome data depth rather than for chemistry alone.
Gross Margin: 42-56%

Sustainability / Regulatory / Next-Generation Tier

Advanced MRD and multi-cancer systems bundled with outcome registry support sold to national cancer programmes and specialty centres seeking documented compliance. Margin reflects both technology differentiation and recurring specification loyalty over time.
Gross Margin: 48-62%
liquid-biopsy-market-portfolio-architecture-1787306006313

High-value Sub-segments and Strategic Watch-out

Multi-Cancer Early Detection Screening

High value and high growth at 18.0%, the fastest segment, as asymptomatic patients increasingly seek blood-based screening covering dozens of cancer types from a single annual draw. Illumina and Exact Sciences dominate current pipeline activity, though challengers like Guardant Health are closing the gap fast this cycle.
Gross Margin: 48-62%

Minimal Residual Disease Monitoring

High value with strong growth at 15.0%, favoured wherever oncologists need molecular recurrence signals months before imaging surveillance would detect relapse across every major cancer type, treatment protocol, and clinical setting. Natera and Foundation Medicine lead current MRD adoption broadly across mainstream and premium accounts alike.
Gross Margin: 42-56%

Companion Diagnostic and Treatment Selection Testing

The volume core, well established across standard treatment pathways, competing on price against generic laboratories in most non-specialised applications and contract categories across every major market and geography worldwide today. Growth here tracks standard replacement volume broadly rather than any new demand or premium upgrades.
Gross Margin: 20-30%

Circulating Tumor Cell Analysis Platforms

The strategic watch-out. Commoditisation and clinical substitution toward ctDNA-based testing threaten a persistent margin decline as improving molecular sensitivity increasingly reduces reliance on cell-based analysis across most reimbursed patient populations, geographies, account tiers, supplier relationships, national drug budgets, and annual reimbursement negotiation cycles going forward.

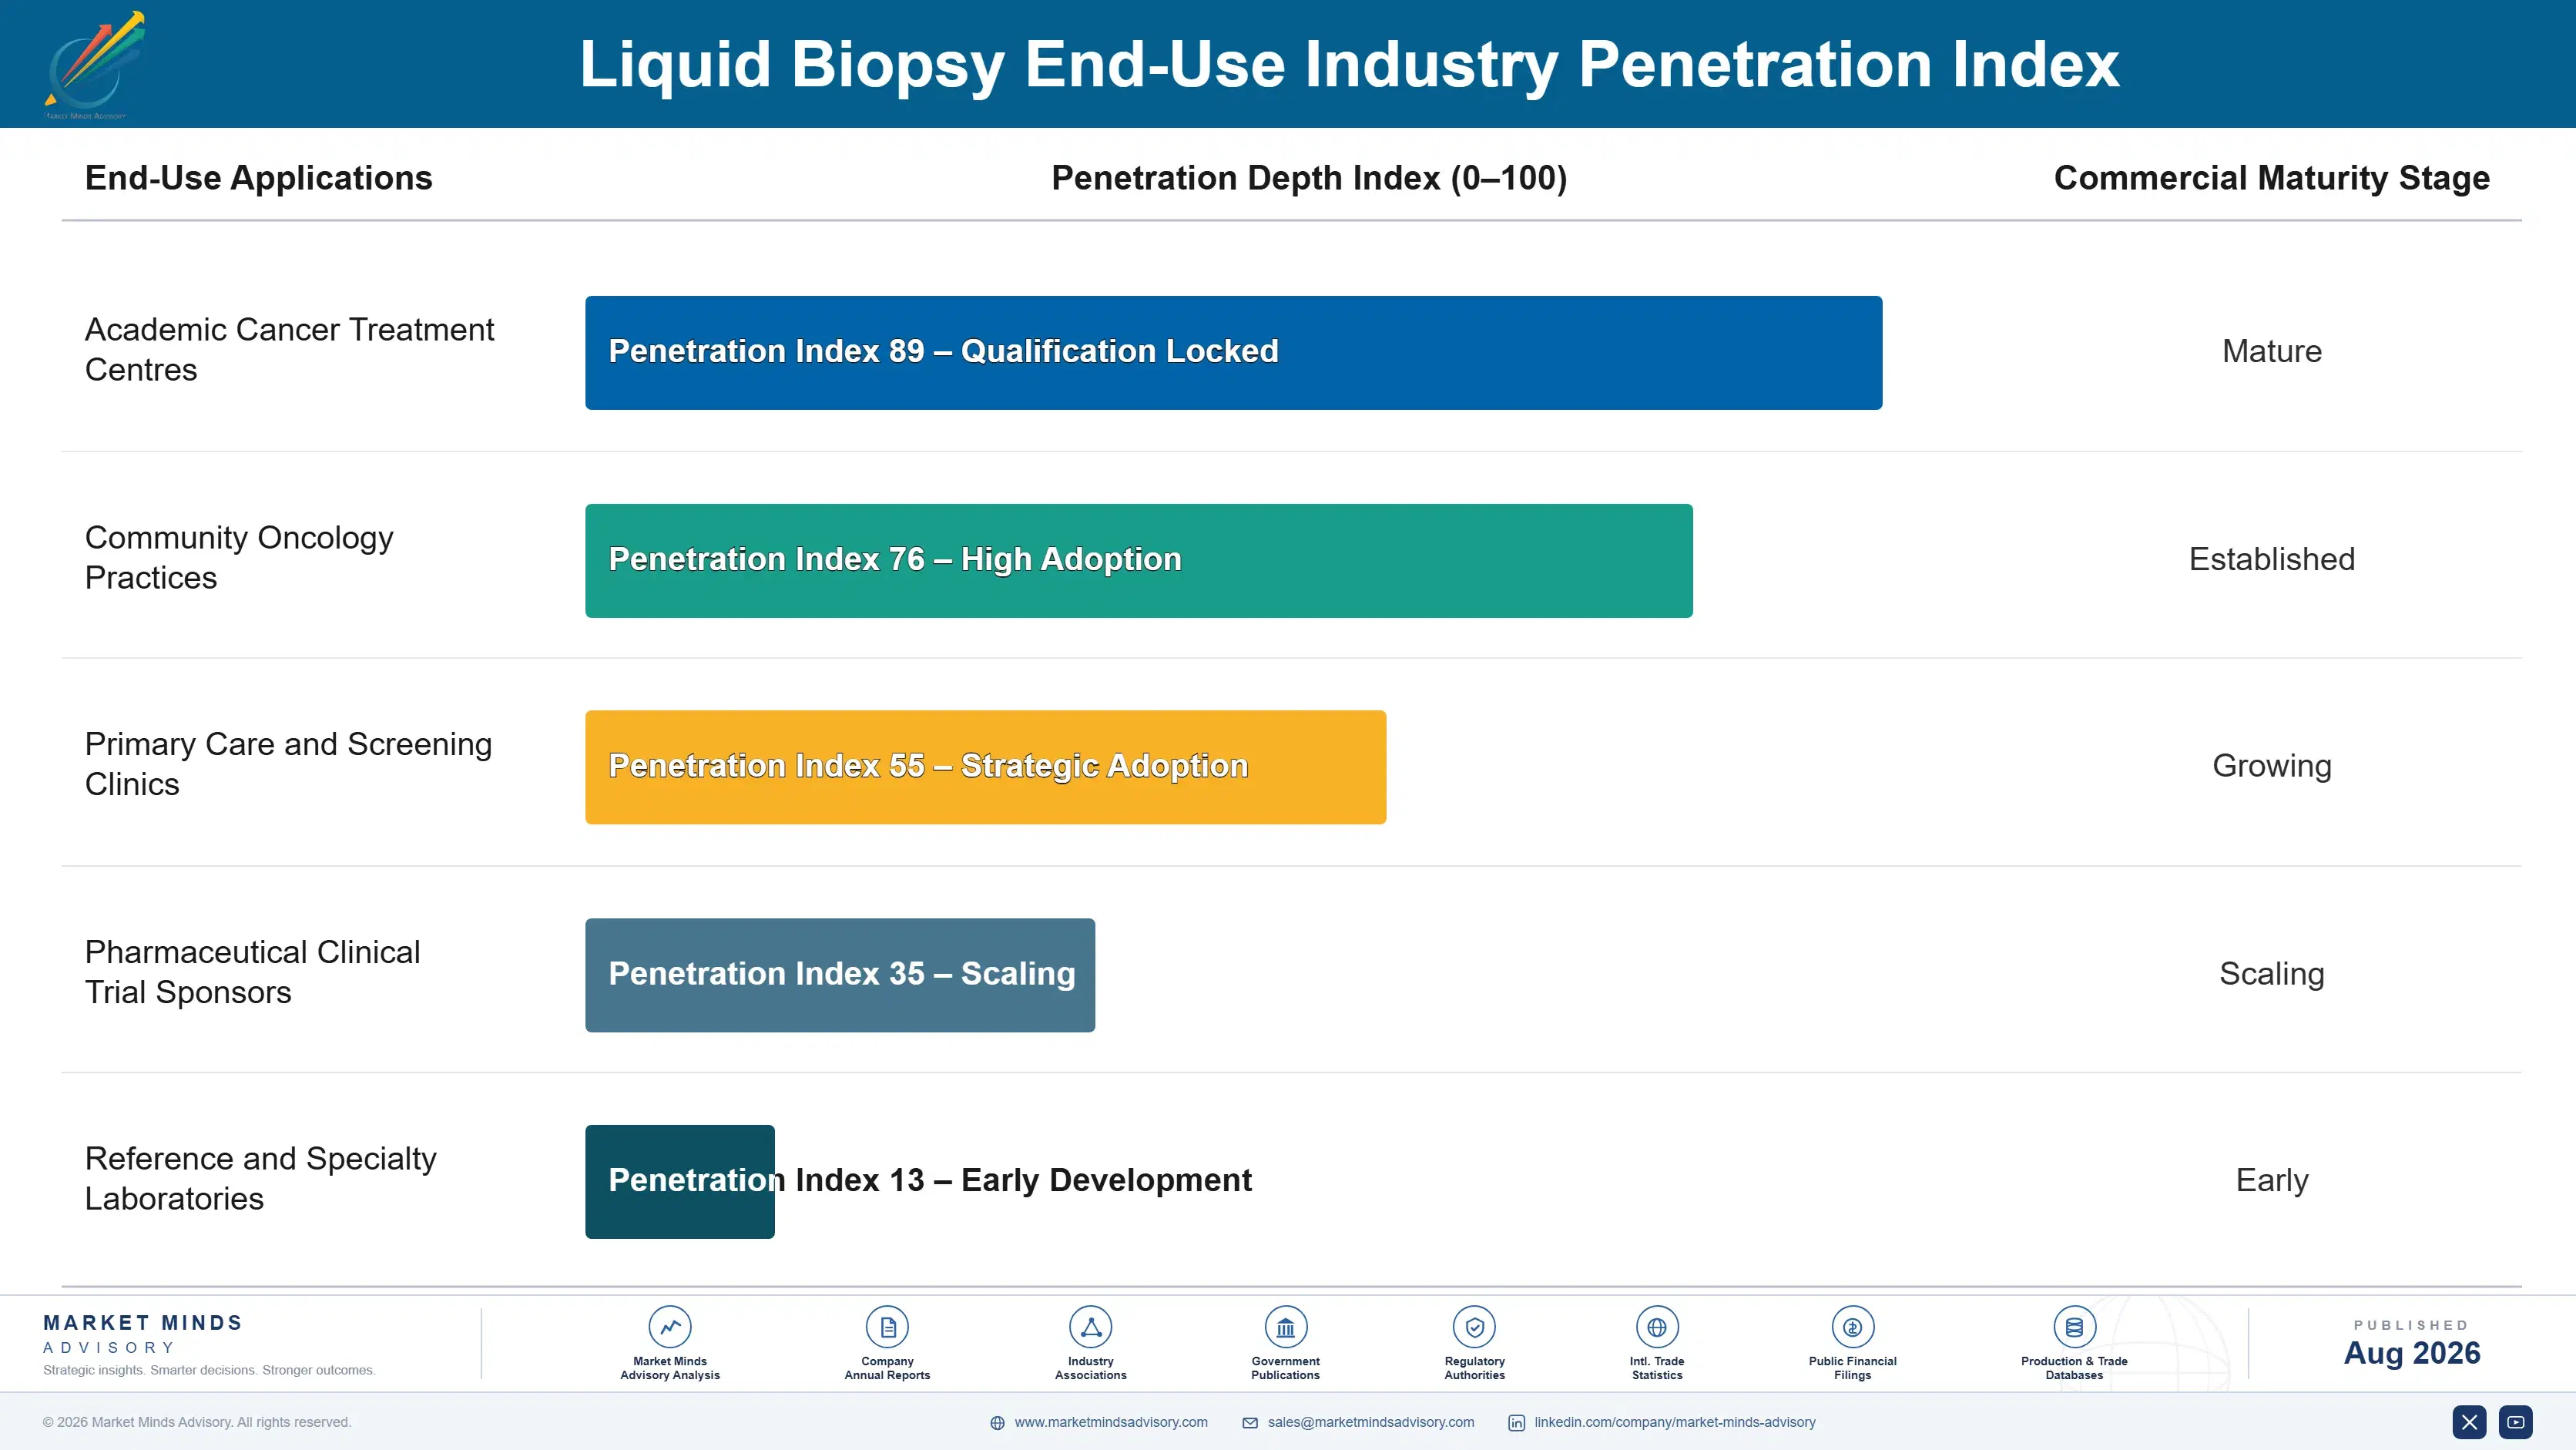
Recurring Testing Revenue Behind Every Patient

Demand behaves like an annuity once a patient enters a screening or monitoring programme, because cancer surveillance remains an ongoing clinical need requiring continuing periodic testing throughout a patient's treatment or screening journey and requires renewed reimbursement alongside continuing outcome monitoring. That continuity, plus the underlying diagnosed pool expansion demand it eventually triggers, gives makers a predictable revenue tail well beyond any single test or reimbursement ren
Adoption depth varies sharply by patient vertical. Newly diagnosed cancer patients adopt recurrence monitoring fastest and deepest, since earlier detection directly improves long-term survival outcomes across their full treatment journey. Post-treatment survivors follow closely on MRD monitoring adoption, chasing comparable outcomes at a somewhat slower pace given established surveillance imaging habits. Asymptomatic screening candidates adopt more slowly, often waiting for a payer coverage decision or physician recommendation to force the testing decision.

Buyer profiles are shifting generationally. Prescribing once sat with individual oncologists evaluating single testing platforms on their own; it now increasingly involves national health authority reimbursement committees who specify coverage standards before a single physician orders a test at all. That shift moves the real access decision earlier into the national negotiation cycle, well ahead of any single patient's test order.
liquid-biopsy-market-end-use-penetration-index-1787306006805

Where Liquid Biopsy Value Concentrates

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / SCREENING PLATFORM STRATEGY

Multi-Cancer Detection Now Decides Franchise Growth

Multi-cancer early detection screening is growing at 18.0%, about 1.64 times the market's 11.0% overall rate, and that gap is widening as asymptomatic patients increasingly seek blood-based screening covering dozens of cancer types from a single annual draw. Makers still anchored on companion diagnostics alone risk losing the fastest-growing, highest-value screening patients to rivals offering proven multi-cancer capability already in clinical deployment. The window to build credible screening capability is closing within this forecast period, and makers who act now capture the largest remaining addressable population.
02 / OUTCOME DATA STRATEGY

Verified Long-Term Data Is Becoming Table Stakes

National cancer programmes increasingly refuse to commit full reimbursement without documented, longitudinal outcome registry data, since unverified launch trial claims represent a genuine budget liability risk under tightening health technology assessment regulation across multiple jurisdictions worldwide today. Makers who build this registry capability capture recurring reimbursement renewal loyalty and preferred-therapy status that launch-data-only competitors cannot easily replicate at comparable scale. Those without a credible outcome registry programme will find themselves facing renewal negotiation risk, losing meaningful value to better-equipped rivals.
03 / NATIONAL PROGRAMME CHANNEL

National Frameworks Will Outgrow Centre-By-Centre Access

National cancer programmes are increasingly folding reimbursement negotiation into corporate health authority standards rather than leaving it to individual treatment centres, concentrating real purchasing power in a small number of framework decisions that smaller makers cannot easily access at scale. Makers who secure framework status with major national programmes capture revenue across an entire diagnosed population that no number of individual centre negotiations can replicate on comparable terms. Those still negotiating purely centre by centre risk being locked out of this fastest-growing channel entirely and permanently.
04 / EMERGING BIOTECH PRICING

Academic Entrants Will Keep Pressuring Category Economics

Academic and biotech entrants have scaled fast enough to attract meaningful clinical trial investment for false-positive-sensitive patients that leading platforms once assumed would remain permanently uncertain, and that competitive pressure is starting to spread into broader screening categories as confirmatory technology matures. Makers competing purely on screening breadth against emerging academic platforms will struggle to hold long-term category leadership. The more durable response is competing on outcome data depth and validation credentials, categories where the leading platforms still hold a meaningful lead today.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Liquid Biopsy Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Liquid Biopsy Exposure Evaluation 2025-26
CLIENT PROFILE
A national cancer screening programme covering a mid-size country's full eligible screening population approached MMA after facing budget pressure to expand multi-cancer screening reimbursement to newly eligible average-risk patients. The client reported that inconsistent access criteria across its regional health authorities was creating equity and budget forecasting risk that leadership considered urgent to resolve before the next budget cycle (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
The programme had negotiated screening access for its original approved high-risk population years earlier without a structured plan for absorbing subsequent coverage expansions, assuming gradual case-by-case exception approval would suffice. The accelerating pace of screening validation data and physician demand forced leadership to confront how far behind current budget forecasting models its programme had fallen, with a fixed annual diagnostic budget.
MMA APPROACH
MMA benchmarked the programme's reimbursement readiness against comparable national programmes already absorbing multiple coverage expansions, quantifying the budget impact a structured multi-year framework would realistically require. We evaluated tiered access options sized to each patient subgroup's clinical priority, and modelled a phased reimbursement schedule against the programme's fixed annual budget.
KEY FINDINGS
  1. The programme's existing case-by-case exception process showed considerably longer patient access timelines than comparable programmes already working with structured multi-year frameworks, based on benchmarking performed during the review.
  2. A tiered reimbursement approach concentrated on the programme's highest-risk patient subgroup addressed most of the equity risk without requiring simultaneous coverage of every risk category immediately.
  3. Modelling showed the programme's fixed budget could absorb high-risk expansion within twelve months but would require phased average-risk coverage to avoid an immediate budget overrun.
  4. Phasing reimbursement by patient subgroup rather than attempting simultaneous full coverage considerably improved the programme's budget forecasting accuracy during the review window (client-reported, unverified by MMA).
CLIENT PROFILE
A national cancer screening programme covering a mid-size country's full eligible screening population approached MMA after facing budget pressure to expand multi-cancer screening reimbursement to newly eligible average-risk patients. The client reported that inconsistent access criteria across its regional health authorities was creating equity and budget forecasting risk that leadership considered urgent to resolve before the next budget cycle (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
The programme had negotiated screening access for its original approved high-risk population years earlier without a structured plan for absorbing subsequent coverage expansions, assuming gradual case-by-case exception approval would suffice. The accelerating pace of screening validation data and physician demand forced leadership to confront how far behind current budget forecasting models its programme had fallen, with a fixed annual diagnostic budget.
MMA APPROACH
MMA benchmarked the programme's reimbursement readiness against comparable national programmes already absorbing multiple coverage expansions, quantifying the budget impact a structured multi-year framework would realistically require. We evaluated tiered access options sized to each patient subgroup's clinical priority, and modelled a phased reimbursement schedule against the programme's fixed annual budget.
KEY FINDINGS
  1. The programme's existing case-by-case exception process showed considerably longer patient access timelines than comparable programmes already working with structured multi-year frameworks, based on benchmarking performed during the review.
  2. A tiered reimbursement approach concentrated on the programme's highest-risk patient subgroup addressed most of the equity risk without requiring simultaneous coverage of every risk category immediately.
  3. Modelling showed the programme's fixed budget could absorb high-risk expansion within twelve months but would require phased average-risk coverage to avoid an immediate budget overrun.
  4. Phasing reimbursement by patient subgroup rather than attempting simultaneous full coverage considerably improved the programme's budget forecasting accuracy during the review window (client-reported, unverified by MMA).
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 6 months): Extend reimbursement to the programme's highest-risk patient subgroup first, prioritising those facing the most time-sensitive screening windows. Phase 2: Phase 2 (6 to 18 months): Extend coverage to remaining average-risk patient subgroups across the programme's full population, validating budget forecasting accuracy at each stage. Phase 3: Phase 3 (18 to 36 months): Fold the phased reimbursement approach into the programme's standing diagnostic budget process going forward, reviewing coverage decisions annually.
OUTCOME
The programme extended reimbursement to its highest-risk patient subgroup ahead of its budget deadline and reported no equity gaps during the following review period. The phased reimbursement approach has since extended to its remaining average-risk patient subgroups facing later coverage decisions (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Liquid Biopsy Market?

The market was valued at USD 6.5 billion in 2025, with demand concentrated in companion diagnostic and multi-cancer screening formats across major precision oncology markets.

How large will the Liquid Biopsy Market be by 2036?

The market is projected to reach USD 20.49 billion by 2036, an expansion multiple of 2.84 times its 2026 value. Screening adoption drives much of that growth.

What is the CAGR for the Liquid Biopsy Market 2026 to 2036?

The base case CAGR is 11.0%, with a bull case of 12.3% and a bear case of 9.7%. The range reflects uncertainty around national screening reimbursement decisions.

Which segment is growing fastest?

Multi-cancer early detection screening grows fastest at 18.0%, about 1.64 times the overall market rate, as asymptomatic patients seek blood-based screening for dozens of cancer types.

Who are the major companies in the Liquid Biopsy Market?

Guardant Health, Exact Sciences, Illumina, Natera, and Foundation Medicine lead the consolidated market at CR5 52%, reflecting deep clinical trial and payer relationship history across regions.

Which country is growing fastest?

India grows fastest at 14.5%, driven by rapidly expanding private healthcare access and rising cancer awareness. The United States remains the largest diagnosed patient market.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Clinical Application and Technology

  • Multi-Cancer Early Detection Screening
  • Minimal Residual Disease Monitoring
  • Companion Diagnostic and Treatment Selection Testing
  • Cancer Recurrence Monitoring
  • Circulating Tumor Cell Analysis Platforms
  • Exosome and Extracellular Vesicle Analysis

By End-Use Industry

  • Academic Cancer Treatment Centres
  • Community Oncology Practices
  • Primary Care and Screening Clinics
  • Pharmaceutical Clinical Trial Sponsors
  • Reference and Specialty Laboratories

By Commercial Dimension

  • National Cancer Programme Framework Agreements
  • Pharmacy Benefit Manager Contracts
  • Distributor and Group Purchasing Contracts
  • Direct Physician Ordering

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The liquid biopsy market comprises minimally invasive diagnostic tests that analyze circulating tumor DNA, circulating tumor cells, exosomes, and other tumor-derived biomarkers from blood and body fluid samples, spanning multi-cancer early detection screening, minimal residual disease monitoring, companion diagnostic and treatment selection testing, cancer recurrence monitoring, circulating tumor cell analysis platforms, and exosome and extracellular vesicle analysis. Tissue biopsy diagnostics, general blood chemistry panels unrelated to cancer biomarkers, and germline genetic testing for inherited cancer risk performed without tumor-derived biomarker analysis are excluded.
Quantitative Units
USD billions (current prices); tested patient volume where applicable
Segmentation Dimensions
By Clinical Application and Technology; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Thailand, Malaysia, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Guardant Health Inc., Exact Sciences Corporation, Illumina Inc., Natera Inc., Foundation Medicine Inc., Bio-Rad Laboratories Inc., Thermo Fisher Scientific Inc., QIAGEN N.V., Menarini Silicon Biosystems S.p.A., ANGLE plc, Biodesix Inc., Personalis Inc., Adaptive Biotechnologies Corporation, Freenome Holdings Inc., Delfi Diagnostics Inc., Burning Rock Biotech Limited, NeoGenomics Laboratories Inc., Myriad Genetics Inc., Bio-Techne Corporation, Twist Bioscience Corporation
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-129
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Liquid Biopsy Market Report (2026 to 2036).

The full MMA Liquid Biopsy report sizes the market across six clinical application and technology types, five end-use verticals, four commercial dimensions, and seven regions through 2036. It profiles twenty participants on a consistent testing revenue basis, scoring each on detection sensitivity, outcome data depth, and multi-country reimbursement reach. Scenario models quantify how screening reimbursement expansion, cancer incidence growth, and MRD monitoring adoption move both demand and realised pricing. The report also includes delivered-cost modelling by clinical application and a national cancer programme benchmarking tool built for market access and precision oncology strategy teams.
Clinical application cost and sensitivity benchmarking
Diagnosed patient pool and screening tracker by region
National reimbursement framework structure and pricing tracker
Screening coverage policy comparison by country
Sequencing reagent supply chain risk screen
Outcome registry revenue forecasting and modelling

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts