Market Minds Advisory
KRAS Inhibitor Market

KRAS Inhibitor Market: When Mutation Coverage Breadth Replaced Approval Count As The Real Product

A commercial reading of the KRAS inhibitor market, where pan-KRAS pipeline advancement and expanding comprehensive genomic profiling are pulling prescribing revenue toward broad mutation coverage faster than the single-mutation drugs that launched this category.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$1.8BMarket Size 2025
2036 FORECAST VALUE$10.6BBase Case , 2026 to 2036
CAGR 2026 TO 203617.5 %Bull 18.9% / Bear 16.1%
INCREMENTAL OPPORTUNITY$8.5BNet 10- year value creation
EXPANSION MULTIPLE5.01x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

KRAS inhibitor treatment selection increasingly turns on validated mutation coverage breadth rather than raw approval count alone, as oncologists weigh pan-KRAS pipeline depth over simple G12C-specific efficacy that once defined prescribing choice broadly across most precision oncology settings entirely and consistently across most developed markets.
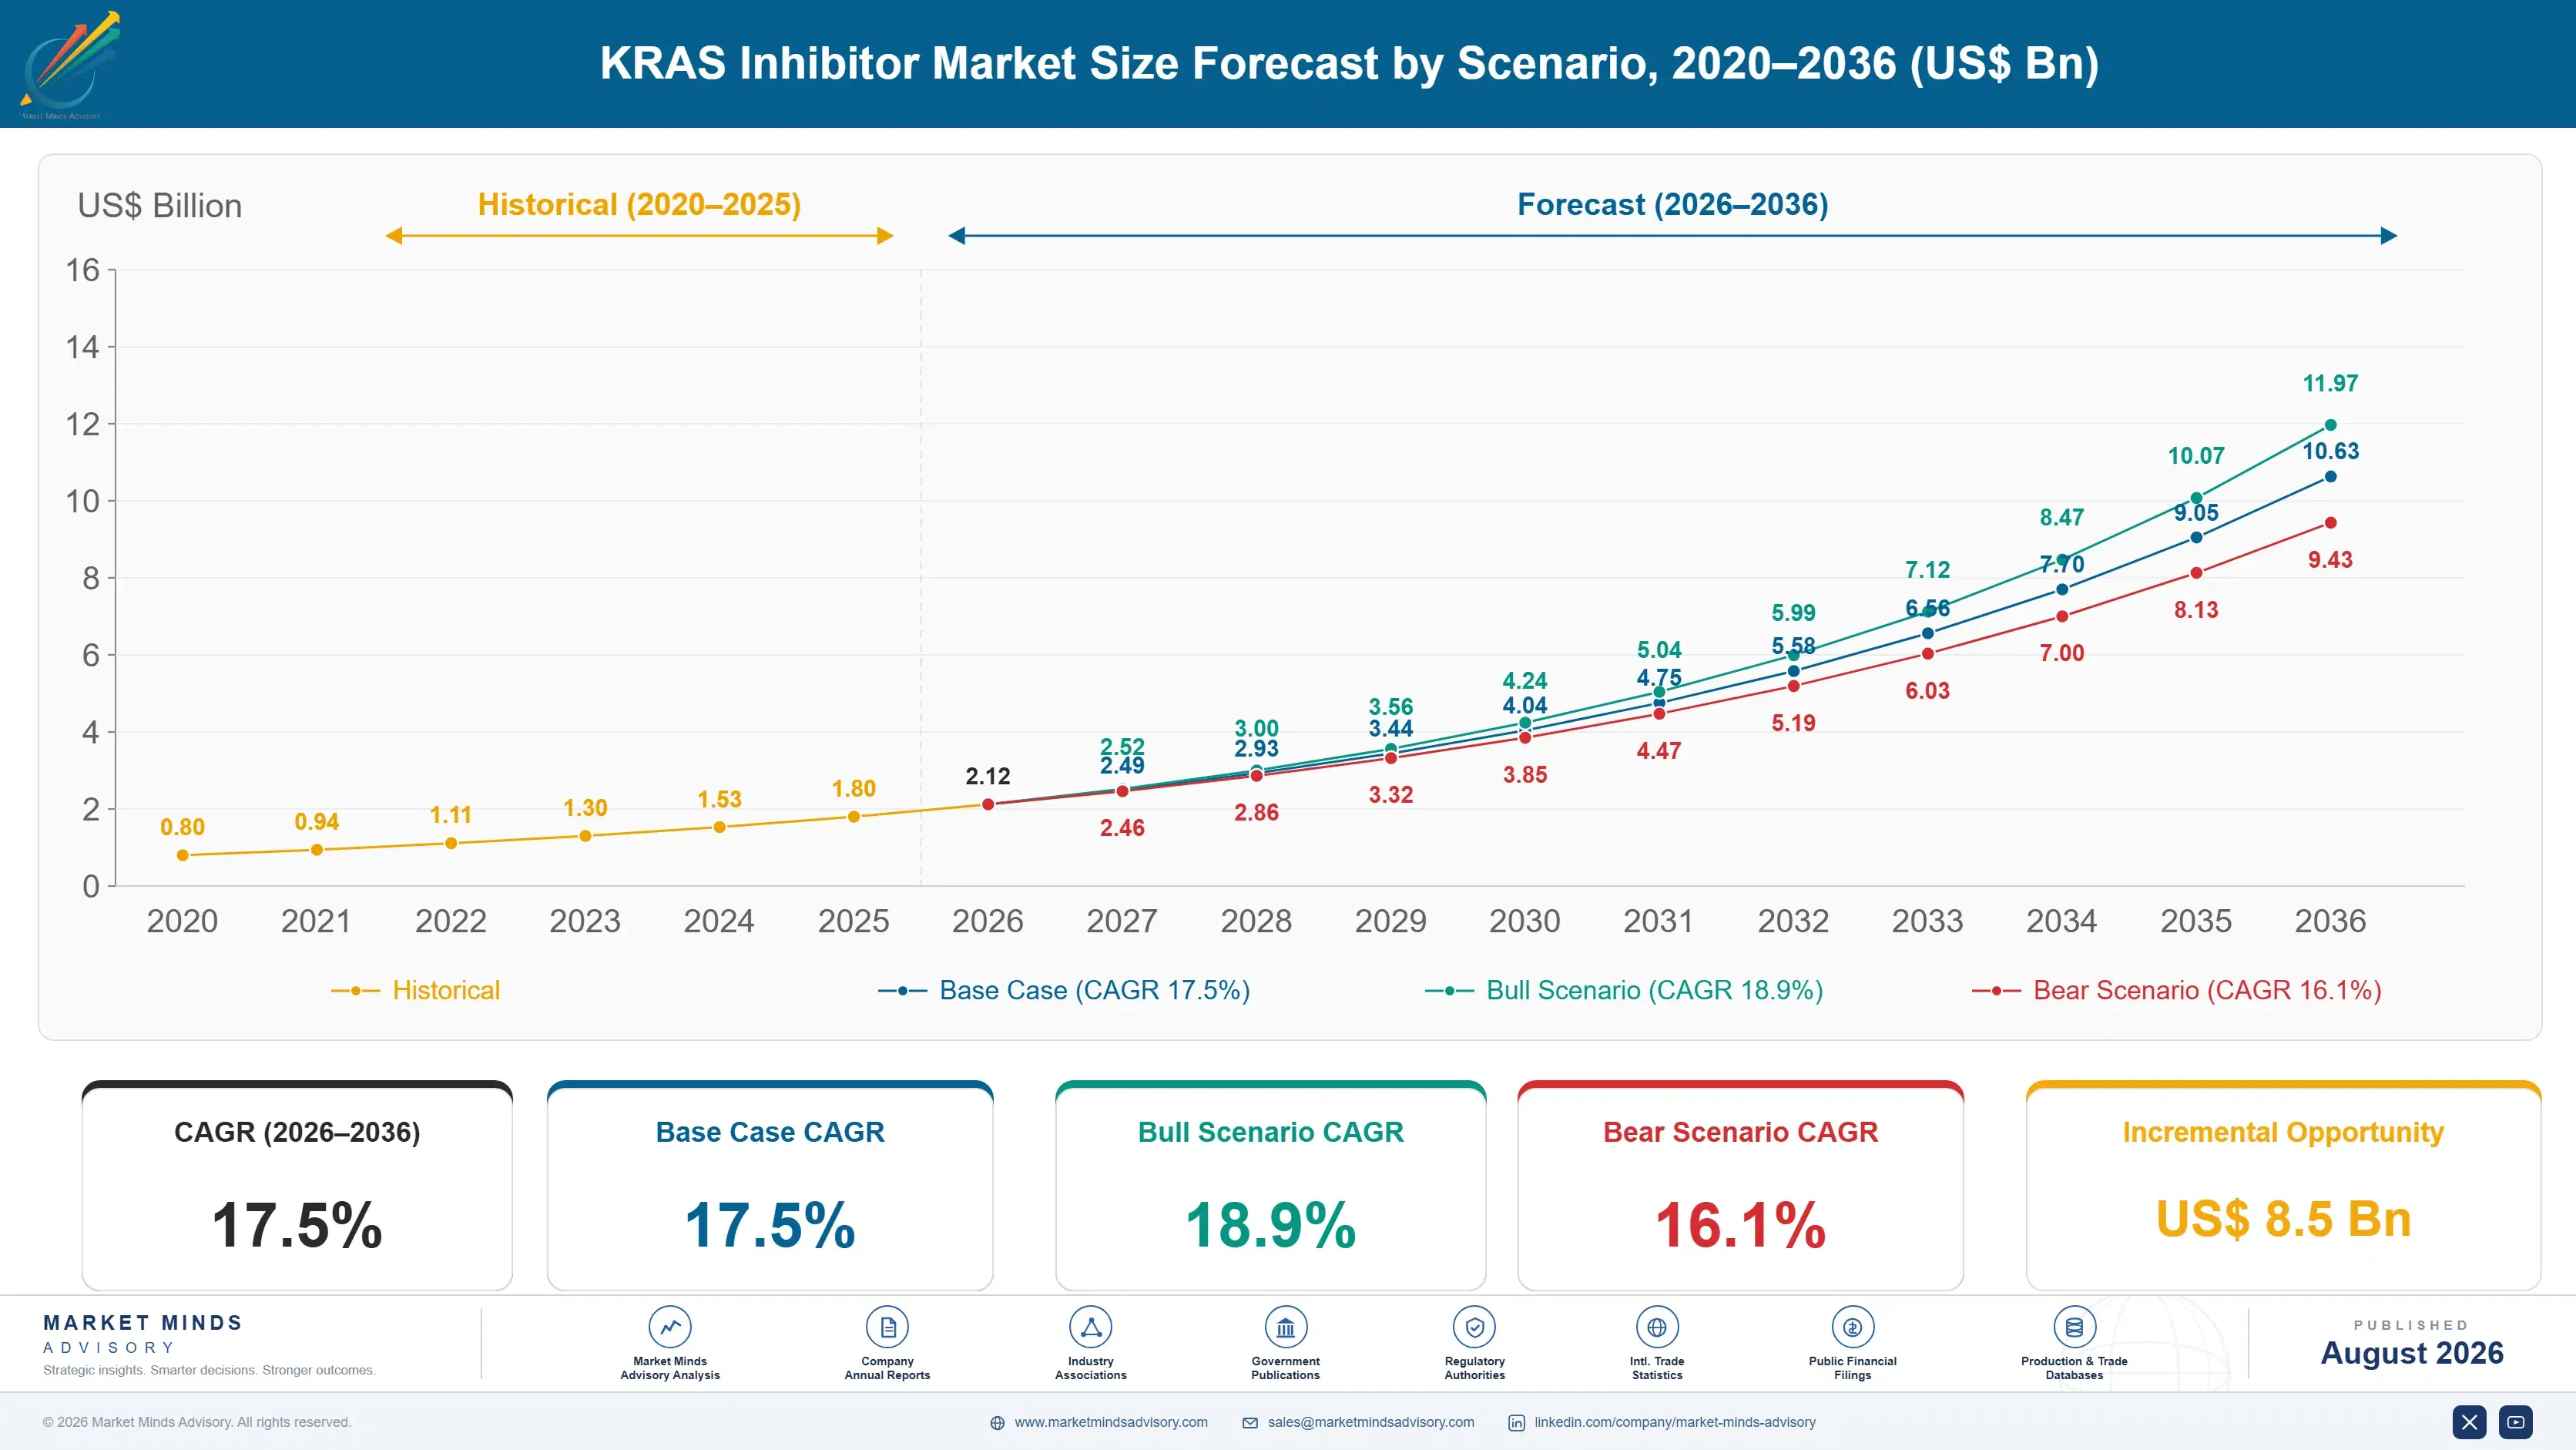
The market stands at USD 2.12 billion in 2025 and reaches USD 10.63 billion by 2036 at a 17.5% CAGR. Pan-KRAS inhibitors grow fastest at 24.0%, roughly 1.37 times the overall rate, as developers pursue broader mutation coverage beyond the G12C-specific drugs that defined the category's first approval wave. North America holds 40% of value on concentrated precision oncology infrastructure, while South Asia and Pacific posts the quickest regional growth at 19.5%.
Concentration sits near 58%, split between the two originating G12C developers holding dominant approved-drug share and emerging pan-KRAS and G12D developers pursuing differentiated mutation coverage across most oncology markets worldwide today entirely and consistently now. Two forces dominate ahead. Comprehensive genomic profiling expansion is widening the addressable patient population, and combination therapy regimens are turning resistance management into a genuine commercial differentiator rather than a purely clinical concern.
Market Definition
The KRAS inhibitor market covers small-molecule and targeted therapeutics designed to inhibit mutant KRAS protein signaling in cancers, including G12C, G12D, G12V, and pan-KRAS mechanisms across approved and pipeline compounds. General chemotherapy and broad-spectrum targeted therapies are excluded.
Base Year Value
$1.8B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
17.5% base case. Bull 18.9%. Bear 16.1%.
Fastest Growth Segment
Pan-KRAS Inhibitors: 24.0% CAGR
Fastest Growth Country
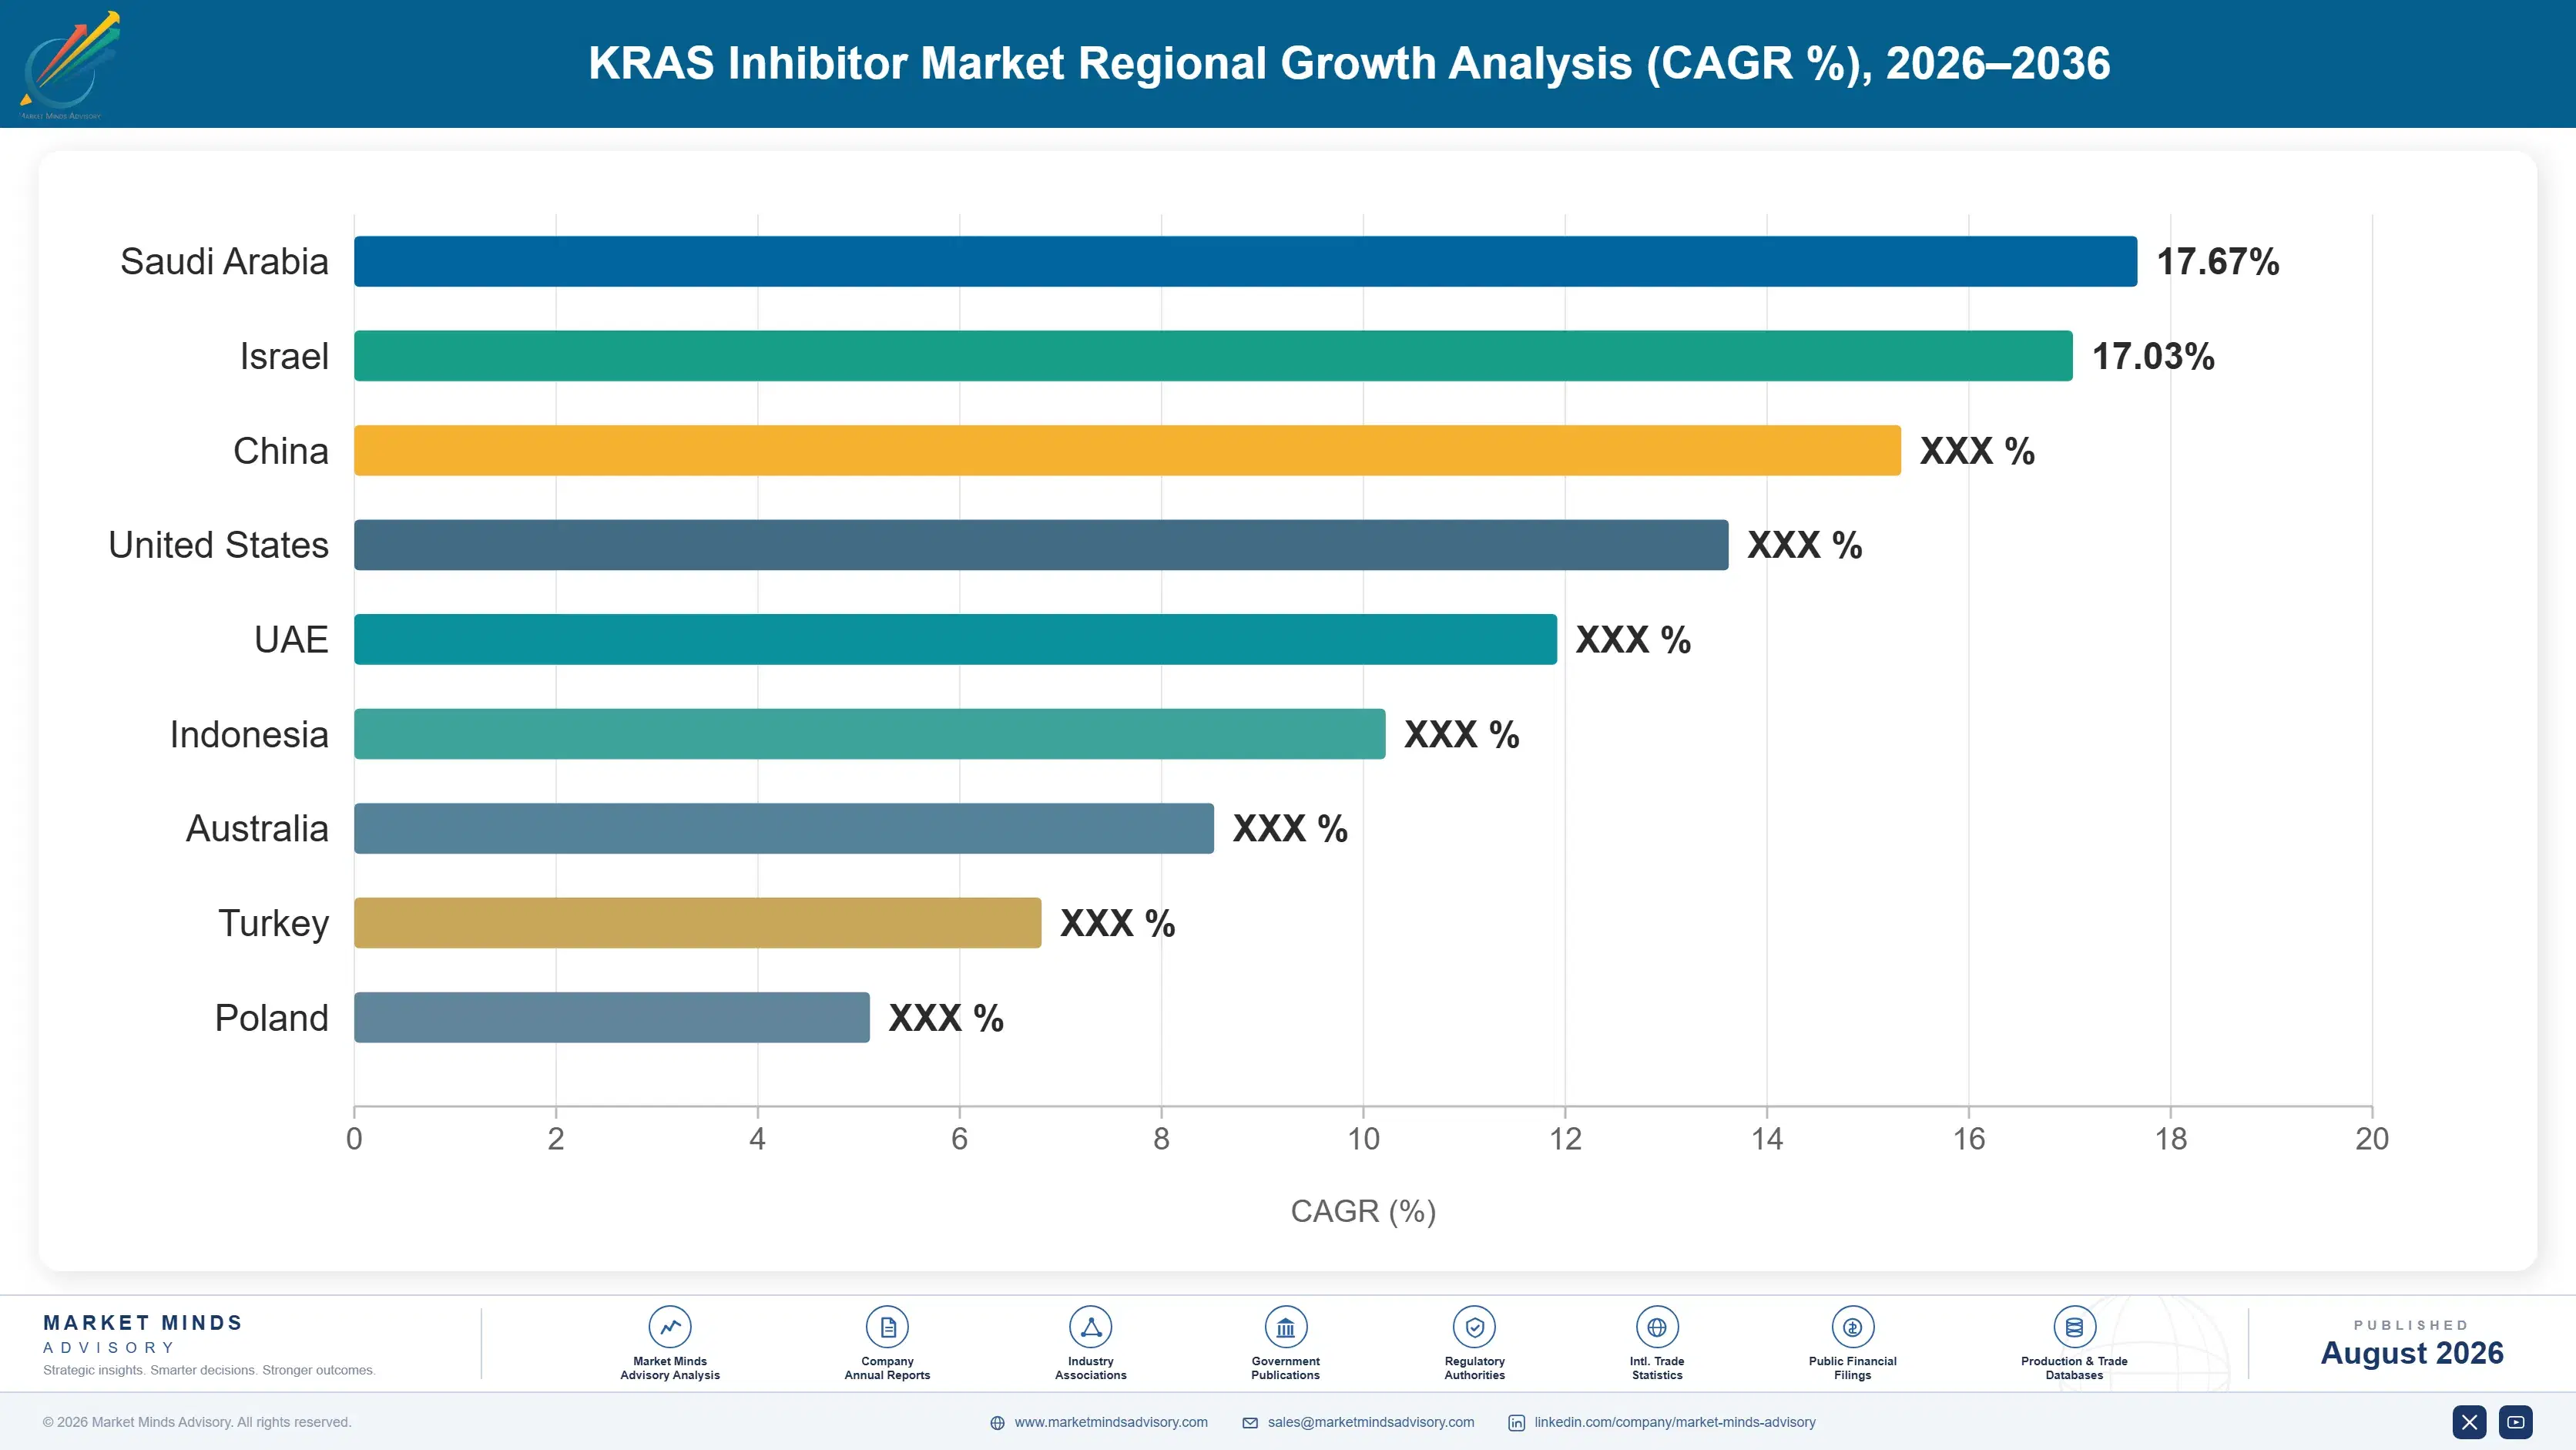
United States: 19.2% CAGR
Fastest Growth Region
South Asia and Pacific: 19.5% CAGR
Largest Region
North America: 40% of 2025 global value
Market Leaders
Amgen, Bristol Myers Squibb (Mirati Therapeutics), Revolution Medicines, Boehringer Ingelheim, Roche (Genentech). Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

KRAS Inhibitor Market Forecast Scenarios

kras-inhibitor-market-size-forecast-scenario-1787298306162
Growth from 2020 to 2025 compounded near 16.0%, tracking rapid commercial launch following the first G12C inhibitor approval in 2021 closely across most developed oncology markets globally, with prescribing volume accelerating sharply as comprehensive genomic profiling adoption expanded testing access throughout the period. A second approved G12C drug followed within a year, deepening category validation considerably.
Three mechanisms carry the base case to 17.5%. First, pan-KRAS inhibitor pipeline advancement expanding as developers pursue broader mutation coverage beyond G12C-specific drugs across most major precision oncology categories worldwide currently building clinical evidence and regulatory submission momentum steadily. Second, comprehensive genomic profiling expansion continuing to widen the addressable patient population eligible for targeted KRAS therapy across developed markets. Third, combination therapy regimens continuing to drive incremental prescribing demand addressing acquired resistance globally.
The bull case at 18.9% assumes pan-KRAS approval and genomic profiling expansion accelerate faster than currently planned across major oncology markets worldwide. The bear case at 16.1% assumes pipeline attrition slows pan-KRAS approval timelines considerably, genomic profiling adoption in developing markets proceeds more slowly than expected, and combination therapy development proceeds more gradually than current expectations suggest.

Why Mutation Coverage Breadth, Not Approval Count, Now Sets Prescribing Contracts

Three forces set demand here. Pan-KRAS inhibitor pipeline advancement drives the largest new-value growth, as developers pursue broader mutation coverage beyond G12C-specific drugs. Comprehensive genomic profiling expansion drives a second stream, since testing access increasingly determines addressable patient population. Combination therapy regimens drive a third, steadier stream.
MARKET CONCENTRATIONCR5: 58%Split between originating first-wave developers and emerging pan-KRAS competitors
OBJECTIVE RESPONSE RATEUp to 46%Typical objective response rate achieved with validated first-wave inhibitor monotherapy
TREATMENT DURATION MEDIAN6 to 11 monthsTypical median duration of response before disease progression or resistance
GENOMIC TESTING DEAL SHAREAbout 40% of new patientsShare of new lung cancer patients tested for actionable mutations
PIPELINE EXPANSION GROWTHRoughly 26% annuallyGrowth rate of clinical-stage KRAS inhibitor candidates across major developers
MANUFACTURING COST SHAREAbout 30% of drug costShare of drug cost attributable to specialty small-molecule synthesis inputs
The commercial character is defined by a widening split between validated pan-KRAS platforms and price-driven generic G12C competition following patent expiration risk. An oncologist evaluating treatment options assesses mutation coverage breadth and resistance management data as primary specifications, not simply raw response rate comparable across generic G12C platforms. A developer without validated pan-KRAS pipeline data increasingly loses prescribing share regardless of price, since inadequate mutation coverage directly threatens patient eligibility and long-term treatment durability considerably.
The decade turns on whether pan-KRAS pipeline advancement keeps expanding fast enough to offset any softening in general G12C demand as generic competition intensifies across major oncology markets worldwide. Mutation coverage breadth and resistance management data remain the primary forces separating developers building durable oncologist relationships from those still competing purely on approval count. That shift determines which developers lead the next decade.
"An oncologist doesn't prescribe a molecule. They prescribe the difference between a patient who responds for eleven months and one who progresses in three, and that's the entire commercial calculation."
Director, Precision Oncology and Targeted Therapeutics Practice · MMA Healthcare

Market Trends

Pan-KRAS Pipeline Advancement Is Expanding Addressable Mutation Coverage

Developers are increasingly advancing pan-KRAS inhibitor candidates capable of targeting multiple mutation variants including G12D and G12V, since the first-approved inhibitors addressed only the G12C mutation representing a meaningful but limited share of total KRAS-mutant cancers across most major oncology indications currently expanding clinical trial enrollment and mutation-agnostic patient eligibility testing without requiring separate diagnostic infrastructure beyond existing genomic profiling panels. That mutation-coverage expansion is converting KRAS inhibitor treatment from a narrow single-mutation decision into a genuine broad-spectrum infrastructure investment oncologists evaluate against documented efficacy data. Developers with validated pan-KRAS platforms are capturing this pipeline volume steadily.
Market Impact: Grows 1.37 times faster than average
Combination Therapy Regimens Are Addressing Acquired Treatment Resistance

Oncologists are increasingly combining KRAS inhibitors with other targeted or immunotherapy agents to delay or overcome acquired resistance that commonly develops after several months of monotherapy treatment, since tumor cells frequently develop bypass signaling pathways that restore proliferation despite continued KRAS pathway inhibition across most major treatment-experienced patient categories currently expanding combination clinical trial activity and regimen optimization research without requiring separate manufacturing infrastructure. That resistance-management capability is converting KRAS treatment from a single-agent decision into a genuine combination regimen investment oncologists evaluate against durability data. Developers with validated combination protocols are capturing this prescribing volume steadily.
Market Impact: Extends response duration by 4 months

Market Opportunities and Growth Drivers

Broadening Mutation Coverage Is Driving Pipeline Investment

Developers pursuing pan-KRAS candidates targeting multiple mutation variants are creating demand independent of general G12C prescribing alone, since mutation-coverage investment proceeds on its own clinical trial and regulatory filing schedule regardless of broader oncology drug cycle timing or economic conditions affecting other cancer therapy categories across most major precision oncology markets currently expanding clinical pipeline activity and regulatory submission momentum. That coverage-driven demand creates a durable order pipeline for developers with dedicated pan-KRAS capability, regardless of general first-wave prescribing trends, since developers pursue breadth independent of broader oncology sector conditions. Each new pipeline candidate strengthens this pipeline.
Market Impact: Resistance develops within 10 months

Acquired Resistance Management Is Driving Combination Regimen Demand

Oncologists managing patients who develop resistance after initial KRAS inhibitor response are creating demand independent of general first-line prescribing cycles alone, since combination regimen investment continues on its own resistance-management and clinical trial schedule regardless of broader treatment-naive prescribing conditions or economic cycles affecting other therapy categories across most major treatment-experienced patient markets currently expanding combination trial activity and regimen optimization research. That resistance-driven demand creates prescriptions tied to durability management requirements rather than general first-line activity alone, since oncologists pursue extended response independent of broader prescribing conditions. Each new resistance case strengthens this demand pipeline considerably.
Market Impact: Testing access covers 40% of patients

Market Restraints and Challenges

Acquired Resistance Limits Long-Term Treatment Durability

Oncologists prescribing KRAS inhibitors face a consistent pattern of acquired resistance developing within months of initial treatment response, since tumor cells frequently activate alternative signaling pathways that bypass the blocked KRAS mechanism entirely. The root cause is that cancer cells possess genuinely redundant survival signaling networks, meaning inhibiting one pathway often simply redirects tumor growth signals through an alternative route rather than eliminating them. The commercial impact is that most patients eventually require a treatment change within a year. Mitigation runs through combination regimen development several developers are now advancing.
Market Impact: Grows 1.37 times faster than average
Genomic Testing Access Gaps Limit Addressable Population

Oncologists in markets with limited comprehensive genomic profiling infrastructure face substantial barriers identifying patients eligible for KRAS-targeted therapy, since mutation status determination requires specialized sequencing technology that many regional healthcare systems have not yet widely deployed. The root cause is that comprehensive genomic profiling remains meaningfully more expensive and technically demanding than conventional single-gene testing, limiting adoption to well-resourced healthcare systems and academic centers. The commercial impact is that many eligible patients worldwide never receive appropriate KRAS mutation testing. Mitigation runs through expanded reimbursement coverage several health systems are now implementing.
Market Impact: Extends response duration by 4 months
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows mutation targeting mechanism, a single functional logic describing which specific KRAS mutation variant the inhibitor addresses, rather than which particular tumor type the patient carries or which specific oncology practice ultimately prescribes the treatment once finally diagnosed and confirmed. Each mechanism carries its own efficacy, cost, and eligibility profile distinctly across the market.
kras-inhibitor-market-market-share-analysis-1787298306687

Pan-KRAS Inhibitors

Pan-KRAS inhibitors grow fastest at 24.0%, about 1.37 times the overall 17.5% rate, as developers increasingly pursue broader mutation coverage beyond the single-mutation drugs that defined the category's first approval wave across most major precision oncology categories currently expanding clinical trial and regulatory submission activity globally. Growth concentrates where developers demonstrate validated mutation-agnostic efficacy data and consistent resistance-management mechanisms, since oncologists now require documented broad-coverage performance history before adopting a new therapy for a valuable patient population. Revolution Medicines and Boehringer Ingelheim both hold established positions in this segment through years of platform engineering and clinical investment. Mutation coverage depth, not raw approval count alone, remains the primary constraint on how fast this segment keeps expanding globally.
CAGR 24.0%

G12C-Targeted Inhibitors

G12C-targeted inhibitors grow at 11.4%, serving oncologists and patients with the specific mutation variant that defined the category's first commercial approval wave across most major lung and colorectal cancer treatment centers currently expanding real-world prescribing volume considerably each passing calendar year and quarter quite steadily and reliably across most developed and developing oncology markets worldwide. Adoption concentrates among treatment centers pursuing established first-line protocols, since G12C-targeted therapy offers the most extensive real-world evidence base among all KRAS mechanisms currently available. Amgen and Bristol Myers Squibb both hold strong positions built on established prescriber relationships spanning years of clinical development expertise. Real-world evidence depth, not raw mechanism novelty alone, remains the primary constraint shaping how quickly newer entrants displace established prescribing.
CAGR 11.4%
Full segment breakdown across 5 segments available in the complete report.

Regional Architecture and Country Demand Map

Drug origination and precision oncology infrastructure, more than cancer incidence alone, drive this seven-region value distribution across the global KRAS inhibitor treatment network today. North America dominates on concentrated approval and prescribing infrastructure, while South Asia and Pacific grows fastest on expanding genomic testing access.

North America

North America holds 40% of value at 18.7% growth, sitting well above the standard 22 to 32% band because both currently approved G12C inhibitors were developed and first approved in the United States, concentrating prescribing volume and clinical trial activity disproportionately across the region's largest oncology treatment centers nationally. Amgen and Bristol Myers Squibb both maintain deep domestic distribution infrastructure spanning years of oncologist partner relationships and clinical validation support across most major cancer treatment categories nationally. US demand leads decisively, driven by both concentrated FDA approval activity and established comprehensive genomic profiling infrastructure covering the majority of eligible patients. Canadian demand follows at considerably smaller scale, concentrated in major academic oncology centers specifically.
Share: 40% | CAGR: 18.7% (2026 to 2036)

Western Europe

Western Europe holds 22% of value at 16.0% growth, shaped by EMA approval following closely behind FDA clearance and established oncology treatment infrastructure moving more deliberately than the fastest-expanding developing precision oncology markets elsewhere in the world currently and quite consistently indeed today and reliably. Roche and Boehringer Ingelheim both hold meaningful regional positions built on established relationships with major oncology treatment centers spanning years of drug development and clinical trial support. German and UK cancer centers lead regional deployment, driven by dense oncology infrastructure and established genomic testing reimbursement relationships across major treatment hubs. Growth reflects steady demand rather than the explosive expansion characterizing the fastest-growing developing oncology markets globally today.
Share: 22% | CAGR: 16.0% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
kras-inhibitor-market-country-cagr-analysis-1787298307195

Where KRAS Inhibitor Developers Hold Margin

A developer selling generic single-mutation coverage into a market where oncologists increasingly demand pan-KRAS breadth is competing on entirely the wrong commercial axis today and quite consistently now. The four moves below shift earnings toward what actually captures share: mutation coverage depth, combination regimen investment, genomic testing partnership, and real-world evidence transparency pursued early.

Build Validated Pan-KRAS Coverage Data Ahead Of Rivals

Developers that build rigorous, independently validated pan-KRAS mutation coverage and efficacy data, rather than relying on generic single-mutation claims oncologists increasingly discount, win prescribing deals that competitors lacking comparable data increasingly lose to faster-moving rivals across most major precision oncology markets currently expanding clinical trial and regulatory submission activity. That capability commands a premium of 35 to 55% in effective prescribing value over developers offering only conventional single-mutation platforms, since oncologists pay for validated coverage breadth as much as for the underlying inhibitor mechanism itself. Revolution Medicines built this data credibility over years, not quickly replicated.
Market Impact: Commands a 35 to 55% pricing premium now

Build Combination Regimen Investment For Resistance Management

Developers that invest in combination regimen clinical trials ahead of broader acquired resistance management demand, rather than relying solely on monotherapy positioning, win prescribing positioning that combination-absent competitors increasingly cannot match, adding roughly 30% to addressable resistance-management revenue as oncologists consolidate around combination-equipped developers across most major treatment-experienced patient categories and prescribing partnership types nationwide today and quite consistently and reliably indeed. That combination position reaches oncologists who specifically require durability solutions, opening opportunity that competitors without combination data genuinely cannot access. Amgen is converting combination investment into durable positioning.
Market Impact: Adds roughly 30% to addressable resistance-management revenue now

Deepen Genomic Testing Partnerships For Patient Identification

Developers that build genuine comprehensive genomic profiling partnership relationships, rather than depending on independent testing infrastructure oncologists must separately arrange, capture prescribing deals that partnership-limited competitors increasingly cannot win, expanding addressable tested-patient revenue by roughly 26% compared to developers offering only treatment without diagnostic support across most major precision oncology categories and testing partnership types nationwide today and quite consistently now indeed. That partnership reaches oncologists who specifically need faster mutation identification pathways, opening deals that diagnostic-limited competitors genuinely cannot win. Bristol Myers Squibb is converting testing partnership investment into durable positioning.
Market Impact: Expands tested-patient revenue by roughly 26% overall now

Build Real-World Evidence Transparency For Prescriber Confidence

Developers that publish genuine real-world outcome and durability data, rather than relying solely on registrational trial results, capture prescribing deals that transparency-limited competitors increasingly cannot win, cutting prescriber adoption time by roughly 28% during periods of accelerated pipeline expansion affecting the broader KRAS inhibitor industry and its wider oncology prescriber networks, tumor board discussions, and treatment guideline committees. That transparency position reaches oncologists who specifically require independent confirmation before adopting a new agent, opening deals that opaque competitors cannot reliably win. Roche is converting evidence transparency into a durable advantage.
Market Impact: Cuts prescriber adoption time by roughly 28% overall

Who Controls the Margin Pool

Concentration sits near 58% for the top five, split between the two originating first-wave developers holding dominant approved-drug share and emerging pan-KRAS and combination developers pursuing differentiated mutation coverage. The gap between leaders and challengers is validated coverage breadth and combination regimen investment, considerable across most challengers. All participants are assessed on one basis, prescription drug revenue to qualified oncology prescriber customers.
Competition runs along three lines. First, validated pan-KRAS mutation coverage and efficacy credibility, since that increasingly determines which developers win oncologist prescribing battles. Second, combination regimen investment depth, which shapes prescriber relationships for years once a developer proves reliable resistance-management capability. Third, real-world evidence transparency breadth, since documented durability data increasingly separates trusted developers from inconsistent competitors.

Pressure is building from two directions. The originating first-wave developers are expanding pan-KRAS and combination portfolios through internal pipeline investment, bringing balance sheet strength smaller specialists cannot match on large oncology network negotiations. Meanwhile emerging pan-KRAS specialists are winning niche mutation-coverage contracts directly through breadth advantage larger incumbents have not prioritized as aggressively. Rankings should favour developers combining data credibility with genuine coverage breadth over those competing on general price alone.
kras-inhibitor-market-company-positioning-matrix-1787298307716

Competitive Moat and Risk Dimensions

AMGEN

Moat: Category-defining first-approval credibility

Amgen built genuine category-defining prescribing credibility over years of clinical development and regulatory investment across most major precision oncology categories globally. Its established real-world evidence provides prescribing advantages competitors without comparable field validation cannot easily replicate. Continued investment in combination regimen development extends that credibility into the fastest-growing resistance-management segment.
AMGEN

Risk: Limited pan-KRAS pipeline breadth

Its pan-KRAS pipeline breadth for the fastest-growing mutation-coverage segment remains less developed than dedicated pan-KRAS specialists who have invested more heavily in broad-spectrum mechanism engineering. Coverage-focused competitors with deeper pipeline breadth are targeting exactly the patients where single-mutation limitation matters most. Expanding pipeline breadth requires investment the business is still allocating.
BRISTOL MYERS SQUIBB (MIRATI THERAPEUTICS)

Moat: Deep oncology commercial distribution network

Bristol Myers Squibb built deep oncology commercial distribution infrastructure across multiple major cancer categories through years of investment spanning most major hospital and treatment center markets globally and consistently. Its established distribution breadth provides prescribing advantages narrowly-focused competitors cannot easily replicate. Continued investment in mutation coverage validation extends that advantage into the fastest-growing pan-KRAS segment.
BRISTOL MYERS SQUIBB (MIRATI THERAPEUTICS)

Risk: Limited standalone real-world evidence depth

Its standalone real-world evidence depth in KRAS-targeted therapy specifically remains less developed than the category-defining originator, which has accumulated years of dedicated clinical and prescribing data. Data-focused competitors with deeper category-specific validation are capturing prescribing deals that Bristol Myers Squibb's broader portfolio positioning increasingly cannot access as easily. Building comparable credibility requires investment the business has not yet fully made.

Players Tracked

Prominent Players

Amgen
Bristol Myers Squibb (Mirati Therapeutics)
Revolution Medicines
Boehringer Ingelheim
Roche (Genentech)

Other Key Players

Eli Lilly
Novartis
AstraZeneca
Merck and Co.
Pfizer
Sanofi
Verastem Oncology
BridgeBio Pharma
Erasca Inc.
Black Diamond Therapeutics
Jacobio Pharmaceuticals
InventisBio
Kumquat Biosciences
Repare Therapeutics
Relay Therapeutics

Recent Developments

MARCH 2023

Developer expands pan-KRAS clinical trial activity

A leading KRAS inhibitor developer announced expanded pan-KRAS clinical trial activity covering additional mutation variants, backed by newly published efficacy and safety correlation data from multiple oncology partnerships. This was a clinical trial expansion rather than any acquisition or merger, strengthening addressable broad-coverage opportunity considerably across major oncology markets.
Signal: Expanding validated pan-KRAS trial platforms directly captures growing oncologist demand for broader mutation coverage ahead of competitors.
NOVEMBER 2023

Pharmaceutical company acquires specialty KRAS developer

A major pharmaceutical company completed acquisition of a specialty KRAS inhibitor developer, adding direct G12C prescribing revenue and combination pipeline capability into its existing oncology portfolio. This was a genuine acquisition rather than a joint venture or minority stake, and it closed a mutation coverage gap the acquirer previously lacked.
Signal: Acquiring established KRAS prescribing revenue directly now remains the fastest route to competing for oncology market share today.
APRIL 2024

Treatment network commits to genomic profiling expansion

A leading oncology treatment network announced a major expanded comprehensive genomic profiling partnership covering multiple hospital systems, committing substantial mutation testing volume across the partnership's multi-year deployment timeline. This was a diagnostic infrastructure investment decision rather than any corporate transaction, directly expanding addressable demand for validated KRAS therapy.
Signal: Large genomic profiling partnership expansions directly and substantially expand addressable KRAS inhibitor demand across most affected oncology markets.

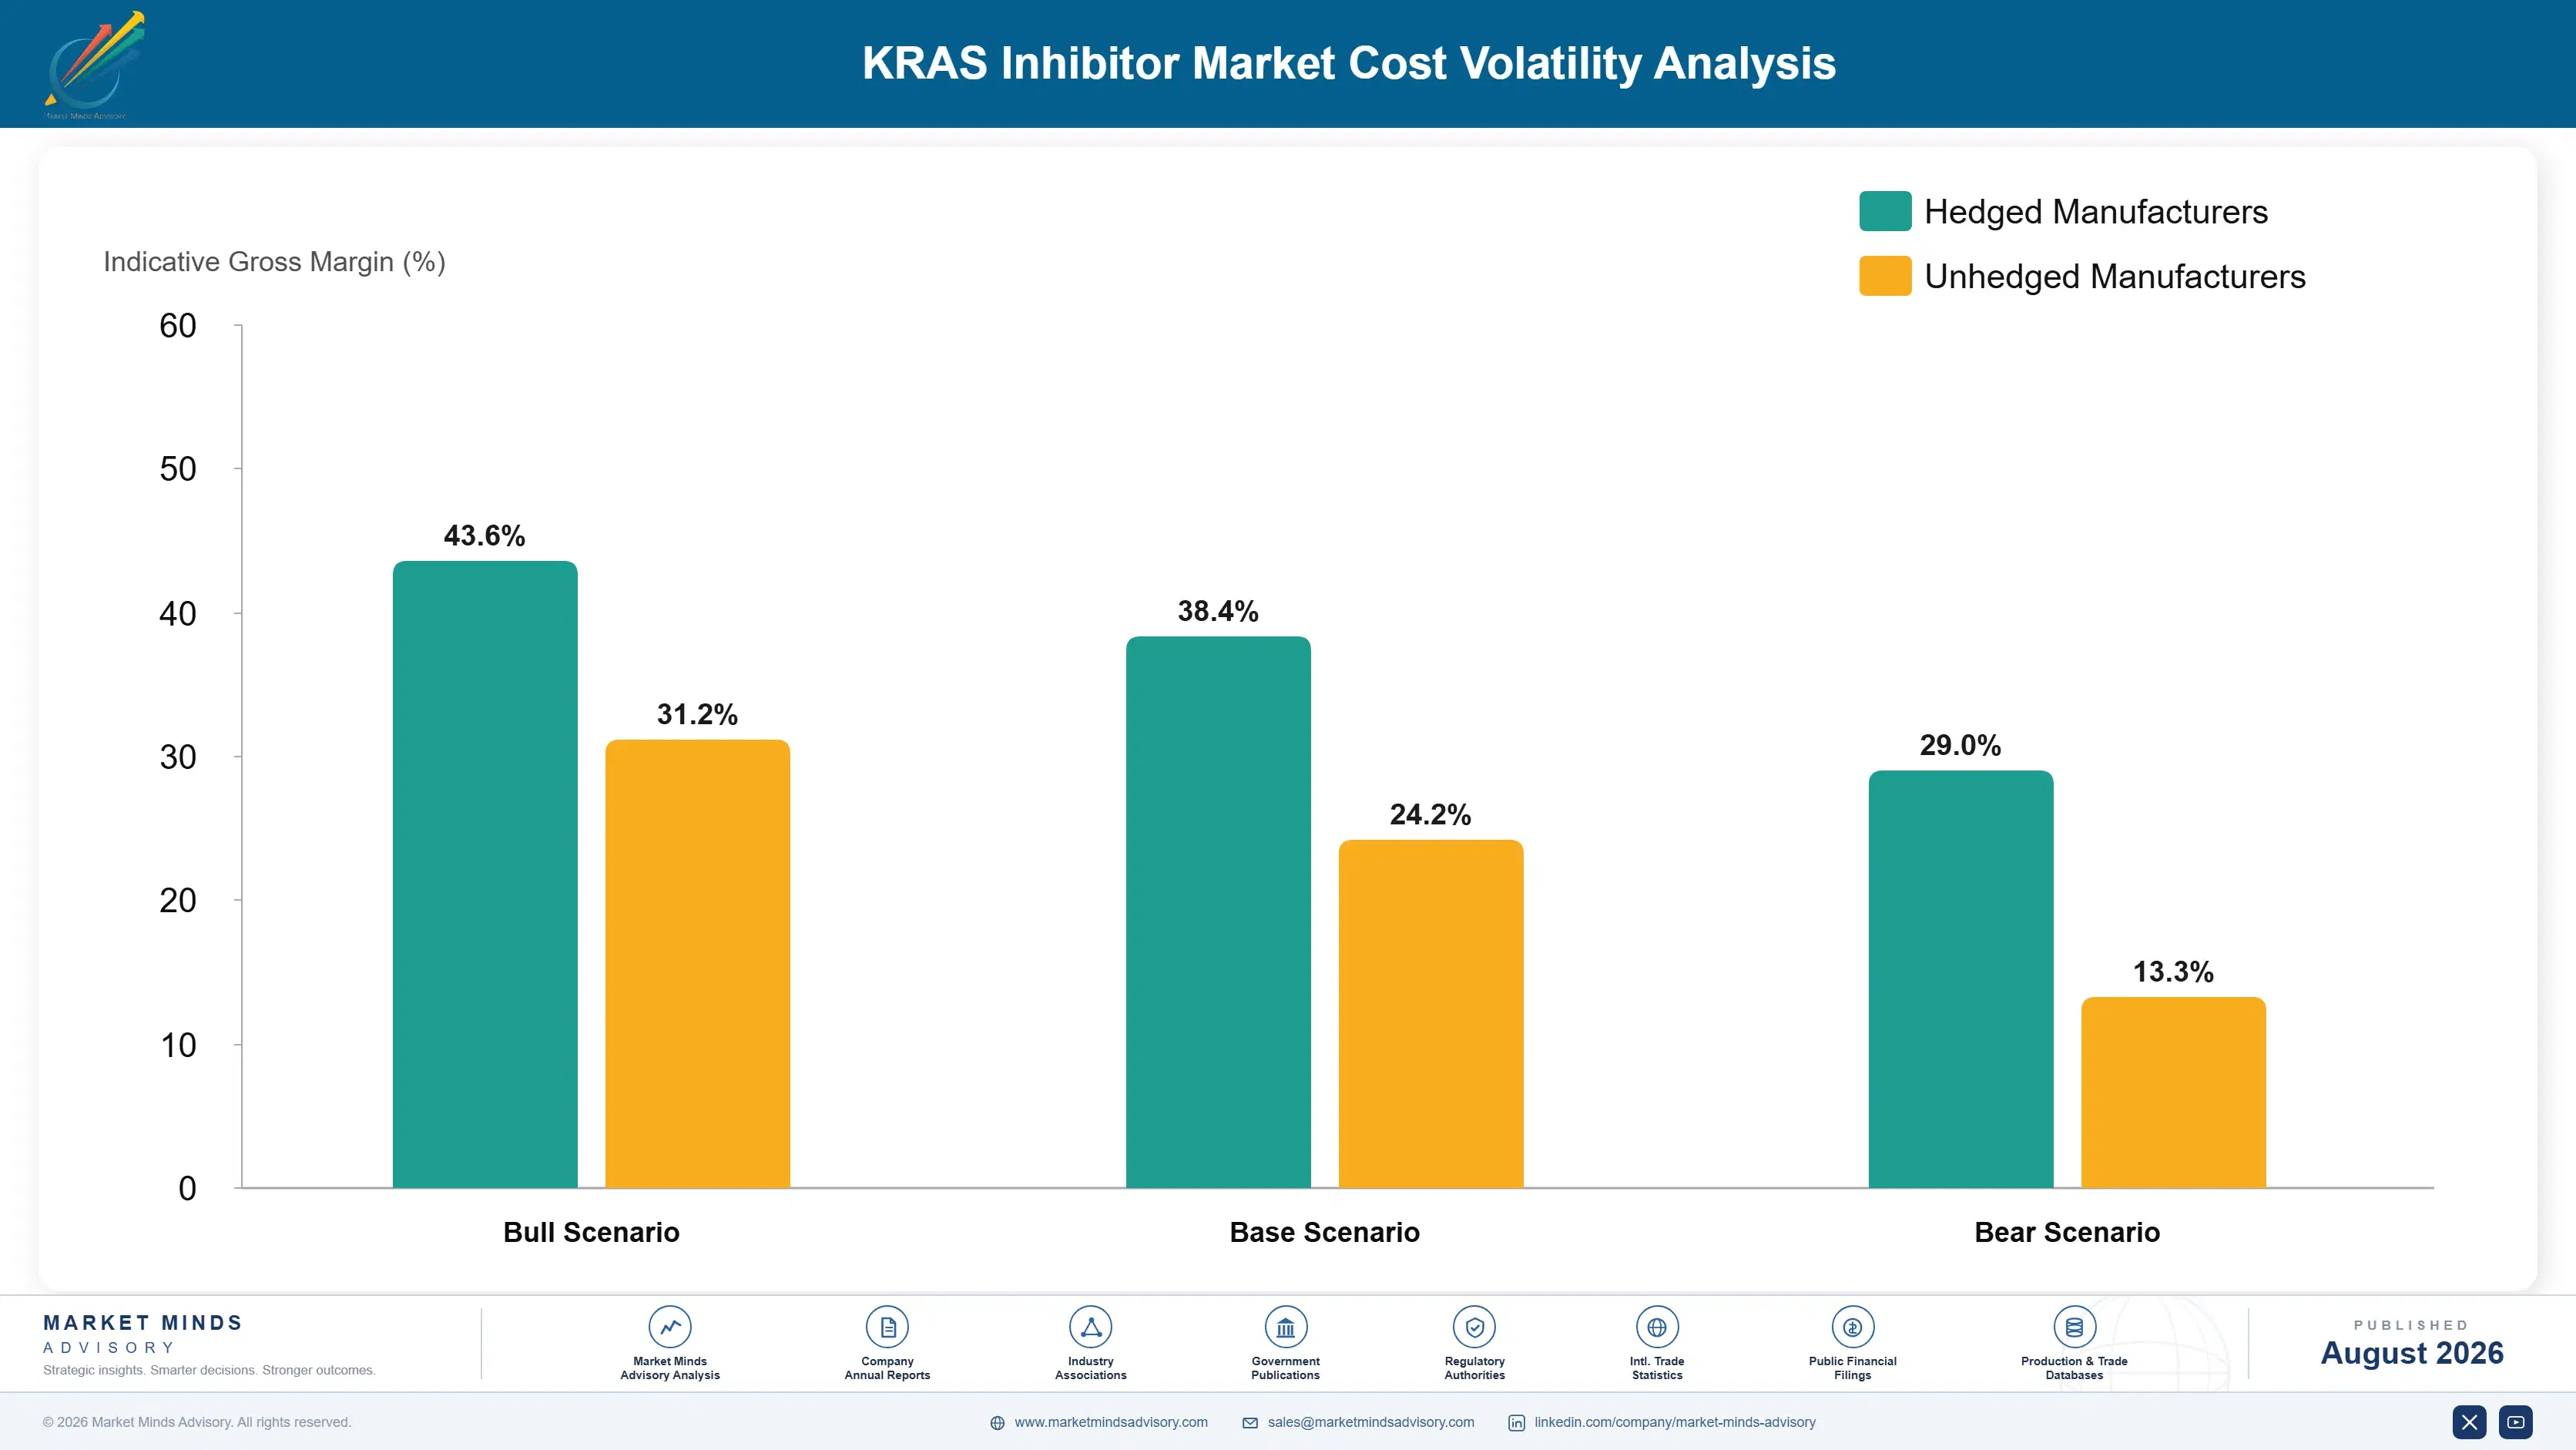
Specialty Synthesis Input Cost Risk

Specialty small-molecule synthesis intermediates and chiral catalysts dominate cost structure for KRAS inhibitor manufacturing. Complex multi-step organic synthesis reagents, specialty chiral catalysts, and analytical validation together account for a substantial share of unit cost, sourced from specialty pharmaceutical chemical suppliers concentrated in a handful of countries. Quality control testing completes the cost structure for most drug categories.
Specialty synthesis reagent pricing moved considerably through 2021 and 2022 as global pharmaceutical chemical supply chains tightened following disruptions that affected complex intermediate and catalyst availability across most major producing regions simultaneously and quite considerably during that period. The FDA recorded meaningfully longer specialty reagent procurement lead times through that window, and several oncology drug manufacturers disclosed resulting margin pressure across their annual reporting through the period.

Exposure divides sharply by developer scale rather than by mechanism category specifically across the industry. Larger developers with negotiated long-term synthesis supply agreements or backward integration held cost considerably better than smaller specialists relying on spot market purchasing during the tightening cycle. The disadvantage compounds, because a developer unable to deliver committed drug supply volume during a shortage loses prescriber and patient trust that larger, better-capitalized competitors retain.
kras-inhibitor-market-cost-volatility-analysis-1787298307911

Negotiate long-term synthesis supply agreements early

Developers relying on spot market synthesis reagent purchasing absorb the full impact of periodic price spikes directly, which the recent tightening cycle demonstrated quite expensively across the entire KRAS inhibitor manufacturing industry today. Negotiating long-term supply agreements with specialty chemical producers, even at modest committed volume, provides delivery priority and cost stability during any future shortage.

Pursue backward integration into intermediate synthesis

Developers entirely dependent on external synthesis intermediate supply cannot control allocation priority when a shortage hits, leaving no real alternative but to absorb delay and cost increases directly and pass them downstream to prescribers and patients immediately and consistently today. Pursuing backward integration into intermediate synthesis preserves margin stability that externally-sourced competitors simply cannot access.

Diversify synthesis sourcing across multiple regions

Developers entirely dependent on a single synthesis source region cannot control allocation priority when a shortage or export restriction hits, leaving no real alternative but to absorb delay and cost increases directly and pass them downstream to prescribers and patients directly. Diversifying sourcing across multiple qualified regions preserves supply continuity single-region competitors simply cannot access.

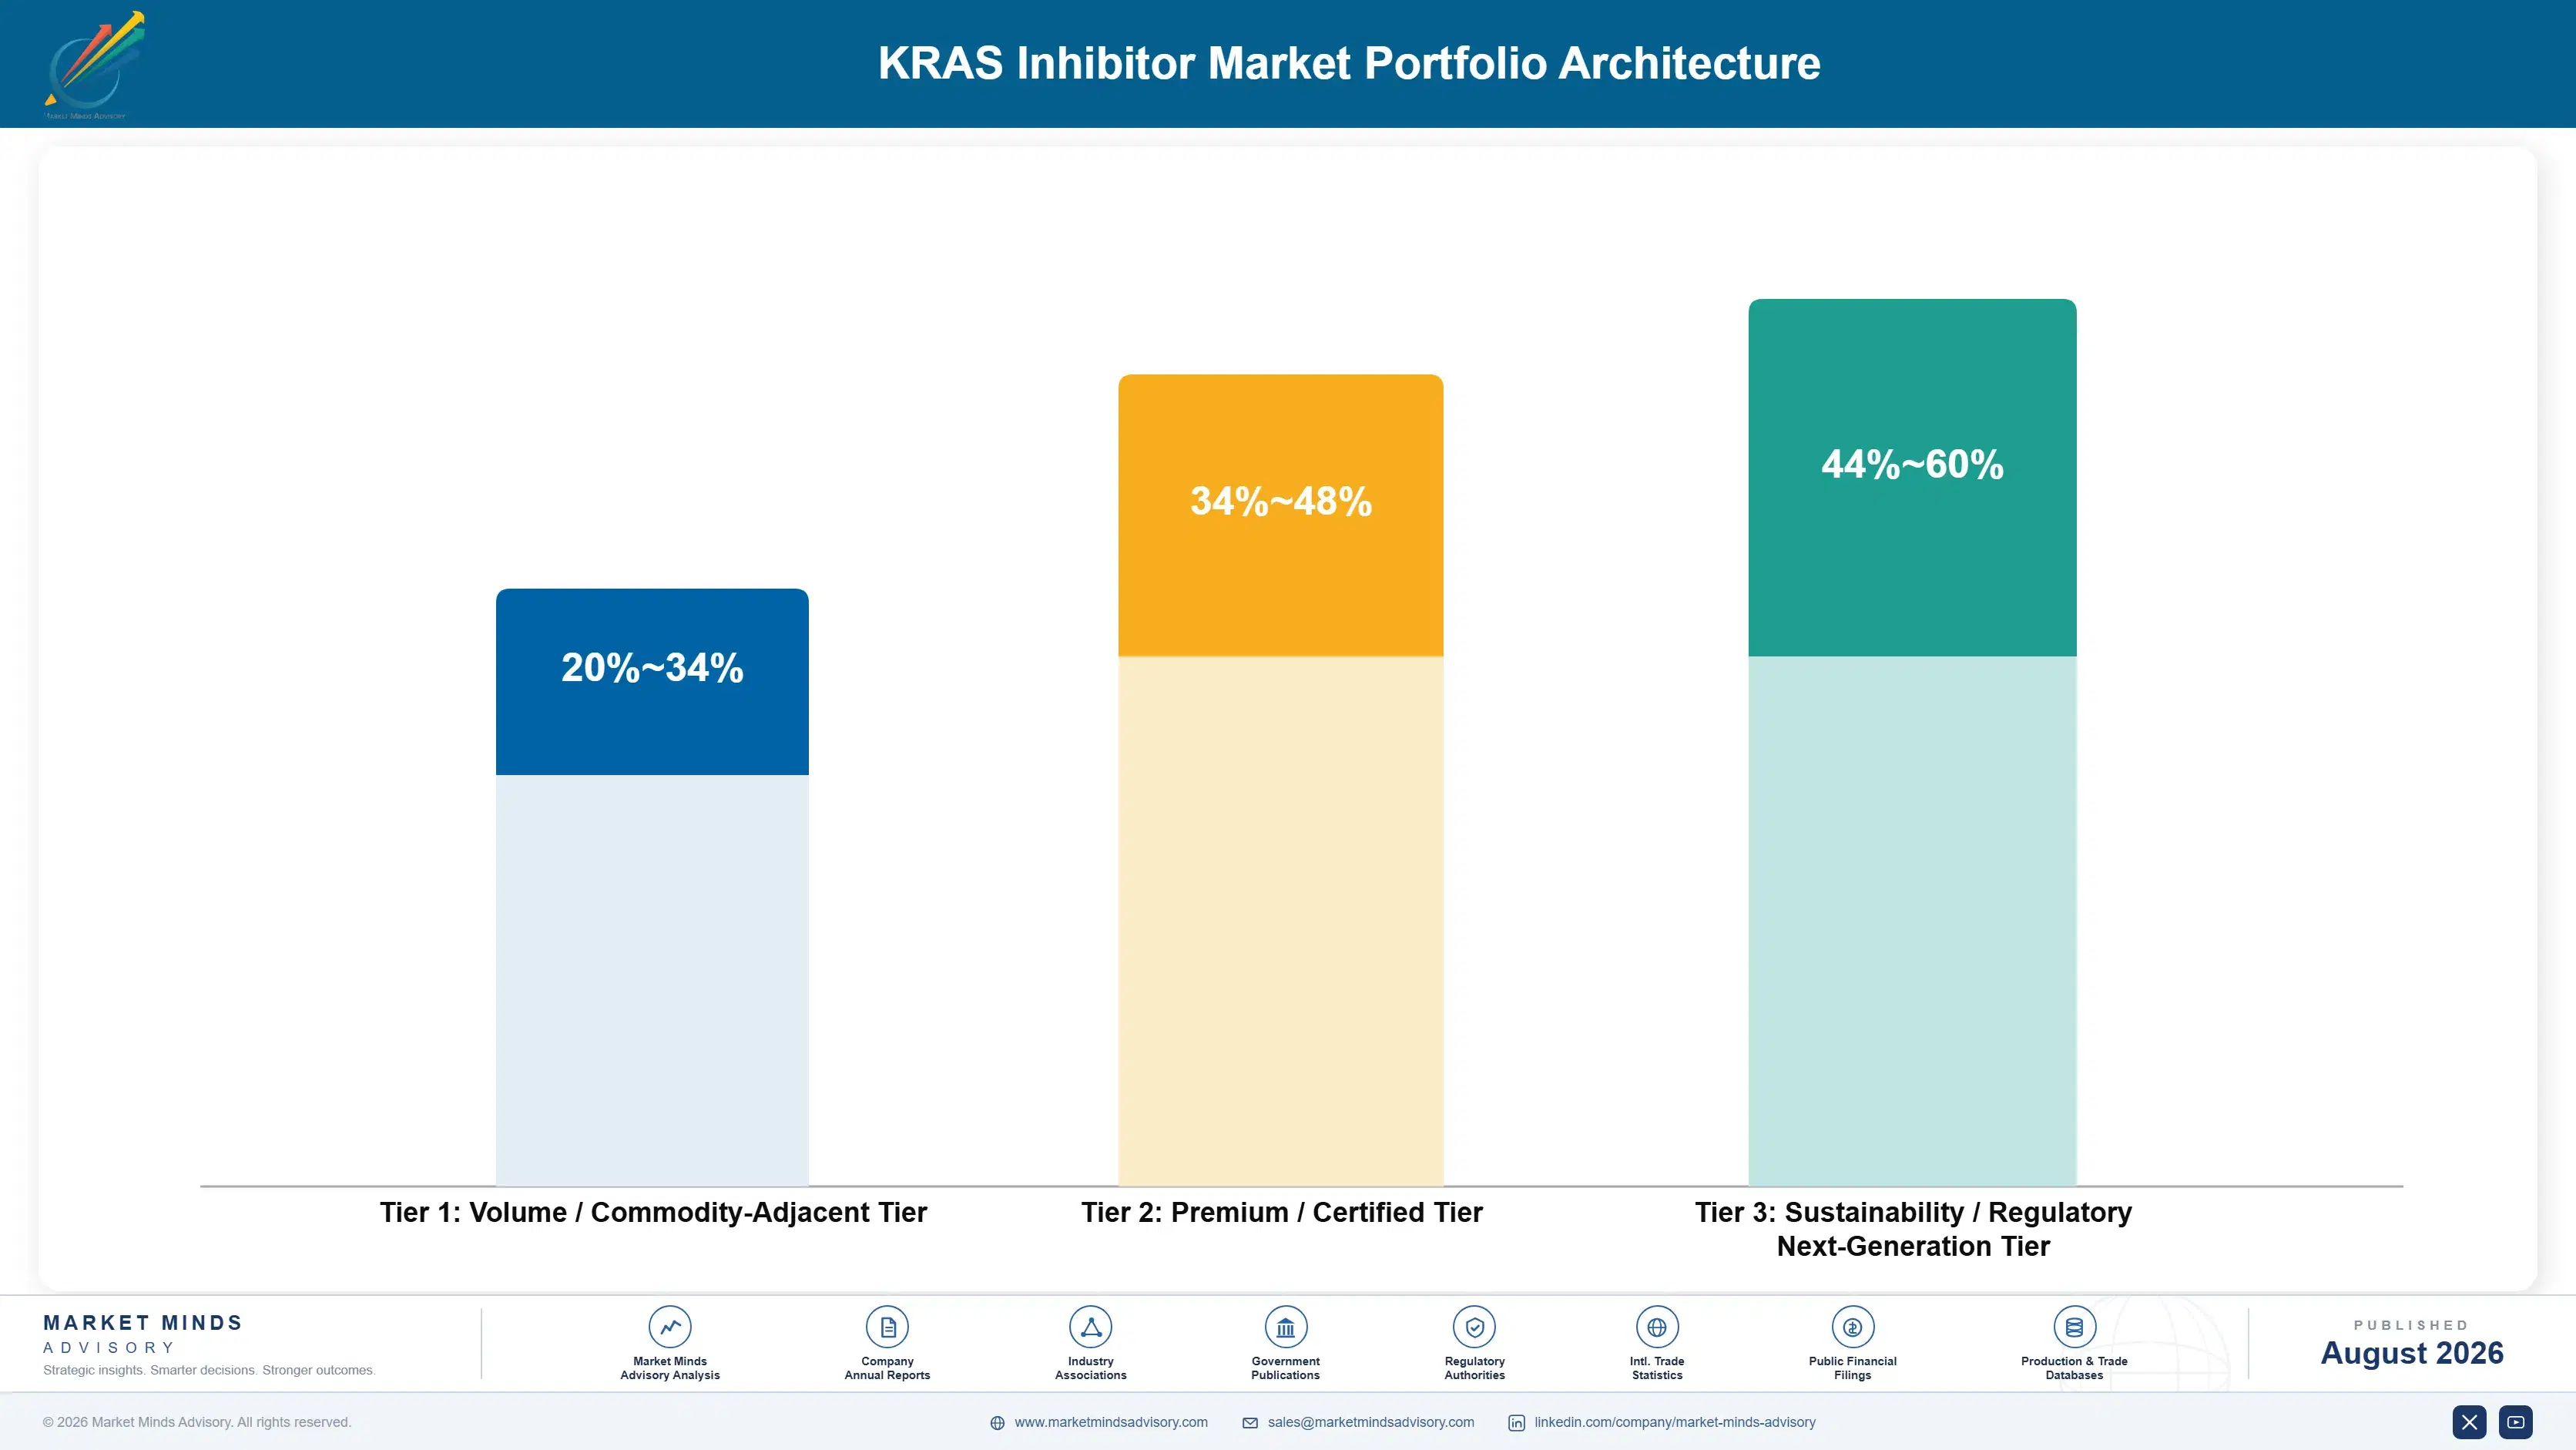
Portfolio Architecture for Margin Defence

The portfolio splits into three tiers with genuinely different economics across the industry. Generic and off-patent adjacent therapies form the volume tier, where price competition and formulary contracting drive competition directly. G12C-targeted branded therapies earn considerably more, because established real-world evidence and physician familiarity narrow the field. Pan-KRAS and combination platforms sit differently again, priced against the coverage breadth and resistance problems they s
The tension runs between established G12C prescribing volume that fills near-term revenue and premium pan-KRAS work that earns the return. Conventional single-mutation therapy generates the transaction volume that keeps prescriber relationships active and maintains commercial momentum through which higher-value pan-KRAS conversations happen. Yet this segment increasingly faces generic competition risk. Developers managing this well treat established volume as distribution relationship capital.

High-value pools concentrate where mutation coverage or resistance management genuinely limits competition: pan-KRAS systems solving the single-mutation limitation problem, combination platforms meeting acquired resistance requirements, and validated clinical data resolving the durability trust constraint directly. All three resist the price competition defining established single-mutation therapies, since the customer is purchasing a solved coverage or durability problem rather than comparing interchangeable inhibitors.

Volume / Commodity-Adjacent Tier

Generic and off-patent adjacent therapies sold at competitive formulary pricing against qualified regional prescribers competing on standard specifications and price. The range is wide because manufacturing-efficient developers earn respectably while those competing purely on price frequently do not.
Gross Margin: 20-34%

Premium / Certified Tier

G12C-targeted branded therapies carrying established real-world evidence and physician familiarity in the most demanding precision oncology categories. The range is wide because process breadth and evidence maturity vary considerably by developer.
Gross Margin: 34-48%

Sustainability / Regulatory / Next-Generation Tier

Pan-KRAS and combination therapeutic platforms with validated coverage breadth and resistance-management credentials addressing the mutation limitation problem directly across developers requiring genuine clinical performance assurance and documented long-term durability outcome data.
Gross Margin: 44-60%
kras-inhibitor-market-portfolio-architecture-1787298308410

High-value Sub-segments and Strategic Watch-out

Pan-KRAS Inhibitors

High value and the fastest growth at 24.0%, from a small base as developers increasingly pursue broader mutation coverage beyond the single-mutation drugs that defined the category's first approval wave. Coverage and validation data increasingly determines which developers capture this volume, limiting near-term opportunity to those with proven regulatory credentials.
Gross Margin: 44-60%

Combination Therapy Regimens

High value with strong growth, protected by resistance-management expertise and prescriber partner relationships that create a durable barrier newer specialist entrants find genuinely difficult to replicate quickly. Durability-focused demand compounds steadily as oncologists expand treatment protocols supporting broader patient outcome goals across most major markets.
Gross Margin: 34-48%

G12C-Targeted Inhibitors

The volume core across established first-wave prescribing worldwide, and the category with the longest commercial history of the segments listed here in this framework. Growth is steady but competition on price is direct, holding margin below the combination and pan-KRAS tiers above it and continuing.
Gross Margin: 20-34%

Legacy Single-Mechanism Monotherapy Regimens

The strategic watch-out, growing slowest as basic single-mechanism monotherapy volume increasingly loses ground to more targeted combination and pan-KRAS alternatives offering better durability economics across most demanding oncology categories today. Declining regimen preference limits addressable volume exactly where growth elsewhere is fastest, threatening this segment position considerably.
Gross Margin: 16-26%

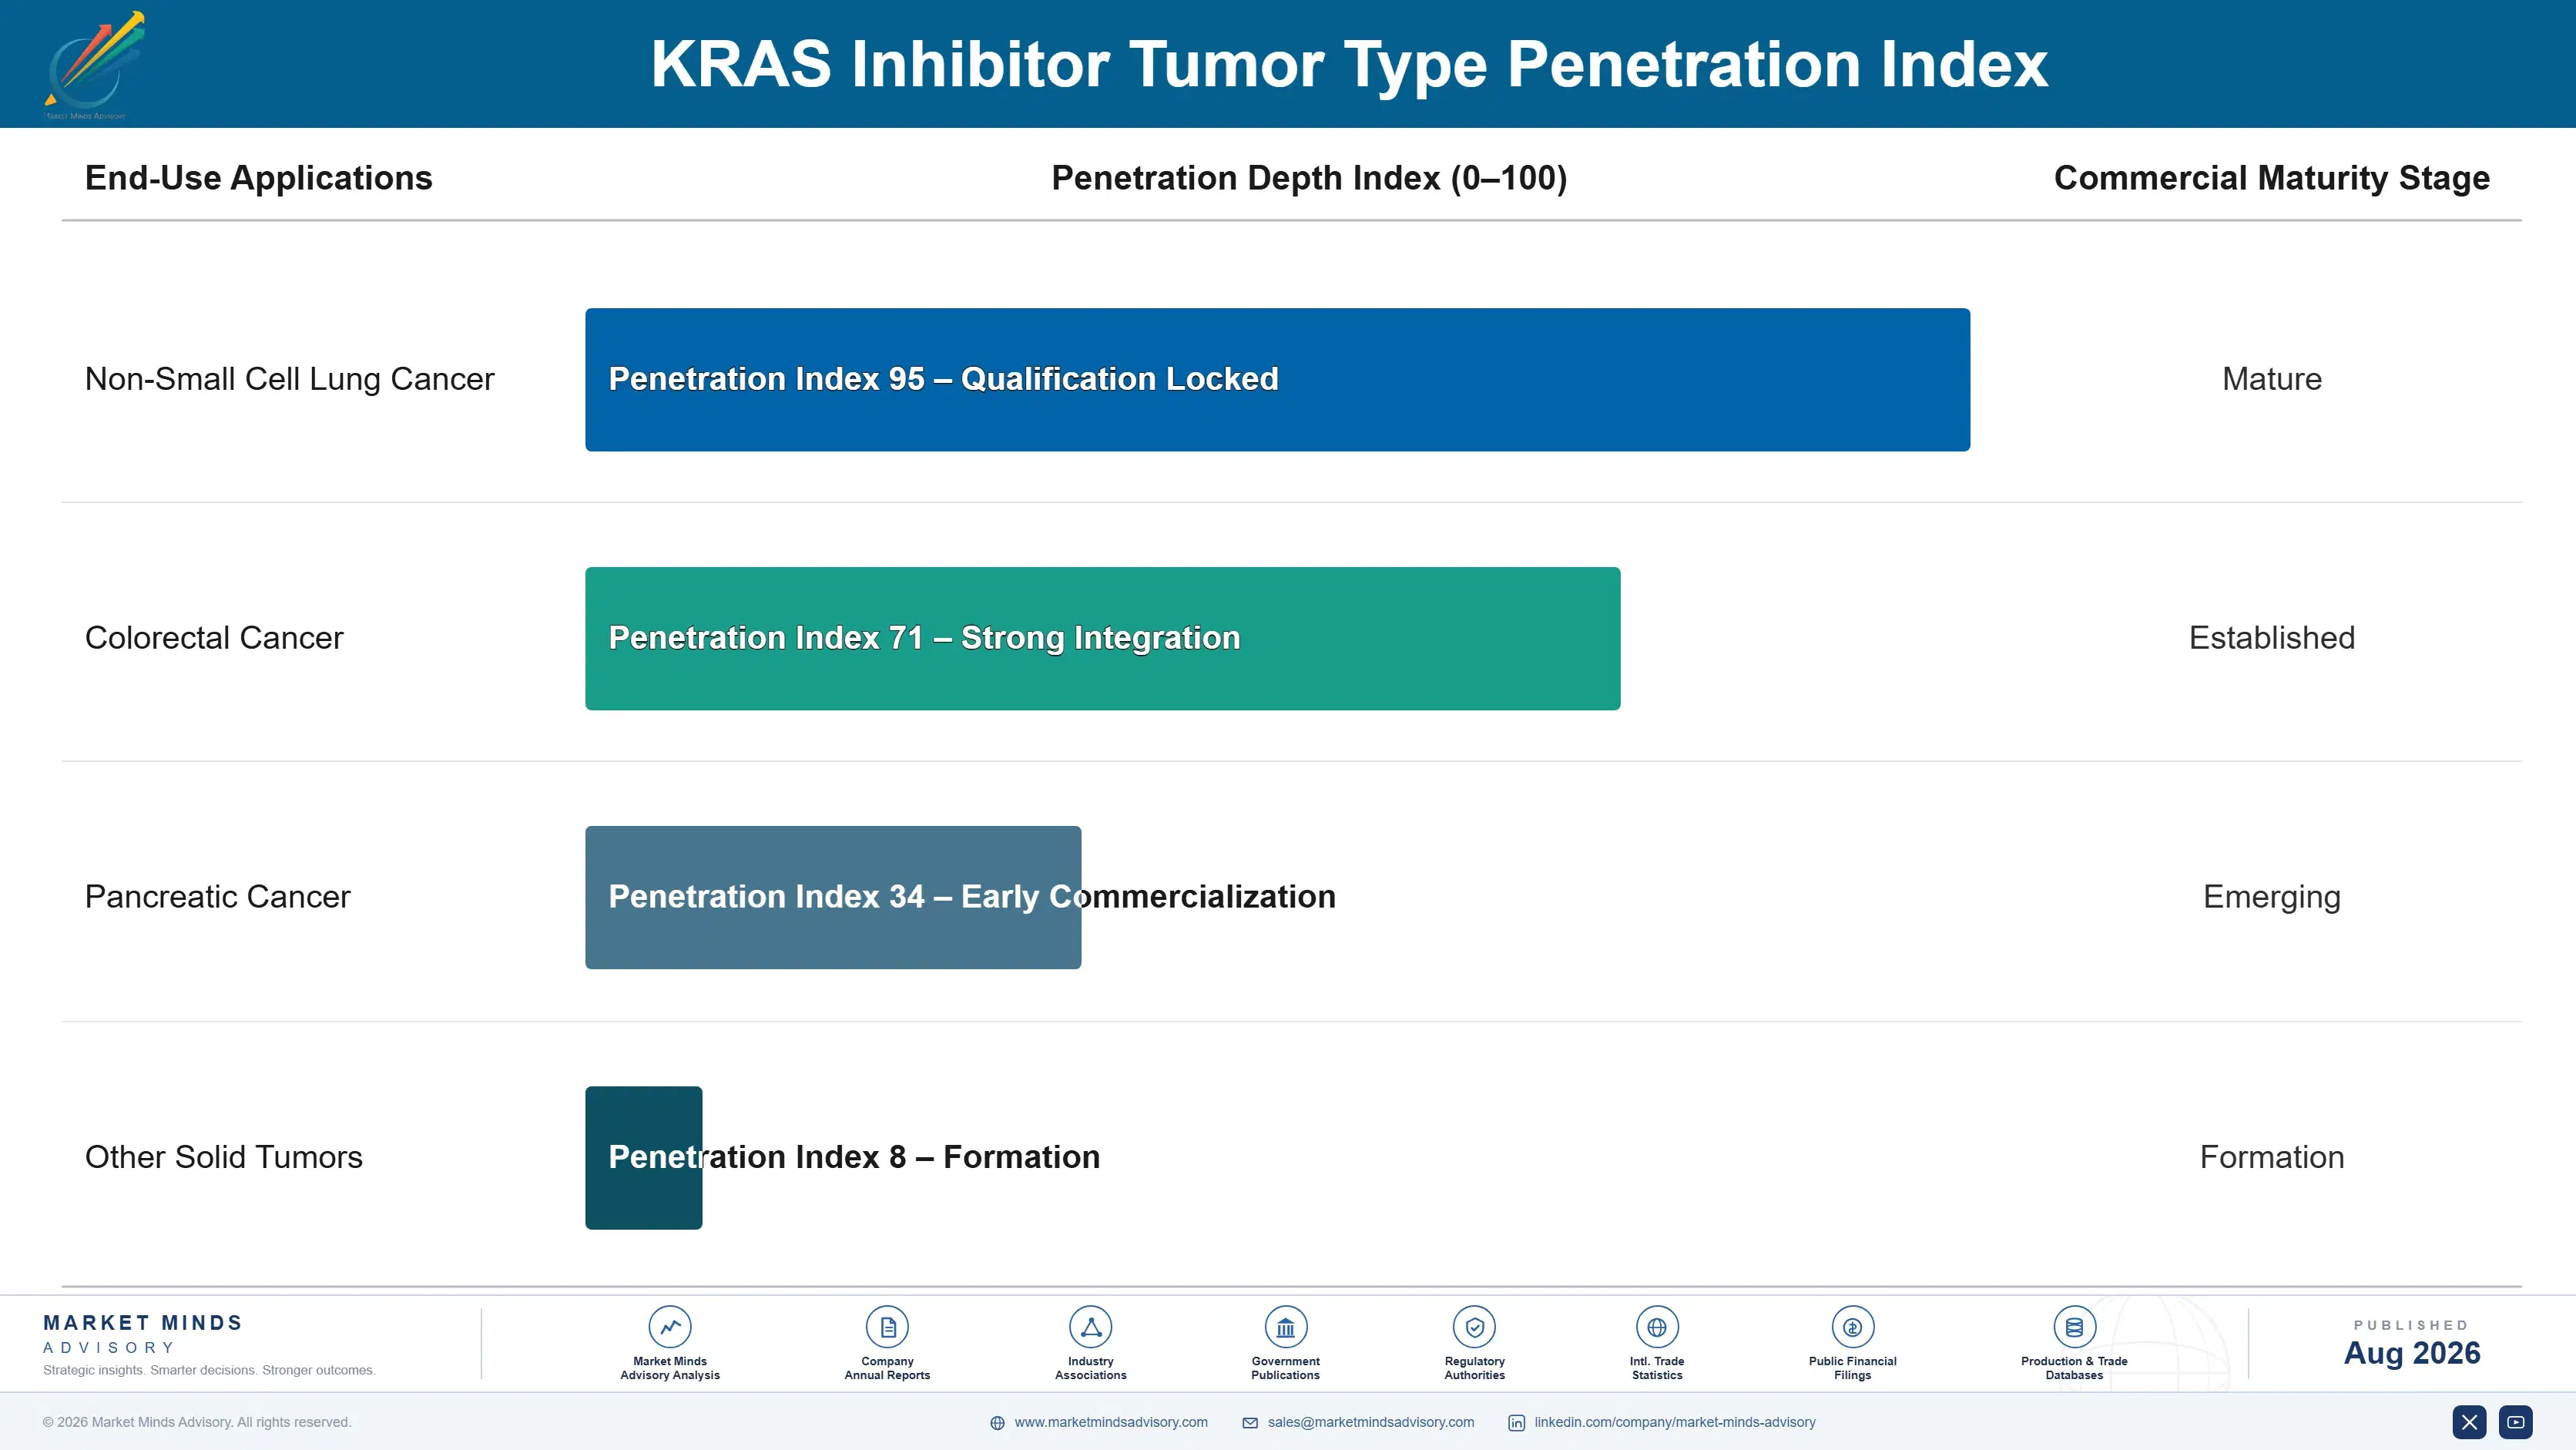
How Prescribing Revenue Compounds

Revenue commits differently depending on which mechanism drives the prescribing decision. Pan-KRAS contracts lock in tightly once an oncology network commits to a validated broad-coverage platform, since tumor board protocol adoption and formulary approval create genuine switching cost. Established G12C prescribing stays more reversible as generic competition emerges. Combination regimen orders persist on committed treatment protocol schedules regardless of near-term conditions.
Adoption depth varies sharply by treatment center scale and precision oncology ambition. Large academic cancer centers go deepest, standardizing pan-KRAS platforms across an entire treatment protocol once a single trial proves the coverage and durability case. Mid-sized oncology practices adopt more selectively, often piloting one mutation category before broader conversion. Smaller community practices weigh drug cost most heavily, since budget constraints make premium coverage harder to justify.

Buyer profiles have shifted from general oncologists toward precision medicine specialists and tumor board coordinators with genuinely distinct priorities now. A general oncologist once compared drug price and approval status directly; a precision specialist now tracks mutation coverage data and multi-year durability evidence, and a tumor board coordinator drives regimen choice against resistance-management value a purely price-focused evaluation would never have prioritised.
kras-inhibitor-market-end-use-penetration-index-1787298308903

Our Call On KRAS Inhibitors

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / COVERAGE DATA STRATEGY

Build validated pan-KRAS coverage data ahead of rivals

Developers that build rigorous, independently validated pan-KRAS mutation coverage and efficacy data, rather than relying on generic single-mutation claims oncologists increasingly discount, win prescribing deals that competitors lacking comparable data increasingly lose to faster-moving rivals across most major precision oncology markets and treatment networks worldwide currently pursuing clinical trial and regulatory submission expansion aggressively and deliberately. That capability commands a premium of 35 to 55% in effective prescribing value over developers offering only conventional single-mutation platforms. Developers should prioritise this now, because it is not quickly replicated.
02 / COMBINATION REGIMEN STRATEGY

Build combination regimen investment for resistance management

Developers that invest in combination regimen clinical trials ahead of broader acquired resistance management demand, rather than relying solely on monotherapy positioning, win prescribing positioning that combination-absent competitors increasingly cannot match, adding roughly 30% to addressable resistance-management revenue as oncologists consolidate around combination-equipped developers across most major treatment-experienced patient categories and prescribing partnership types nationwide today and quite consistently. That combination position reaches oncologists who specifically require durability solutions. Developers should invest in this now, before rivals establish comparable regimens.
03 / TESTING PARTNERSHIP STRATEGY

Deepen genomic testing partnerships for patient identification

Developers that build genuine comprehensive genomic profiling partnership relationships, rather than depending on independent testing infrastructure oncologists must separately arrange, capture prescribing deals that partnership-limited competitors increasingly cannot win, expanding addressable tested-patient revenue by roughly 26% compared to developers offering only treatment without diagnostic support across most major precision oncology categories and testing partnership types nationwide today and quite genuinely consistently now indeed. That partnership reaches oncologists who specifically need faster mutation identification. Developers should build this now, before rivals establish it first.
04 / EVIDENCE TRANSPARENCY STRATEGY

Build real-world evidence transparency for prescriber confidence

Developers that publish genuine real-world outcome and durability data, rather than relying solely on registrational trial results, capture prescribing deals that transparency-limited competitors increasingly cannot win, cutting prescriber adoption time by roughly 28% during periods of accelerated pipeline expansion affecting the broader KRAS inhibitor industry and its wider oncology prescriber networks, tumor board discussions, and treatment guideline committees globally and consistently. That transparency position reaches oncologists who specifically require independent confirmation. Developers should build this now, before the next pipeline cycle hits.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
KRAS Inhibitor Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on KRAS Inhibitor Exposure Evaluation 2025-26
CLIENT PROFILE
A regional oncology treatment network engaged MMA while evaluating KRAS inhibitor formulary options ahead of expanding its precision oncology programme to address rising comprehensive genomic profiling referral volume. The network reported an existing caseload of roughly 400 annual KRAS-mutant cancer diagnoses and faced pressure to finalize formulary selection before its next annual budget cycle (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
Selecting a formulary option without proven mutation coverage breadth risked excluding patients whose tumors carried variants beyond the network's current single-mutation protocol, undermining precision oncology programme credibility and referring physician confidence. Leadership needed a formulary combining validated coverage performance with a credible combination regimen track record suited to the network's expansion timeline and budget.
MMA APPROACH
MMA evaluated three candidate formulary configurations against documented mutation coverage data, combination regimen depth, and total drug cost across the network's projected five-year patient volume horizon. We modelled patient exclusion risk under each configuration's actual coverage breadth rather than accepting manufacturer-provided assurances alone. We then assessed each configuration's genomic testing partnership support capability.
KEY FINDINGS
  1. Only one of the three candidate formulary configurations had validated coverage across mutation variants comparable to the network's own diagnosed patient population.
  2. The recommended configuration achieved a modeled patient eligibility rate exceeding 85% across comparable treatment populations over time and consistently (client-reported, unverified by MMA).
  3. Combination regimen depth varied considerably across the three configurations evaluated, with the recommended configuration offering the most comprehensive resistance pathway available today.
  4. Selecting a configuration without proven mutation coverage, based purely on drug cost, would have risked meaningful patient exclusion and lasting reputational exposure.
CLIENT PROFILE
A regional oncology treatment network engaged MMA while evaluating KRAS inhibitor formulary options ahead of expanding its precision oncology programme to address rising comprehensive genomic profiling referral volume. The network reported an existing caseload of roughly 400 annual KRAS-mutant cancer diagnoses and faced pressure to finalize formulary selection before its next annual budget cycle (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
Selecting a formulary option without proven mutation coverage breadth risked excluding patients whose tumors carried variants beyond the network's current single-mutation protocol, undermining precision oncology programme credibility and referring physician confidence. Leadership needed a formulary combining validated coverage performance with a credible combination regimen track record suited to the network's expansion timeline and budget.
MMA APPROACH
MMA evaluated three candidate formulary configurations against documented mutation coverage data, combination regimen depth, and total drug cost across the network's projected five-year patient volume horizon. We modelled patient exclusion risk under each configuration's actual coverage breadth rather than accepting manufacturer-provided assurances alone. We then assessed each configuration's genomic testing partnership support capability.
KEY FINDINGS
  1. Only one of the three candidate formulary configurations had validated coverage across mutation variants comparable to the network's own diagnosed patient population.
  2. The recommended configuration achieved a modeled patient eligibility rate exceeding 85% across comparable treatment populations over time and consistently (client-reported, unverified by MMA).
  3. Combination regimen depth varied considerably across the three configurations evaluated, with the recommended configuration offering the most comprehensive resistance pathway available today.
  4. Selecting a configuration without proven mutation coverage, based purely on drug cost, would have risked meaningful patient exclusion and lasting reputational exposure.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 3 months): Finalize formulary selection and integrate mutation coverage requirements into new tumor board protocol design. Phase 2: Phase 2 (3 to 9 months): Complete physician training and testing partnership rollout, confirming eligibility rates against modeled projections throughout. Phase 3: Phase 3 (9 to 12 months): Launch expanded precision oncology programme and validate outcomes against the original 85% eligibility benchmark target.
OUTCOME
The network completed physician training and programme expansion within the twelve-month timeline, achieving patient eligibility rates in line with the projected estimate ahead of the launch deadline. Formulary performance held steady through initial patient volume, and the selection framework is now the network's standard approach for future precision oncology programme expansion (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the KRAS Inhibitor Market?

The global KRAS inhibitor market reached an estimated USD 2.12 billion in 2025, covering G12C, G12D, G12V, and pan-KRAS targeted therapeutics across approved and pipeline oncology compounds.

How large will the KRAS Inhibitor Market be by 2036?

MMA projects the market will reach approximately USD 10.63 billion by 2036, reflecting expanding pan-KRAS pipeline advancement and rising comprehensive genomic profiling adoption across major oncology markets worldwide.

What is the CAGR for the KRAS Inhibitor Market 2026 to 2036?

The market is forecast to grow at a 17.5% CAGR between 2026 and 2036, driven by pan-KRAS pipeline advancement and expanding genomic testing access across major oncology markets.

Which segment is growing fastest?

Pan-KRAS inhibitors lead at a 24.0% CAGR, roughly 1.37 times the overall market rate, as developers pursue broader mutation coverage beyond the G12C-specific drugs that defined the category.

Who are the major companies in the KRAS Inhibitor Market?

Leading participants include Amgen, Bristol Myers Squibb, Revolution Medicines, Boehringer Ingelheim, and Roche, evaluated on a consistent prescription drug revenue basis across qualified oncology prescriber customers.

Which country is growing fastest?

The United States leads country-level growth, anchoring North America's dominant share since both currently approved G12C inhibitors were developed and first approved domestically nationwide today.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Mutation Mechanism

  • Pan-KRAS Inhibitors
  • G12C-Targeted Inhibitors
  • G12D-Targeted Inhibitors
  • G12V-Targeted Inhibitors
  • Combination Therapy Regimens

By Tumor Type

  • Non-Small Cell Lung Cancer
  • Colorectal Cancer
  • Pancreatic Cancer
  • Other Solid Tumors

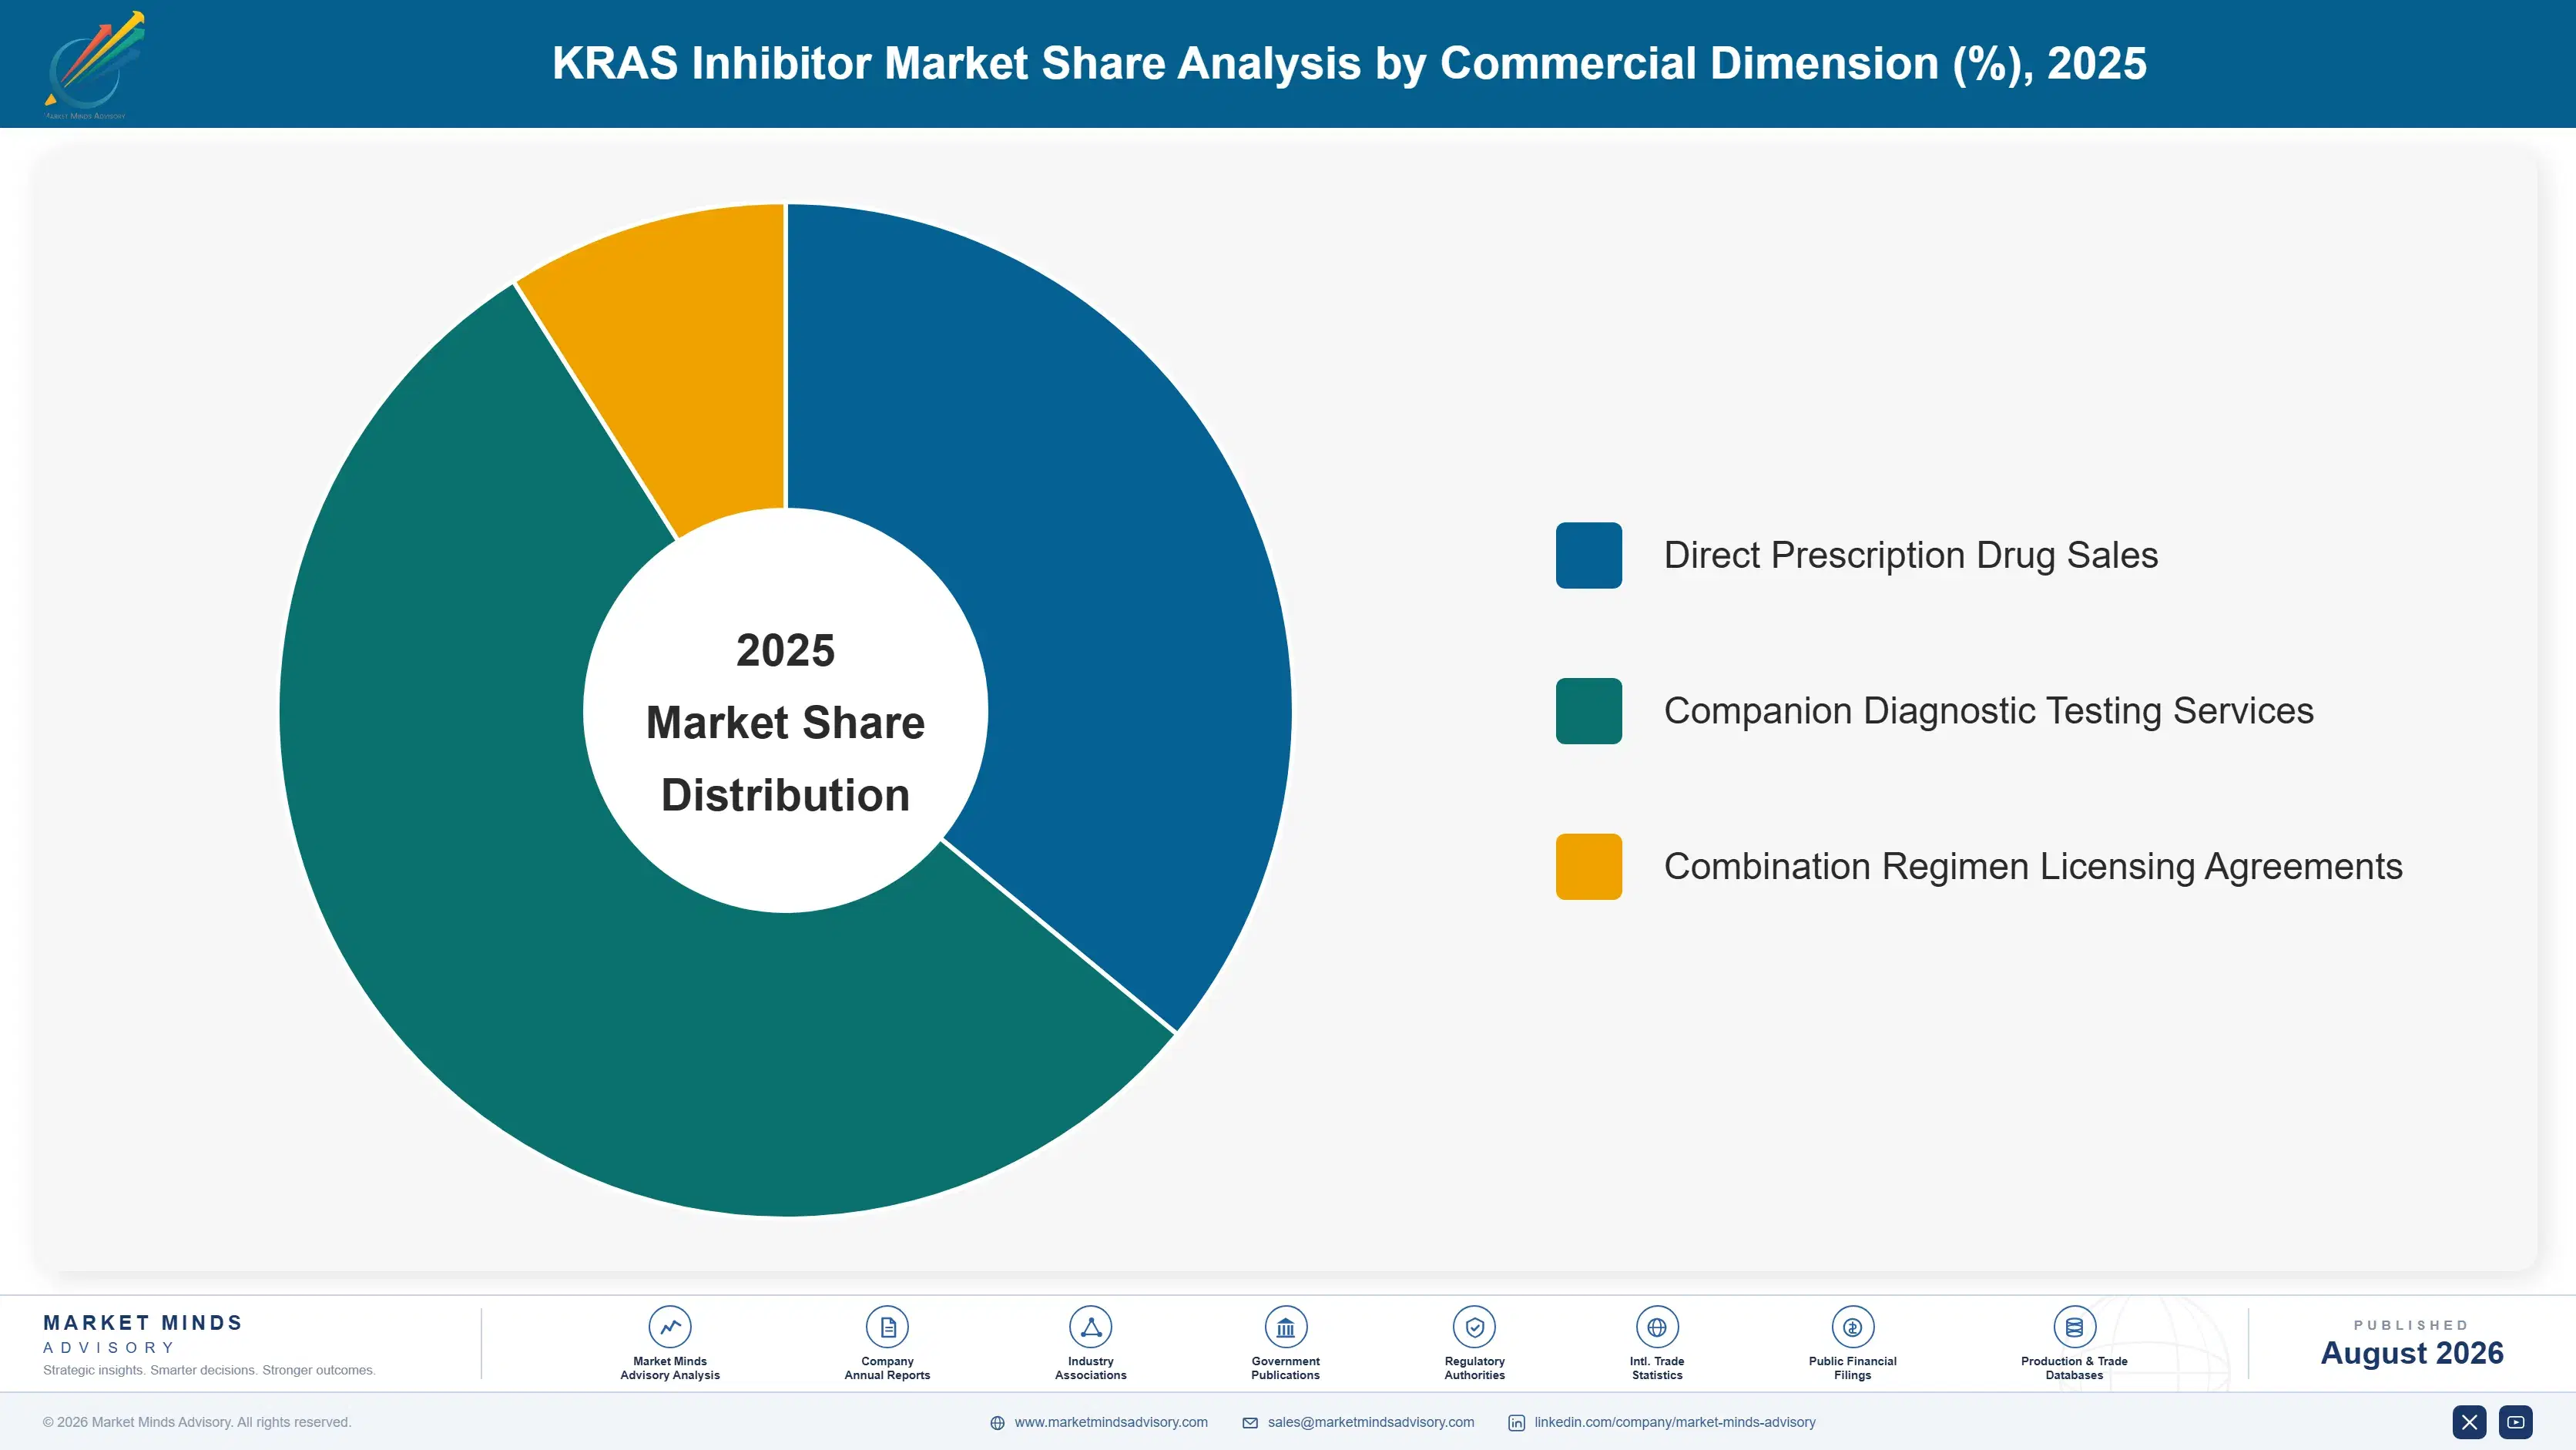
By Commercial Dimension

  • Direct Prescription Drug Sales
  • Companion Diagnostic Testing Services
  • Combination Regimen Licensing Agreements

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The KRAS inhibitor market comprises small-molecule and targeted therapeutics inhibiting mutant KRAS protein signaling in cancers, valued at manufacturer prescription drug prices to oncology treatment centers. It spans G12C, G12D, G12V, and pan-KRAS mechanisms across approved and pipeline compounds. General chemotherapy and broad-spectrum targeted therapies are excluded from this scope entirely.
Quantitative Units
USD billions (current prices); prescription volume where applicable
Segmentation Dimensions
By Mutation Mechanism; By Tumor Type; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Germany, UK, France, China, Japan, South Korea, Taiwan, India, Australia, Brazil, Mexico, Argentina, Chile, UAE, Saudi Arabia, South Africa, Poland, Czechia, and additional markets relevant to this sector
Key Companies Profiled
Amgen, Bristol Myers Squibb (Mirati Therapeutics), Revolution Medicines, Boehringer Ingelheim, Roche (Genentech), Eli Lilly, Novartis, AstraZeneca, Merck and Co., Pfizer, Sanofi, Verastem Oncology, BridgeBio Pharma, Erasca Inc., Black Diamond Therapeutics, Jacobio Pharmaceuticals, InventisBio, Kumquat Biosciences, Repare Therapeutics, Relay Therapeutics
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-241
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full KRAS Inhibitor Market Report (2026 to 2036).

The full MMA KRAS Inhibitor report sizes the market across five mutation mechanism segments, seven regions, and multiple tumor type categories through 2036. It profiles 20 companies on a consistent basis of prescription drug revenue to qualified oncology prescriber customers, scoring each on pan-KRAS coverage validation, combination regimen investment, genomic testing partnerships, and evidence transparency. Scenario models quantify how mutation coverage expansion and combination therapy adoption move both volume and achievable margin across all seven regions. The report also includes efficacy benchmark data and prescriber mapping.
Five-mechanism market sizing across seven regions through 2036
Twenty-company benchmark on prescription drug and testing revenue
Pan-KRAS pipeline regulatory tracking by region and phase
Validated mutation coverage benchmarking across leading developers
Combination regimen mapping across major oncology treatment networks
Specialty synthesis input supply chain risk mapping

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts