Market Minds Advisory
Hospital Surgical Disinfectant Market

Hospital Surgical Disinfectant Market: Aldehyde Displacement, Contact Time Reality, and Purchasing Consolidation

Disinfectant accounts for under one per cent of what a surgical procedure costs and carries a wholly disproportionate share of its infection liability, which is why price alone has never decided these contracts.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$4.6BMarket Size 2025
2036 FORECAST VALUE$8.7BBase Case , 2026 to 2036
CAGR 2026 TO 20366.0 %Bull 7.2% / Bear 4.8%
INCREMENTAL OPPORTUNITY$3.9BNet 10- year value creation
EXPANSION MULTIPLE1.79x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Glutaraldehyde is being removed from hospitals for reasons that have nothing to do with how well it works. Occupational exposure limits and staff sensitisation claims are driving the change, and peracetic acid and hydrogen peroxide are taking the volume it leaves behind. The chemistry never stopped working.
Oxidising agent formulations compound at 9.0%, a full 1.50x the market rate, absorbing aldehyde volume in endoscope reprocessing and no-touch room decontamination alike. East Asia holds the largest share at 29%, carried by Chinese and Indian surgical volumes that exceed any other region and by domestic manufacturers supplying most of it. Per-procedure spending there sits well below Western levels, and domestic producers supply most of the volume.
Concentration is moderate at 44%. Ecolab and STERIS reach hospitals through quite different routes: chemical service contracts on one side, reprocessing equipment on the other. Group purchasing organisations now control roughly 68% of United States volume. Material compatibility with flexible endoscopes remains the real technical barrier, and efficacy data alone has never been enough to clear it. Warranty coverage follows the validated list exactly, so an unvalidated agent is unusable however well it performs.
Market Definition
This market covers chemical disinfectant and antiseptic products supplied for use in hospital surgical settings, spanning surgical site skin antisepsis, surgical hand preparation, instrument and endoscope high-level disinfection, and operating theatre environmental surface disinfection. Measurement is at manufacturer revenue attributable to surgical and perioperative use. Terminal sterilisation equipment and consumables, general ward and non-surgical cleaning chemicals, consumer antiseptics, wound care antimicrobials, and systemic antibiotic prophylaxis are excluded.
Base Year Value
$4.6B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
6.0% base case. Bull 7.2%. Bear 4.8%.
Fastest Growth Segment
Oxidising Agent Formulations: 9.0% CAGR
Fastest Growth Country
India: 9.6% CAGR
Fastest Growth Region
South Asia and Pacific: 8.2% CAGR
Largest Region
East Asia: 29% of 2025 global value
Market Leaders
Ecolab, STERIS, 3M, Becton Dickinson, and Solenis. Source: MMA Primary Research Dataset, July 2026.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Hospital Surgical Disinfectant Market Forecast Scenarios

hospital-surgical-disinfectant-market-size-forecast-scenario-1787303497189
Growth ran at roughly 4.9% between 2020 and 2025, and the pandemic distorted it in both directions. Environmental disinfectant consumption rose sharply through 2020 and 2021 as protocols intensified everywhere, while elective surgical volumes collapsed and took instrument and skin antisepsis demand with them. Elective backlogs then cleared through 2022 and 2023 at unusually high theatre utilisation, and consumption normalised somewhat above its pre-pandemic trend.
Base case growth of 6.0% depends on three mechanisms. Surgical procedure volumes rise steadily with ageing populations and expanding access across Asia and Latin America, and disinfectant consumption tracks procedure count almost exactly. Aldehyde displacement transfers volume toward oxidising chemistries that carry higher unit pricing. And automated endoscope reprocessing continues replacing manual soaking, which raises chemical consumption per procedure while improving the consistency of the outcome. None depends on product innovation.
The bull case at 7.2% assumes accelerated aldehyde restriction across European and Asian occupational regulation, which would compress a transition currently spread over a decade into perhaps four years. The bear case at 4.8% is a purchasing one: further group purchasing consolidation, combined with commoditisation of surface disinfectants, would push more of this market onto tender pricing that erodes annually.

Surgical Disinfectants: Liability Asymmetry and Chemistry Transition

The commercial logic here rests on an asymmetry. Disinfectant costs about four dollars across an entire surgical procedure, well under one per cent of the total, while a surgical site infection costs a hospital tens of thousands to manage and carries reputational and legal consequences besides. That gap is why infection prevention teams, not procurement, have historically decided which antiseptic goes on the shelf.
TOP FIVE CONCENTRATION44%Chemical service and reprocessing equipment suppliers reach hospitals differently
SURGICAL INFECTION RATE2.6%Procedures resulting in a surgical site infection across tracked systems
COST PER PROCEDUREUSD 4.10Blended disinfectant and antiseptic spend for one surgical procedure
ALDEHYDE SHARE REMAINING11%High-level disinfection volume still using aldehyde based chemistry
CONTRACT RENEWAL CYCLE3 yearsTypical interval before hospitals retender disinfectant supply agreements
GROUP PURCHASING SHARE68%United States hospital volume contracted through purchasing organisation agreements
Purchasing has been shifting that balance for a decade. Group purchasing organisations now contract roughly 68% of United States hospital volume, and consolidated systems elsewhere behave similarly. Surface disinfectants have largely become tendered commodities as a result. Skin antiseptics and high-level disinfectants have resisted, because clinical protocol and instrument compatibility still give the infection prevention team an effective veto over purchasing decisions.
The transition underway is regulatory rather than clinical. Glutaraldehyde and ortho-phthalaldehyde work perfectly well and are being removed anyway, because occupational exposure limits have tightened and staff sensitisation claims have proved expensive. Peracetic acid and hydrogen peroxide formulations absorb the volume at higher unit prices. Aldehydes now represent about 11% of high-level disinfection and that share keeps falling steadily. Nothing about that transition is clinical.
"Nobody has ever lost a hospital contract because the disinfectant cost too much. They lose it because the product corroded a scope, or because a theatre nurse developed occupational asthma, and both of those problems are far more expensive than any price difference."
Principal Analyst, Infection Prevention and Specialty Chemicals Practice · MMA C

Market Trends

Occupational regulation removes aldehydes from high-level disinfection

Glutaraldehyde and ortho-phthalaldehyde remain clinically effective and are disappearing from hospitals regardless, because tightened occupational exposure limits and a history of staff sensitisation have made them a liability to keep. European and Australian regulators moved earliest, with Asian occupational authorities following. Peracetic acid and hydrogen peroxide formulations take the displaced volume at higher unit prices and with better material compatibility profiles. Aldehyde chemistry now covers about 11% of high-level disinfection volume, down from a position of clear dominance fifteen years ago. Occupational timetables, not clinical guidelines, decide when each market converts.
Market Impact: Roughly 330 million procedures annu

Automated reprocessing raises chemical consumption per endoscope cycle

Manual soaking of flexible endoscopes is being replaced by automated endoscope reprocessors that control contact time, temperature and rinse volume without depending on staff technique. The clinical case is strong, since manual reprocessing failures have caused documented outbreaks. Commercially the effect is favourable in an unexpected way: automated cycles consume more chemical per procedure than careful manual practice does, and they use single-use or short-cycle concentrate formats that lock the hospital into one supplier's chemistry for the machine's working life. Manual reprocessing failures have caused documented outbreaks, so the clinical argument runs alongside the commercial one rather than against it.
Market Impact: Infections cost 5,000 times disinfe

Market Opportunities and Growth Drivers

Surgical volumes rise steadily with ageing and expanding access

Disinfectant consumption tracks surgical procedure count more directly than almost any other hospital consumable, because every case requires skin preparation, hand antisepsis, instrument processing and theatre turnover cleaning regardless of complexity. Global procedure volumes keep rising as populations age and as surgical access expands across Asia and Latin America. Roughly 330 million surgical procedures are performed annually, and that figure grows every year the health systems tracked here add theatre capacity. No product innovation is required to capture it. Forecasting is unusually reliable as a result, and no supplier grows by persuading hospitals to use more of it.
Market Impact: Roughly 68% of volume tendered

Infection reporting mandates make prevention spending politically defensible

Public reporting of surgical site infection rates, and payment penalties tied to them in the United States and several European systems, have converted infection prevention from a cost line into a measured performance outcome. Hospital boards approve antiseptic protocol changes far more readily when the infection rate appears in a published table. A surgical site infection costs a hospital tens of thousands to manage against roughly four dollars of disinfectant per procedure, and that arithmetic becomes persuasive once somebody is publishing the numbers. Publication changed the conversation more than any efficacy data ever did.
Market Impact: Only 4 chemistries widely validated

Market Restraints and Challenges

Group purchasing consolidation commoditises surface disinfectant supply

Purchasing organisations now contract roughly 68% of United States hospital volume and consolidated systems elsewhere behave similarly, tendering surface disinfectants on price with efficacy treated as a qualifying threshold rather than a differentiator. The root cause is that environmental disinfectants genuinely have converged: most quaternary ammonium and hypochlorite products meet the same efficacy claims. Commercial impact is annual price erosion on a large volume base. Suppliers respond by bundling dispensing equipment, training and compliance auditing into contracts, which tender documents struggle to price comparably. Tender documents struggle to price that bundling comparably, which is exactly the intention behind it.
Market Impact: Aldehyde share down to 11%

Material compatibility constrains which chemistries endoscopes can accept

A flexible endoscope costs tens of thousands of dollars and a chemistry that degrades its adhesives, coatings or sealing over repeated cycles is unusable however well it kills organisms. The root cause is that endoscope manufacturers validate a limited list of compatible agents and warranty coverage follows that list exactly. Commercial impact is a genuine barrier to entry that has little to do with the disinfectant itself. New entrants respond by pursuing manufacturer validation early and by funding multi-cycle compatibility studies before making any efficacy claim. Validation typically takes eighteen months or more to complete.
Market Impact: Chemical use up 30% per cycle
2 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows active chemistry, because the active agent determines the regulatory pathway, the occupational exposure profile, material compatibility, contact time and the clinical application it can serve. Six chemistries cover surgical disinfectant supply without overlap. Application format, whether wipe, solution, concentrate or applicator, varies within each chemistry and is treated as a delivery attribute here. Chemistry sets the commercial rules.
hospital-surgical-disinfectant-market-market-share-analysis-1787303497722

Oxidising Agent Formulations

Growing at 9.0%, a full 1.50x the market rate, peracetic acid, hydrogen peroxide and chlorine dioxide formulations are absorbing the volume that aldehyde restriction has released. They achieve high-level disinfection with far better occupational exposure profiles and generally shorter contact times, which matters when theatre turnover is the constraint. Hydrogen peroxide vapour systems have also established themselves in no-touch room decontamination between cases. Unit pricing runs above aldehydes and above quaternary ammonium products, and material compatibility work with endoscope manufacturers has removed the reservations that once limited adoption in reprocessing applications. Concentrate formats for automated reprocessors also commit a hospital to one supplier's chemistry across the machine's whole working life.
CAGR 9.0%

Chlorhexidine Gluconate Formulations

Chlorhexidine gluconate grows at 7.2%, having won the surgical site preparation argument against povidone-iodine on clinical evidence over the past fifteen years. Alcoholic chlorhexidine preparations show lower infection rates in most comparative studies and have been written into guidelines accordingly. Residual activity on skin is the practical advantage, since the agent keeps working through a long procedure. Growth is tempered by documented anaphylaxis cases that have prompted regulatory warnings and kept iodine preparations in use as an alternative. Preoperative bathing protocols and impregnated dressings have opened further volume beyond theatre application itself. Purchasing organisations have recently begun tendering this category directly, which clinical committees have protected until now, and that shift is the main commercial risk ahead.
CAGR 7.2%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Regional value follows surgical procedure volume and protocol intensity together, and the two diverge sharply. East Asia performs the most surgery at the lowest disinfectant spend per case. North America performs considerably less at several times the per-procedure cost of any other region tracked. Protocol intensity explains the gap.

East Asia

East Asia holds the largest share at 29%, and surgical volume rather than pricing explains it. Chinese hospitals perform more operations annually than any other national system, and domestic manufacturers including Shanghai Likang and Lionser supply most of the disinfectant they use at prices international suppliers cannot approach. Centralised procurement has compressed pricing further. Japanese protocol intensity is high and per-procedure spending resembles Western Europe, which lifts the regional average considerably. South Korean and Taiwanese hospitals adopt automated endoscope reprocessing quickly. Growth at 7.1% comes from procedure volume and from aldehyde displacement running slightly behind the Western timetable. Value share understates procedure share here by a very considerable margin, and domestic pricing shows no sign of rising.
Share: 29% | CAGR: 7.1% (2026 to 2036)

North America

Twenty-six per cent of value on considerably fewer procedures than East Asia performs, because United States per-procedure disinfectant spending runs several times higher and protocols are more intensive. Public reporting of surgical site infection rates and payment penalties tied to them have made infection prevention spending straightforward to justify at board level. Group purchasing organisations contract roughly 68% of hospital volume, and surface disinfectants have become tendered commodities as a result. Skin antiseptics have resisted that pressure because clinical protocol still governs selection. Growth at 5.2% reflects a mature procedure base absorbing steady tender price erosion. Purchasing organisations have begun extending tendering into antiseptic categories that clinical committees previously kept outside price-led contracting altogether.
Share: 26% | CAGR: 5.2% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: Western Europe, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
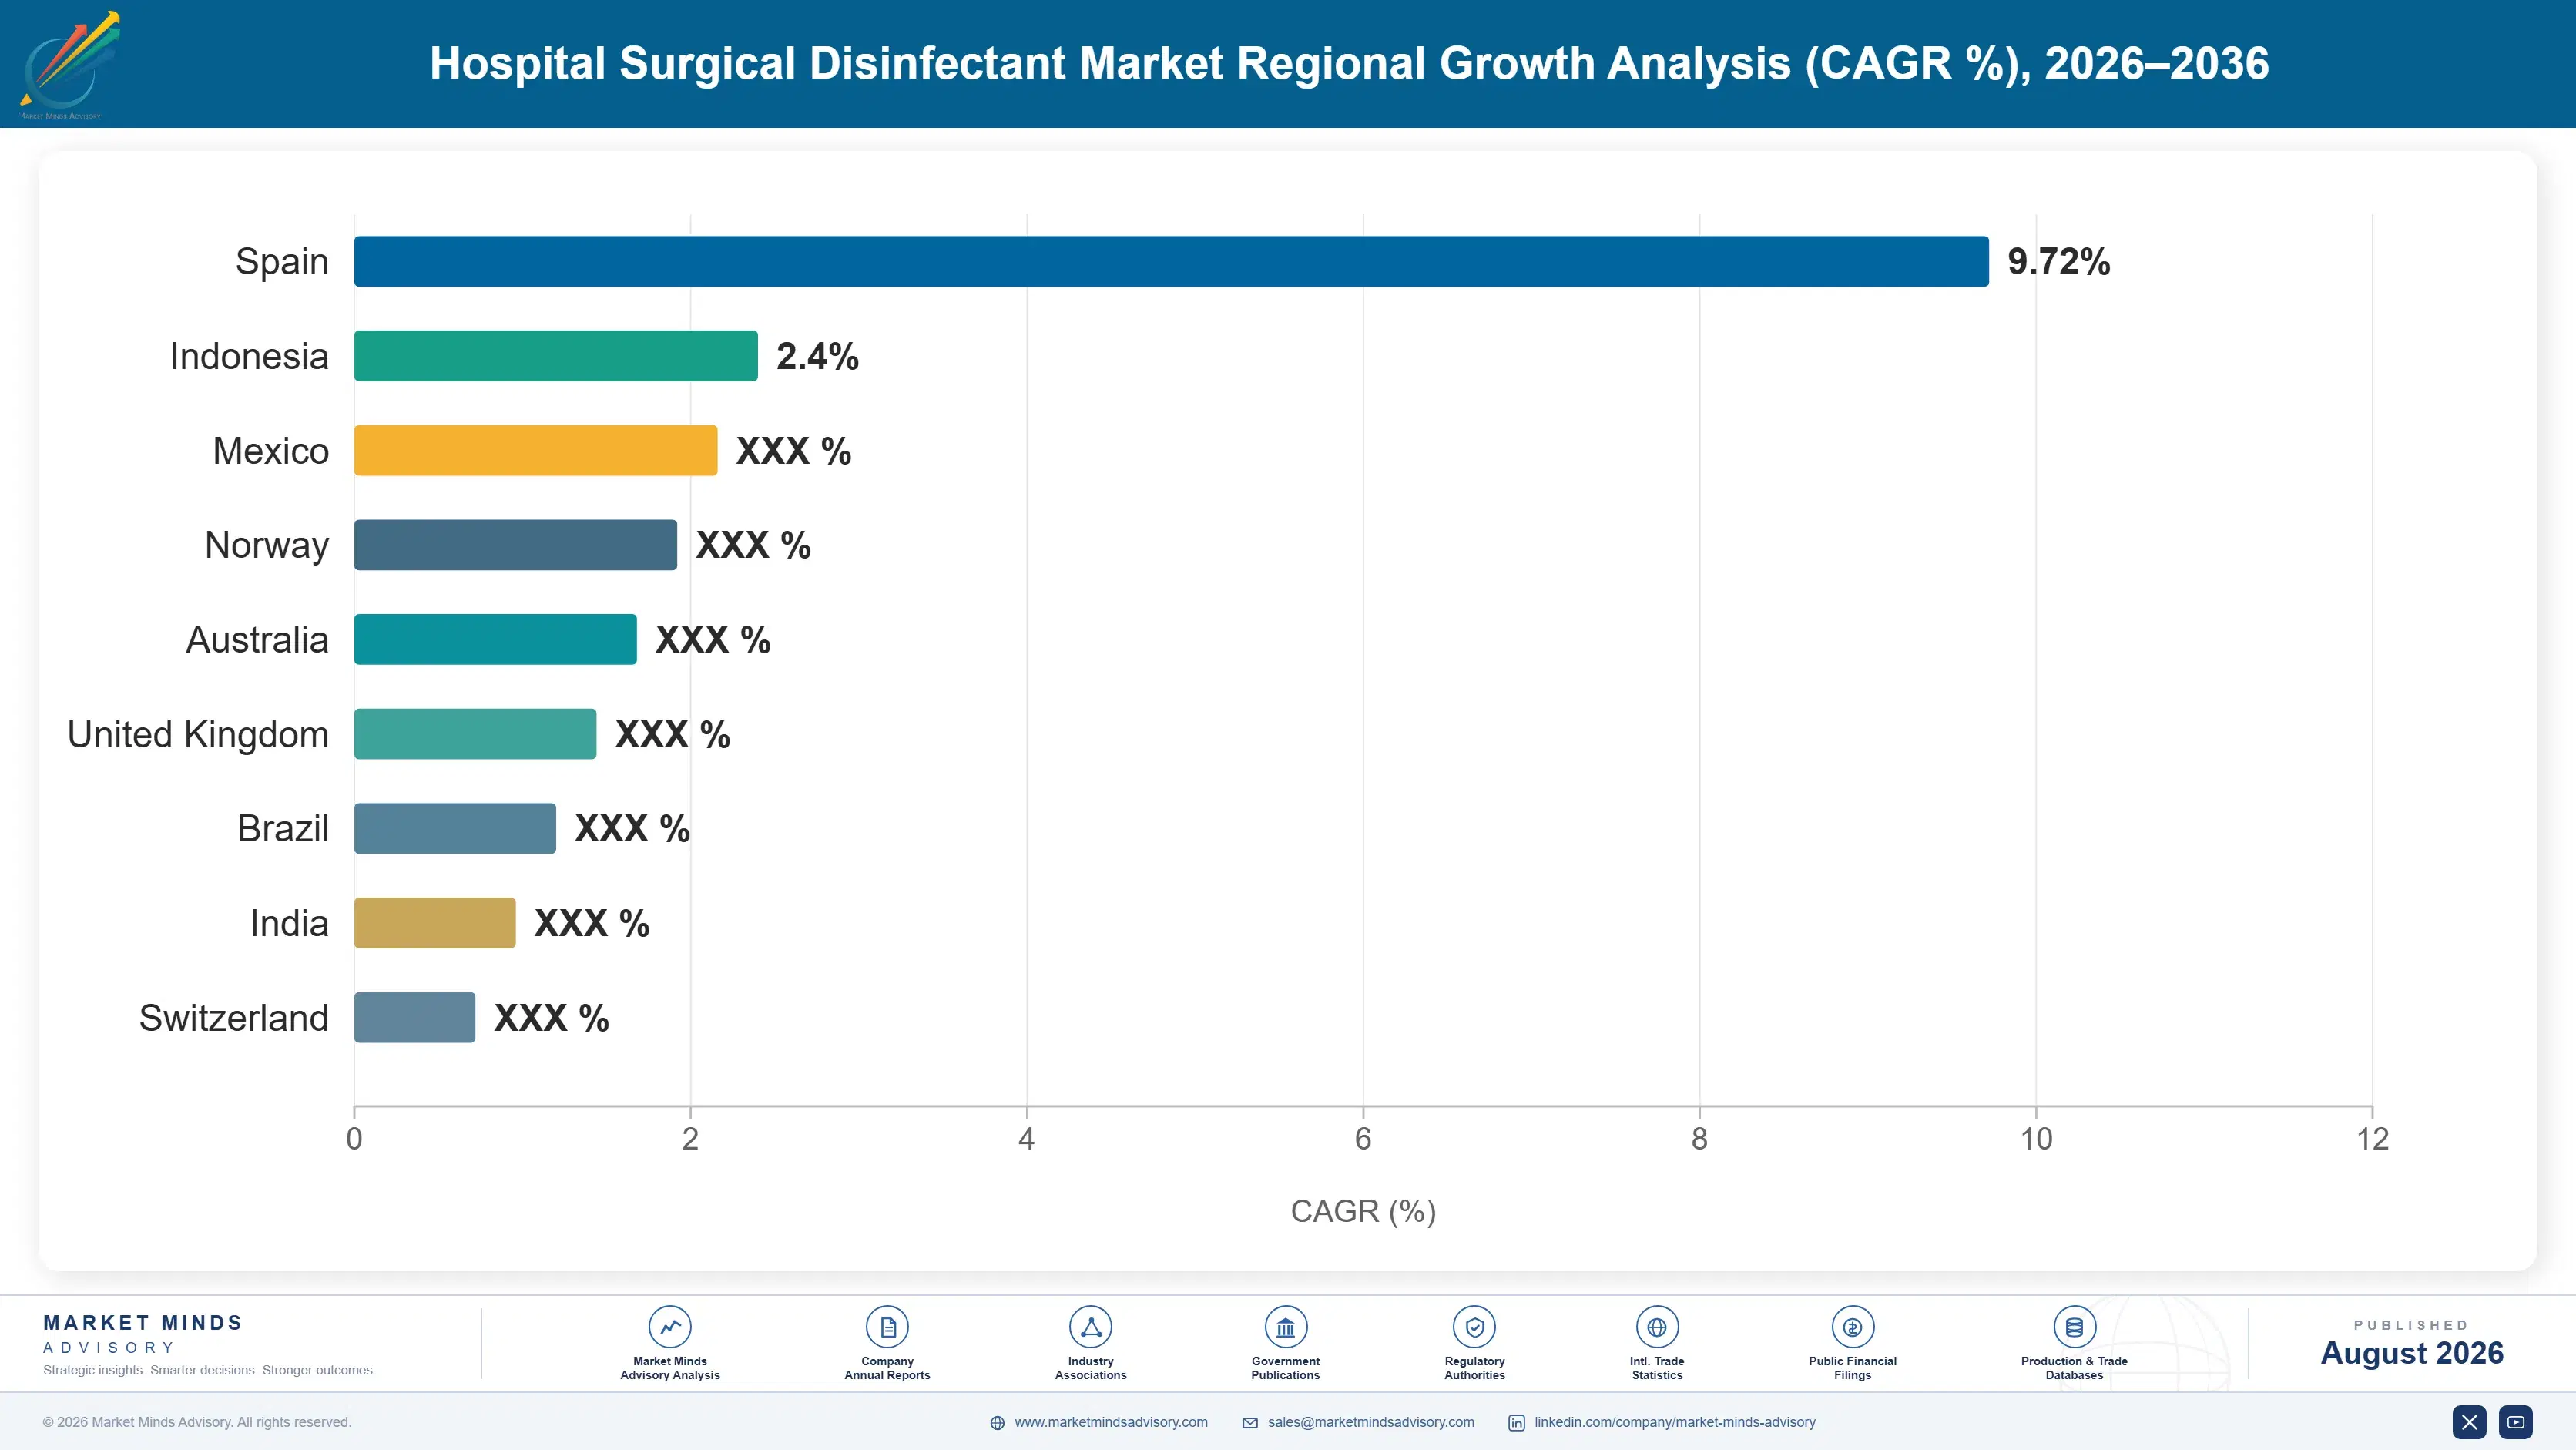
hospital-surgical-disinfectant-market-country-cagr-analysis-1787303498245

Where Disinfectant Contracts Are Actually Won

Disinfectant is a trivial share of procedure cost and a substantial share of infection liability, so price has never decided these contracts on its own. Value accrues to whoever controls the endoscope compatibility list, whoever owns the dispensing equipment inside the hospital, and whoever the infection prevention team trusts. Price has rarely been decisive.

Secure endoscope manufacturer validation before making efficacy claims

Endoscope manufacturers validate a limited list of compatible chemistries and warranty coverage follows that list precisely, so a hospital will not use an unvalidated agent regardless of its efficacy data. Only about four chemistries are widely validated across the major scope platforms. Funding multi-cycle compatibility studies costs real money and takes eighteen months or more, and it converts a commodity chemical into a product with a genuine barrier around it. Suppliers who pursued validation early hold reprocessing positions that price competition has been unable to dislodge. Validation typically covers 3 major scope platforms before national bidding.
Market Impact: Only about 4 chemistries currently

Place dispensing and reprocessing equipment to lock chemistry supply

Automated endoscope reprocessors and wall-mounted dispensing systems accept specific concentrate formats, and a hospital that installs them commits to that chemistry for the equipment's working life of seven years or more. Placing equipment at or below cost buys that consumable annuity outright, and consumables represent roughly 85% of lifetime contract value. The discipline required is contractual: placement agreements need minimum consumable commitments, because hospitals that accept discounted equipment and then tender the chemistry separately break the arrangement completely. Hospitals accepting discounted equipment and then tendering the chemistry separately break the arrangement entirely, so enforcement matters as much as placement.
Market Impact: Consumables carry about 85% of tota

Sell infection cost arithmetic to the board, not the buyer

Procurement compares disinfectant prices; infection prevention compares outcomes. A surgical site infection costs a hospital tens of thousands to manage against roughly four dollars of disinfectant per procedure, a ratio of several thousand to one, and that argument only lands with people who carry the infection rate as a published performance measure. Suppliers who present at board and quality committee level rather than to purchasing consistently defend pricing that tender processes would otherwise erode. It is a longer sale and it holds far better. A single infection costs roughly 5,000 times the disinfectant used in the procedure that caused it.
Market Impact: Infection cost ratio exceeds 5,000

Bundle training and compliance audit into supply agreements

Environmental disinfectant labels specify contact times of four to ten minutes and observed practice frequently falls well under one minute, which means the product routinely fails in use rather than in testing. Suppliers who provide staff training, compliance auditing and contact time monitoring convert a tendered commodity into a service relationship worth roughly 20% more per contract. Tender documents struggle to price that comparably, which is precisely the point. It also improves the outcome the hospital is actually buying. Compliance auditing also improves the outcome the hospital believes it is buying, which is not a trivial secondary benefit.
Market Impact: Worth roughly 20% more per hospital

Who Controls the Margin Pool

Concentration sits at 44% across the top five, measured on annual revenue from disinfectant and antiseptic products supplied into hospital surgical settings, the single basis applied throughout. Ecolab and STERIS lead through routes that barely overlap: chemical service contracts and dispensing infrastructure on one side, reprocessing equipment on the other. 3M, Becton Dickinson and Solenis follow with positions concentrated in skin antisepsis and surface disinfection respectively.
Competition runs on quite different terms by application. Surface disinfectants compete on tendered price with efficacy as a qualifying threshold, since products have genuinely converged. Skin antiseptics compete on clinical evidence and guideline placement, where chlorhexidine has largely displaced povidone-iodine. High-level disinfection competes on endoscope manufacturer validation and occupational exposure profile, and that contest is effectively closed to anyone who has not funded multi-cycle compatibility work.

Pressure is building from two directions. Chinese and Indian manufacturers supply their domestic hospital systems at prices international suppliers cannot match, and centralised procurement in both countries rewards that directly. Separately, purchasing organisations keep extending tendered categories upward from surface products toward antiseptics. Rankings shift most where a supplier loses the infection prevention relationship that has historically kept its products outside the tender process altogether.
hospital-surgical-disinfectant-market-company-positioning-matrix-1787303498774

Competitive Moat and Risk Dimensions

ECOLAB

Moat: Installed dispensing and service depth

Ecolab reaches hospitals through service contracts that include dispensing equipment, staff training and compliance auditing rather than through product supply alone. That arrangement is difficult for a tender document to price against a competing chemical quotation, and the installed dispensing base commits a hospital to compatible concentrate formats for years at a time.
ECOLAB

Risk: Surface disinfectant commoditisation

A substantial part of the portfolio sits in environmental disinfection, where products have converged and purchasing organisations tender on price with efficacy as a threshold. Service bundling defends margin but not indefinitely. Chinese and Indian domestic manufacturers meanwhile supply their own hospital systems at costs no international service model can absorb.
STERIS

Moat: Reprocessing equipment chemistry control

Automated endoscope reprocessors and sterilisation equipment accept specific chemistry formats, so an installed STERIS machine determines which consumables a hospital can buy for the seven or more years it remains in service. That equipment position converts capital sales into a chemical annuity, and replacing it means recapitalising a reprocessing department entirely.
STERIS

Risk: Capital cycle dependence

Growth depends on placing new reprocessing equipment, and hospital capital budgets tighten quickly when operating margins compress. Competing equipment manufacturers validate their own chemistries in parallel. Any move by endoscope manufacturers toward open chemistry compatibility standards would weaken the lock that currently protects the consumable revenue base.

Players Tracked

Prominent Players

Ecolab
STERIS
3M
Becton Dickinson
Solenis

Other Key Players

Reckitt Benckiser
Getinge
B. Braun
Schülke & Mayr
Medline Industries
Cardinal Health
PAUL HARTMANN
Metrex Research
Advanced Sterilization Products
Whiteley Corporation
Contec Inc.
Certol International
Nice-Pak Products
Shanghai Likang Disinfectant
Lionser Medical

Recent Developments

FEBRUARY 2025

European occupational authorities tighten glutaraldehyde workplace exposure limits

European occupational health authorities lowered permissible workplace exposure limits for glutaraldehyde and ortho-phthalaldehyde, tightening ventilation and monitoring requirements to a level that makes continued hospital use impractical for most reprocessing departments across the region. Reprocessing departments were given a transition period rather than an immediate prohibition.
Signal: Aldehyde removal is being decided by occup
JULY 2025

STERIS expands peracetic acid concentrate production capacity in Europe

STERIS commissioned additional peracetic acid concentrate manufacturing capacity at a European site, an organic expansion rather than an acquisition, responding to demand growth as hospitals across the region converted endoscope reprocessing away from aldehyde based chemistry. No acquisition or partner site formed part of the expansion.
Signal: Oxidising chemistry supply is being built
MARCH 2026

Major purchasing organisation extends tendering to surgical skin antiseptics

A major United States group purchasing organisation extended competitive tendering to surgical skin antiseptic products, a category that clinical protocol had previously kept outside price-led contracting, prompting objections from several member hospital infection prevention committees. Several member hospital infection committees objected formally to the change.
Signal: Purchasing organisations are moving tender

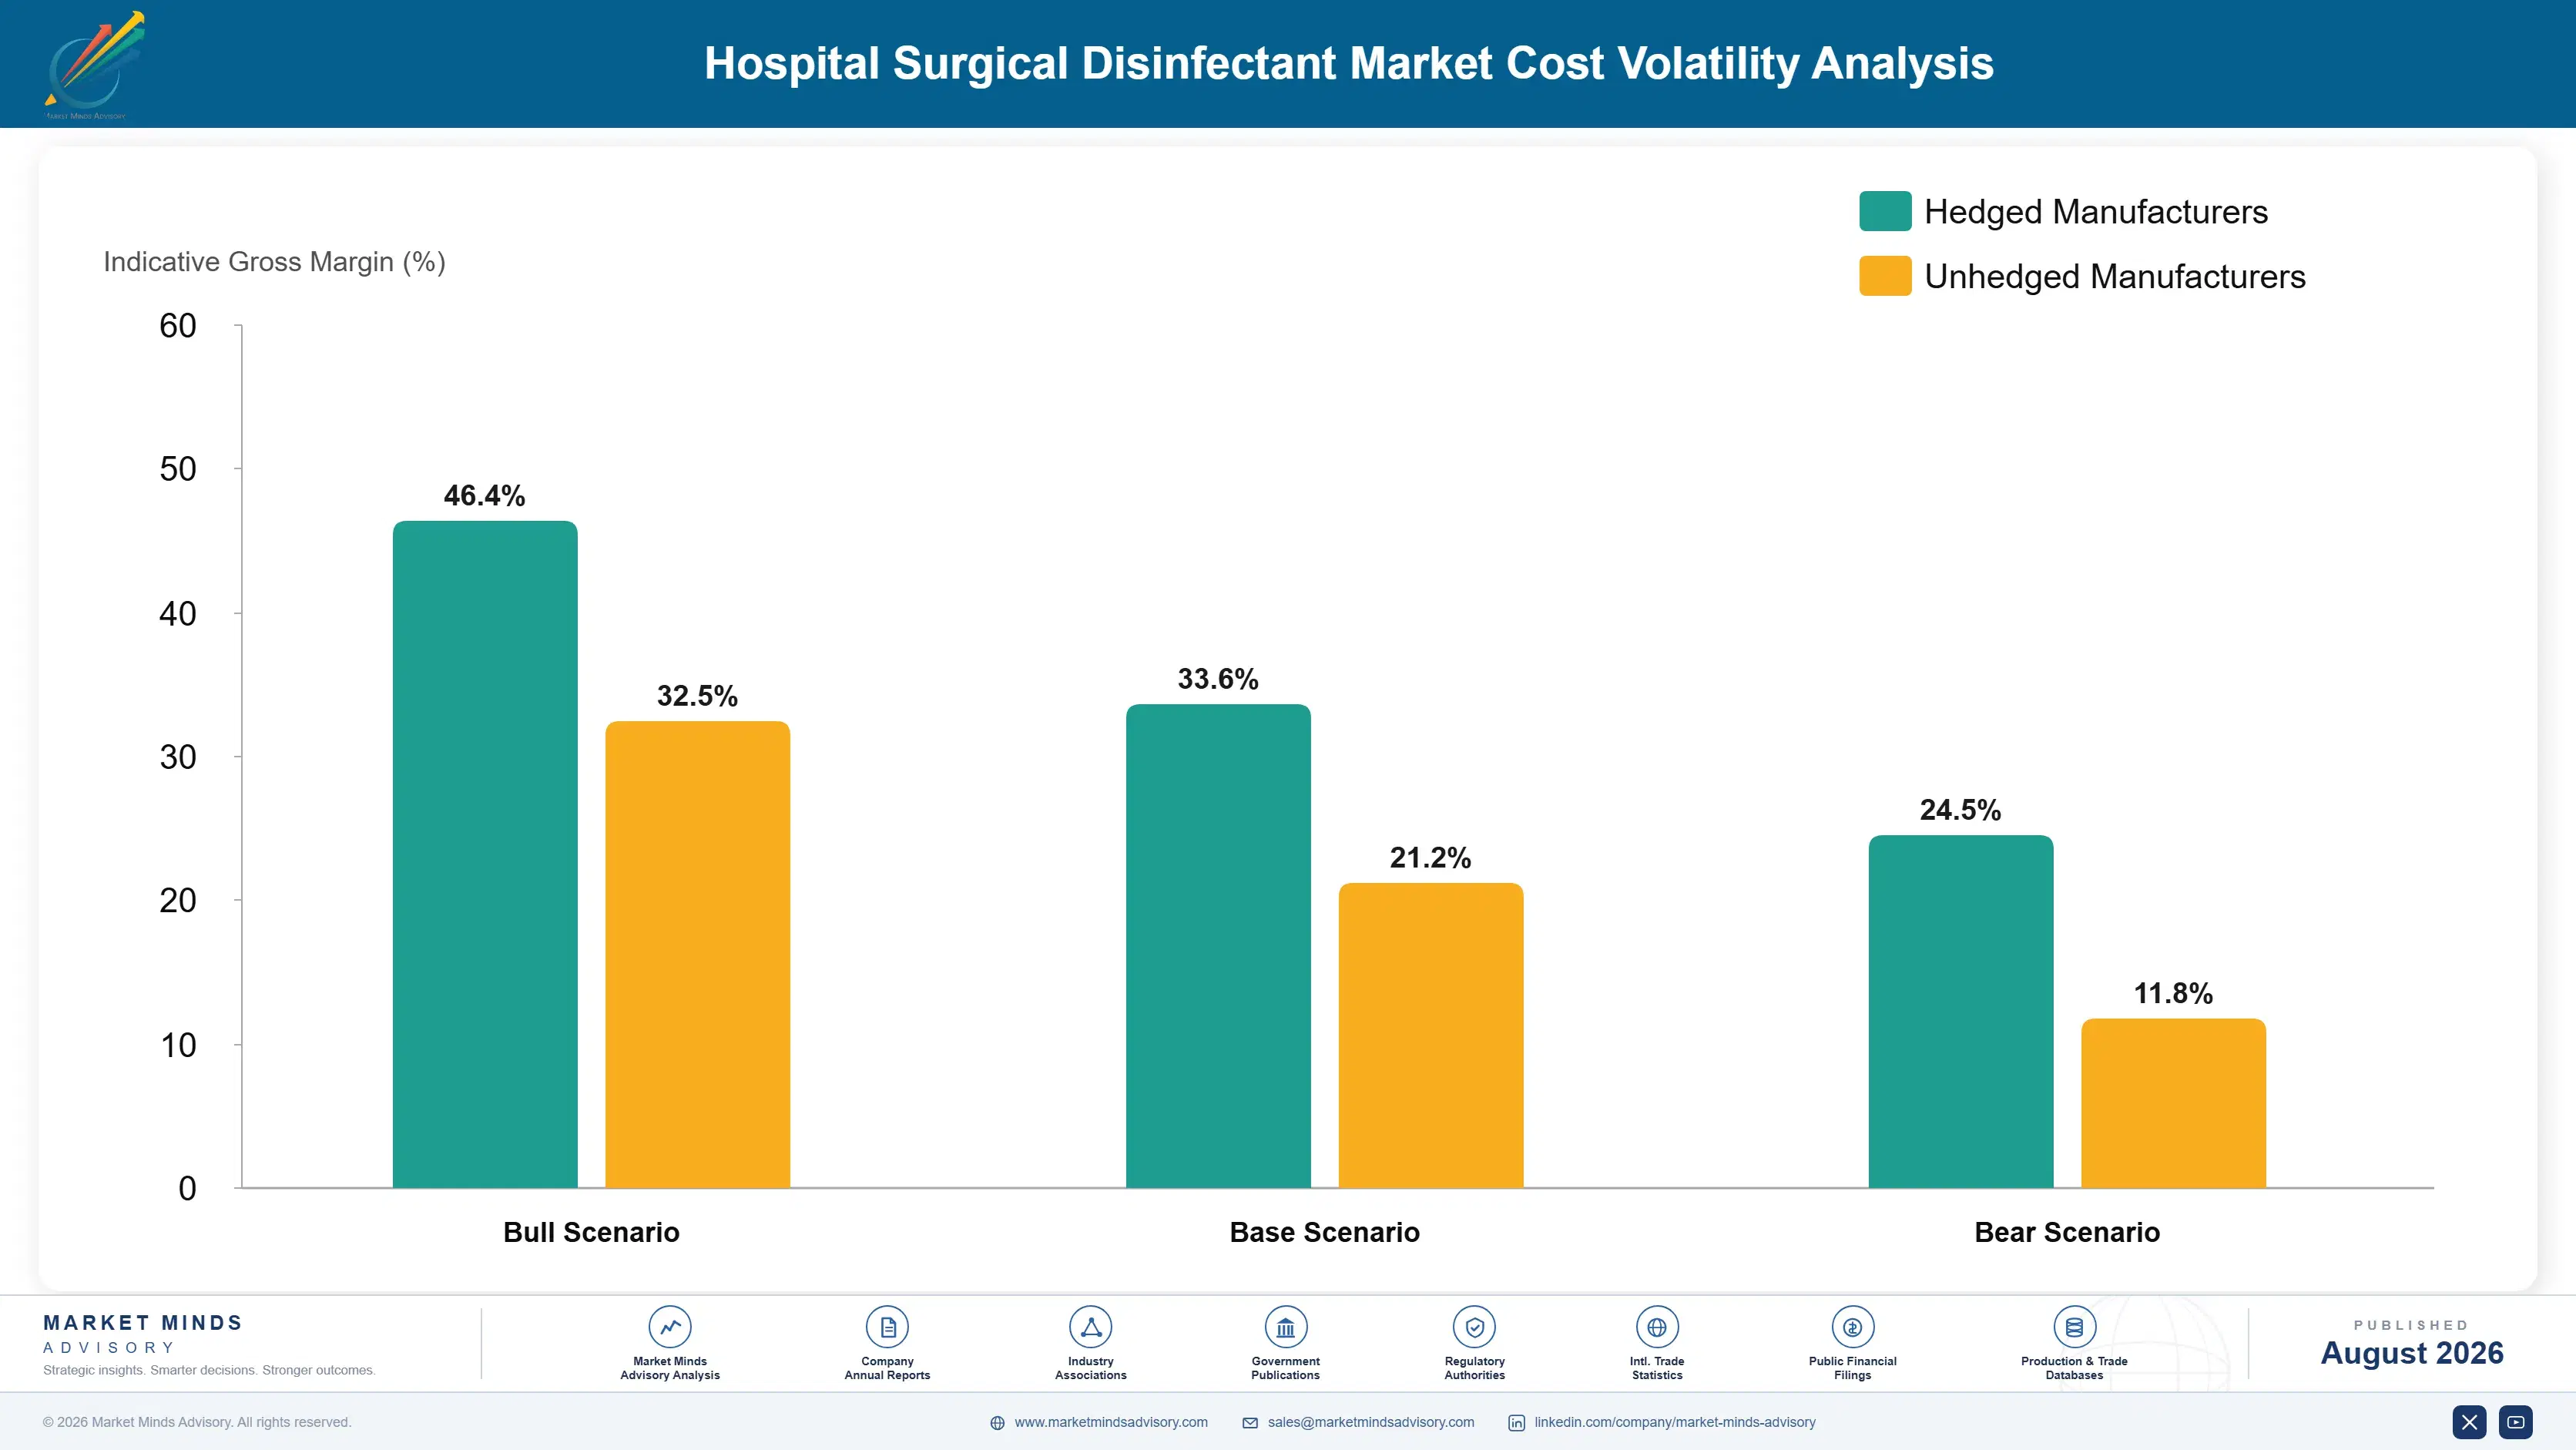
Active Chemistry and Packaging Cost Exposure

Cost structures vary widely by chemistry and that variation drives most of the pricing behaviour in this market. Chlorhexidine gluconate active accounts for roughly 34% of finished antiseptic cost of goods, sourced predominantly from Indian and Chinese producers. Peracetic acid and hydrogen peroxide formulations carry lower active cost but demanding stabilisation and packaging requirements, since both decompose and require compatible containers, contributing around 30% together.
Hydrogen peroxide supply through 2022 and 2023 showed the exposure. European energy costs pushed peroxide production economics sharply higher while demand rose from both disinfection and semiconductor customers, and Solvay and Evonik both documented capacity and cost pressure in their annual reporting for those years. Disinfectant manufacturers absorbed much of it, because hospital tender contracts run three years at fixed pricing and reopening one invites a competitive retender.

The disadvantage falls hardest on suppliers without formulation breadth. A manufacturer holding one chemistry cannot shift mix when its active cost rises, while a broad supplier moves promotional emphasis toward whichever chemistry is currently favourable. Geography compounds it: European producers carry energy and regulatory compliance costs that Chinese and Indian manufacturers do not, in categories where tendered surface products decide on delivered price alone.
hospital-surgical-disinfectant-market-cost-volatility-analysis-1787303498973

Hold formulation breadth across at least three active chemistries

Single-chemistry suppliers cannot respond when their active cost moves, and hospital contracts are too long to reprice mid-term. Carrying chlorhexidine, alcohol and oxidising formulations together allows promotional emphasis to shift toward whichever chemistry is currently favourable. The regulatory and manufacturing overhead of breadth is real, and it is what makes tender participation survivable across a cost cycle.

Secure multi-year hydrogen peroxide supply outside European production

European peroxide economics deteriorated sharply under energy costs while semiconductor demand competed for the same output. Contracting supply from North American or Asian producers alongside European volume protects against a repeat. The freight penalty is modest against the cost of failing to supply a hospital contract, and allocation risk is the real exposure rather than unit price.

Write three-year tender contracts with narrow active cost indexation

Fixed multi-year hospital pricing transferred the entire active ingredient increase onto suppliers during the last cycle. Newer agreements increasingly include indexation limited to named active chemistry costs. Hospital procurement accepts that more readily than any general escalator, because the underlying chemical benchmarks are externally published and clearly outside the individual supplier's control. Buyers verify the benchmark themselves.

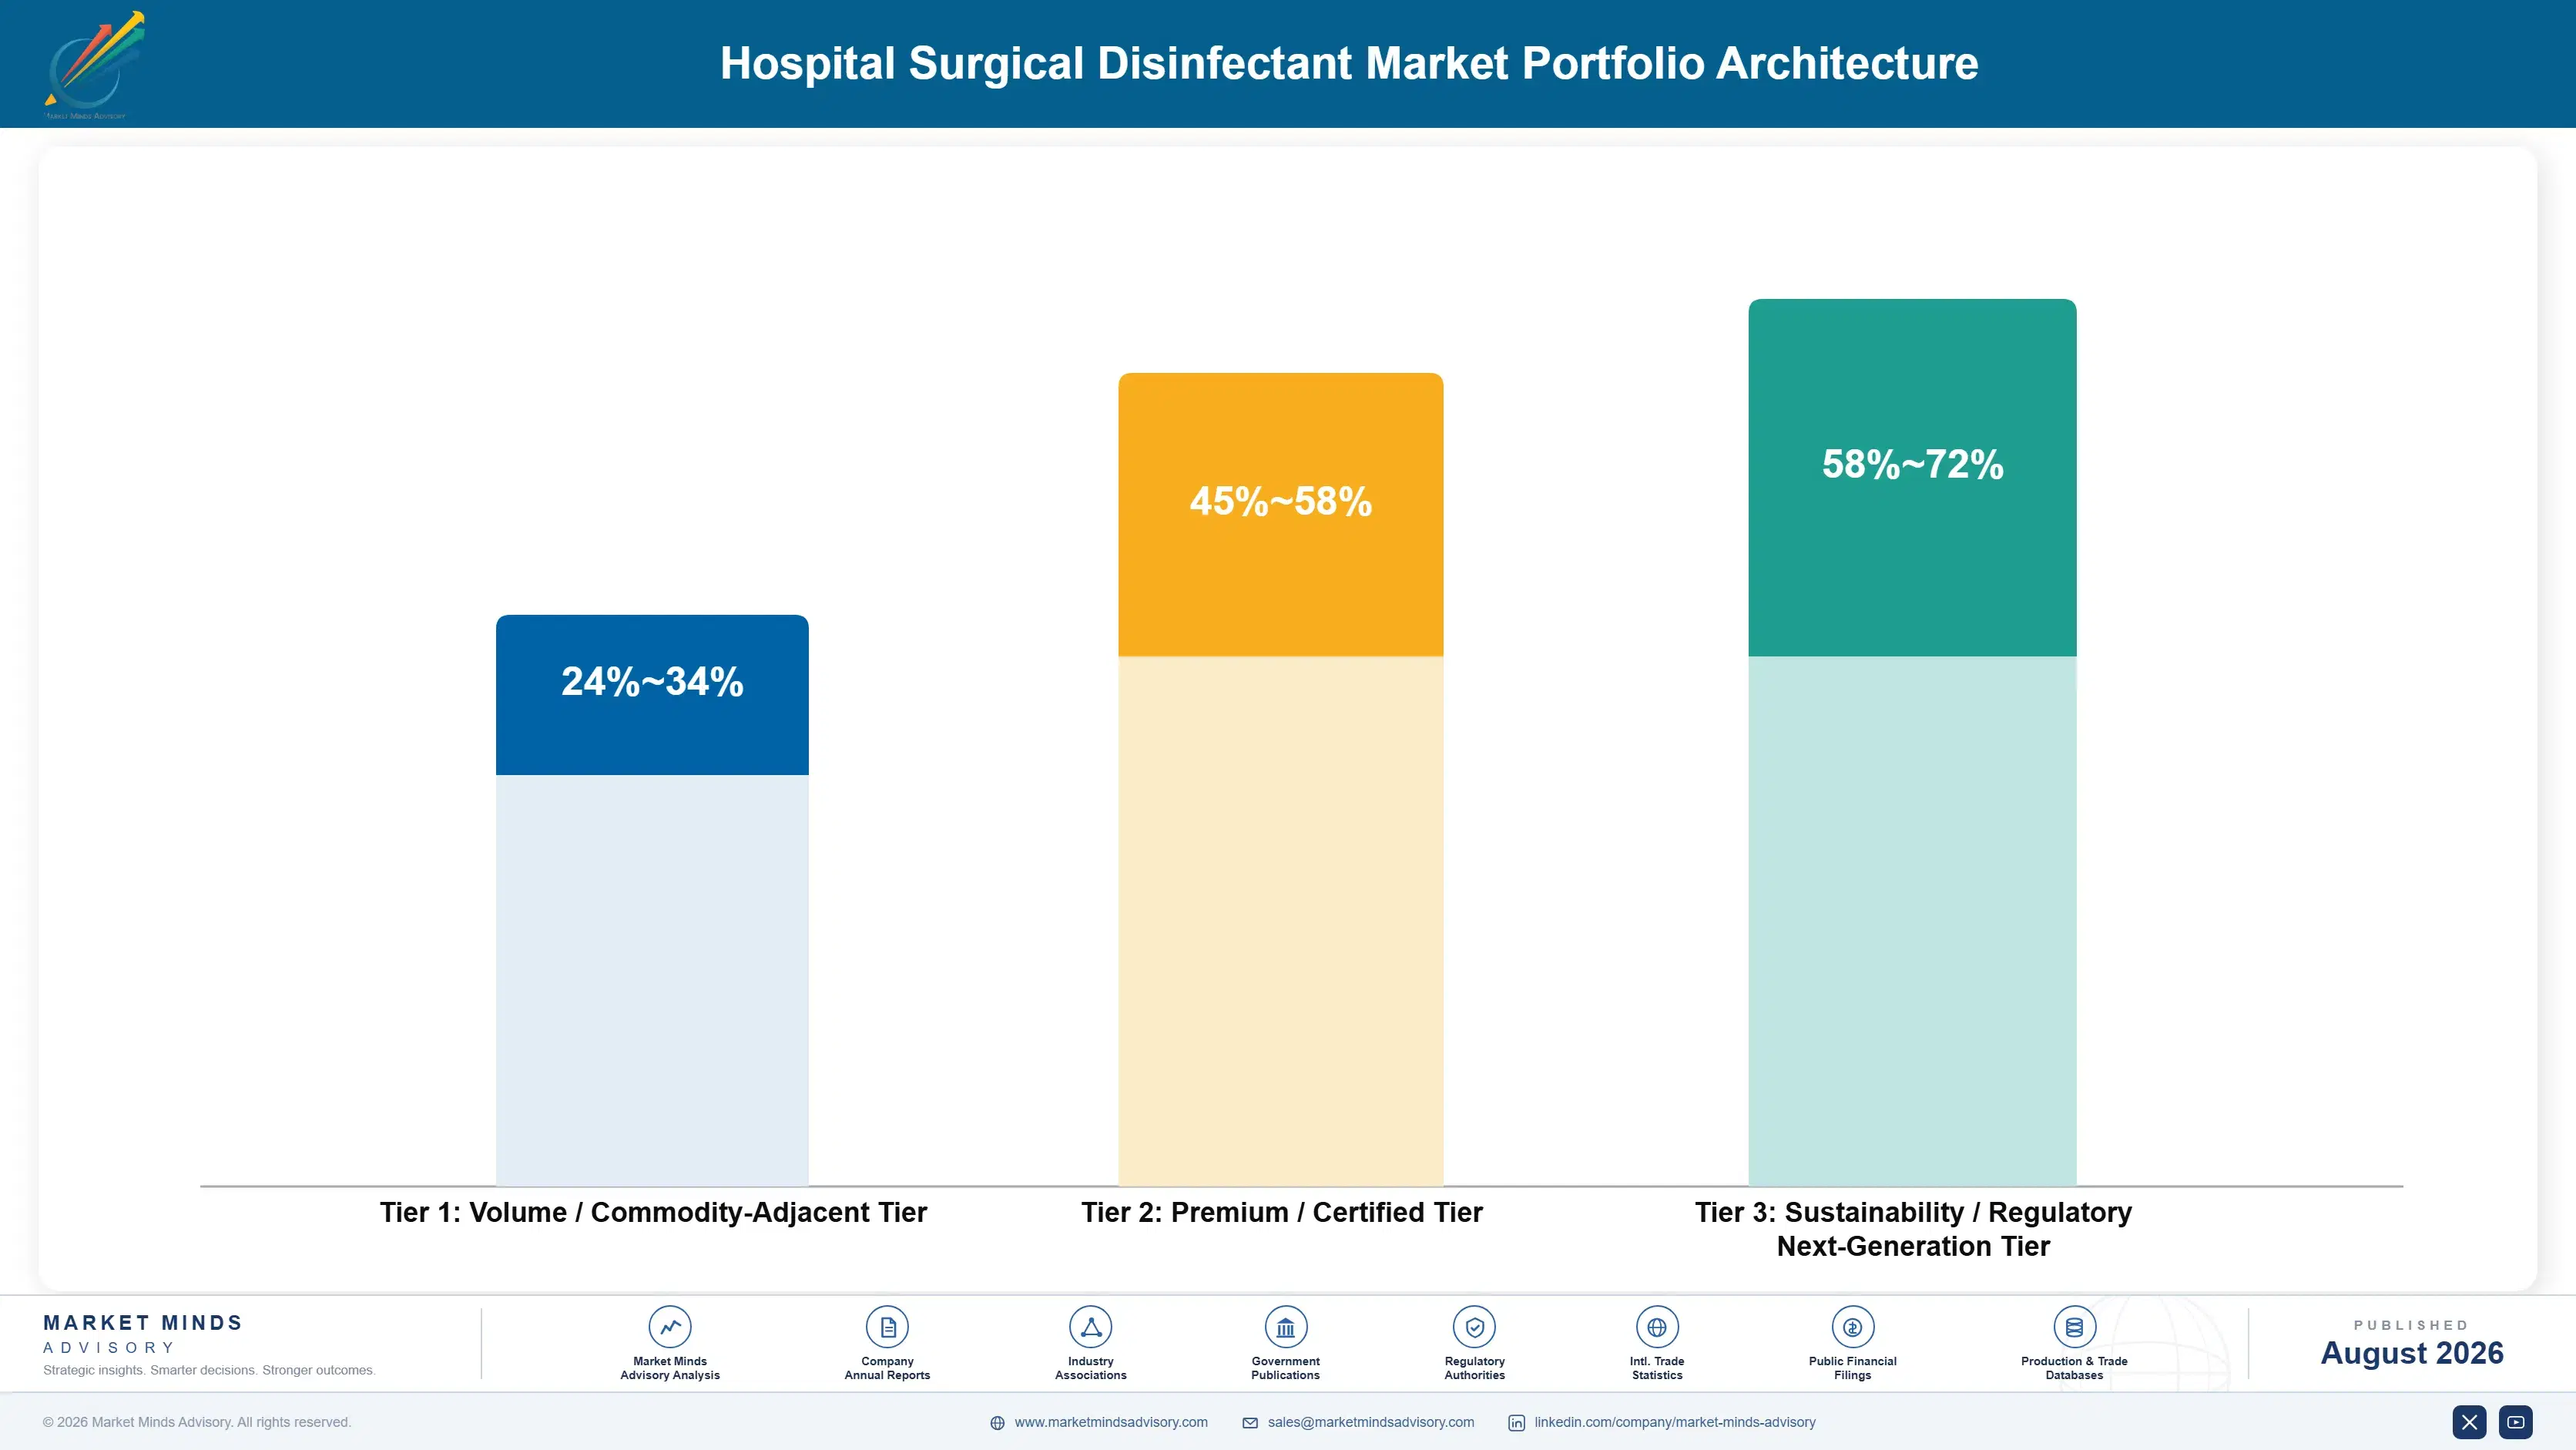
Portfolio Architecture for Margin Defence

Margin architecture follows how far a product sits from a tender document. Environmental surface disinfectants have converged on efficacy and are bought on price by purchasing organisations, earning commodity returns. Skin antiseptics earn considerably more because clinical guidelines and protocol committees govern selection. High-level disinfectants tied to validated endoscope compatibility earn the most, since the barrier is manufacturer validation rather than anything a competitor can price a
The volume versus premium tension runs along the same line. Surface disinfectants supply the largest volume by a wide margin and the thinnest margin, and they are the products purchasing organisations understand best. The premium sits in categories where a clinical committee retains an effective veto over procurement, and purchasing organisations have spent a decade steadily extending tendering into exactly those categories.

High-value pools concentrate where switching carries a risk somebody has to sign for. An endoscope reprocessing chemistry change requires validation, revalidation of the machine and acceptance of warranty implications on expensive instruments. A surgical skin antiseptic change requires guideline review and surgeon agreement. A surface wipe change requires nothing at all, which is precisely why that category has been commoditised first and most completely.

Volume / Commodity-Adjacent Tier

Environmental surface disinfectants and general theatre cleaning chemistry, where quaternary ammonium and hypochlorite products meet identical efficacy claims and purchasing organisations tender on delivered price. Chinese and Indian manufacturers set the cost floor in their own domestic systems.
Gross Margin: 24-34%

Premium / Certified Tier

Surgical skin antiseptics and hand preparation products, where clinical guidelines, protocol committees and applicator design protect selection from pure price competition. Chlorhexidine alcohol preparations command the strongest position on comparative evidence.
Gross Margin: 45-58%

Sustainability / Regulatory / Next-Generation Tier

Oxidising high-level disinfectants tied to validated endoscope compatibility and automated reprocessing systems, protected by manufacturer validation lists and equipment lock-in. Best margins in the market and the position least exposed to tender pressure.
Gross Margin: 58-72%
hospital-surgical-disinfectant-market-portfolio-architecture-1787303499497

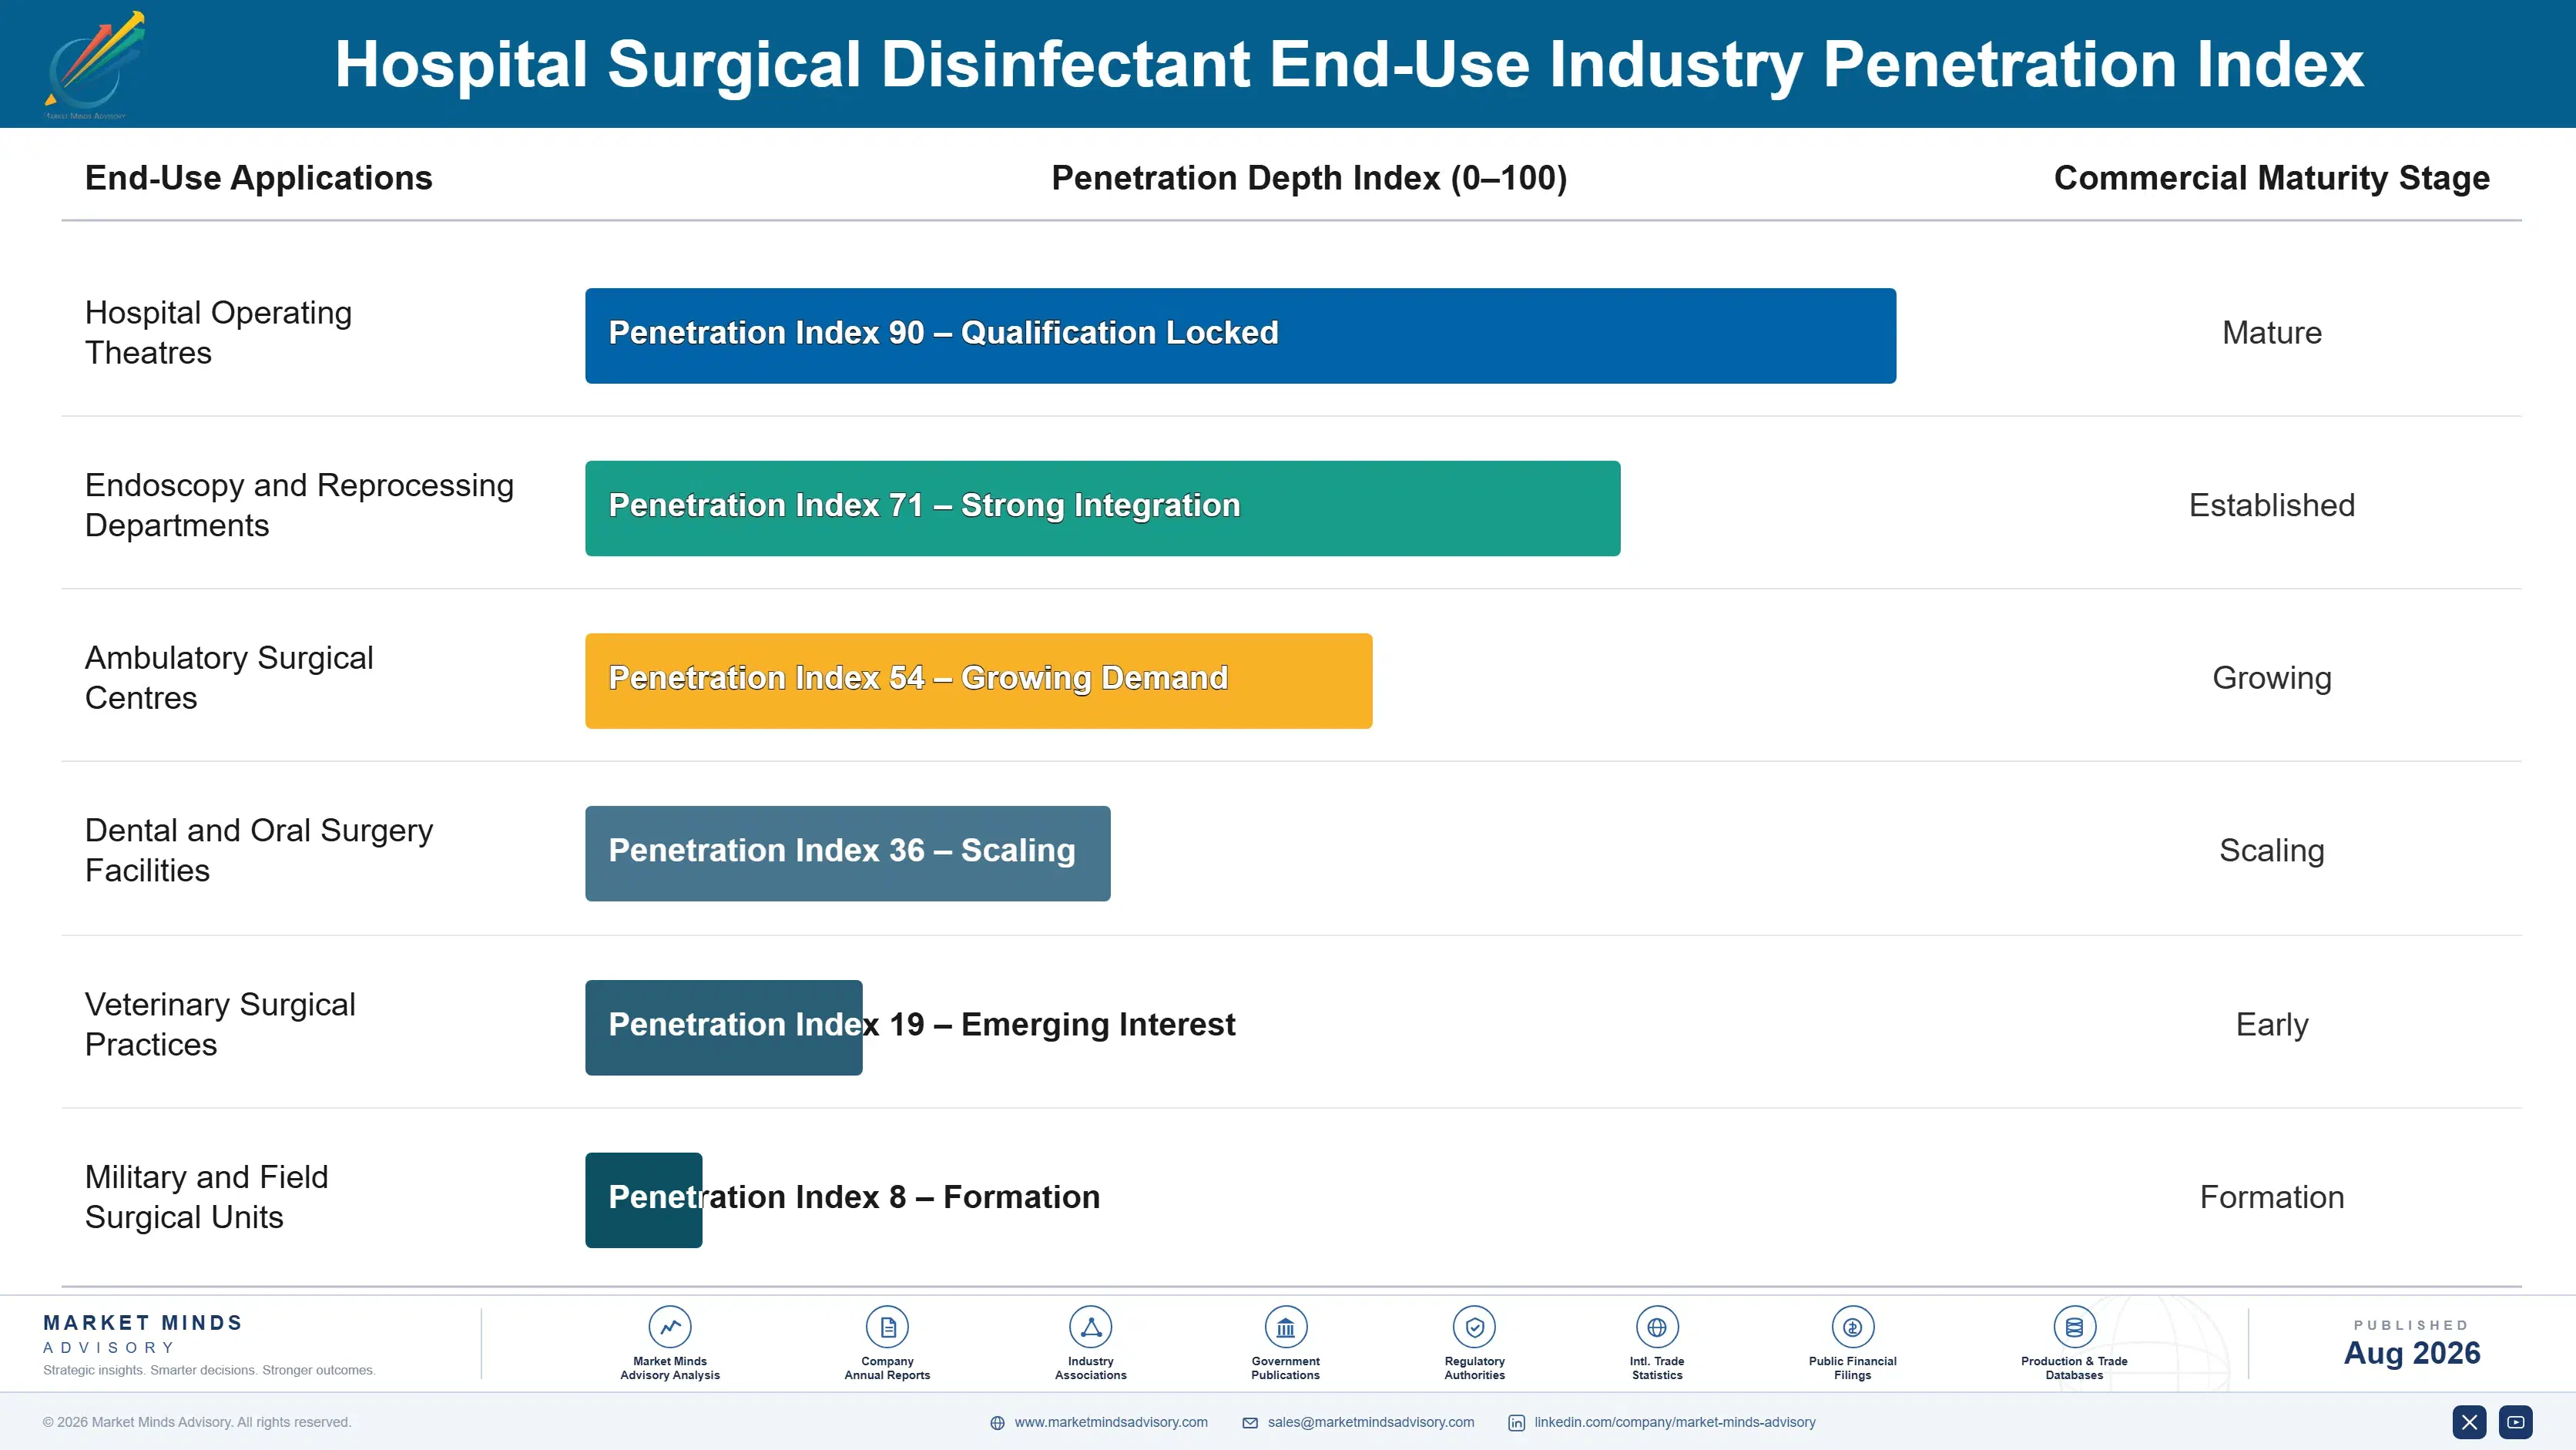
Consumable Demand Across Procedure Volume

Demand here tracks surgical activity almost mechanically. Every procedure consumes skin preparation, hand antisepsis, instrument processing chemistry and theatre turnover cleaning, whatever the operation involves, so consumption follows theatre schedules rather than any purchasing decision. Roughly 330 million procedures happen annually and the figure grows each year. That makes forecasting unusually reliable and it also means no supplier grows by persuading hospitals to use more.
Stickiness varies enormously by application. Endoscope reprocessing chemistry is the stickiest position in the market, because changing it means machine revalidation and warranty exposure on instruments worth tens of thousands each. Skin antiseptic selection sits with protocol committees and changes only when guidelines do, which is slow but not immovable. Surface disinfectants show almost no stickiness at all and change hands at every tender renewal without anyone in the hospital noticing.

Buyer profiles have shifted decisively toward procurement. A decade ago infection prevention nurses and theatre managers effectively chose products and finance approved them afterwards. Today purchasing organisations and consolidated system contracts decide most categories, with clinical committees retaining a veto that is narrowing year by year. Suppliers who kept only clinical relationships have found themselves excluded from tenders they never knew were running.
hospital-surgical-disinfectant-market-end-use-penetration-index-1787303500008

Where Disinfectant Strategy Must Land

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / COMPATIBILITY VALIDATION PRIORITY

Scope validation matters more than any efficacy claim

Endoscope manufacturers validate a limited list of compatible chemistries and their warranty coverage follows that list exactly, so hospitals simply will not use an unvalidated agent whatever its microbiological performance data happens to show. Only about four chemistries currently hold broad validation across the major scope platforms, which is a genuine barrier having nothing to do with the disinfectant itself. Suppliers who funded multi-cycle compatibility work early now hold reprocessing positions that straightforward price competition has proved quite unable to dislodge anywhere.
02 / EQUIPMENT PLACEMENT ECONOMICS

Place the reprocessor and the chemistry follows for years

Automated endoscope reprocessors and wall-mounted dispensing systems accept only specific concentrate formats, committing a hospital to a single chemistry across an equipment working life of seven years or more. Consumables represent roughly 85% of lifetime contract value, which makes placing that equipment at aggressive discount entirely rational rather than reckless. The discipline required is entirely contractual rather than financial, because hospitals that accept discounted equipment and then tender the chemistry separately dismantle the whole arrangement that justified giving the discount.
03 / CLINICAL RELATIONSHIP DEFENCE

Purchasing organisations keep tendering categories clinicians once protected

Competitive tendering has moved steadily upward from environmental surface products into surgical skin antiseptics, and each category crossing that line loses roughly twenty margin points without ever once recovering them afterwards. Clinical committees still retain a veto over product selection that narrows every single year as purchasing consolidation continues advancing across every developed market tracked in this report. Suppliers who maintained only clinical relationships have repeatedly found themselves excluded from tender processes they had no idea were even running until afterwards.
04 / OCCUPATIONAL TRANSITION TIMING

Regulation not efficacy is removing aldehyde chemistry entirely

Glutaraldehyde and ortho-phthalaldehyde both work perfectly well and are disappearing from hospitals anyway, because occupational exposure limits have tightened steadily and staff sensitisation claims have proved expensive to defend. Aldehyde chemistry now covers only about 11% of global high-level disinfection volume, and that share keeps falling steadily wherever occupational exposure enforcement is genuinely active. Suppliers should therefore be tracking occupational regulation timetables rather than clinical guidelines, since the former is what actually determines when each individual national market finally converts.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Hospital Surgical Disinfectant Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Hospital Surgical Disinfectant Exposure Evaluation 2025-26
CLIENT PROFILE
A European specialty disinfectant manufacturer supplying hospital environmental surface products and surgical hand preparation across Western and Eastern European markets, with annual revenue of approximately USD 190 million (client-reported, unverified by MMA). Roughly 65% came from environmental surface disinfectants sold through national hospital tenders. The company held no high-level disinfection products and no endoscope manufacturer validation of any kind.
STRATEGIC CHALLENGE
Tendered surface disinfectant pricing had eroded for four consecutive years while hydrogen peroxide and chlorhexidine active costs rose, compressing margin from both directions at once. The board wanted to know whether to defend surface tender share through cost reduction, or to invest in developing an oxidising high-level disinfection range for a reprocessing market where it had no validation and no established customer relationships.
MMA APPROACH
MMA conducted 47 expert interviews across hospital infection prevention leads, reprocessing department managers, procurement officers, endoscope manufacturer technical staff and occupational health regulators in six countries. A quantitative survey of 3,800 respondents established product selection authority and switching behaviour by application. We then modelled margin and share outcomes for both options against observed tender erosion rates and the aldehyde displacement timetable in each national market.
KEY FINDINGS
  1. Reprocessing department managers in every market surveyed refused to consider any chemistry lacking endoscope manufacturer validation, and none regarded competitive efficacy data as a substitute for that validation.
  2. Surface disinfectant tender pricing had eroded consistently for four years and procurement officers expected the pattern to continue, with none anticipating any reversal on efficacy or service grounds.
  3. Aldehyde displacement in Eastern European markets trailed German and Nordic timing by roughly four years, leaving a conversion window the client's existing distribution relationships could genuinely reach.
  4. Multi-cycle compatibility validation across the major endoscope platforms was estimated at eighteen to twenty-four months and a cost the client could fund without external financing.
RECOMMENDED STRATEGY
Phase 1: Phase one: begin endoscope manufacturer compatibility validation immediately for a peracetic acid formulation, ahead of any commercial launch activity or customer announcement. Phase 2: Phase two: hold surface tender share on cost reduction alone rather than investment, treating that business as cash generation rather than as a growth platform. Phase 3: Phase three: launch the validated high-level range into Eastern European markets first, where aldehyde conversion is still ahead rather than behind.
OUTCOME
The client began compatibility validation and completed it across two major scope platforms within twenty months, at approximately USD 12 million (client-reported, unverified by MMA). Surface disinfectant revenue continued declining as expected, while the high-level range reached its first Polish and Czech hospital contracts and carried gross margins roughly double the surface business.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Hospital Surgical Disinfectant Market?

The global hospital surgical disinfectant market was valued at USD 4.6 billion in 2025, covering surgical site antisepsis, hand preparation, instrument and endoscope high-level disinfection, and theatre surface disinfection. Disinfectant represents under one per cent of procedure cost.

How large will the Hospital Surgical Disinfectant Market be by 2036?

MMA forecasts the market at USD 8.73 billion by 2036, expanding 1.79 times from the 2026 base of USD 4.88 billion. That represents roughly USD 3.85 billion of incremental value across the forecast decade.

What is the CAGR for the Hospital Surgical Disinfectant Market 2026 to 2036?

The base case compound annual growth rate is 6.0%, with a bull case of 7.2% and a bear case of 4.8%. The bull case assumes accelerated aldehyde restriction across European and Asian occupational regulation.

Which segment is growing fastest?

Oxidising agent formulations grow at 9.0%, a full 1.50x the overall market rate. Peracetic acid and hydrogen peroxide are absorbing the volume that occupational regulation is removing from aldehyde chemistry.

Who are the major companies in the Hospital Surgical Disinfectant Market?

Ecolab, STERIS, 3M, Becton Dickinson and Solenis together hold 44% of revenue. Ecolab leads through chemical service contracts while STERIS leads through reprocessing equipment that determines which chemistry hospitals can run.

Which country is growing fastest?

India grows fastest at 9.6%, driven by private hospital theatre expansion and formalising infection prevention protocols. South Asia and Pacific is the fastest region overall at 8.2%.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Active Chemistry

  • Chlorhexidine Gluconate Formulations
  • Povidone-Iodine Formulations
  • Alcohol-Based Formulations
  • Quaternary Ammonium Compounds
  • Oxidising Agent Formulations
  • Aldehyde-Based Agents

By End-Use Industry

  • Hospital Operating Theatres
  • Endoscopy and Reprocessing Departments
  • Ambulatory Surgical Centres
  • Dental and Oral Surgery Facilities
  • Veterinary Surgical Practices
  • Military and Field Surgical Units

By Commercial Dimension

  • Group Purchasing Organisation Contracts
  • National Hospital Tender Programmes
  • Direct Hospital Supply Agreements
  • Chemical Service and Dispensing Contracts
  • Equipment-Linked Consumable Agreements
  • Distributor and Wholesaler Networks

By Region

  • East Asia
  • North America
  • Western Europe
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
This market comprises chemical disinfectant and antiseptic products supplied for use in hospital surgical and perioperative settings, measured at manufacturer revenue across tendered, contracted, service-linked and direct supply channels. Coverage spans surgical site skin antisepsis preparations including chlorhexidine gluconate and povidone-iodine formulations, surgical hand preparation products, instrument and flexible endoscope high-level disinfectants including peracetic acid, hydrogen peroxide and aldehyde chemistries, operating theatre environmental surface disinfectants including quaternary ammonium and hypochlorite products, and the concentrate formats supplied for automated endoscope reprocessing systems. Terminal sterilisation equipment and its consumables, general ward and non-surgical facility cleaning chemicals, consumer and retail antiseptics, wound care antimicrobial dressings, systemic antibiotic prophylaxis, laboratory disinfectants, and water treatment biocides fall outside scope.
Quantitative Units
USD billions (current prices); consumption volumes by active chemistry; disinfectant cost per surgical procedure; surgical procedure counts by region; installed reprocessing equipment base
Segmentation Dimensions
By Active Chemistry; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
East Asia, North America, Western Europe, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
China, Japan, South Korea, Taiwan, United States, Canada, Mexico, Germany, France, United Kingdom, Italy, Spain, Netherlands, Sweden, Denmark, India, Australia, Singapore, Malaysia, Thailand, Indonesia, Brazil, Argentina, Chile, Colombia, Saudi Arabia, United Arab Emirates, South Africa, Poland, Czechia, Hungary, Romania, and additional markets relevant to hospital infection prevention supply
Key Companies Profiled
Ecolab, STERIS, 3M, Becton Dickinson, Solenis, Reckitt Benckiser, Getinge, B. Braun, Schülke & Mayr, Medline Industries, Cardinal Health, PAUL HARTMANN, Metrex Research, Advanced Sterilization Products, Whiteley Corporation, Contec Inc., Certol International, Nice-Pak Products, Shanghai Likang Disinfectant, Lionser Medical
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-CHM-101
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Hospital Surgical Disinfectant Market Report (2026 to 2036).

The full MMA report examines a market where a trivially cheap consumable carries disproportionate infection liability, and traces how that asymmetry has protected pricing against a decade of purchasing consolidation. It sizes six active chemistries and seven regions to 2036, modelling surgical procedure volumes, per-procedure consumption and tender pricing separately so that volume and value can be distinguished. Competitive assessment covers twenty suppliers on one consistent revenue basis. Input cost exposure is traced through chlorhexidine active sourcing, hydrogen peroxide production economics and stabilised packaging requirements. Four commercial levers and a strategic verdict close the report, grounded in 47 expert interviews and a 3,800-respondent survey.
Six active chemistries sized separately to 2036
Aldehyde displacement timetable mapped by occupational jurisdiction
Endoscope compatibility validation barriers assessed across platforms
Twenty suppliers assessed on one consistent basis
Purchasing organisation tender expansion modelled by category
Anonymised client engagement with tested strategic recommendations

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts