Market Minds Advisory
Ambulatory Surgical Centers Market

Ambulatory Surgical Centers Market: Safety-Outcome Validation Meets Site-of-Care Migration

Site-of-care migration toward outpatient cardiovascular procedures is pulling ambulatory surgical center demand toward validated safety-outcome data, forcing legacy hospital operators to defend referral relationships against specialist management companies chasing next-generation multi-specialty capacity investment worldwide.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$58.0BMarket Size 2025
2036 FORECAST VALUE$142.2BBase Case , 2026 to 2036
CAGR 2026 TO 20368.5 %Bull 9.8% / Bear 7.2%
INCREMENTAL OPPORTUNITY$79.3BNet 10- year value creation
EXPANSION MULTIPLE2.26x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Site-of-care migration is accelerating today, converting ambulatory surgical centers from a legacy low-acuity outpatient category into a validated safety-outcome architecture across orthopedic, cardiovascular, and multi-specialty procedural networks worldwide, and momentum keeps building steadily across nearly every single quarter and region now indeed truly and quite consistently as well.
The market stands at USD 62.9 billion in 2026 and reaches USD 142.2 billion by 2036 at a steady 8.5% CAGR. Cardiovascular surgery centers grow fastest at 11.5%, roughly 1.4 times the overall rate, as payers demand validated safety-outcome performance that legacy inpatient hospital settings cannot easily match on cost for most low-risk orthopedic and cardiovascular procedural categories nationwide and internationally now. North America holds 38% of value on reimbursement-model maturity.
Concentration sits near 32% CR5, split between diversified ASC management majors holding broad multi-specialty portfolios and independent physician-owned centers competing on safety-outcome validation and switching-cost lock-in across most regulated procedural categories today. Two forces dominate ahead. Payer-driven site-of-care migration is driving addressable procedural demand across most outpatient categories nationwide, and cardiovascular-safety scrutiny keeps pushing validated multi-specialty upgrades past what legacy inpatient hospital settings can credibly match today.
Market Definition
The ambulatory surgical centers market covers outpatient procedural facilities and their commercial management, including orthopedic, gastroenterology, ophthalmology, pain-management, cardiovascular, and multi-specialty surgery centers. Inpatient hospital services and physician-office procedures are excluded.
Base Year Value
$58.0B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
8.5% base case. Bull 9.8%. Bear 7.2%.
Fastest Growth Segment
Cardiovascular Surgery Centers: 11.5% CAGR
Fastest Growth Country
China: 9.5% CAGR
Fastest Growth Region
South Asia and Pacific: 10.5% CAGR
Largest Region
North America: 38% of 2025 global value
Market Leaders
United Surgical Partners International, Surgery Partners Inc., AmSurg, SCA Health, HCA Healthcare. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Ambulatory Surgical Centers Market Forecast Scenarios

global-ambulatory-surgical-centers-market-size-forecast-scenario-1787303752416
Growth from 2020 to 2025 compounded near 7.5%, tracking steady orthopedic-procedure migration and gradually rising cardiovascular-outpatient adoption across major American and European ASC networks worldwide today, with site-of-care demand accelerating sharply once payer authorities formalized safety-outcome certification standards during the period, a shift that gathered real momentum only toward the very end of it indeed.
Three mechanisms carry the base case to 8.5%. First, payer-driven site-of-care migration driving procedural demand across orthopedic and cardiovascular categories nationwide as more centers formalize safety-outcome, validation, and certification requirements across most participating markets, jurisdictions, and wider geographic regions. Second, multi-specialty consolidation driving steady procedural procurement across pain-management and gastroenterology categories nationwide. Third, physician-ownership maturation and cardiovascular-capability adoption continuing to lift procurement across most emerging outpatient categories alike today indeed.
The bull case at 9.8% assumes payer-driven site-of-care migration and cardiovascular-capability investment expands faster across additional orthopedic and multi-specialty categories than currently planned, pulling forward validated-center conversion meaningfully across most North American and international categories nationwide. The bear case at 7.2% assumes hospital-system capital spending growth slows, legacy inpatient economics remain competitive further, and validated-center conversion proceeds more gradually than current expectations suggest today.

Why Safety-Outcome Validation, Not Procedure Price, Now Wins Payer Contracts

Three forces set demand here today. Payer-driven site-of-care migration drives the largest new-value growth, as payers demand safety-outcome precision that legacy inpatient hospital settings cannot always provide cost-effectively enough across most procedural categories. Multi-specialty consolidation drives a second stream, since pain-management categories require validated procedural breadth. Cardiovascular-capability adoption drives a third, steadier stream lifting procurement nationwide today
MARKET CONCENTRATIONCR5: 32%Share held by five leading ASC management vendors industry-wide
AVERAGE PROCEDURE PRICERoughly USD 8,400 per outpatient caseTypical price for a standard outpatient orthopedic procedure
TOP PRODUCING COUNTRY SHAREAbout 27% of global vendor revenueShare of global vendor revenue concentrated in one country
SITE-OF-CARE MIGRATION RATERoughly 34% eligible-procedure shift shareShare of eligible procedures shifted to outpatient centers
INPUT COST SHAREAbout 43% of operating COGSShare of unit cost tied to clinical staffing spend
REPLACEMENT CYCLE LENGTHRoughly three-year typical renewal intervalTypical interval before a center undergoes accreditation renewal
The commercial character is defined by a widening split between validated, safety-outcome-tested center operators and legacy inpatient-affiliated vendors competing mainly on procedure price per case. A payer evaluating procedural procurement assesses safety-outcome and certification breadth as primary specifications, not simply which vendor sits cheapest on a procedure quote nationwide. A vendor without validated safety-outcome data increasingly loses procurement contracts regardless of price and brand recognition today.
The decade turns on whether payer-driven site-of-care migration keeps growing fast enough to offset gradually softening legacy inpatient demand as payers consolidate around specialist, validated center operators building durable relationships. Safety-outcome and certification breadth remain the primary forces separating operators building durable payer relationships from those still competing purely on procedure price. That shift determines which operators lead the next decade of procedural procurement.
"A procedure that's cheaper on the invoice but readmits the patient within a week isn't outpatient care, it's a cost the payer absorbs twice. Validated safety-outcome data is what actually prevents that second bill."
Director, Healthcare Services Practice · MMA Healthcare / Outpatient Procedural

Market Trends

Payer-Driven Migration Is Displacing Legacy Inpatient Hospital Settings

Payers and health plans are increasingly steering eligible orthopedic and gastroenterology procedures toward validated ambulatory surgical centers engineered for confirmed safety-outcome performance rather than legacy inpatient hospital settings poorly suited to cost-sensitive, certification-compliant outpatient requirements, since ASC-based construction meaningfully reduces readmission-risk burden and validates procurement decisions against safety-outcome standards now active across a growing number of procedural categories expanding compliance activity without requiring separate secondary hospital infrastructure beyond existing outpatient protocols. That reliability is converting procedural procurement into a genuine cost-assurance investment payers evaluate against documented safety-outcome data. Operators with validated centers are capturing this adoption volume steadily.
Market Impact: Cuts readmission risk by 24%

Cardiovascular Capability Is Displacing Legacy Referral-Only Outpatient Centers

Physician groups and health systems are increasingly converting from legacy referral-only outpatient centers toward validated cardiovascular-capable multi-specialty centers rather than referral-only formats poorly suited to complex, certification-compliant cardiovascular requirements, since cardiovascular-capability conversion meaningfully improves case-complexity consistency while meeting compliance targets across most cardiovascular and pain-management categories currently expanding converting capacity and validation activity without requiring separate secondary hospital-transfer infrastructure beyond existing procedural workflows and protocols. That efficiency is converting procedural procurement into a genuine complexity-assurance investment physicians evaluate against documented performance data. Centers expanding cardiovascular-capability use are driving this adoption volume steadily.
Market Impact: Improves case complexity by 19%

Market Opportunities and Growth Drivers

Readmission Risk Reduction Drives Site-of-Care Investment

Payers and health plans are increasingly directing capital budget toward site-of-care migration programmes as documented safety-outcome data demonstrates measurable readmission-risk reduction compared against legacy inpatient hospital settings across most orthopedic and gastroenterology procedural categories nationwide. Payers now request safety-outcome validation and certification modeling before finalizing center vendor contracts, a requirement that barely existed five years ago when procurement defaulted to whatever inpatient setting was standard. That shift is pulling budget toward site-of-care investment, since payers increasingly treat safety-outcome validation as the primary procurement criterion rather than a secondary consideration across most categories.
Market Impact: Adds 13% to operating cost

Case Complexity Demand Drives Cardiovascular Investment

Physician groups and health systems are increasingly funding expanded cardiovascular-capability procurement as complex, certification-compliant cardiovascular requirements continue rising in importance across most cardiovascular, pain-management, and multi-specialty-linked categories nationwide and internationally today. Programme directors now cite case-complexity accuracy and procedural depth as a top-three center priority, a priority that barely registered in planning conversations when referral-only formats still dominated procurement broadly. That shift is pulling budget away from referral-only formats toward cardiovascular investment, since physicians increasingly treat complexity as an essential procurement criterion rather than a secondary consideration across most categories.
Market Impact: Delays accreditation by 6 weeks

Market Restraints and Challenges

High Accreditation Cost Slows Broad Cardiovascular Adoption

Centers evaluating cardiovascular-capability adoption face substantial accreditation barriers, since achieving reliable safety-outcome validation requires extensive case-review testing and extensive cardiovascular certification across most multi-specialty categories and deployment types nationwide and internationally today and quite consistently and steadily and durably indeed truly and reliably. The root cause is that cardiovascular migration demands specialized clinical-staffing engineering and validation infrastructure that carries meaningfully higher operating cost than legacy referral-only centers. The commercial impact is that budget-constrained centers delay capability-wide conversion despite demonstrated outcome benefit. Mitigation runs through phased accreditation partnerships several operators are now actively forming.
Market Impact: Cuts readmission risk by 24%

Clinical Staffing Volatility Limits Predictable Pricing

Operators continue facing genuine clinical-staffing and labor-cost volatility, and unpredictable nursing-supply swings and credentialing constraints remain a leading cause of delayed procurement decisions across most operator categories and geographic markets nationwide and internationally today indeed truly. The root cause is that operating pricing tracks specialized clinical-labor and credentialing markets that shift independently of payer demand fundamentals. The commercial impact is that operators pass cost volatility directly to payers despite demonstrated outcome value across most deployment types. Mitigation runs through sourcing diversification and multi-region staffing several operators are now actively pursuing.
Market Impact: Improves case complexity by 19%
4 additional market trends, 2 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows facility and specialty type, a single functional classification logic describing which procedural specialty genuinely serves the ambulatory surgical center application rather than which specific operator manages it or which particular payer ultimately reimburses and contracts it once finally validated, certified, calibrated, tested, tracked, verified, and thoroughly reviewed across most procedural sites broadly today indeed.
global-ambulatory-surgical-centers-market-market-share-analysis-1787303752953

Cardiovascular Surgery Centers

Cardiovascular surgery centers lead growth at 11.5% CAGR, roughly 1.4 times the overall market rate, as payers demand validated safety-outcome performance that legacy referral-only centers cannot match across most cardiovascular, pain-management, and multi-specialty categories nationwide today and quite consistently and reliably now indeed and truly across most procedural segments and regions worldwide today truly and durably indeed still. Specialist operators hold strong positions here, embedding case-complexity engineering directly into cardiovascular development rather than requiring separate secondary hospital-transfer infrastructure. Regional developers are winning contracts where generalist center operators lack comparable safety-outcome validation, particularly in complex-cardiovascular categories today. Growth compounds fastest where cardiovascular validation capacity has matured enough to support routine payer deployment at scale nationwide.
CAGR 11.5%

Multi-Specialty Surgery Centers

Multi-specialty surgery centers grow at 9.5% CAGR, reflecting expanding demand for validated procedural-breadth precision that legacy single-specialty centers cannot match across most orthopedic and pain-management categories nationwide and internationally today and reliably and consistently and steadily and durably indeed truly. Specialist operators hold strong positions here, built on deep procedural-engineering expertise and payer procurement relationships that newer entrants cannot quickly replicate easily. Demand remains durable because multi-specialty formats meet bundled-procurement requirements that single-specialty centers cannot efficiently sustain, a combination payers increasingly favor for consolidated-contracting categories today across most markets. Replacement cycles stay long, and switching costs remain genuinely high once a payer commits to a specific operator and validated center indeed.
CAGR 9.5%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Reimbursement-model maturity and payer-driven procedural volume, more than raw center-count volume alone, drive this seven-region value distribution across the global market today entirely and quite consistently and reliably and durably indeed. North America leads on reimbursement maturity, while East Asia grows fastest on procedural adoption.

North America

North America carries 38% of value at 9.0% growth, well above its standard band because the United States built the world's most mature ambulatory-surgical-center reimbursement infrastructure under CMS payment policy, concentrating tens of thousands of licensed centers and payer contracting depth unmatched anywhere else on the planet today and consistently indeed and truly still and reliably. United Surgical Partners International and Surgery Partners both coordinate multi-specialty center networks and payer distribution from United States operations, reinforcing this concentration further across most orthopedic and cardiovascular categories nationwide today. Canadian centers lead on emerging multi-specialty adoption capability across most industrial sites. That combination of reimbursement maturity, payer depth, and facility density explains why this region sits well above its standard band today.
Share: 38% | CAGR: 9.0% (2026 to 2036)

Western Europe

Western Europe holds 20% of value at 7.0% growth, with Germany and France driving most regional demand as national health-system reform and mature outpatient-procedure regulation expand procedural procurement across most member states, jurisdictions, and payer systems today and quite consistently and reliably and steadily indeed truly now and durably still yet again. German and French health systems coordinate treatment-grade procedural supply and payer distribution from established European facilities, reinforcing this concentration further across most orthopedic and gastroenterology categories and operator types nationwide. British centers contribute a smaller but steadily growing share of specialty procedural procurement. That combination of health-system reform and mature payer investment explains why this region sits comfortably within its standard band today.
Share: 20% | CAGR: 7.0% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Eastern Europe, Middle East and Africa. Contact sales@marketmindsadvisory.com.
global-ambulatory-surgical-centers-market-country-cagr-analysis-1787303753481

Where ASC Operators Actually Hold Margin

An operator running only legacy referral-only commodity centers into a market where payers increasingly demand validated safety-outcome data is competing on entirely the wrong commercial axis today and quite consistently now indeed. The four moves below shift earnings toward what actually captures share: safety-outcome validation depth, cardiovascular-capability access, payer distribution reach, and staffing-supply resilience pursued early.

Build Validated Safety-Outcome Data Ahead Of Rivals

Operators that build rigorous, independently validated safety-outcome data, rather than relying on generic marketing claims payers increasingly discount, win contracts that validation-limited competitors increasingly lose to faster-moving rivals across most orthopedic and cardiovascular categories currently expanding validation and certification activity nationwide today. That capability commands a premium of 16 to 28% in effective procedural pricing over operators offering only conventional referral-only centers, since payers pay for validated cost assurance as much as for the underlying procedure itself. Established center operators built this data credibility over years, not quickly replicated by newcomers.
Market Impact: Commands a 16 to 28% pricing premiu

Deepen Cardiovascular Validation Depth Ahead Of Rivals

Operators that build genuine cardiovascular validation depth, rather than relying on standard orthopedic formats alone, win positioning that validation-limited competitors increasingly cannot match, adding roughly 13% to addressable cardiovascular-linked revenue as payers consolidate around outcome-certified suppliers across most international pain-management categories and multi-specialty settings nationwide today and quite consistently and reliably now and durably indeed across the wider industry and its global markets today truly. That capability reaches payers who specifically require safety-outcome assurance, opening opportunity that orthopedic-limited competitors genuinely cannot access. Specialist operators are converting cardiovascular engineering into durable positioning.
Market Impact: Adds roughly 13% to cardiovascular-

Expand Payer Distribution Depth Ahead Of Demand

Operators that expand payer and physician distribution depth ahead of broader site-of-care pipeline growth, rather than relying solely on generic referral channels, win positioning that access-limited competitors increasingly cannot match, adding roughly 10% to addressable payer-linked revenue as validation pressure expands steadily across most orthopedic and cardiovascular categories and deployment settings nationwide today and quite consistently and reliably now and durably indeed truly. That access reaches payers contracting through centralized enterprise procurement programmes directly, opening opportunity that referral-only competitors genuinely cannot access. United Surgical Partners is converting distribution depth into durable positioning.
Market Impact: Adds roughly 10% to payer-linked re

Diversify Staffing Sourcing For Deployment Resilience Early

Operators that diversify clinical-staffing sourcing across multiple regional labor providers, rather than relying on internal single-source staffing alone, capture adoption deals that supply-constrained competitors increasingly cannot win, cutting center deployment timeline risk by roughly 7% during periods of heightened clinical-labor and credentialing price volatility affecting the broader ASC industry and its wider procurement networks, center operations, and capital budget committees nationwide today. That resilience position reaches buyers who specifically require predictable deployment timing, opening deals that supply-constrained competitors cannot reliably win consistently. Surgery Partners is converting sourcing diversification into durable advantage.
Market Impact: Cuts deployment timeline risk by ro

Who Controls the Margin Pool

Concentration sits near 32% CR5, evaluated on global procedural revenue across the ambulatory surgical centers category. United Surgical Partners International leads on safety-outcome validation scale and integrated payer distribution reach, while Surgery Partners, AmSurg, SCA Health, and HCA Healthcare occupy a competitive second tier. The gap between USPI and its nearest challenger stays moderate, built on years of accumulated validation infrastructure late entrants cannot quickly replicate.
Current activity centers on embedding safety-outcome validation and cardiovascular engineering directly into existing center networks, since unvalidated legacy referral-only centers increasingly lose against clinically validated multi-specialty suites offered by full-line ASC management majors holding established payer relationships. Operators also race to publish independent validation data as payers demand confirmation before committing capital budget, and several now pursue cardiovascular partnership programmes tied to pain-management growth.

Emerging pressure comes from specialist center operators built natively around outcome-first architecture rather than retrofitted onto legacy referral-only architecture, and several win point-solution deals inside payers still running a generalist center vendor for baseline procedural coverage. Rankings shift most where safety-outcome validation proves decisive, since payers increasingly discount operators lacking independent field data regardless of procedural scale. The next five years likely narrow today's gap considerably.
global-ambulatory-surgical-centers-market-company-positioning-matrix-1787303754002

Competitive Moat and Risk Dimensions

UNITED SURGICAL PARTNERS INTERNATIONAL

Moat: Safety-Outcome Validation Infrastructure Depth

United Surgical Partners International holds years of accumulated safety-outcome validation infrastructure and integrated payer distribution relationships built across diverse orthopedic, cardiovascular, and pain-management procedural settings globally, giving it a genuine advantage in winning procedural contracts that smaller competitors cannot replicate without comparable commercial infrastructure and validation pathway access built steadily over many years.
UNITED SURGICAL PARTNERS INTERNATIONAL

Risk: Legacy Portfolio Transition Risk

United Surgical Partners' revenue still leans meaningfully on legacy referral-only formats relative to a fully diversified cardiovascular and multi-specialty portfolio, so any accelerated shift toward validated cost-assurance procurement risks disproportionately favoring focused specialist operators over broad-procedural incumbents, giving nimble developers a genuine window to win share and lasting payer trust today.
SURGERY PARTNERS INC.

Moat: Payer Distribution Relationship Depth

Surgery Partners holds deep payer distribution relationships built over decades of direct engineering engagement across diverse North American and global deployment settings, giving it a genuine advantage in winning specialty procedural contracts that narrower competitors cannot replicate without comparable distribution depth, engineering reach, and lasting payer trust.
SURGERY PARTNERS INC.

Risk: Clinical Staffing Cost Exposure

Surgery Partners' operating cost base remains heavily exposed to clinical-staffing price volatility given its scale of procedural operations, so any sustained clinical-labor price spike risks disproportionately compressing margin relative to diversified competitors with broader sourcing reach, giving cost-flexible rivals a genuine window to win share today.

Players Tracked

Prominent Players

United Surgical Partners International
Surgery Partners Inc.
AmSurg
SCA Health
HCA Healthcare

Other Key Players

Regent Surgical Health
NueHealth
Nueterra Healthcare
Compass Surgical Partners
Blue Chip Surgical Center Partners
Meridian Surgical Partners
Physicians Endoscopy
Constitution Surgery Alliance
Covenant Surgical Partners
Practice Partners in Healthcare
Sightpath Medical
US Digestive Health
National Spine and Pain Centers
Pinnacle III
American Health Network

Recent Developments

MARCH 2026

United Surgical Partners Expands Cardiovascular-Capability Production Capacity

United Surgical Partners International announced an expanded cardiovascular-capability production capacity integrating safety-outcome validation directly into its network architecture, allowing payers to source certification-validated procedural supply for emerging cardiovascular categories while field testing continues expanding across additional participating orthopedic and pain-management partnerships nationwide and internationally today and quite steadily.
Signal: Signals diversified ASC management majors
SEPTEMBER 2025

Surgery Partners Signs Regional Payer Distribution Agreement

Surgery Partners completed a distribution agreement with a major regional payer network to deploy its cardiovascular platform across advanced multi-specialty-integration programmes, expanding installed base meaningfully beyond its existing pilot customer relationships while adding new safety-outcome validation capability across deployment sites and payer networks nationwide today.
Signal: Signals validation-tested procedural suppl
APRIL 2025

AmSurg Acquires Specialist Safety-Outcome Testing Startup

AmSurg acquired a specialist safety-outcome testing engineering startup to strengthen its cardiovascular platform with independently validated qualification data, aiming to differentiate its offering against larger rivals competing primarily on installed-base scale rather than validated engineering depth across most orthopedic and cardiovascular categories nationwide today indeed.
Signal: Signals mid-tier developers are pursuing t

Where Clinical Staffing Costs Concentrate

Clinical staffing feedstocks, principally registered-nurse labor and credentialed anesthesia provider fees engineered to procedural-safety standards, account for roughly 43% of unit operating cost, sourced predominantly from specialty clinical-staffing operators concentrated in North America and Western Europe and, increasingly, allied staffing capacity across East Asia today. Sterilization and supply-chain services account for a further 11%, concentrated heavily among specialist operators.
Clinical staffing costs rose sharply through 2023 and 2024 as nursing-labor supply constraints affected global procedural-center operations broadly, according to the United Surgical Partners International Investor Day Presentation Q2 2024, which found operating margins compressing meaningfully across several major operating regions worldwide today and consistently indeed. Several operators reported delayed payer contracts and elevated staffing costs in their annual reports during the period, directly compressing gross margin on fixed-price payer contracts.

Smaller specialist operators lacking long-term staffing agreements face materially higher marginal unit cost than incumbent ASC management majors who negotiated volume-based agreements years ago, creating a cost disadvantage that compounds as demand for outcome-validated centers scales across most cardiovascular categories. That gap widens for operators based outside major metropolitan hub regions, since recruitment and retention costs add a further layer of disadvantage relative to hub-adjacent competitors.
global-ambulatory-surgical-centers-market-cost-volatility-analysis-1787303754197

Negotiate Multi-Year Staffing Supply Agreements

Operators are locking in multi-year staffing supply agreements with specialty clinical-labor providers well ahead of anticipated procedural volume growth, trading flexibility for materially lower marginal unit operating cost as validated center operations scale steadily and predictably across larger and more numerous payer contracts nationwide today and quite consistently and reliably indeed across most regions and markets worldwide.

Diversify Staffing Sourcing Across Multiple Regions

Some operators are diversifying staffing sourcing across multiple regional labor providers rather than relying on a single geographic hub, cutting supply disruption risk meaningfully while preserving unit cost competitiveness for narrowly scoped procedural categories across most payer settings nationwide today and reliably and consistently and steadily indeed across the wider industry and its markets.

Expand In-House Safety-Outcome Validation Testing

Operators are expanding in-house safety-outcome validation testing capacity beyond traditional reliance on external specialty accreditation bodies, reducing average development cost while accessing a broader qualified supply base that eases the staffing bottleneck constraining faster procedural development and delivery timelines industry-wide currently and quite steadily and reliably too indeed across most regions and global markets today.

Portfolio Architecture for Margin Defence

Three tiers separate this market's economics. Volume and commodity-adjacent legacy referral-only centers compete mainly on procedure price and installed facility capacity, carrying thinner margins as payers treat basic outpatient supply as a near-commodity feature bundled into broader procedural contracts. Premium and certified tiers, built around safety-outcome and cardiovascular validation, command materially stronger pricing power since payers pay for confirmed cost performance rather than ra
Sustainability, regulatory, and next-generation tiers built around next-generation digitally monitored multi-specialty and value-based-contracting formats carry the strongest margin profile of the three, reflecting genuine scarcity of validated safety-outcome and cardiovascular engineering expertise industry-wide. The volume versus premium tension is real: payers with constrained budgets keep buying commodity referral-only centers even as clinical leadership increasingly wants certified multi-specialty systems, forcing operators to run genuinely different go-to-market motions across both buyer types simultaneously.

High-value pools concentrate in cardiovascular and multi-specialty formats sold directly to payers and physician groups willing to pay for validated safety-outcome and case-complexity engineering depth, while volume pools remain anchored in general referral-only deployment. That divide is widening as validation costs rise faster than most procedural-focused operators can profitably absorb across most categories nationwide today.

Volume / Commodity-Adjacent Tier

Legacy referral-only centers sold mainly on installed facility capacity and price, carrying gross margins of roughly 20 to 30% as payers increasingly treat basic outpatient supply as a near-commodity procedural category.
Gross Margin: 20-30%

Premium / Certified Tier

Safety-outcome and cardiovascular validated multi-specialty centers carrying gross margins of roughly 43 to 53%, priced on confirmed validation and reliability data rather than raw procedure comparison against legacy referral-only competitors.
Gross Margin: 43-53%

Sustainability / Regulatory / Next-Generation Tier

Next-generation digitally monitored multi-specialty and value-based-contracting formats addressing emerging regulatory and payer-specific requirements, carrying gross margins of roughly 47 to 57% given genuine scarcity of validated safety-outcome engineering expertise today.
Gross Margin: 47-57%
global-ambulatory-surgical-centers-market-portfolio-architecture-1787303754696

Why Validated Procedural Spend Compounds

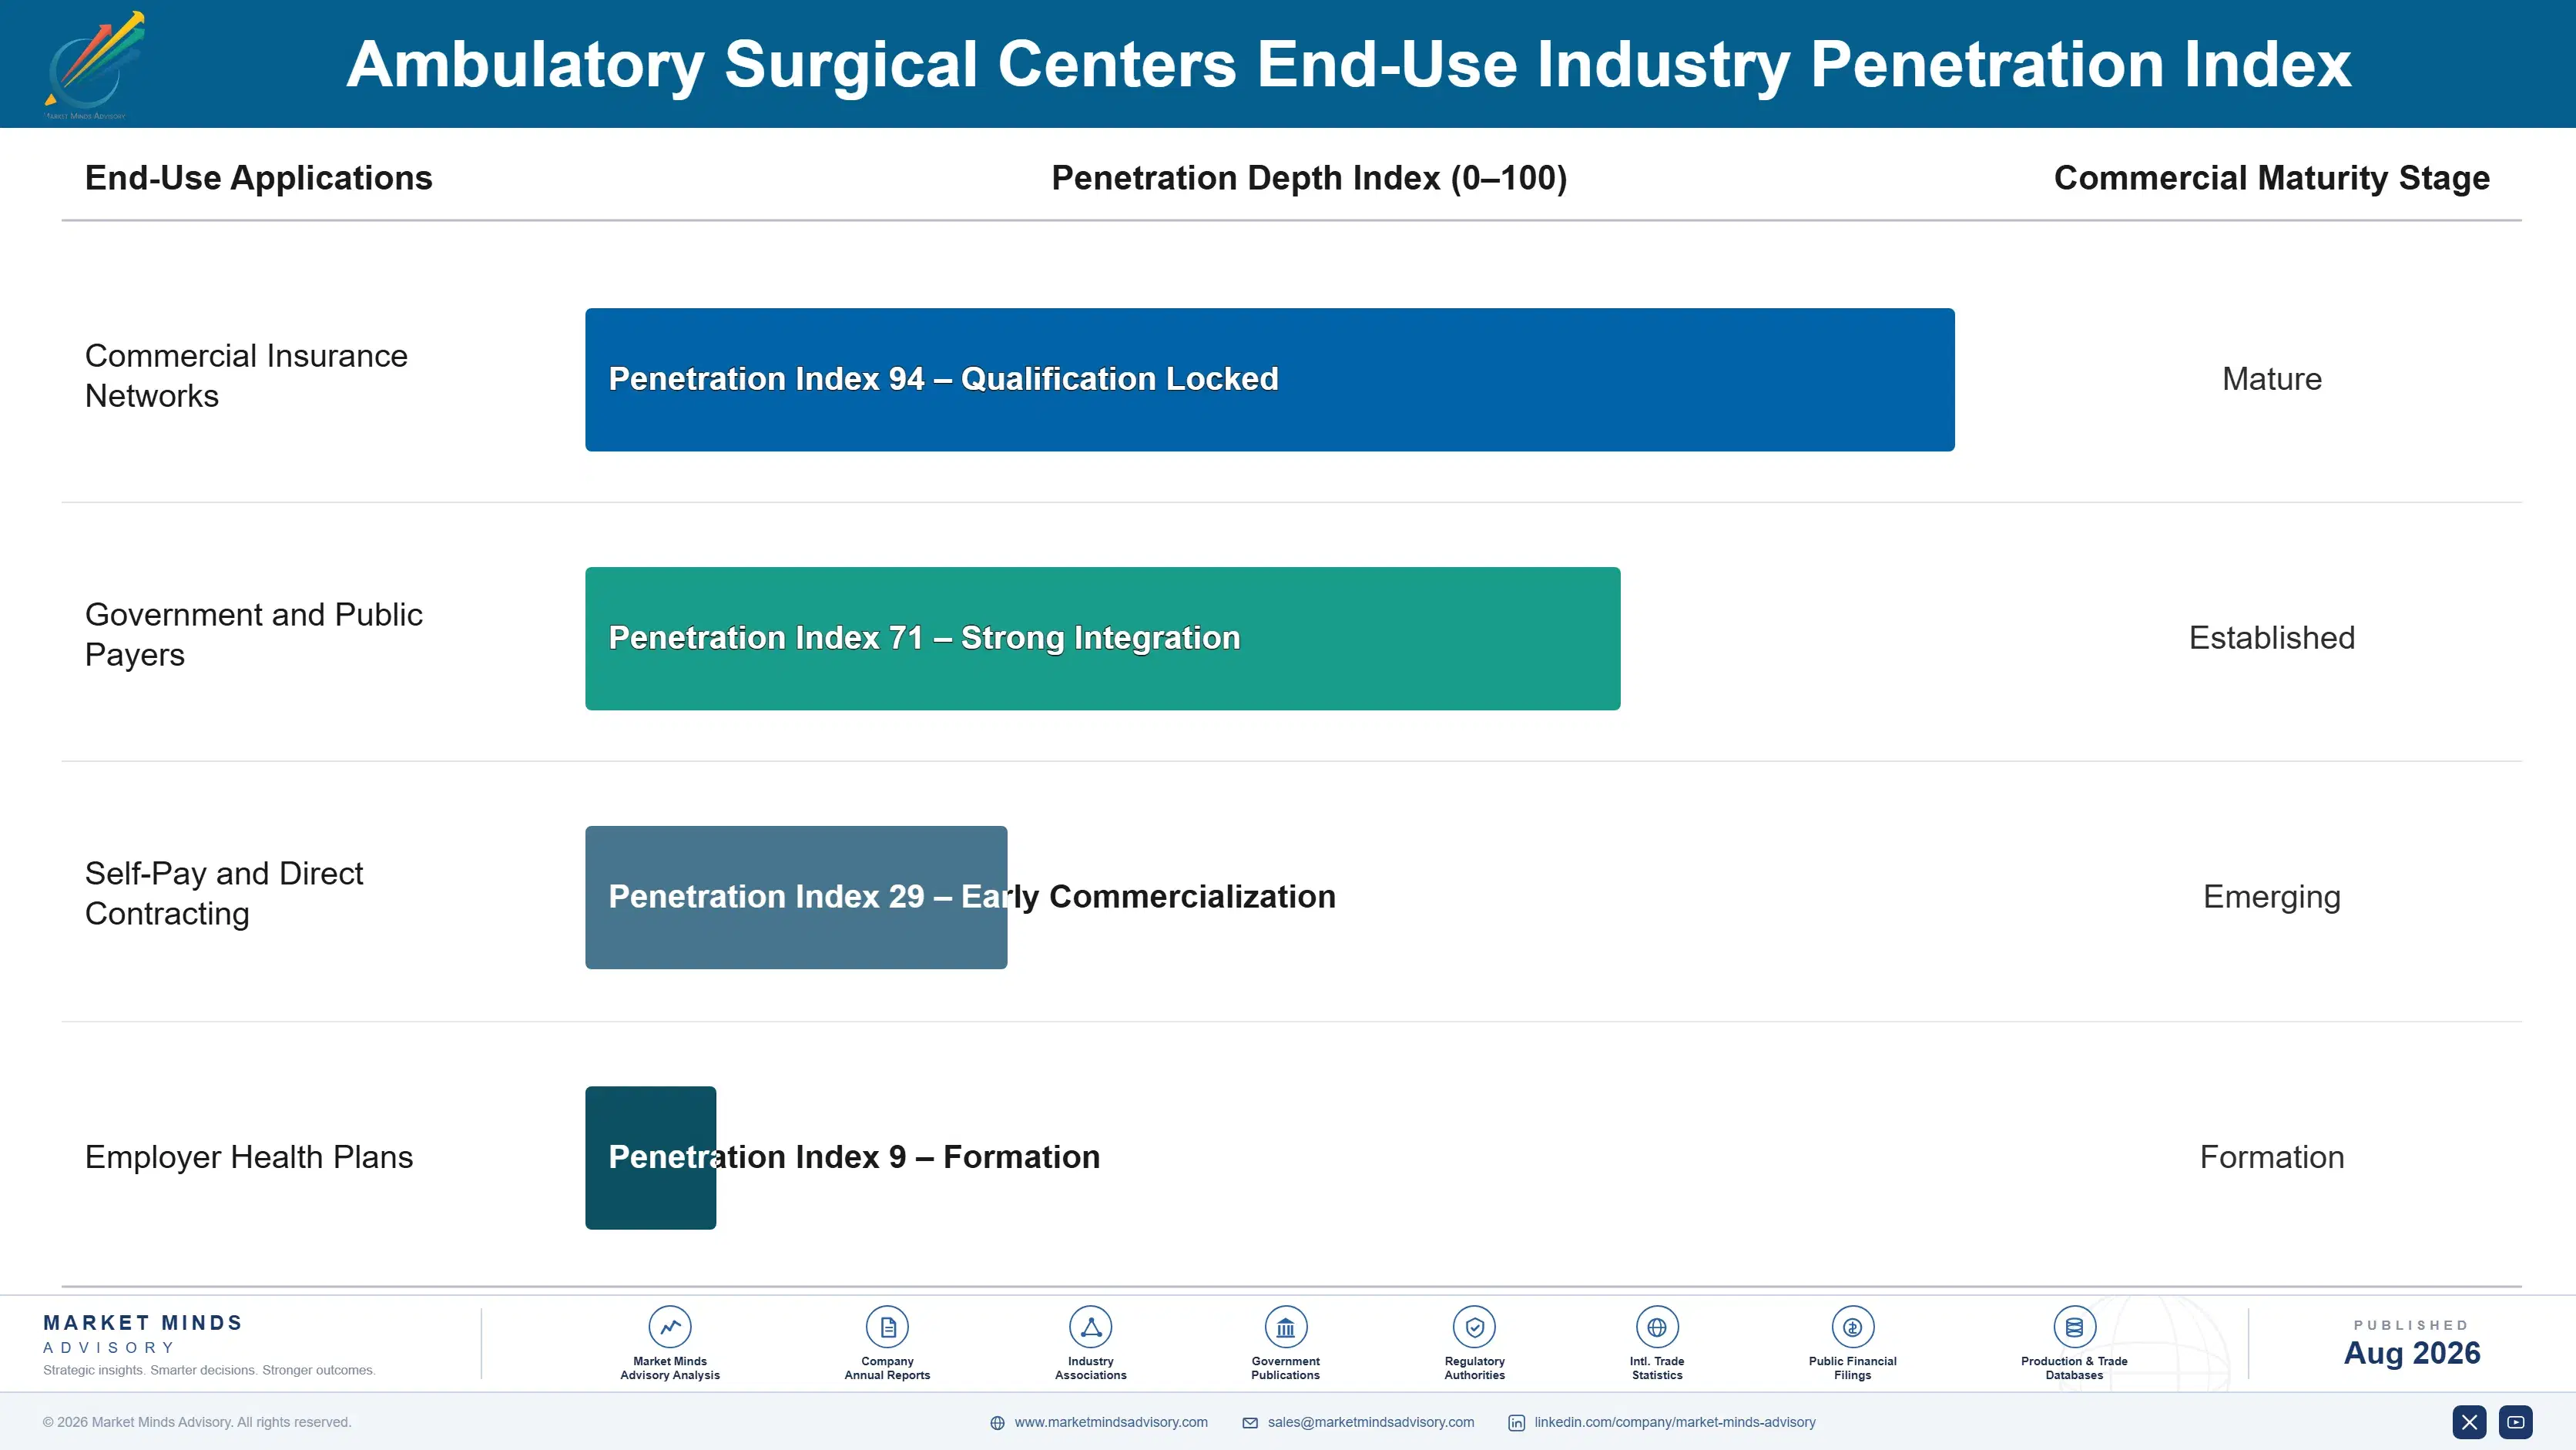
Procedural procurement revenue behaves like an annuity once a payer commits to a preferred operator and safety-outcome validation relationship, since switching costs run high after network-credentialing rollout and case-scheduling workflows become embedded around a specific center platform. Renewal rates stay elevated for incumbent operators, and expansion revenue from added cardiovascular product lines compounds steadily on top of the base contract each budget cycle.
Adoption stickiness runs deepest in cardiovascular and pain-management categories, where safety-outcome validation and case-complexity breadth directly touch readmission risk that payers will not risk disrupting once trust is established. Adoption stays shallower in routine gastroenterology categories, where procedure competes against simpler standard-cost referral-only centers and lower validation urgency reduces demand. Premium cardiovascular and multi-specialty programmes sit between these extremes, adopting selectively around specific high-value use cases.

A generational shift is underway in buyer profiles, as payer medical directors with genuine cardiovascular and multi-specialty literacy increasingly replace procurement managers who evaluated centers mainly on procedure price and vendor relationship. These newer buyers demand validated safety-outcome evidence before committing capital budget, reshaping which operators win renewal conversations. Younger physicians also expect outcome-first formats, pressuring legacy referral-only suppliers to modernize faster than before.
global-ambulatory-surgical-centers-market-end-use-penetration-index-1787303755183

What Wins The Next Decade Here

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / SAFETY OUTCOME VALIDATION PRIORITY

Fund independent safety-outcome validation before scaling

Operators that publish independently validated safety-outcome data ahead of competitors win payer contracts that validation-limited rivals increasingly cannot match, since payers now discount unverified qualification claims regardless of procedural scale, brand recognition, or historical relationship depth across most orthopedic and cardiovascular categories worldwide today. That validation gap is widening fast as safety-outcome scrutiny intensifies around legacy referral-only limitations affecting the broader ASC industry. Operators delaying this investment risk losing renewal conversations to faster-moving, evidence-backed challengers within a few contract cycles.
02 / CARDIOVASCULAR INVESTMENT TIMING

Build cardiovascular validation depth ahead of demand

Operators that convert basic referral-only offerings into genuine cardiovascular validation depth capture disproportionate pain-management demand before competitors close the gap, since payers increasingly treat safety-outcome validation as an active procurement requirement rather than an optional accessory bundled into broader procedural contracts today. Delay carries real cost, because early movers are already building payer trust and daily workflow habit around their specific validated platform across major multi-specialty and orthopedic categories nationwide. Late entrants will face materially higher switching-cost resistance later on.
03 / PAYER ACCESS TIMING

Build payer distribution depth ahead of demand

Operators that build genuine payer and physician distribution depth now, tying pricing directly to demonstrated safety-outcome performance and reduced readmission burden, position themselves ahead of an addressable site-of-care pipeline shift that keeps expanding steadily across major regulated orthopedic and cardiovascular markets and payer relationships nationwide. Competitors still selling pure referral-only formats risk appearing outdated once payer-linked pricing becomes the accepted industry norm among sophisticated procurement buyers evaluating long-term procedural partnerships. Early movers on this front are already converting pilot programmes into multi-year procurement commitments today.
04 / STAFFING SUPPLY RESILIENCE DISCIPLINE

Diversify staffing sourcing ahead of disruption

Operators that build diversified staffing sourcing and clinical-labor redundancy ahead of anticipated nursing-market disruption avoid the delivery delays currently slowing less-prepared competitors through unpredictable staffing timelines across most major ASC markets and clinical-labor categories worldwide today. That readiness becomes a genuine commercial differentiator once payers start favoring operators who can demonstrate delivery confidence during procurement evaluation and ongoing operational performance review. Operators treating supply strategy as an afterthought risk multi-quarter delivery delays precisely when prepared competitors are capturing share fastest.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Ambulatory Surgical Centers Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Ambulatory Surgical Centers Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-sized regional payer network covering three metropolitan service areas across a single large commercial-insurance footprint, relying primarily on legacy referral-only outpatient centers for its core orthopedic procedural network. Medical leadership had grown concerned about rising readmission rates on complex cardiovascular cases and wanted an independent assessment of cardiovascular-capable alternatives ahead of its next annual contracting cycle.
STRATEGIC CHALLENGE
The payer faced a network-design decision after internal audit data showed readmission rates on complex cardiovascular cases had risen meaningfully over the prior year, tied to referral-only centers' limited safety-outcome capability for high-acuity procedures. Leadership needed an independent, vendor-neutral assessment comparing continued referral-only network against cardiovascular-capable alternatives, weighing operating cost against projected readmission improvement.
MMA APPROACH
MMA conducted structured interviews with medical directors, network managers, and operator partner leadership across all three service areas, benchmarked readmission and validation-rate data against comparable cardiovascular-capable deployments at peer payer networks nationwide, and modeled total contracting cost including network conversion, credentialing, and workflow disruption against projected operational value across the network today.
KEY FINDINGS
  1. Readmission rates on complex cardiovascular cases had risen quite meaningfully over the prior year, tied directly to referral-only centers' limited safety-outcome capability across all three service areas today.
  2. Comparable cardiovascular-capable deployments at peer payer networks showed meaningful readmission-reduction gains sufficient to justify the operating cost within one fiscal year of deployment.
  3. Medical leadership across all three service areas strongly favored cardiovascular-capable adoption despite operating cost increase, citing genuine readmission and outcome concerns broadly today.
  4. Legacy-referral-only rework and delay cost had risen quite sharply overall (client-reported, unverified by MMA) without any real corresponding improvement in outcome data.
RECOMMENDED STRATEGY
Phase 1: Phase one: pilot cardiovascular-capable network deployment at the highest-readmission service area while fully retaining referral-only centers elsewhere throughout the entire pilot period. Phase 2: Phase two: expand validated cardiovascular-capable network deployment to the remaining service areas, phasing out legacy referral-only contracts gradually over nine full calendar months. Phase 3: Phase three: formalize cardiovascular-capable centers as the standard procedural network area-wide once validation data fully confirms every readmission target achieved.
OUTCOME
The payer approved a phased cardiovascular-capable transition beginning at its highest-readmission service area, with full area-wide expansion planned over nine months. Early pilot data showed readmission rates declining meaningfully within the first quarter (client-reported, unverified by MMA), and medical leadership reported improved confidence in conversion-timeline trajectory.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Ambulatory Surgical Centers Market?

The ambulatory surgical centers market reached USD 62.9 billion in 2026, following a 2025 base value of USD 58.0 billion. Growth continues steadily as site-of-care migration lifts demand across most major regions.

How large will the Ambulatory Surgical Centers Market be by 2036?

The market is projected to reach USD 142.2 billion by 2036, up from USD 62.9 billion in 2026. That represents a 2.26 times expansion over the ten-year forecast period.

What is the CAGR for the Ambulatory Surgical Centers Market 2026 to 2036?

The market is forecast to grow at a 8.5% CAGR between 2026 and 2036. Bull and bear scenarios range from 9.8% to 7.2%, depending on payer-driven migration pace.

Which segment is growing fastest?

Cardiovascular surgery centers lead growth at 11.5% CAGR, roughly 1.4 times the overall market rate, as payers demand validated safety-outcome performance over standard referral-only centers.

Who are the major companies in the Ambulatory Surgical Centers Market?

United Surgical Partners, Surgery Partners, AmSurg, SCA Health, and HCA Healthcare lead the market today. USPI holds the strongest position through safety-outcome validation scale and deep distribution reach.

Which country is growing fastest?

North America leads with a 38% regional value share, anchored by the United States unmatched reimbursement-model maturity under CMS payment policy. Reimbursement maturity and payer depth drive this pace.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Primary Market Dimension

  • Orthopedic Surgery Centers
  • Gastroenterology and Endoscopy Centers
  • Ophthalmology Surgery Centers
  • Pain Management Centers
  • Cardiovascular Surgery Centers
  • Multi-Specialty Surgery Centers

By End-Use Industry

  • Commercial Insurance Networks
  • Government and Public Payers
  • Self-Pay and Direct Contracting
  • Employer Health Plans

By Commercial Dimension

  • Physician-Owned Independent Centers
  • Corporate Management Company Operated
  • Health-System Joint Venture

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Eastern Europe
  • Middle East and Africa

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The ambulatory surgical centers market covers outpatient procedural facilities and their commercial management across specialty categories, including orthopedic, gastroenterology, ophthalmology, pain-management, cardiovascular, and multi-specialty surgery centers. Inpatient hospital services, physician-office procedures, and unrelated urgent-care facilities are excluded.
Quantitative Units
USD billions (current prices); segment and regional share percentages
Segmentation Dimensions
By Primary Market Dimension; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Eastern Europe, Middle East and Africa
Countries Covered
USA, Canada, Germany, France, UK, China, Japan, South Korea, India, Australia, Brazil, Mexico, Poland, Hungary, UAE, Saudi Arabia, South Africa, and additional markets relevant to this sector
Key Companies Profiled
United Surgical Partners International, Surgery Partners Inc., AmSurg, SCA Health, HCA Healthcare, Regent Surgical Health, NueHealth, Nueterra Healthcare, Compass Surgical Partners, Blue Chip Surgical Center Partners, Meridian Surgical Partners, Physicians Endoscopy, Constitution Surgery Alliance, Covenant Surgical Partners, Practice Partners in Healthcare
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-002
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Ambulatory Surgical Centers Market Report (2026 to 2036).

This report examines the global ambulatory surgical centers market across facility and specialty type, end-use industry, and commercial distribution model, quantifying market size, segment growth, and regional distribution through 2036. It profiles leading ASC management majors and independent operators, benchmarking competitive positioning, safety-outcome validation, and cardiovascular momentum across major orthopedic and pain-management markets. Coverage includes staffing cost exposure, procedural economics, and revenue lever analysis built for healthcare investors and payer procurement teams. The analysis draws on primary survey data, expert interviews, and company disclosures to support investment decisions.
Segment-level growth and revenue forecasts through 2036
Regional demand mapping across all seven world regions
Competitive benchmarking of leading ASC management vendors
Clinical staffing cost and supply exposure risk analysis
Revenue lever and margin expansion opportunity mapping
Safety-outcome validation and cardiovascular economics and margin outlook

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts