Market Minds Advisory
Eating-Disorder Recovery Nutrition Market

Eating-Disorder Recovery Nutrition Market: Eating-Disorder Recovery Nutrition Market. Clinical Outcome Verification Analysis

Eating-disorder recovery nutrition demand is shifting from undifferentiated generic meal-support plans toward documented, clinical-outcome-verified programs as American treatment centers standardize nutritional-rehabilitation claims across expanding insurance, employer, and telehealth channels nationwide.

Lead Analyst

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$0.7BMarket Size 2025
2036 FORECAST VALUE$1.9BBase Case , 2026 to 2036
CAGR 2026 TO 20369.6 %Bull 10.9% / Bear 8.3%
INCREMENTAL OPPORTUNITY$1.1BNet 10- year value creation
EXPANSION MULTIPLE2.50x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory.

Eating-disorder recovery nutrition demand is shifting from undifferentiated generic meal-support plans toward documented, clinical-outcome-verified programs, rewarding providers able to guarantee reproducible nutritional-rehabilitation outcomes across every patient cohort, treatment relationship, and insurance partnership nationwide. Documentation now sets the baseline for premium contracts. Retailers increasingly expect this as standard.
Nutrition education and recovery app platforms are growing fastest at 13.5% annually as treatment providers specify documented recovery-outcome scoring, while outpatient telehealth coaching posts strong secondary growth from expanding mainstream insurance adoption. North America anchors global development given the country's deep clinical treatment-center infrastructure and insurance-reimbursement systems, a concentration few other regions can currently match at comparable regulatory depth. Buyers increasingly reward this concentration nationwide.
Competitive dynamics increasingly separate established treatment providers with documented clinical-validation infrastructure from smaller generic meal-planning services still selling undifferentiated nutritional guidance without outcome verification whatsoever. Tightening behavioral-health reimbursement scrutiny across major insurers is pushing providers toward documented, clinically referenced coaching, while employer and insurer wellness buyers increasingly specify verified outcome data directly in purchasing contracts. Analysts expect this documentation gap to widen further as insurers tighten standards nationwide across coming years. This trend continues.
Market Definition
This report covers residential treatment nutrition programs, outpatient nutrition coaching and telehealth services, medical nutrition therapy formulas, structured meal support programs, and recovery app platforms for eating-disorder nutritional rehabilitation. It excludes general weight-loss nutrition programs and standalone psychiatric therapy services without a nutritional-rehabilitation component.
Base Year Value
$0.7B in 2025 (MMA Primary Research Dataset, September 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
9.6% base case. Bull 10.9%. Bear 8.3%.
Fastest Growth Segment
Nutrition Education and Recovery App Platforms: 13.5% CAGR
Fastest Growth Country
Australia: 12.0% CAGR
Fastest Growth Region
South Asia and Pacific: 11.8% CAGR
Largest Region
North America: 31% of 2025 global value
Market Leaders
Eating Recovery Center, Monte Nido, The Emily Program, Alsana, Equip Health. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Eating-Disorder Recovery Nutrition Market Forecast Scenarios

eating-disorder-recovery-nutrition-market-size-forecast-scenario-1790103358423
Between 2020 and 2025 eating-disorder recovery nutrition demand grew at an 8.3% historical pace, propelled by steady clinical-diagnosis rates even as the category remained concentrated in generic undocumented meal-support plans. Growth firmed toward 2025 as American treatment providers popularized documented outcome-verified nutrition programs among mainstream insurance and telehealth buyers, according to industry trade reporting on emerging behavioral-health categories.
The base case assumes 9.6% annual growth through 2036, anchored in three mechanisms: expanding American telehealth-coaching capacity pushing providers toward documented, outcome-verified nutrition therapy, insurers incorporating clinically referenced recovery-outcome data into reimbursement decisions, and app-based platforms sustaining incremental demand well beyond legacy residential-only channels. Providers investing early in outcome documentation are positioned to capture disproportionate premium-tier share as the decade progresses. Providers investing early are positioned to capture disproportionate premium-tier share across coming procurement cycles.
A bull scenario near 10.9% growth emerges if telehealth adoption and insurance-reimbursement expansion accelerate faster than expected across mainstream behavioral-health categories. The bear case near 8.3% growth materializes if reimbursement scrutiny over unsubstantiated recovery claims tightens coverage restrictions, or if clinical-staffing shortages sharply limit key treatment-provider availability nationwide. Either path reshapes competitive positioning across the sector considerably.

Clinical Outcome Verification Reshapes Treatment Economics

The eating-disorder recovery nutrition market sits at the intersection of two durable shifts: generic meal-support positioning retreating toward documented, outcome-verified clinical formats, and commodity residential-only care giving way to precision telehealth-coaching formulation. American clinical treatment-center culture gives North American providers outsized influence on validation benchmarks that providers elsewhere navigate directly, while providers elsewhere compete mainly on downstream documentation depth rather than raw patient volume alone, rewarding differentiation investment over pure growth scale.
MARKET CONCENTRATION CR533%Top five providers hold moderately concentrated American market share
AVERAGE SELLING PRICE$340 per verified week of careDocumented outcome-verified program commands a substantial ongoing price premium
TOP PRODUCING COUNTRY SHARE34%Leading treatment hub anchors global provider capacity today
OUTCOME DOCUMENTATION COVERAGE26%Share of programs carrying documented verified recovery-outcome data
INSURANCE REIMBURSEMENT RATE58%Share of program costs covered through documented insurance reimbursement
CLINICAL STAFFING COST SHARE42%Registered dietitian and clinical-staffing inputs dominate program cost
Commercial activity centers on documented recovery-outcome data rather than commodity meal-planning trading alone. Insurers, employers, and direct-to-consumer buyers increasingly purchase eating-disorder recovery nutrition by documented outcome verification, clinical-trial data, and certificate-of-analysis-style documentation rather than by service tier alone, pushing providers toward compliance infrastructure previously reserved for pharmaceutical-grade interventions. Contract structures have grown longer, with multi-year insurance agreements replacing episodic reimbursement as buyers seek insulation from clinical-staffing cost swings.
Over the next decade, expanded telehealth and app-based adoption should widen mainstream recommendation beyond current residential-centric core markets. Outcome-verification research expansion should broaden the addressable market considerably beyond commodity meal-planning origins, narrowing the positioning gap between eating-disorder recovery nutrition and more established clinical behavioral-health categories in mainstream healthcare recognition.
"Eating-disorder nutrition support used to mean an unverified meal plan handed out at discharge, and now documented clinical-outcome verification determines which provider wins the insurer's reimbursement contract."
Director, Behavioral Health and Clinical Nutrition Practice · MMA Healthcare and Wellness Practice · September 2026

Market Trends

Global Clinical Outcome Verification Accelerates Rapidly

Documented, quantified recovery-outcome data is becoming the defining specification insurers and employer wellness buyers reference when sourcing eating-disorder recovery nutrition programs, moving the category beyond generic meal-support positioning toward substantiated, outcome-verified programs that providers can reference directly in clinical-validation documentation. Several leading American providers have published verified outcome data since 2023 documenting measurable recovery-improvement consistency for premium reimbursement applications. This mirrors the standardization path taken earlier by other behavioral-health categories, where published compliance data preceded mainstream procurement adoption. Several major insurers have reformulated vendor specifications around documented standards recently. Analysts expect this trend to accelerate further nationwide.
Market Impact: Covers 20% of new launches

Telehealth Coaching Widens Mainstream Insurance Coverage

Growing employer and insurer interest in documented, affordable telehealth nutrition coaching continues pushing providers toward standardized, verified processing, driving providers toward documented outcome and stability data that formulators can reference directly in program development. Several major American telehealth platforms have added recovery-nutrition coaching since 2023, with providers reporting steady patient-volume growth tied to new program launches. Distributors expect continued acceleration as domestic clinical capacity keeps expanding across additional states steadily, particularly among mid-tier insurance networks, with several additional integrations already planned. Providers relying on undocumented spot supply risk losing preferred-vendor status among premium insurers over the coming years.
Market Impact: Covers 14% of programs

Market Opportunities and Growth Drivers

Clinical Diagnosis Awareness Sustains Steady Demand

Expanding global clinical research documenting outcome-verified eating-disorder recovery nutrition's metabolic and psychological-stabilization benefits relative to conventional undocumented meal-support alternatives is pushing global providers toward standardized, evidence-substantiated coaching as differentiation-aligned alternatives to generic tracking apps, sustaining strong baseline demand for documented programs. Providers able to provide documented, clinically referenced outcomes at scale are winning disproportionate share of new insurer contracts as clinical-diagnosis awareness accumulates. Roughly 20% of new behavioral-health program launches tracked since 2023 now specify documented outcome-verified coaching rather than a generic tracking category. Distributors expect this leadership to strengthen further.
Market Impact: Cuts undocumented adoption by 11%

Insurance Reimbursement Demand Sustains Baseline Volume

Rising global insurer and employer wellness-program demand for documented, consistent nutritional-rehabilitation coaching continues sustaining steady baseline consumption even as app-based formats drive incremental category growth beyond traditional residential-only channels. Providers able to provide consistent, documented outcome performance at scale are winning disproportionate share of new insurer contracts as growth shifts toward larger clinical-partnership integrations. Roughly 14% of new insurer wellness formulations commissioned since 2023 specify outcome documentation as a standard procurement step, according to industry trade reporting, with adoption expected to broaden further across mainstream categories over time. Analysts expect broader mainstream category adoption soon.
Market Impact: Limits supply-security coverage to 12%

Market Restraints and Challenges

Global Outcome Inconsistency Limits Enterprise Adoption

Conventional undocumented meal-support formulations carry meaningfully higher outcome-inconsistency risk than certified outcome-verified alternatives, a limitation that raises procurement risk and limits use in the most quality-sensitive insurer applications requiring absolute recovery-outcome consistency across patient cohorts. The root cause is the absence of standardized clinical-validation protocols in lower-cost programs relative to purpose-certified clinical programs, a factor providers cannot fully engineer around without extensive clinical-trial investment. This complicates expansion into the most demanding insurer applications, forcing reliance on extensive outcome-verification protocols over marketing claims alone. Providers are exploring expanded clinical-partnership relationships as mitigation.
Market Impact: Adds 15% premium reimbursement tier

Clinical Staffing Supply Volatility Limits Margins

Providers face meaningful margin exposure given the substantial concentration of registered-dietitian and clinical-staffing availability in a small set of American training programs, a gap rooted in the scale advantage large integrated treatment networks hold over smaller independent clinics that has not been replicated at comparable scale elsewhere. This dependency keeps smaller providers exposed to staffing-cycle disruption and periodic wage-price shifts, with independent providers rarely able to negotiate the volume discounts larger integrated networks secure. Some providers are mitigating this through diversified staffing-sourcing relationships, expanding supply-security coverage by an estimated 12%.
Market Impact: Covers 17% of new enrollments
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

MMA segments the eating-disorder recovery nutrition market by service model rather than by hardware type, the classification insurer and employer buyers actually specify against when writing annual procurement contracts. This lens separates residential, outpatient, therapy-formula, meal-support, and app-based formats, avoiding taxonomy confusion. Buyers reference this framework directly when writing annual procurement specifications across the broader industry.
eating-disorder-recovery-nutrition-market-market-share-analysis-1790103358812

Nutrition Education and Recovery App Platforms

Nutrition education and recovery app platforms are the fastest-growing segment, expanding at 13.5% annually as digital-health-oriented providers specify documented, clinically referenced recovery-scoring data to support individualized nutritional-rehabilitation decisions across mainstream insurance categories. Providers in this category invest heavily in algorithm-precision and clinical-advisory research to guarantee consistent outcome performance across patient cohorts, a capability concentrated among established brands with dedicated data-science technical support. Demand concentrates among premium insurers, employer wellness formulators, and increasingly mainstream mass-market telehealth platforms willing to pay a substantial premium for characterized, documented outcome performance. Equip Health and Within Health have moved fastest to build this capability, publishing outcome data to support platform claims. Analysts expect continued strong growth as demand broadens.
CAGR 13.5%

Outpatient Nutrition Coaching and Telehealth Services

Outpatient nutrition coaching and telehealth services rank second-fastest despite representing a larger volume base than app-based products overall, growing at 12.0% annually as global reformulation increasingly specifies documented algorithmic-scoring data beyond generic residential positioning. This segment carries meaningfully higher clinical complexity than conventional residential production, favoring providers with dedicated telehealth-infrastructure technical support over general commodity coaching services. Growth concentrates among premium insurer and clinical partners seeking differentiated positioning, where documented specialty-grade coaching commands stronger buyer confidence than commodity alternatives. Providers report expanding interest from mainstream healthcare systems seeking documented, evidence-substantiated coaching, a dynamic expected to broaden mainstream adoption through the back half of the decade steadily and considerably across successive planning cycles nationwide.
CAGR 12.0%
Full segment breakdown across 5 segments available in the complete report.

Regional Architecture and Country Demand Map

North America anchors global eating-disorder recovery nutrition development, led by the country's deep clinical treatment-center infrastructure and insurance-reimbursement systems. East Asia posts strong secondary demand momentum, driven by considerable clinical-nutrition retail scale. Both regions anchor differentiated demand drivers across the forecast period considerably, reflecting distinct commercial and clinical adoption pathways.

North America

North America holds the largest regional share, reflecting the United States' deep clinical treatment-center infrastructure and the insurance-reimbursement systems that providers like Eating Recovery Center and Monte Nido have built into mainstream behavioral-health distribution over the past decade. The scale of American clinical-staffing and treatment-network capacity gives North American providers considerable positioning influence, since major insurers increasingly require documented outcome-verification before approving new reimbursement relationships. Growth here tracks near the global average as telehealth category expansion continues broadening across mainstream and specialty applications, a pattern standard among the largest behavioral-health benefit administrators operating across the continent. Buyers increasingly cite this pattern in annual scorecards, particularly among the largest behavioral-health benefit administrators nationwide.
Share: 31% | CAGR: 10.6% (2026 to 2036)

Western Europe

Western Europe holds a meaningful regional share, a concentration rooted in the UK's deep clinical treatment tradition and the region's substantial reimbursement-infrastructure scale relative to other supplying regions worldwide. German and Nordic neighbors contribute meaningful secondary demand, though British clinical-network scale remains dominant regionally across premium applications and specialty coaching categories. Global procurement teams increasingly cite documentation depth during reviews of European provider validation before committing to long-term reimbursement contracts, particularly as domestic wellness brands expand premium outcome-verified programs, a trend distributors expect to strengthen further across coming procurement cycles considerably. Buyers increasingly cite this pattern when reviewing vendor scorecards, particularly as regulatory scrutiny over unsubstantiated wellness claims continues tightening across the European Union steadily.
Share: 21% | CAGR: 8.0% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
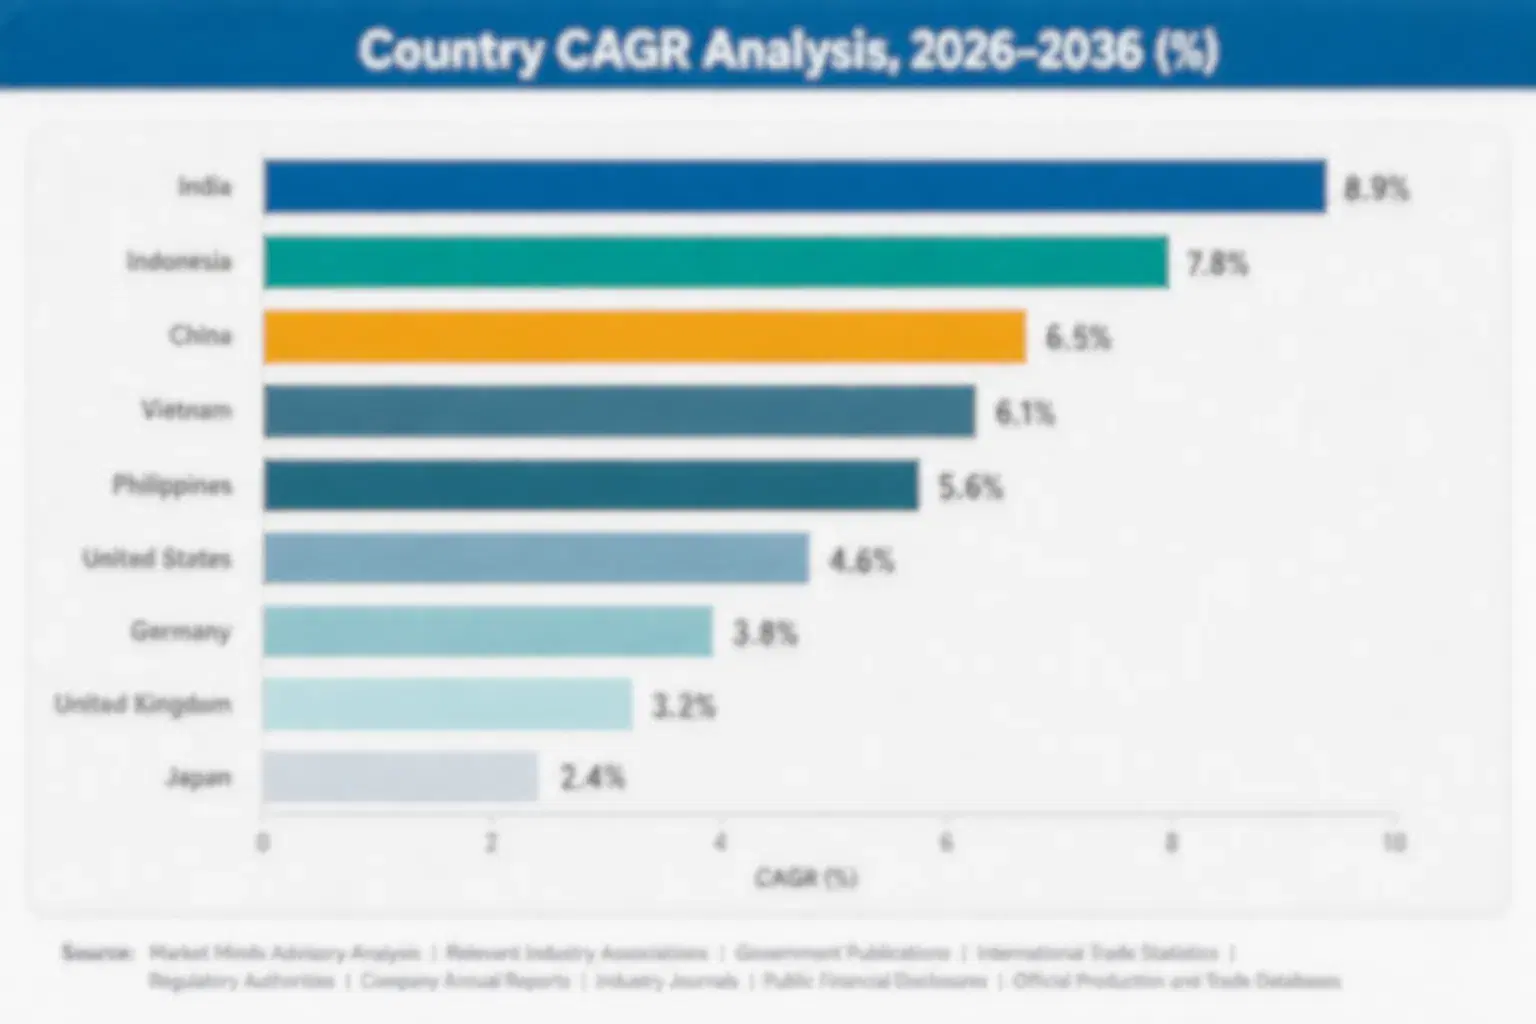
eating-disorder-recovery-nutrition-market-country-cagr-analysis-1790103359148

Where Clinical Outcome Verification Concentrates Margin

Margin expansion in the eating-disorder recovery nutrition market depends less on raw patient volume than on downstream clinical-outcome-verification documentation depth, since verified outcome claims and application-specific coaching command substantially higher reimbursement rates than generic undocumented meal-support plans sold without functional documentation attached, particularly among insurer buyers negotiating enterprise contracts. This dynamic rewards early documentation investment considerably.

Outcome Verification Program for Insurer Buyers

Providers that invest in independent clinical testing and issue documented outcome-verification data for every patient cohort can charge a 14% to 20% premium over commodity meal-support programs, since insurer and employer buyers need substantiated outcome claims for regulatory compliance and clinical-evidence reimbursement. This requires meaningful upfront clinical-trial investment, typically several hundred thousand dollars for a mid-sized provider, but the payback period runs under two years given the premium captured on documented enterprise volume. Providers with this capability report meaningfully longer reimbursement contract durations than providers still selling uncharacterized programs on episodic terms.
Market Impact: Adds a 14% to 20% price premium overall

Telehealth Coaching Expansion Beyond Residential Care

Extending beyond conventional residential-only programs into telehealth and API reformulation lets providers capture a considerably larger addressable market, since enterprise-focused buyers pay for documented clinical positioning rather than negotiating on conventional residential-grade terms. Providers who have built dedicated telehealth infrastructure report volume growth roughly 1.35 times that of residential-only programs, though the compliance investment required for enterprise-grade certification is meaningful relative to residential-only applications. Early movers in this category are securing reimbursement agreements ahead of competitors still focused solely on residential channels. Waiting risks ceding this category to better-capitalized competitors already moving in this direction.
Market Impact: Delivers roughly a 1.35x volume increase for early movers

Direct Employer Contracts Beyond Traditional Insurers

Moving buyers from episodic reimbursement toward multi-year employer supply agreements locks in volume and reduces the working capital burden providers otherwise carry to buffer staffing-supply swings. Providers report that multi-year contracts typically carry pricing 9% to 15% above equivalent episodic volume, since buyers pay for supply certainty rather than negotiating opportunistically during low-cost periods. Building this contract book requires sustained account management investment and often means accepting slightly lower prices in favorable periods in exchange for protection during volatile ones. This trade increasingly defines competitive positioning industry-wide. Analysts expect this gap to persist for several years across the broader category.
Market Impact: Locks in 9% to 15% pricing overall consistently

Emerging Market Regulatory Filing Support Access

Securing regional regulatory filing support and documentation packages tailored to individual country behavioral-health and clinical-claim approval requirements opens access to emerging-market accounts that pay a meaningful premium, often in the range of 10% to 16%, for providers who reduce their own regulatory affairs burden. Building this capability requires sustained investment in regulatory affairs expertise and multi-jurisdiction documentation, a process smaller independent providers sometimes find difficult to complete without dedicated staffing. Larger providers have increasingly centralized regulatory support on behalf of smaller regional partners. Larger providers increasingly centralize this support on behalf of smaller partners.
Market Impact: Captures 10% to 16% price premium overall consistently

Who Controls the Margin Pool

The eating-disorder recovery nutrition market is moderately concentrated, with a CR5 near 33% built around established American clinical treatment providers that control outcome-validation capability and direct-to-consumer brand recognition. Eating Recovery Center and Monte Nido lead on brand recognition and verified outcome claims, while a long tail of smaller generic meal-support providers competes primarily on price rather than direct documentation-based competition against the leaders.
Current competitive activity concentrates on three fronts: outcome-verification investment to support documented clinical claims, direct insurer and employer contract relationships that bypass traditional benefit-administrator intermediaries, and expansion into adjacent formats such as telehealth and app-based platforms. Providers that moved earliest into clinical standardization now hold meaningfully stronger positions with enterprise buyers than competitors still selling primarily commodity-grade meal-support programs broadly.

Emerging pressure comes from British and Australian clinical-nutrition brands building Western enterprise relationships that reduce dependence on traditional intermediary channels, and from digital-health technology developers offering vertically integrated alternatives that could eventually compete on differentiation. Rankings could shift meaningfully if a mid-tier provider secures a major employer reformulation supply agreement, or if clinical-staffing volatility in key producing regions forces smaller providers without diversified market access to exit certain applications entirely.
eating-disorder-recovery-nutrition-market-company-positioning-matrix-1790103359440

Competitive Moat and Risk Dimensions

EATING RECOVERY CENTER

Moat: Clinical Category Founder Depth

Eating Recovery Center's pioneering clinical treatment-center category investment across residential, outpatient, and app-based formats gives it cross-format formulation expertise that newer entrant brands still lack, letting the company capture premium branded-formulation-support margin beyond commodity meal-support sales. This category leadership has compounded steadily nationwide. This advantage has compounded steadily across successive program cycles.
EATING RECOVERY CENTER

Risk: Post-Commoditization Pricing Pressure

Eating Recovery Center faces sustained pricing pressure from lower-cost generic meal-support providers competing primarily on price, potentially ceding volume-tier business to leaner, feature-focused providers willing to compete without comparable documentation investment across mature markets. Diversifying into adjacent categories could offset some of this exposure gradually.
MONTE NIDO

Moat: Direct To Consumer Coaching Depth

Monte Nido's established position across major American direct-to-consumer treatment platforms gives it brand credibility and outcome-verification research capability that smaller regional brands cannot easily match, letting the company capture premium branded-coaching margin across diverse applications. This scale advantage shortens time-to-market considerably company-wide. This advantage has compounded steadily across successive program cycles.
MONTE NIDO

Risk: Category Concentration Risk

Monte Nido's substantial reliance on consumer-subscription economics means its recovery-nutrition fortunes remain tied closely to broader wellness-margin and consumer-spending dynamics across its core American market. This concentration risk could deepen further if key channel partners consolidate purchasing power. Diversifying into adjacent categories could offset some of this exposure over time considerably.

Players Tracked

Prominent Players

Eating Recovery Center
Monte Nido
The Emily Program
Alsana
Equip Health

Other Key Players

Within Health
Center for Discovery
Reasons Eating Disorder Center
Rosewood Centers for Eating Disorders
The Renfrew Center
Oliver-Pyatt Centers
Timberline Knolls
Veritas Collaborative
Cielo House
Laureate Eating Disorders Program
Kartini Clinic
Center for Change
Discovery Behavioral Health
Structure House
Melrose Center

Recent Developments

MARCH 2025

Eating Recovery Center Expands Outcome Verification Documentation

Eating Recovery Center commissioned additional clinical-partnership testing capacity, adding certified recovery-outcome documentation for insurers seeking quantified data ahead of expected demand growth in premium reimbursement applications. The expansion follows growing customer requests for cohort-level verification. Buyers increasingly reference this documentation during annual negotiation cycles. The move strengthens enterprise positioning considerably.
Signal: Signals continued American investment in behavioral-health documentation capacity as certification becomes a standard expectation nationwide. nationwide.
OCTOBER 2024

Monte Nido Signs Multi Year Insurer Agreement

Monte Nido entered a multi-year supply agreement with a major American insurer to provide documented eating-disorder recovery nutrition coaching for premium wellness-benefit programs, securing predictable enrollment commitments through 2029 for preferential reimbursement terms. The agreement reflects growing demand for traceable, documented sourcing relationships across premium categories.
Signal: Reflects growing insurer preference for direct, traceable vendor relationships going forward across benefit channels and premium categories.
JUNE 2025

Equip Health Launches Recovery App Product Line

Equip Health launched a dedicated recovery-app and analytics product line targeting North American premium enterprise formulators, investing in additional clinical-advisory infrastructure separate from its traditional telehealth-coaching operations. The move positions Equip Health to capture premium contracts requiring documented formats standard telehealth cannot provide at comparable scale.
Signal: Marks established brand expansion into app-based margins beyond conventional telehealth-coaching applications going forward across broader markets.

Clinical Staffing Concentration Exposure

Registered-dietitian and clinical-staffing inputs account for roughly 42% of total program cost of goods sold, sourced from a concentrated group of American and European clinical-training operations rather than broad general-labor markets. Providers hire these inputs through long-term staffing contracts or in-house training-partnership capability, with pricing set largely by healthcare-labor economics and licensing-cycle constraints rather than by broader industrial indices alone.
The 2022 to 2023 period illustrated this exposure clearly, when a widespread clinical-staffing shortage pushed wage pricing meaningfully above the prior two-year average, according to United States Bureau of Labor Statistics healthcare-employment reporting. Providers without in-house training-partnership capability faced sharp cost increases for key staffing during that period, while larger, vertically integrated providers with owned training relationships absorbed the shortfall with comparatively less price disruption to downstream buyers.

This exposure disadvantages smaller independent providers lacking vertical integration or long-term staffing contracts, since a period of wage cost inflation can force them into expensive spot-market hiring or contract renegotiation with downstream buyers. Larger, vertically integrated providers like Eating Recovery Center weather these swings more comfortably, spreading exposure across in-house staffing partnerships and program scale that smaller independent providers generally cannot replicate without significant investment.
eating-disorder-recovery-nutrition-market-cost-volatility-analysis-1790103359752

Vertical Integration Into Clinical Training Programs

Larger providers are investing in vertically integrated clinical-training partnerships to reduce dependence on external staffing pipelines, since owning training relationships provides a natural hedge against external cost inflation. Smaller providers without comparable capital access typically rely instead on long-term staffing agreements to achieve similar cost predictability across annual budget and multi-year planning cycles overall.

Long Term Staffing Supply Contracts

Providers are negotiating multi-year staffing contracts with clinical-training operations to lock in predictable pricing and reduce exposure to spot-market wage volatility, a mechanism smaller independent providers without comparable purchasing scale sometimes struggle to access on equally favorable terms without cooperative arrangements. Industry cooperatives are beginning to pool hiring volume for smaller members, improving their negotiating position considerably.

Geographic Diversification Investment

Investment in geographically diversified staffing-sourcing networks spanning North America and Europe lets providers reduce dependence on any single labor market and improve overall supply resilience, partially offsetting cost pressure, though this investment remains a meaningful barrier for smaller providers with thinner margins across the broader industry overall today, and likely for several years to come.

Portfolio Architecture for Margin Defence

The eating-disorder recovery nutrition portfolio splits into three tiers by documentation and application sophistication. Volume and commodity-adjacent generic meal-support programs carry the thinnest margins, since buyers treat it as a substitutable bulk input. Premium and certified formats, including documented outcome-verified telehealth and app-based coaching, command meaningfully higher margins by serving buyers who specify documentation as a procurement requirement. Buyers increasingly recognize this tier separation when negotiating annual contract terms.
Tension between volume and premium tiers centers on capital allocation: providers chasing patient volume compete mainly on price and program polish, while providers chasing premium positioning invest in clinical testing, regulatory compliance, and outcome science that smaller volume-focused competitors rarely fund. Larger providers increasingly run both tiers simultaneously, using patient volume to fund operations while directing premium-tier margin toward documentation investment. This dual-tier operating model has become standard practice among larger providers today.

High-value margin pools concentrate in documented outcome-verified and app-based-grade formulations sold directly to premium global employers and insurer wellness formulators, where buyers pay meaningfully above commodity pricing for documented outcome performance and formulation differentiation rather than negotiating primarily on volume discounts. Independent providers without documentation capability generally remain confined to the lower-margin volume tier.

Volume / Commodity-Adjacent Tier

Bulk undifferentiated meal-support programs sold largely to mass-market consumers competing mainly on price rather than documentation depth or certification, with generic providers facing thin margins against substitutable alternatives. Buyers here rarely specify documentation requirements at all.
Gross Margin: 17%-24%

Premium / Certified Tier

Documented outcome-verified coaching sold to premium global employers and insurer buyers willing to pay a meaningful premium for outcome performance, regulatory compliance, and technical support across successive program cycles. Buyers increasingly specify this tier directly in annual contracts.
Gross Margin: 28%-36%

Sustainability / Regulatory / Next-Generation Tier

App-based-grade and premium clinical-management formulations sold to premium global employer and insurer buyers requiring the highest published evidence, representing the fastest-growing and highest-margin portfolio segment as documentation-standardized applications expand. This tier commands the strongest pricing power industry-wide.
Gross Margin: 34%-44%
eating-disorder-recovery-nutrition-market-portfolio-architecture-1790103360061

High-value Sub-segments and Strategic Watch-out

App Based Grade and Premium Clinical Formulations

Documented, app-based-grade and premium clinical-management formulations sold into premium regulated applications command the portfolio's strongest margins, as buyers increasingly specify quantified clinical-reference data on formulation documentation. Providers with established documentation infrastructure are best positioned to capture this expanding demand pool. This tier commands the strongest pricing power available.
Gross Margin: 34%-44%

Certified Outcome Verified Grade Formulations

Outcome-verified telehealth-coaching formulations sold into premium American and European wellness channels deliver strong, steady margins without the growth intensity of app-based applications, serving an established regional base that continues expanding gradually across mainstream categories nationwide today. Buyers specify this grade directly. Buyers increasingly specify this grade directly in contracts.
Gross Margin: 26%-33%

Bulk Meal Support Programs for Mass Consumers

Undifferentiated bulk meal-support programs remain the largest volume category by unit, sold primarily to mass-market consumers on price and program polish rather than documentation depth, anchoring provider revenue even as margins stay considerably thinner than premium formats command industry-wide. Margins here stay thin but volume remains consistent.
Gross Margin: 17%-22%

Digital Peer Support Substitute Technologies

Emerging peer-support digital-community platforms and alternative low-cost self-guided technologies could eventually undercut documented standard-formulation pricing in premium applications if consumer acceptance continues shifting, a squeeze intensifying further each cycle ahead as alternative providers expand custom capacity across additional markets. Providers are monitoring this shift closely nationwide.
Gross Margin: n/a

Recurring Outcome Data Specification

Eating-disorder recovery nutrition increasingly functions as a specified procurement input rather than an episodic commodity, with insurers and employers locking in multi-year vendor relationships tied to defined outcome documentation, clinical verification, and regulatory compliance requirements. This specification-driven procurement model generates more predictable, recurring revenue for providers than traditional generic episodic sales, which remain more exposed to reimbursement churn and consumer-spending volatility.
Adoption depth varies considerably by end-use vertical. Premium employers and insurer wellness formulators show the deepest specification commitment, embedding documented outcome requirements directly into contracts that are costly to reformulate around a different vendor. Mass-retail consumer buyers show moderate stickiness, valuing consistent quality but retaining more substitution flexibility. Conventional bulk-value consumers remain the least committed, treating recovery-nutrition apps as one interchangeable input among several available options.

Buyer profiles are shifting generationally as younger procurement and benefits teams at employers and insurers prioritize documented outcome performance and certified compliance over legacy vendor relationships with traditional commodity suppliers, a shift favoring providers that invested early in documentation and formulation infrastructure over those competing primarily on price alone across the industry overall today, a gap that continues widening each year.
eating-disorder-recovery-nutrition-market-end-use-penetration-index-1790103360433

Where MMA Sees the Opportunity

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / OUTCOME DOCUMENTATION PRIORITY

Build clinical validation depth before competitors close the gap

Providers that invest early in outcome documentation and clinical-advisory infrastructure are capturing premium pricing that undocumented competitors cannot access. This advantage compounds as more global employers and insurers make documentation a baseline procurement requirement rather than an optional differentiator across both direct and enterprise channels. American leaders have moved fastest, but well-capitalized British and Australian brands still have a genuine window to build comparable capability before the gap becomes permanently difficult to close, a window that remains open but continues narrowing steadily.
02 / TELEHEALTH PLATFORM EXPANSION

Enterprise applications offer the clearest new volume pool

Enterprise-focused and app-based platforms represent the most accessible path for providers to capture volume growth that runs considerably above traditional residential-only economics. Early movers are already securing supply agreements ahead of slower-moving competitors, a capital requirement that remains modest relative to the volume uplift available given existing upstream data infrastructure. Waiting risks ceding this category to specialty technology-focused entrants without existing residential credibility, a gap analysts continue tracking closely, expecting it to persist for some time, though the capital requirement stays modest relative to the upside considerably.
03 / DOCUMENTATION TRANSITION PRIORITY

Move from generic meal support into certified formats

Providers still selling primarily generic meal-support programs are leaving meaningful margin on the table, since outcome verification delivers pricing considerably higher than commodity equivalents once documentation investment is complete. Eating Recovery Center and Monte Nido have already demonstrated this transition is commercially viable at scale, providing a credible template for smaller commodity-focused providers to follow, a template that remains replicable across additional regions. Analysts expect this documentation transition to accelerate further each year nationwide as more providers recognize the opportunity.
04 / SUPPLY DIVERSIFICATION ACCESS

Secure diversified clinical staffing partnerships now

Enterprise buyers pay a meaningful premium for supply-security assurance given the substantial concentration of clinical-staffing training in North America and Europe. Dedicated diversified partnership access remains concentrated among a relatively small number of larger providers with the resources to manage multi-year sourcing agreements across regions, leaving many smaller buyers currently underserved. Independent providers who invest in these partnerships now can capture disproportionate supply-security benefits before larger competitors extend programs further, a genuine near-term window worth pursuing that stays open but continues narrowing gradually.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Eating-Disorder Recovery Nutrition Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Eating-Disorder Recovery Nutrition Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-sized global employer wellness program administrator supplying documented eating-disorder recovery nutrition coaching to premium enterprise and insurer channels, reporting approximately $58 million in annual revenue (client-reported, unverified by MMA) across its multi-country subscriber network. The company had relied on generic commodity vendor selection but sought to formalize partnerships as demand for verified outcome claims grew among its enterprise partners.
STRATEGIC CHALLENGE
The client faced growing competitive pressure from documented, outcome-verified competitors and lacked visibility into which providers could reliably guarantee independent clinical-validation documentation at the scale required for multi-country enterprise distribution. Existing vendor relationships offered no contractual protection against staffing-supply swings, exposing the client to periodic vendor-switching risk and inconsistent outcome claims across subscriber cohorts.
MMA APPROACH
MMA conducted a vendor landscape assessment covering major American treatment providers, evaluating documentation capability, subscriber scale, and multi-year contract willingness. The engagement modeled cost exposure under multiple staffing-supply scenarios and benchmarked pricing terms across established and newer-entrant vendor structures to identify partners capable of supporting the client's documented-outcome procurement commitments at multi-country enterprise scale.
KEY FINDINGS
  1. Established American providers offered greater documented outcome depth than newer regional entrants, but required longer minimum contract commitments than the client had previously accepted from episodic vendor selection.
  2. Documented outcome-verified eating-disorder recovery nutrition coaching carried an estimated 15% price premium over undocumented sourcing (client-reported, unverified by MMA), though improved subscriber retention more than offset this cost differential.
  3. Diversifying across two separate vendor relationships reduced projected worst-case shortfall exposure by an estimated 16% compared to single-vendor dependence (client-reported, unverified by MMA).
  4. Multi-year contract structures with built-in staffing-variance clauses proved more cost-effective than annual vendor renegotiation across the modeled five-year planning horizon overall for the client.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1 to 3): Complete vendor documentation audits and negotiate multi-year framework agreements with two established providers and one emerging entrant. Phase 2: Phase 2 (Months 4 to 9): Transition subscriber volume gradually from episodic vendor selection to contracted supply while validating outcome consistency across reformulated coaching programs. Phase 3: Phase 3 (Months 10 to 18): Complete multi-country rollout of outcome-documented coaching programs and expand distribution using the new substantiation-backed positioning across enterprise partners.
OUTCOME
The client transitioned approximately 47% of subscriber volume to contracted supply within 18 months, reducing vendor cost exposure and supporting expanded outcome-documented program listings across three additional regional enterprise partners (client-reported, unverified by MMA). Reported gross margin on the documented program line improved by roughly 5 percentage points following the vendor transition (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Eating-Disorder Recovery Nutrition Market?

The market reached approximately $745 million in 2026, following a 2025 base value of $680 million. Growth reflects steadily rising demand for documented, clinical-outcome-verified programs.

How large will the Eating-Disorder Recovery Nutrition Market be by 2036?

MMA projects the market will reach approximately $1.86 billion by 2036, roughly 2.50 times its 2026 value. This reflects sustained employer-wellness demand alongside expanding telehealth applications.

What is the CAGR for the Eating-Disorder Recovery Nutrition Market 2026 to 2036?

The market is projected to grow at a 9.6% compound annual growth rate between 2026 and 2036. Bull and bear scenarios range from 10.9% to 8.3% depending on telehealth-adoption pace.

Which segment is growing fastest?

Nutrition education and recovery app platforms are the fastest-growing segment, expanding at 13.5% annually, roughly 1.41 times the overall market rate. Outpatient telehealth coaching follows at 12.0% annual growth.

Who are the major companies in the Eating-Disorder Recovery Nutrition Market?

Leading companies include Eating Recovery Center, Monte Nido, The Emily Program, Alsana, and Equip Health, with market concentration moderately concentrated at a CR5 near 33% globally.

Which country is growing fastest?

Australia is growing fastest at 12.0% annually, driven by rapidly expanding clinical treatment-center demand. South Asia and Pacific anchors much of this regional growth alongside expanding digital-health infrastructure.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Service Model

  • Residential Treatment Nutrition Programs
  • Outpatient Nutrition Coaching and Telehealth Services
  • Medical Nutrition Therapy Formulas
  • Structured Meal Support Programs
  • Nutrition Education and Recovery App Platforms

By End-Use Industry

  • Clinical Treatment Center Manufacturing
  • Employer Wellness Manufacturing
  • Health Insurance Manufacturing
  • Digital Health Platform Manufacturing
  • Institutional Healthcare Manufacturing

By Commercial Dimension

  • Direct Employer Contracts
  • Insurance Reimbursement Channels
  • Retail and E-Commerce Channels
  • Distributor and Broker Supply

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, September 2026)
Market Definition
This report covers residential treatment nutrition programs, outpatient nutrition coaching and telehealth services, medical nutrition therapy formulas, structured meal support programs, and recovery app platforms for eating-disorder nutritional rehabilitation. It excludes general weight-loss nutrition programs and standalone psychiatric therapy services without a nutritional-rehabilitation component.
Quantitative Units
USD billions (current prices); active patient-enrollment counts where applicable
Segmentation Dimensions
By Service Model; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Germany, UK, France, Japan, South Korea, China, India, Australia, Brazil, Mexico, and additional markets relevant to this sector
Key Companies Profiled
Eating Recovery Center, Monte Nido, The Emily Program, Alsana, Equip Health, Within Health, The Renfrew Center, Veritas Collaborative, Discovery Behavioral Health, Center for Discovery
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-002
Published
September 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Eating-Disorder Recovery Nutrition Market Report (2026 to 2036).

This report provides a comprehensive analysis of the global eating-disorder recovery nutrition market, covering sizing, segmentation, and regional demand dynamics across the 2026 to 2036 forecast period. It profiles twenty leading companies including Eating Recovery Center and Monte Nido, benchmarking competitive positioning across clinical-validation depth and documentation capability. The analysis examines North American treatment-infrastructure concentration, outcome-verification standardization adoption across telehealth and app-based applications, and pricing dynamics across volume, premium, and next-generation portfolio tiers. Regional deep-dives cover all seven MMA-defined geographies, with particular attention to American provider leadership.
Seven-region demand sizing with defined CAGR ranges
Twenty-company competitive benchmarking on clinical-validation depth
Segment-level growth analysis across five service models
Input cost exposure and mitigation strategy assessment
Revenue lever analysis with quantified margin impact
Anonymized case study on clinical outcome verification strategy

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts