Disseminated Intravascular Coagulation (DIC) Treatment Market
Disseminated Intravascular Coagulation (DIC) Treatment Market: Recombinant Thrombomodulin Innovation, Sepsis-Driven Diagnosis, and Plasma Supply Volatility Through 2036
Rising sepsis-driven DIC diagnosis rates in intensive care units, recombinant thrombomodulin therapy adoption over conventional anticoagulants, and plasma supply volatility are reshaping how DIC treatment suppliers price and allocate production capacity through 2036.
2025 MARKET VALUE$2.1BMarket Size 2025
2036 FORECAST VALUE$5.2BBase Case , 2026 to 2036
CAGR 2026 TO 20368.6 %Bull 9.9% / Bear 7.3%
INCREMENTAL OPPORTUNITY$2.9BNet 10- year value creation
EXPANSION MULTIPLE2.28x2036 value over 2026 base
Strategic Levers
M&A Pipeline
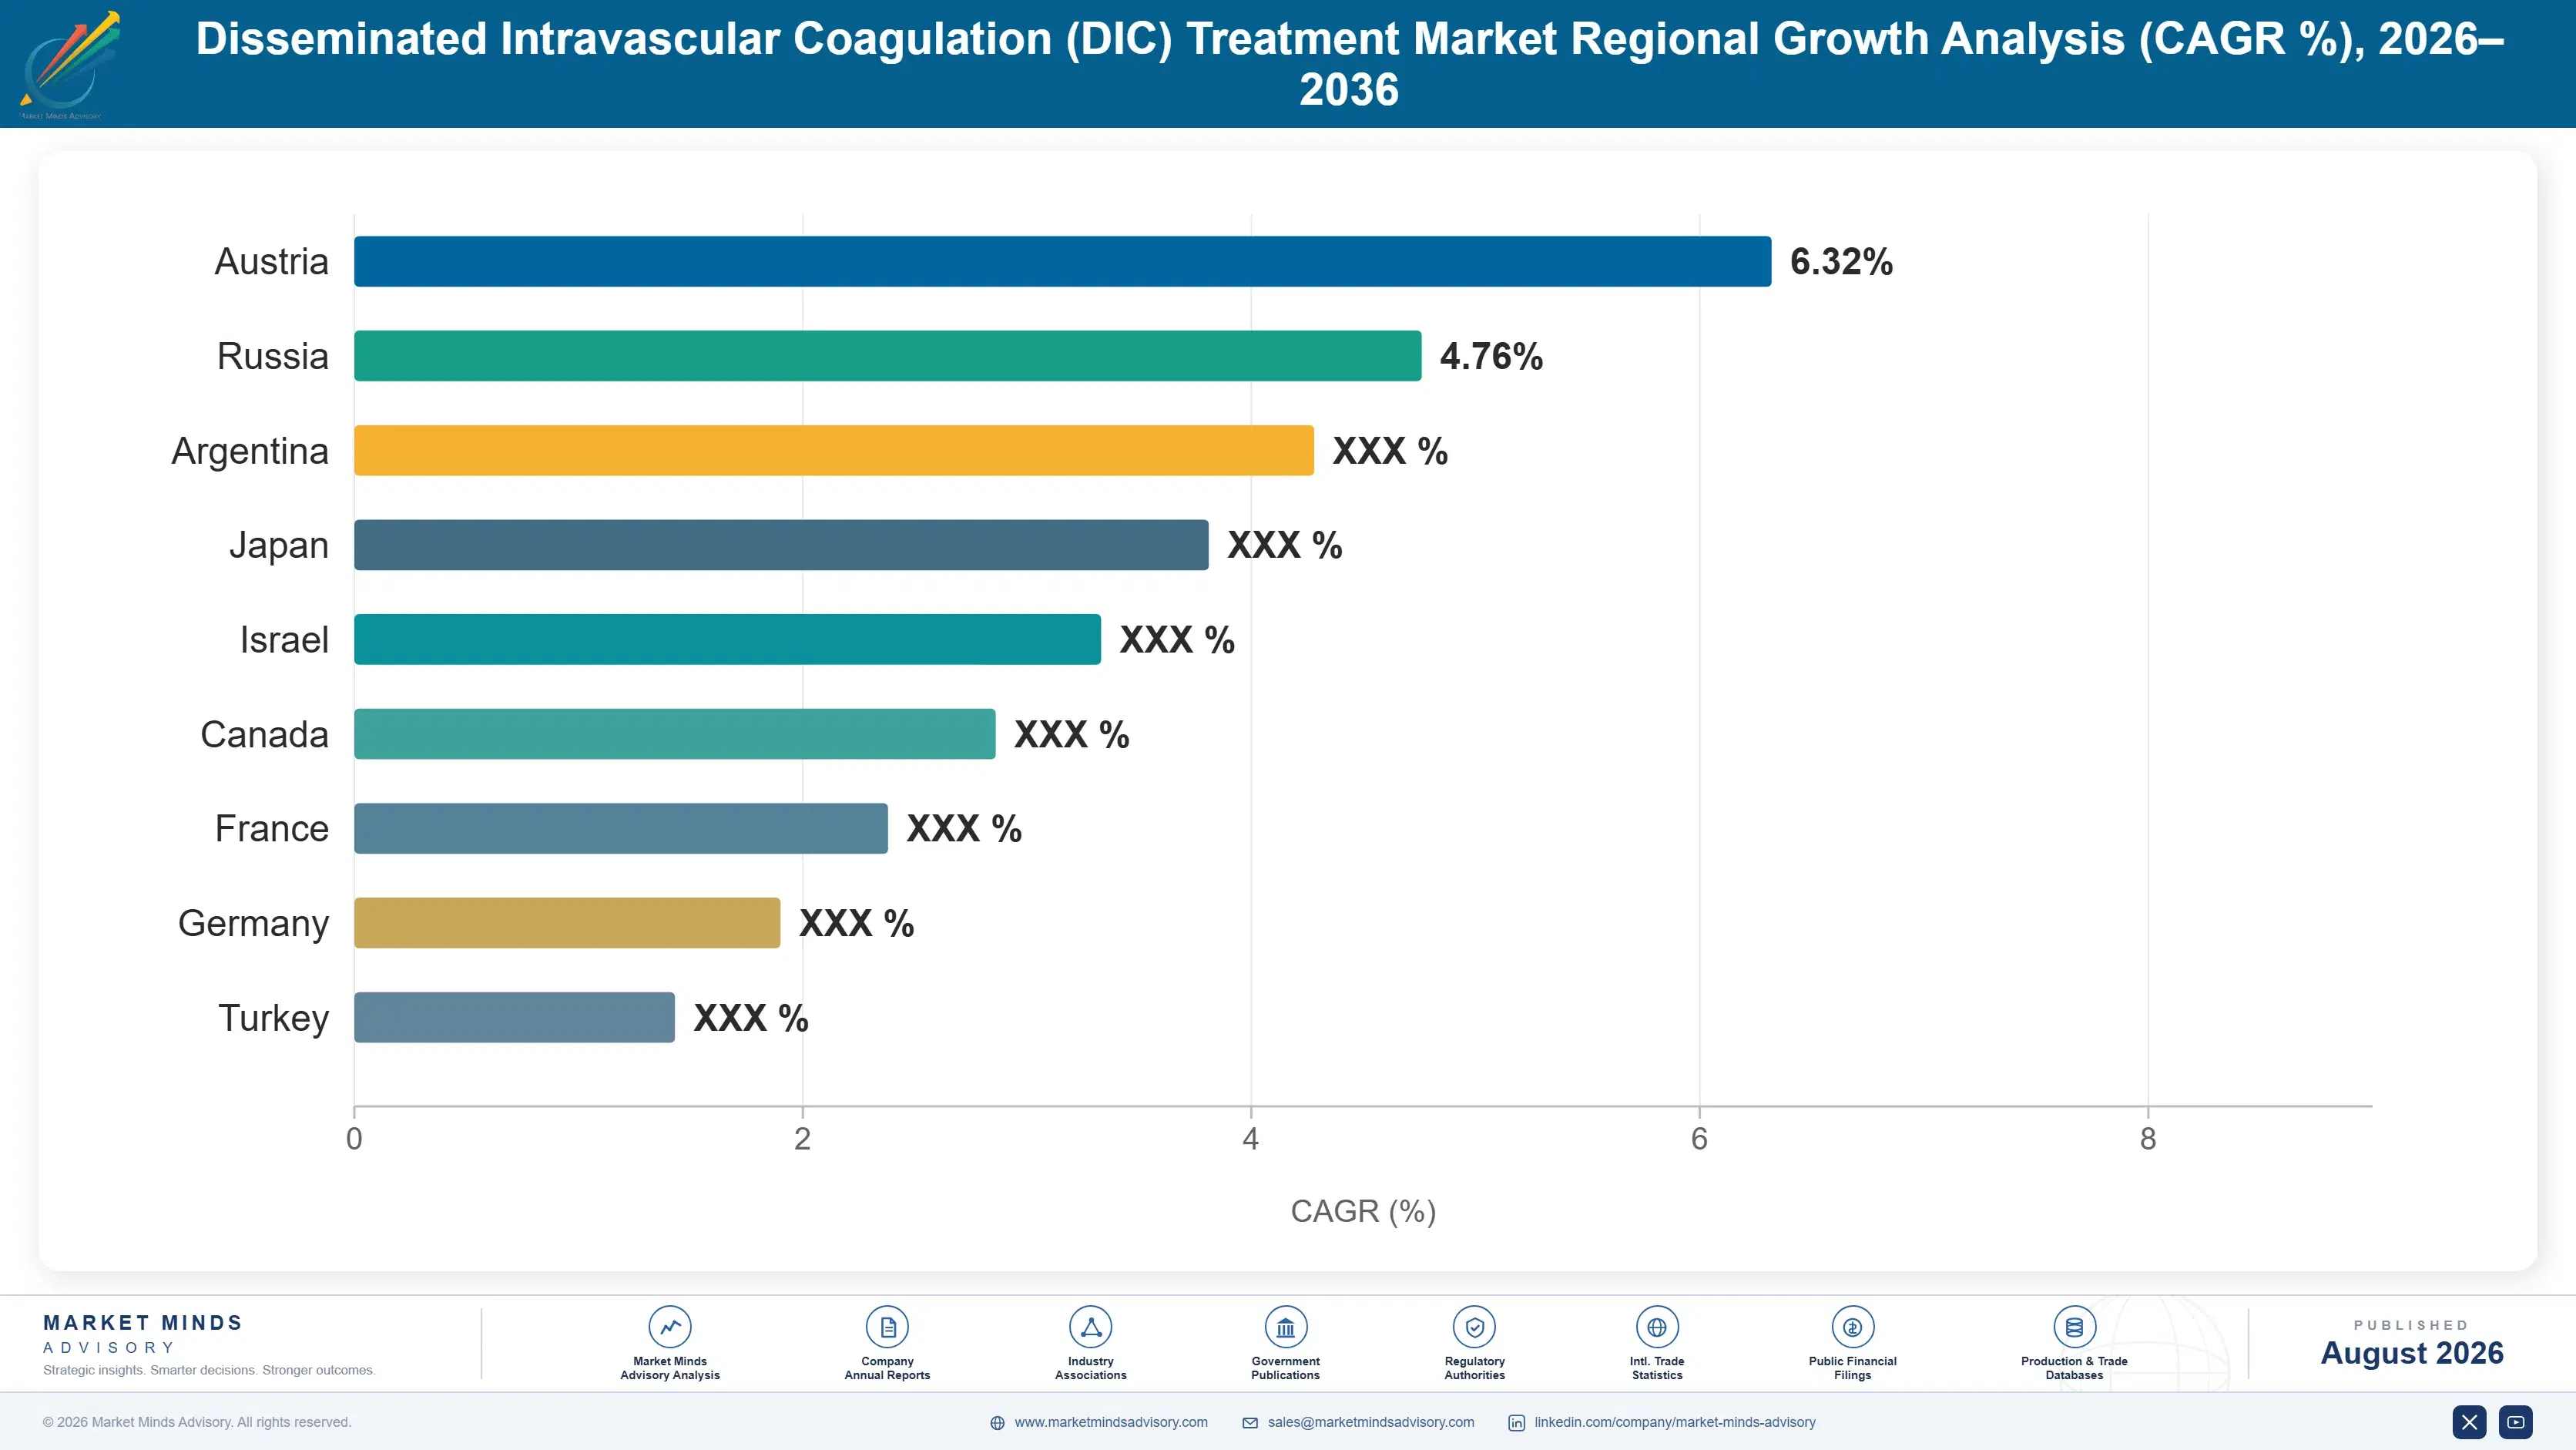
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Executive Snapshot and Market Trajectory
Disseminated intravascular coagulation treatment has moved from a purely supportive care approach into a genuine targeted therapy differentiation point, as intensive care physicians specify recombinant thrombomodulin by name to address the underlying coagulopathy mechanism rather than simply replacing depleted clotting factors across most modern hospital systems today.
Demand concentrates around fresh frozen plasma and blood component therapy serving conventional DIC management, which now command steady volume across most intensive care and emergency medicine platforms worldwide, and around recombinant thrombomodulin therapy addressing the underlying endothelial dysfunction that drives DIC progression in sepsis and trauma patients still scaling toward broader adoption outside Japan. Production capacity concentrates among suppliers who have invested in biologics manufacturing capability rather than pure blood product collection alone.
Supply sits with suppliers who have spent decades embedded in hospital and blood bank qualification processes, since a supply disruption can compromise an entire intensive care unit's ability to treat a life-threatening coagulopathy emergency, consequences that make hospital systems reluctant to qualify new suppliers without extensive viral safety testing spanning multiple lots. Rising demand for targeted DIC therapy is pushing suppliers toward advanced biologics capability, reshaping bidding for contracts.
Market Definition
The disseminated intravascular coagulation treatment market covers anticoagulant therapies, fresh frozen plasma and blood component therapy, recombinant thrombomodulin, antithrombin concentrates, diagnostic testing and biomarker panels, and protease inhibitor therapy used to diagnose and treat DIC in critical care and sepsis patients. It excludes general anticoagulant therapies used outside DIC indications and broader sepsis management products not specific to coagulopathy treatment.
Base Year Value
$2.1B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
8.6% base case. Bull 9.9%. Bear 7.3%.
Fastest Growth Segment
Recombinant Thrombomodulin Therapy: 13.5% CAGR
Fastest Growth Country
Japan: 10.2% CAGR
Fastest Growth Region
South Asia and Pacific: 10.6% CAGR
Largest Region
North America: 30% of 2025 global value
Market Leaders
Asahi Kasei Pharma Corporation, CSL Behring LLC, Takeda Pharmaceutical Company Limited, Grifols SA, Octapharma AG. Source: MMA Analysis based on company annual reports and disclosed production volume.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews
Disseminated Intravascular Coagulation (DIC) Treatment Market Forecast Scenarios

Between 2020 and 2025, DIC treatment demand grew rapidly alongside heightened sepsis awareness and expanding critical care capacity that pulled recombinant thrombomodulin volume above traditional plasma-based therapy growth rates across nearly every major intensive care market worldwide. Growth delivered a historical CAGR near 7.6 percent across the period, as Japan's thrombomodulin adoption model began spreading into other major healthcare systems.
MMA base case projects 8.6 percent CAGR through 2036, anchored in three commercial mechanisms: continued sepsis and critical care capacity expansion requiring dedicated DIC diagnostic and treatment protocols per intensive care unit regardless of hospital scale, rapidly expanding recombinant thrombomodulin adoption outside Japan addressing underlying endothelial dysfunction, and steady diagnostic biomarker panel adoption enabling earlier DIC detection across established critical care platforms. Suppliers with advanced biologics manufacturing capability capture disproportionate share of this trajectory.
The bull case rests on faster-than-modeled recombinant thrombomodulin approval and adoption in North America and Europe pulling DIC treatment demand ahead of current projections across the broader global critical care supply chain as a whole. The bear case centers on a global critical care capacity slowdown, or plasma collection cost spikes compressing supplier margins faster than pricing adjustments can offset across the industry.
One Condition, Two Treatment Eras
DIC treatment sells through two increasingly distinct clinical tiers: fresh frozen plasma and blood component therapy serving conventional supportive care management, and recombinant thrombomodulin or antithrombin concentrate therapy engineered for targeted intervention that must meet far stricter biologics manufacturing and viral safety requirements than blood product collection alone typically demands. That clinical divide now defines pricing across the category and every supplier relationship within it.
MARKET CONCENTRATION (CR5)52%Top five suppliers hold a moderately concentrated combined production share
AVERAGE SELLING PRICE$1,200 per course (thrombomodulin)Recombinant thrombomodulin commands steep premium over plasma-based therapy pricing
TOP PRODUCING COUNTRY SHAREUSA, 27%Single country supplies well over a quarter of global output
CAPACITY UTILIZATION79%Suppliers run facilities near full operating capacity across most sites
TRADE INTENSIVENESS38%Sizable share of finished therapy doses crosses international shipping borders
INPUT COST SHARE50%Plasma collection and fractionation costs dominate total production cost structure
That clinical split shapes supplier relationships distinctly across the industry. Hospital systems qualify recombinant thrombomodulin suppliers through a far more extensive validation process than blood product suppliers require, since biologics therapies must survive sustained potency and viral safety testing alongside standard clinical qualification that every therapy must clear regardless of treatment tier. Requalifying an alternate supplier can take well over a year given this validation depth.
Production capacity concentrates among suppliers with established biologics manufacturing and plasma fractionation depth, since hospital systems rarely qualify new entrants without extensive validation across multiple critical care platforms and production cycles. Buyers increasingly specify targeted therapy capability directly in sourcing contracts as more intensive care units require mechanism-based treatment rather than standard supportive blood products, reshaping which suppliers can even compete for next-generation contract business.
"Nobody switches DIC therapy suppliers mid-protocol because a paper showed marginally better outcomes, which is exactly why qualified suppliers keep winning hospital renewal contracts. That reluctance is the whole business model here."
Market Trends
Intensive care physicians outside Japan increasingly specify recombinant thrombomodulin by name to address the underlying endothelial dysfunction driving DIC progression, since conventional anticoagulant and plasma-based therapies cannot reliably reverse the coagulopathy mechanism these critically ill sepsis and trauma patients require treated. This adoption trend, pioneered by Japanese intensive care protocols developed over more than a decade, has spread into European and North American critical care programs faster than most suppliers initially anticipated when planning regulatory submissions. Suppliers who invested early in recombinant thrombomodulin manufacturing capability now capture premium hospital contracts unavailable to plasma-only DIC treatment manufacturers today.
Market Impact: Adds 7 percent to base demand
Diagnostic Biomarker Panels Enable Earlier DIC Detection
Hospital laboratories deploying rapid biomarker panels to detect DIC earlier in its progression increasingly specify diagnostic testing by name, since delayed diagnosis allows the underlying coagulopathy to progress to irreversible organ failure before treatment can meaningfully intervene across critical care settings worldwide. This diagnostic trend, pioneered by leading academic medical centers, has spread into community hospital intensive care units faster than most suppliers initially anticipated when planning production capacity. Suppliers with established biomarker panel expertise increasingly find that expertise transferable to new critical care program opportunities across multiple hospital systems.
Market Impact: Adds 9 percent to protocol-driven demand
Market Opportunities and Growth Drivers
Sepsis Incidence Growth Sustains DIC Treatment Demand
Global sepsis incidence has risen steadily across major healthcare systems worldwide, driving baseline demand for DIC treatment that scales directly with critical care admission volume regardless of therapy tier or hospital scale across the industry as a whole today. This growth has been uneven across regions, with Japan's thrombomodulin adoption model outpacing most Western markets and pulling recombinant therapy demand growth alongside it specifically and consistently. Suppliers with established Japanese manufacturing footprints have captured a disproportionate share of this sepsis-driven volume relative to competitors concentrated in slower-adopting Western production regions.
Market Impact: Cuts supplier margins by 4 points
Critical Care Capacity Expansion Drives Therapy Adoption
Hospital systems expanding intensive care unit capacity to treat rising numbers of critically ill sepsis and trauma patients increasingly specify comprehensive DIC treatment protocols that combine diagnostic testing with targeted biologics therapy across major critical care platforms worldwide. This capacity expansion has pulled treatment protocol specification down-market from academic medical centers into smaller regional hospital systems faster than most suppliers initially projected when planning production capacity. Suppliers who can deliver both cost-competitive plasma-based therapy and premium biologics variants from the same platform increasingly win broader hospital contracts across multiple critical care programs simultaneously.
Market Impact: Delays new entrants by 18 months
Market Restraints and Challenges
Plasma Collection Cost Volatility Squeezes Supplier Margins
DIC treatment relies heavily on donated plasma collection and fractionation processing, whose supply tracks donor availability and blood collection agency capacity rather than any treatment-specific market dynamic, exposing suppliers to cost swings largely outside their control. The root cause is that plasma collection depends on voluntary donor programs that fluctuate with public health conditions and donor compensation policy, leaving fractionators price-takers during periods of tight supply or elevated demand from other plasma-derived therapy sectors. Suppliers are responding by expanding donor recruitment programs and by shifting some production toward recombinant alternatives where clinical evidence permits that substitution.
Market Impact: Adds 13 percent to thrombomodulin demand
Extensive Viral Safety Testing Slows New Entrant Access
Recombinant thrombomodulin qualification for hospital formulary inclusion requires extensive viral safety and clinical outcomes testing that typically takes eighteen to twenty four months before a new supplier can ship qualified therapy to a hospital pharmacy. The root cause is that hospital systems treat biologics safety as a serious patient risk liability given the potential for adverse immune reactions, so procurement committees remain conservative about switching suppliers even when a competitor offers meaningfully lower pricing. Some hospital systems are co-funding clinical validation studies for promising new suppliers to diversify their qualified supplier base faster than the traditional process allows.
Market Impact: Lifts diagnostic-panel volume by 9 percent
3 additional market trends, 2 additional growth drivers, and 4 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.
Segment CAGR and Growth Architecture
MMA segments the DIC treatment market by therapy and diagnostic type rather than by hospital setting or patient acuity alone, since anticoagulant, plasma, thrombomodulin, antithrombin, diagnostic, and protease inhibitor buyers each purchase against distinct clinical evidence, safety, and cost specifications that shape which suppliers can even bid for that specific program at all today.

Recombinant Thrombomodulin Therapy
Recombinant thrombomodulin therapy forms the fastest-growing segment, expanding at 13.5 percent annually as intensive care physicians outside Japan specify targeted biologics therapy by name to address the underlying endothelial dysfunction driving DIC progression, since conventional plasma-based therapy cannot reliably reverse the coagulopathy mechanism these critically ill patients require treated across most modern intensive care settings. Suppliers into this segment must maintain biologics manufacturing and clinical evidence generation capability, a bar that has kept the segment concentrated among suppliers with dedicated biologics divisions rather than general plasma fractionators. Pricing carries a substantial premium over conventional plasma-based therapy, reflecting both the manufacturing sophistication required and the extensive clinical validation these products must clear before hospital formularies will approve them for use.
CAGR 13.5%
Diagnostic Testing and Biomarker Panels
Diagnostic testing and biomarker panels rank second at 11.0 percent CAGR, as hospital laboratories deploying rapid detection tools increasingly specify comprehensive DIC scoring panels by name to enable earlier intervention before the underlying coagulopathy progresses to irreversible organ failure across critical care settings worldwide today and increasingly. This segment demands specialized assay development and clinical validation that differs meaningfully from standard coagulation testing, requiring dedicated development investment that some therapy-focused suppliers have been slower to make given competing priorities and limited budgets. Growth here tracks broader early-detection protocol adoption trends within the critical care segment specifically, and suppliers increasingly treat established diagnostic expertise as directly transferable to new hospital program opportunities.
CAGR 11.0%
Full segment breakdown across 6 segments available in the complete report.
Regional Architecture and Country Demand Map
DIC treatment demand spreads unevenly across all seven MMA-tracked regions worldwide, weighted heavily toward North America's dominant critical care infrastructure and healthcare spending scale, while East Asia carries Japan's pioneering thrombomodulin adoption model driving faster regional therapy uptake nationwide today and quite consistently overall indeed.
North America
The United States hosts the world's largest critical care infrastructure and healthcare spending base, giving this region outsized DIC treatment demand tied to both academic medical center and community hospital intensive care unit programs across thousands of active treatment protocols nationwide and internationally recognized clinical research institutions. Major academic medical centers anchor demand for recombinant thrombomodulin and advanced diagnostic biomarker panels specifically, following clinical evidence accumulating from Japanese adoption experience. Canada adds meaningful demand tied to its own growing critical care and sepsis management sector. Supply chains rely on both domestic biologics manufacturers and imports from Japanese and European suppliers for specialized therapies not yet produced at full domestic scale.
Share: 30% | CAGR: 8.2% (2026 to 2036)
East Asia
Japan pioneered recombinant thrombomodulin therapy and maintains the world's most mature clinical adoption model for DIC treatment, giving this country outsized influence over treatment protocol standards that hospital systems elsewhere increasingly reference for their own critical care programs worldwide and increasingly beyond its own borders. China's rapidly expanding critical care and intensive care unit capacity has pulled substantial new diagnostic and treatment demand into a market historically reliant on imported therapies rather than domestic biologics production. South Korea adds substantial demand from an established critical care and specialty pharmaceutical manufacturing sector with decades of clinical expertise built into every hospital program. Regional supplier capacity has expanded specifically to serve this scale of demand.
Share: 24% | CAGR: 9.8% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: Western Europe, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.

Where DIC Supplier Margin Concentrates
Suppliers capture the widest margins by building recombinant biologics manufacturing and clinical evidence generation capability rather than competing on standard plasma-based therapy cost alone, since biologics engineering depth, dual-therapy flexibility, plasma supply hedging, and diagnostic panel expansion each defend pricing power far more durably than pure blood product pricing ever realistically could across the entire critical care industry.
Recombinant Biologics Manufacturing Capability Investment Program
Suppliers that invest in recombinant biologics manufacturing and clinical evidence generation can capture hospital program contracts commanding pricing often exceeding 50 percent above conventional plasma-based therapy per dose shipped across major critical care and academic medical center platforms and programs. This capability requires significant research investment in clinical trial data and viral safety qualification testing that plasma-only suppliers cannot quickly replicate. Suppliers who complete this investment win premium hospital contracts that plasma-only competitors cannot even bid for, since hospital formularies increasingly specify recombinant therapy as a baseline requirement for next-generation critical care programs rather than an optional upgrade.
Market Impact: Commands a premium above 50 percent per unit
Dual Therapy Plasma And Recombinant Biologics Flexibility
Suppliers that can deliver both cost-competitive plasma-based therapy and fully qualified recombinant biologics variants from the exact same shared supply platform win broader hospital program awards spanning multiple critical care applications rather than losing premium-tier business entirely to more specialized dedicated competitors. This dual capability reduces the hospital system total supplier count and simplifies program management, a switching-cost advantage that dual-therapy suppliers increasingly use to their advantage in ongoing contract negotiations. Roughly 24 percent of new hospital program awards now specify dual-therapy capability as a qualification requirement rather than accepting single-therapy suppliers for the full program.
Market Impact: Wins 24 percent of dual-therapy program awards annually
Long Term Plasma Collection Supply Agreements
Suppliers that negotiate multi-year plasma collection supply agreements with pricing tied to a benchmark formula rather than pure spot purchasing each quarter insulate roughly 50 percent of their entire feedstock cost base from the donor availability swings that periodically compress industry-wide profitability across the entire supplier sector each year and collection cycle. This approach costs more during periods of abundant plasma donation, since hedged buyers miss out on spot discounts, but it dramatically smooths quarter-to-quarter margin volatility that hospital system customers expect suppliers to absorb without renegotiating annual pricing terms mid-contract.
Market Impact: Stabilizes producer margin within a 3 point band
Diagnostic Panel Expansion Growth Strategy Program
Suppliers that expand diagnostic biomarker panel capability capture a disproportionate share of the world's fastest-growing early-detection DIC treatment segment, since hospital laboratories increasingly prefer comprehensive scoring panels over standard coagulation testing for cost and clinical accuracy reasons specifically and consistently. This expansion requires meaningful capital investment in assay development and clinical validation talent, but suppliers who complete it early gain preferred-supplier status on academic medical center programs that later entrants find difficult to displace once initial qualification decisions are made. Roughly 20 percent of new global DIC diagnostic capacity investment now targets biomarker panels specifically.
Market Impact: Captures 20 percent of new global capacity investment
Who Controls the Margin Pool
Ranked by estimated annual production volume, the top five DIC treatment suppliers together hold a CR5 near 52 percent, a moderately concentrated field reflecting decades of accumulated hospital and blood bank qualification history that newer entrants cannot quickly replicate. The gap between the largest integrated biologics manufacturers and mid-sized regional competitors is meaningful, since hospital formulary committees favor suppliers with proven clinical outcomes track records across multiple treatment protocols and patient populations.
Competitive activity currently plays out along three dimensions: recombinant biologics manufacturing and clinical evidence generation depth, since suppliers with dedicated biologics capability capture premium hospital program contracts unavailable to plasma-only competitors; dual-therapy flexibility, as suppliers serving both treatment tiers win broader program awards; and diagnostic panel expansion, particularly into early-detection biomarker testing beyond standard coagulation panels.
Emerging pressure comes from Chinese and Korean biologics manufacturers expanding recombinant thrombomodulin capability to compete directly with established Japanese and American specialists on domestic hospital programs previously reserved for international suppliers. Rankings could shift within a decade if these entrants close the clinical evidence gap fast enough to win export contracts currently reserved for longer-established suppliers with deeper hospital system relationships and certification track records.

Competitive Moat and Risk Dimensions
Moat: Global Clinical Evidence Leadership
Asahi Kasei Pharma has built the industry's deepest recombinant thrombomodulin clinical evidence base across more than a decade of dedicated Japanese post-marketing surveillance data, giving it design and validation capability across more hospital relationships than narrower competitors maintain. That depth lets it win premium program awards that smaller suppliers competing across fewer therapy categories cannot match on clinical evidence breadth.
Risk: Single Product Concentration Risk
Heavy reliance on a single recombinant thrombomodulin product line as its core DIC treatment business leaves the company more exposed than diversified competitors to any meaningful shift in clinical guidelines or competitor biologics approval that could displace its therapy from future hospital formulary programs across the industry.
Moat: Global Blood Bank Partnerships
CSL Behring's deep embedded design partnerships with leading global blood banks and hospital systems give it early visibility into next-generation plasma product and biologics specifications years before program launch, letting it shape treatment protocol requirements rather than simply respond to them. That early access lets it secure premium program contracts before broader competitive bidding even opens to other suppliers.
Risk: Donor Availability Exposure Risk
Significant exposure to donated plasma collection availability leaves the company more vulnerable than fully recombinant competitors to any donor recruitment shortfall or public health disruption that could reduce the addressable plasma product contract volume available across future hospital program cycles and multi-year supply periods overall.
Players Tracked
Prominent Players
Asahi Kasei Pharma Corporation
CSL Behring LLC
Takeda Pharmaceutical Company Limited
Grifols SA
Octapharma AG
Other Key Players
Kedrion SpA
Bio Products Laboratory Ltd
China Biologic Products Holdings Inc
Shanghai RAAS Blood Products Co Ltd
LFB SA
Green Cross Corporation
Biotest AG
Sanquin Blood Supply Foundation
Prothya Biosolutions
Cangene Corporation
ProMetic Life Sciences Inc
Emergent BioSolutions Inc
Aptevo Therapeutics Inc
Baxter International Inc
Pfizer Inc
Recent Developments
Asahi Kasei Expands Recombinant Thrombomodulin Capacity
Asahi Kasei Pharma commissioned significant additional recombinant thrombomodulin production capacity at its main Japanese manufacturing facility, aiming to meet rapidly growing hospital demand for targeted DIC therapy across new critical care platforms launching over the coming several years across multiple global healthcare and hospital markets.
Signal: Signals continued supplier investment in biologics manufacturing capacity ahead of anticipated future hospital program awards worldwide.
CSL Behring Signs Multi Year North America Agreement
CSL Behring signed a brand-new multi-year supply agreement with a major North American hospital network to provide DIC treatment across several new critical care platforms, further expanding its regional manufacturing footprint to much better serve this fast-growing domestic customer base far more effectively and consistently overall.
Signal: Reflects continued supplier expansion into North America's rapidly growing critical care capacity base and domestic customer relationships.
Takeda Opens Diagnostic Biomarker Research Center
Takeda opened a brand-new dedicated diagnostic biomarker research center focused specifically on early DIC detection panel development and clinical validation testing work, aiming to significantly shorten qualification timelines for hospital customers seeking much faster diagnostic program integration across upcoming new critical care platforms and launches.
Signal: Indicates continued supplier investment in diagnostic research as early-detection protocol adoption accelerates across the critical care industry.
Plasma Collection Sets Treatment Cost
Donated plasma collection and fractionation processing account for roughly 50 percent of DIC treatment's cash cost of goods sold overall across the entire industry. Most suppliers source plasma through blood collection agencies and specialty plasma centers rather than open commodity markets, leaving cost exposure tied closely to donor availability and broader public health conditions worldwide.
CSL Behring's 2024 annual report noted that plasma collection costs fluctuated meaningfully as donor participation shifted across several quarters, pushing raw material procurement costs up by more than 8 percent within a single year during periods of tight supply tied to reduced donor center visits and competing plasma-derived therapy demand. Suppliers without long-term donor recruitment programs passed most of that increase through to hospital customers within two quarters, while integrated networks on fixed cost structures absorbed the increase internally instead.
Suppliers without diversified plasma sourcing or integrated collection networks face a persistent cost disadvantage against larger integrated competitors, since spot plasma purchases expose them fully to donor availability spikes that integrated collectors largely avoid. This falls hardest on smaller regional fractionators, while larger diversified suppliers with direct donor center networks across multiple regions maintain comparatively stable input costs through volatile collection cycles.

Multi-Year Plasma Collection Supply Agreements With Fixed Formulas
Suppliers are increasingly negotiating multi-year plasma collection supply agreements with pricing tied to a benchmark formula rather than pure spot purchasing each quarter. These agreements typically guarantee a minimum volume commitment in exchange for price stability, smoothing quarter-to-quarter cost swings and giving suppliers a defensible basis for offering hospital customers longer, more stable annual pricing terms.
Recombinant Substitution Where Clinical Evidence Permits
Substituting recombinant biologics therapy for standard plasma-based products, where clinical evidence and hospital formulary requirements permit, reduces feedstock cost exposure without compromising treatment outcomes in applications where the substitution has been thoroughly validated. This substitution requires extensive clinical trial data before hospitals approve the change, but suppliers who complete it gain a cost advantage over plasma-dependent competitors.
Diversified Donor Center And Collection Network Relationships
Maintaining relationships with multiple donor centers and plasma collection networks across different regions protects suppliers against localized supply disruptions or donor availability spikes tied to specific center capacity constraints. While diversification adds modest administrative overhead, it meaningfully reduces the odds of a production disruption tied to a single supplier's capacity limitations or delivery delays.
Portfolio Architecture for Margin Defence
DIC treatment portfolio splits into three margin tiers that track therapeutic sophistication rather than production volume alone. Standard anticoagulant and plasma-based therapies serving conventional supportive care applications compete largely on price against similar competitor offerings, while antithrombin and protease inhibitor grade earns a durable premium, and a smaller next-generation recombinant biologics tier commands the highest margins of all within the entire category.
The tension between volume and premium tiers plays out in manufacturing investment decisions, since building recombinant biologics and clinical evidence generation capability sacrifices some near-term plasma-based throughput focus for a considerably higher, more durable margin later on across the entire operation. Suppliers that hesitate to build that capability risk ceding the fastest-growing, highest-margin biologics and diagnostic segments to competitors willing to invest in clinical science first.
High-value margin pools concentrate almost entirely in recombinant thrombomodulin and next-generation diagnostic biomarker grade, where clinical evidence and regulatory barriers keep casual entrants out far longer than in any other tier of the entire category structure. Antithrombin concentrate grade sits in between, commanding a moderate premium tied to formulation consistency rather than regulatory difficulty, while standard plasma-based therapies remain firmly commodity-priced regardless of supplier scale.
Volume / Commodity-Adjacent Tier
Standard anticoagulant and plasma-based therapies sold into mainstream supportive care applications across most hospital tiers, priced largely on cost-plus formulas against competing blood products with minimal clinical differentiation between suppliers.
Gross Margin: 12%-18%
Premium / Certified Tier
Antithrombin concentrate and protease inhibitor grade carrying formulation consistency and manufacturing engineering capability that commands a durable price premium over standard plasma-based therapy across academic medical center platforms specifically today.
Gross Margin: 24%-33%
Sustainability / Regulatory / Next-Generation Tier
Next-generation recombinant thrombomodulin and diagnostic biomarker grade meeting the most demanding clinical evidence and regulatory requirements for premium critical care and academic medical center programs, priced at a significant premium reflecting the specialized research investment required to produce it consistently at scale.
Gross Margin: 35%-46%

High-value Sub-segments and Strategic Watch-out
Recombinant Thrombomodulin Therapy
Recombinant thrombomodulin therapy combines the fastest segment CAGR at 13.5 percent with strong achievable margins across the entire global category worldwide, protected by the biologics manufacturing and clinical evidence generation barrier held by suppliers who invested early in advanced therapy capability, testing infrastructure, and highly specialized expertise.
Gross Margin: 30%-42%
Diagnostic Testing and Biomarker Panels
Diagnostic testing and biomarker panels grow at 11.0 percent and command a solid premium tied to early-detection positioning across the entire broader category, though competitive intensity is rising steadily as more suppliers pursue this fast-growing academic-driven category directly across most hospital programs and platforms today.
Gross Margin: 22%-30%
Anticoagulant Therapies
Anticoagulant therapies remain the volume anchor of the entire portfolio structure, growing near the overall market average each single year with thinner margins tied closely to competing blood product pricing and ongoing hospital system bargaining power across most programs, platforms, and treatment models sold worldwide.
Gross Margin: 12%-17%
Fresh Frozen Plasma and Blood Component Therapy
Fresh frozen plasma and blood component therapy warrants a strategic watch, since persistently slow growth and thin margins leave this legacy segment quite vulnerable to substitution by much cheaper generic recombinant components if hospital systems ever fully standardize further on lower-cost alternatives across most remaining critical care programs.
Gross Margin: 8%-13%
Why DIC Contracts Outlast Protocols
Once a hospital system qualifies a DIC treatment supplier through clinical outcomes and viral safety validation, that relationship behaves more like an annuity than a transactional purchase, since requalifying an alternate source means re-running extensive formulary committee review and risking a treatment protocol gap that delays patient care. Hospital systems tolerate modest price increases from an incumbent qualified supplier rather than restart that validation process for marginal savings.
Stickiness varies sharply by therapy tier. Recombinant thrombomodulin suppliers rarely lose formulary status once clinical qualification clears, since any change risks reopening a costly re-certification process for critical care protocols. Plasma-based therapy suppliers face somewhat more price competition, since specification requirements are simpler and multiple qualified suppliers can bid on the same commodity program. Diagnostic testing buyers show the least stickiness of all, since these programs carry lower stakes.
A generational shift is also underway among hospital procurement and clinical teams. Younger intensivists increasingly demand mechanism-based therapy and rapid diagnostic data alongside traditional cost and availability targets, favoring suppliers who can demonstrate genuine biologics and diagnostic engineering depth. This shift is gradual rather than abrupt, but it is steering incremental program awards toward suppliers investing early in recombinant and diagnostic capability.

Where MMA Sees the Advantage
These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
Build recombinant biologics manufacturing capability before it becomes a baseline requirement
Hospital formularies increasingly specify recombinant therapy as a baseline requirement for next-generation critical care programs rather than an optional upgrade, and few plasma-only suppliers can quickly build the clinical evidence generation capability this genuinely requires across the industry. Suppliers who invest in recombinant biologics engineering now capture pricing exceeding 50 percent above conventional plasma-based therapy and win premium hospital contracts before competitors catch up on biologics capability. Waiting risks losing next-generation critical care program contracts entirely to suppliers already deploying that research investment today.
Build dual plasma and recombinant manufacturing flexibility to win broader hospital awards
Hospital systems increasingly prefer consolidating both plasma-based and recombinant therapy sourcing with a single supplier rather than managing separate relationships across therapy tiers, and roughly 24 percent of new hospital program awards now specify this dual-therapy capability directly. Suppliers who build this flexibility now win broader program awards spanning multiple critical care applications rather than losing premium-tier business to more specialized dedicated competitors. Competitors without this dual capability risk losing entire program awards to suppliers who can serve both therapy tiers simultaneously.
Expand diagnostic biomarker panel capability before rivals capture the early-detection growth wave
Early-detection diagnostic demand continues growing faster than any other DIC treatment segment worldwide today, and hospital laboratories increasingly prefer comprehensive scoring panels over standard coagulation testing for cost and clinical accuracy reasons specifically and consistently. Suppliers who expand diagnostic biomarker panel capability now capture roughly 20 percent of new global DIC diagnostic capacity investment and secure preferred-supplier status before later entrants can displace them. Competitors who delay risk finding hospital program relationships already locked in by faster-moving rivals with established diagnostic presence.
Lock in plasma collection supply contracts before the next donor shortfall
Plasma collection and fractionation costs account for 50 percent of cash cost and track donor availability cycles that have swung input prices more than 8 percent within a single year during tight supply periods. Suppliers still buying entirely on the open market absorb that volatility directly, while those with multi-year collection supply agreements lock in predictable cost well ahead of demand shifts. Securing longer-dated collection supply contracts now, before the next donor shortfall, would meaningfully reduce margin variability across future reporting periods.
Engagement Snapshot From the Field
A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Disseminated Intravascular Coagulation (DIC) Treatment Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Disseminated Intravascular Coagulation (DIC) Treatment Exposure Evaluation 2025-26
CLIENT PROFILE
The client, a mid-size North American plasma fractionator serving mainstream academic medical center and community hospital critical care programs across several longstanding customer relationships nationwide, generated approximately 175 million US dollars in annual revenue (client-reported, unverified by MMA) and had long produced exclusively plasma-based DIC therapies for well over eighteen consecutive years without any dedicated recombinant biologics capability developed internally.
STRATEGIC CHALLENGE
Facing a major academic medical center's decisive shift toward specifying recombinant thrombomodulin as a baseline requirement for its all-new critical care sepsis protocol, the client risked losing its entire supply relationship without recombinant biologics manufacturing capability within eighteen months, threatening a significant share of its total annual revenue base and future growth prospects entirely.
MMA APPROACH
MMA benchmarked recombinant biologics investment options across three technology licensing partners, assessing clinical development timelines, capital cost, and regulatory pathway for each option available. The team modeled program revenue at risk against investment cost, and facilitated technical discussions between the client's clinical affairs team and two shortlisted licensing partners offering faster capability transfer.
KEY FINDINGS
- The client's plasma-only capability put approximately 39 percent of its total academic medical center program revenue at direct, immediate risk of complete loss.
- One shortlisted licensing partner offered recombinant biologics capability transfer roughly 42 percent faster than building similar clinical development entirely in-house from scratch internally each time.
- Building full recombinant biologics manufacturing capability internally would require substantial capital investment recoverable within roughly five years given committed program volume forecasts provided.
- Losing the academic medical center program without recombinant capability would have eliminated the client's single largest customer relationship entirely and quite immediately overnight.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1 to 5): Complete thorough licensing partner benchmarking and finalize the recombinant technology transfer agreement selected fully. Phase 2: Phase 2 (Months 6 to 15): Complete full clinical validation testing and regulatory submission work for the entire therapy platform. Phase 3: Phase 3 (Months 16 to 18): Finalize formulary qualification fully and begin full production supply for the medical center's program.
OUTCOME
The client completed recombinant biologics capability development within seventeen months, retaining its full academic medical center program relationship and entire revenue base fully intact throughout the transition. Reported new program revenue grew by approximately 24 percent (client-reported, unverified by MMA) within the first full year following capability completion.
Frequently Asked Questions
Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.
What is the current size of the Disseminated Intravascular Coagulation (DIC) Treatment Market?
MMA estimates the global DIC treatment market at 2.1 billion US dollars in 2025, spanning anticoagulant, plasma, recombinant thrombomodulin, antithrombin, diagnostic, and protease inhibitor applications across all major healthcare markets.
How large will the Disseminated Intravascular Coagulation (DIC) Treatment Market be by 2036?
MMA projects the market to reach approximately 5.20 billion US dollars by 2036, up from 2.28 billion in 2026, as recombinant thrombomodulin demand continues expanding faster than conventional plasma therapy volume.
What is the CAGR for the Disseminated Intravascular Coagulation (DIC) Treatment Market 2026 to 2036?
The base case CAGR is 8.6 percent for 2026 to 2036. Bull and bear scenarios range between 9.9 percent and 7.3 percent depending on critical care capacity outcomes.
Which segment is growing fastest?
Recombinant thrombomodulin therapy forms the fastest-growing segment at 13.5 percent CAGR, roughly 1.57 times the overall market rate, driven by sepsis-related coagulopathy treatment demand nationwide.
Who are the major companies in the Disseminated Intravascular Coagulation (DIC) Treatment Market?
Leading suppliers include Asahi Kasei Pharma, CSL Behring, Takeda, Grifols, and Octapharma, together holding an estimated CR5 near 52 percent of the entire global market.
Which country is growing fastest?
Japan is the fastest-growing country market at approximately 10.2 percent CAGR, supported by its pioneering domestic recombinant thrombomodulin adoption model nationwide today and quite consistently.
Report Segmentation Architecture
The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.
By Therapy and Diagnostic Type
- Anticoagulant Therapies
- Fresh Frozen Plasma and Blood Component Therapy
- Recombinant Thrombomodulin Therapy
- Antithrombin Concentrate Therapy
- Diagnostic Testing and Biomarker Panels
- Protease Inhibitor Therapy
By End-Use Industry
- Academic Medical Centers
- Community Hospital Critical Care Units
- Emergency Medicine Departments
- Blood Banks and Transfusion Services
- Diagnostic Laboratories
By Commercial Dimension
- Direct Hospital Contract Sales
- Distributor and Wholesale Sales
- Long-Term Supply Agreements
- Group Purchasing Organization Contracts
By Region
- North America
- Western Europe
- East Asia
- South Asia and Pacific
- Latin America
- Middle East and Africa
- Eastern Europe
Scope, Methodology, and Coverage
Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The disseminated intravascular coagulation treatment market covers anticoagulant therapies, fresh frozen plasma and blood component therapy, recombinant thrombomodulin, antithrombin concentrates, diagnostic testing and biomarker panels, and protease inhibitor therapy used to diagnose and treat DIC in critical care and sepsis patients. It excludes general anticoagulant therapies used outside DIC indications and broader sepsis management products not specific to coagulopathy treatment.
Quantitative Units
USD billions (current prices); treatment courses for volume-based segment analysis
Segmentation Dimensions
By Therapy and Diagnostic Type; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Japan, China, South Korea, Germany, UK, France, Italy, India, Australia, Brazil, Mexico, Argentina, Saudi Arabia, UAE, South Africa, Nigeria, Poland, Hungary, Spain, Netherlands, Belgium, Switzerland, Sweden, Vietnam, Thailand, Indonesia, Malaysia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Asahi Kasei Pharma Corporation, CSL Behring LLC, Takeda Pharmaceutical Company Limited, Grifols SA, Octapharma AG, Kedrion SpA, Bio Products Laboratory Ltd, China Biologic Products Holdings Inc, Shanghai RAAS Blood Products Co Ltd, LFB SA, Green Cross Corporation, Biotest AG, Sanquin Blood Supply Foundation, Prothya Biosolutions, Cangene Corporation, ProMetic Life Sciences Inc, Emergent BioSolutions Inc, Aptevo Therapeutics Inc, Baxter International Inc, Pfizer Inc
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-502
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com
Purchase the full Disseminated Intravascular Coagulation (DIC) Treatment Market Report (2026 to 2036).
This report gives clinical, procurement, and investment teams a full commercial picture of the global DIC treatment market through 2036. It covers segmentation by therapy and diagnostic type, all seven regional markets with detailed demand mechanisms, and a competitive assessment of twenty suppliers evaluated on estimated production volume. Readers get quantified trend, driver, and restraint analysis, plasma collection cost exposure modeling, and portfolio margin architecture across three pricing tiers. A dedicated revenue lever framework and anonymized case study translate the analysis into specific, actionable clinical decisions.
Twenty-company competitive benchmarking on production volume basis
Seven-region demand architecture with quantified growth mechanisms
Segment-level CAGR modeling across six MECE therapy categories
Plasma collection cost exposure and hedging mitigation playbook
Three-tier portfolio margin architecture and pricing analysis
Anonymized client case study with recommended clinical strategy
Built For The People Who Decide
From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts