Market Minds Advisory
Cluster Headache Syndrome Market

Cluster Headache Syndrome Market: CGRP Biologic Adoption and Specialist Access Analysis 2026 to 2036

Cluster headache treatment is shifting from generic acute therapies and off-label preventives toward CGRP monoclonal antibody biologics and neurostimulation devices, as headache specialists and payers increasingly demand documented efficacy data for this rare condition.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$1.2BMarket Size 2025
2036 FORECAST VALUE$3.5BBase Case , 2026 to 2036
CAGR 2026 TO 203610.2 %Bull 11.5% / Bear 8.9%
INCREMENTAL OPPORTUNITY$2.2BNet 10- year value creation
EXPANSION MULTIPLE2.64x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Cluster headache treatment is shifting decisively toward CGRP monoclonal antibody biologics and neurostimulation devices, as headache specialists move away from generic acute therapies and off-label preventives that dominated care for a historically underdiagnosed condition, forcing manufacturers to invest in rare-disease clinical trial data that smaller generic manufacturers cannot easily fund.
CGRP monoclonal antibody preventive therapies and neurostimulation devices capture the fastest growth as headache specialists increasingly prescribe disease-specific biologics rather than repurposed migraine or hypertension drugs used off-label for decades. North America leads demand given its established headache specialist infrastructure and CGRP biologic reimbursement pathways, supplying three in ten units sold, while South Asia and Pacific grows fastest as expanding neurology specialist access broadens cluster headache diagnosis and treatment demand beyond mature developed-market replacement volume.
Competitive intensity centers on five manufacturers holding three in five units, most having built franchises through clinical trial investment and headache specialist relationships rather than manufacturing scale. Rare-disease clinical substantiation depth and specialist prescriber reach separate manufacturers positioned for premium biologic placement from competitors dependent on generic off-label therapies. Digital headache tracking and combination biologic-device protocols are opening a smaller but fast-growing niche that established manufacturers are only beginning to pursue.
Market Definition
This report covers pharmaceutical and device-based treatments for cluster headache, including acute triptans, oxygen therapy, CGRP monoclonal antibody preventive biologics, neurostimulation devices, corticosteroid transitional therapies, and verapamil and other preventive pharmacotherapy. It excludes treatments marketed exclusively for migraine or tension-type headache without cluster headache indication, and general pain management devices not specific to headache disorders. Scope covers global sales revenue of finished cluster headache treatment products.
Base Year Value
$1.2B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
10.2% base case. Bull 11.5%. Bear 8.9%.
Fastest Growth Segment
CGRP Monoclonal Antibody Preventive Therapies: 16.8% CAGR
Fastest Growth Country
Germany: 11.9% CAGR
Fastest Growth Region
South Asia and Pacific: 12.3% CAGR
Largest Region
North America: 30% of 2025 global value
Market Leaders
Eli Lilly, Amgen, Teva Pharmaceutical Industries, electroCore, and Medtronic. Source: MMA Analysis based on company annual reports and investor filings.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Cluster Headache Syndrome Market Forecast Scenarios

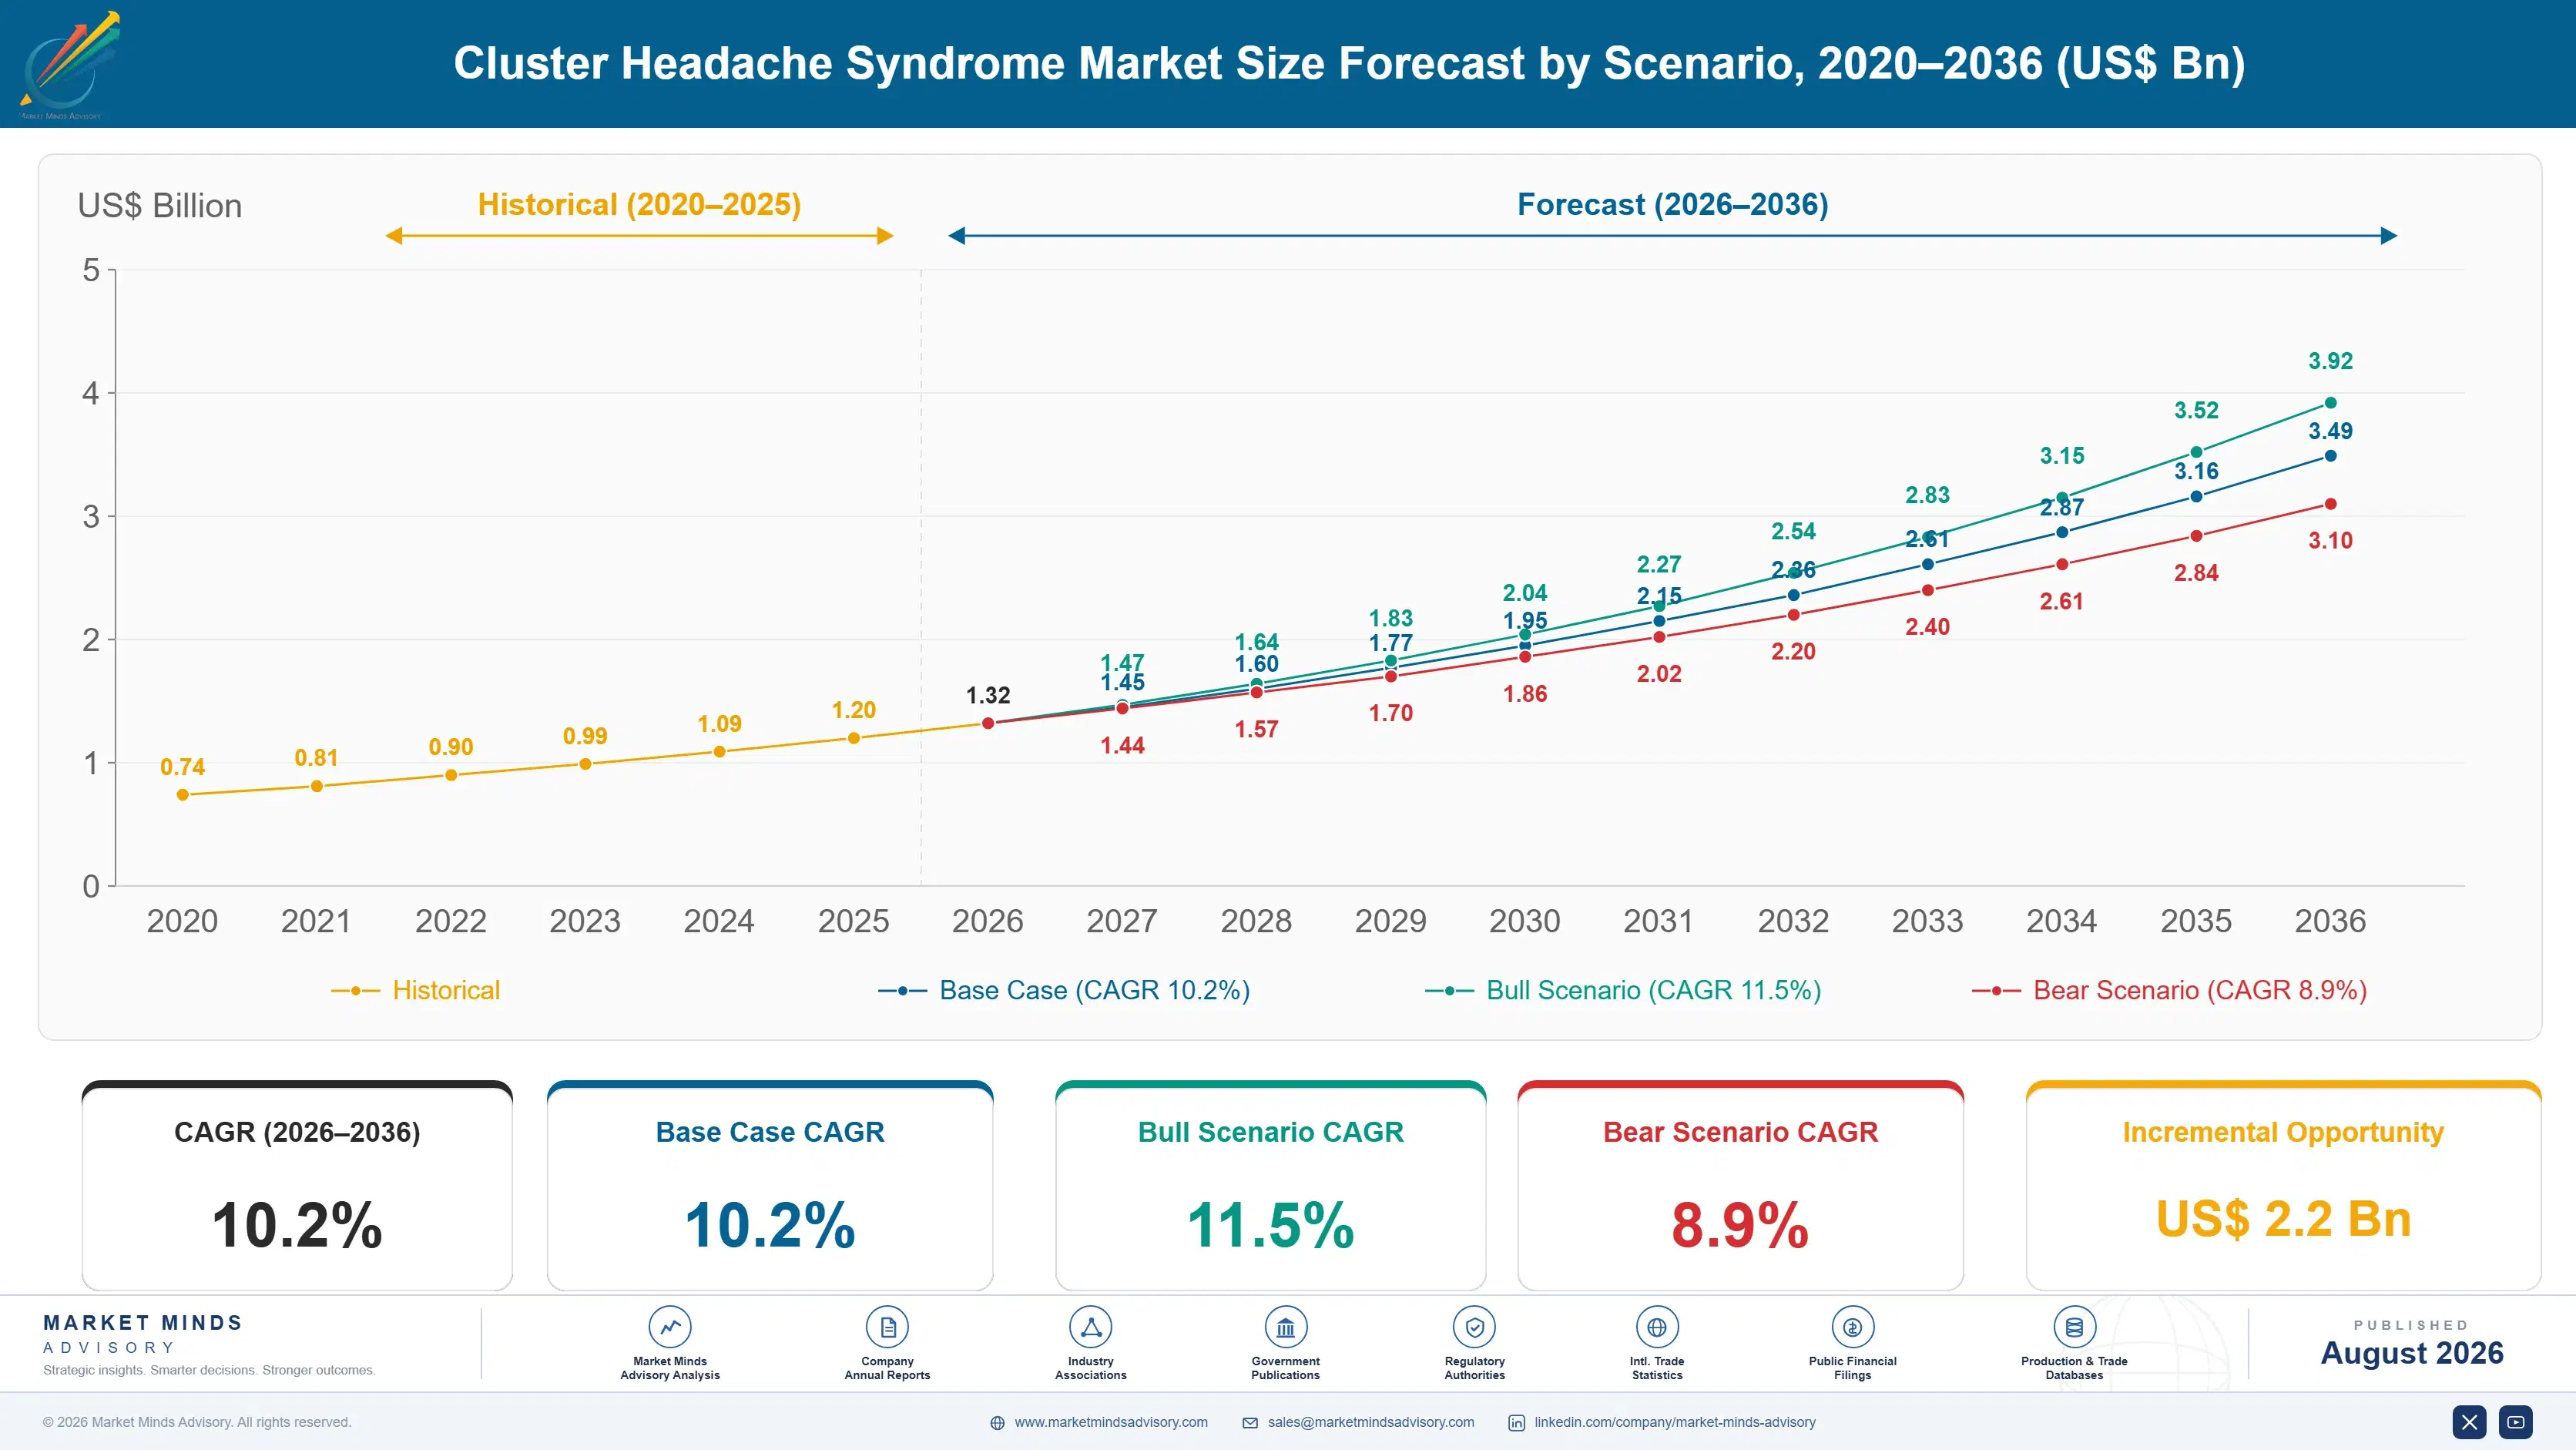
cluster-headache-syndrome-market-size-forecast-scenario-1787304735723
Cluster headache treatment demand grew steadily through 2020 and 2021 as telehealth expansion improved access to headache specialist diagnosis despite pandemic disruption, then accelerated through 2022 and 2023 as CGRP monoclonal antibody biologics gained expanded regulatory approval for cluster headache indications. Shipments grew at a 9.0% historical rate, with CGRP biologics accelerating fastest as specialists shifted prescribing away from off-label alternatives.
The base case assumes 10.2% growth through 2036, anchored by three mechanisms. First, expanding regulatory approval of CGRP biologics for cluster headache is pulling prescribing away from off-label migraine and hypertension drugs used previously. Second, headache specialist awareness and diagnosis pathways are expanding the addressable treated patient population beyond the underdiagnosed base. Third, neurostimulation device adoption is expanding average selling price as specialists combine device and biologic protocols rather than relying on pharmacotherapy.
The bull case rests on faster CGRP biologic adoption and accelerated headache specialist diagnosis capacity, which could pull forward premium treatment demand and push growth toward 11.5%. The bear case centers on payer scrutiny: if insurers tighten prior authorization requirements for CGRP biologics faster than manufacturers can demonstrate cost-effectiveness, prescribing constraints could soften demand and drag growth toward 8.9% as patients face longer treatment access delays.

CGRP Biologic Adoption and Specialist Access Economics

Cluster headache treatment demand sits at the intersection of two forces: a biologic adoption shift that keeps pulling prescribing from off-label generic pharmacotherapy toward disease-specific CGRP monoclonal antibodies faster than conventional treatment protocols were designed to accommodate, and a diagnosis expansion that pulls treated patient demand into headache specialist capacity previously served by limited neurology referral pathways. Manufacturers that invest in rare-disease clinical s
CR5 CONCENTRATION61%Top five manufacturers hold roughly three in five units
AVERAGE TREATMENT COST$1,850 per monthCGRP biologics carry a premium over generic pharmacotherapy
TOP PRESCRIBING COUNTRY SHARE23%United States accounts for the largest single treatment share
DIAGNOSIS RATE42%Estimated share of cluster headache patients receiving formal diagnosis
SPECIALIST REFERRAL RATE36%Patients referred to headache specialist centers rather than general neurology
BIOLOGIC PRESCRIBING SHARE29%Preventive treatment volume prescribed as CGRP biologics rather than generic
Commercial character is defined by substantiation-driven prescribing: manufacturers with strong clinical trial data and specialist relationship reach capture disproportionate prescriber trust as treatment protocols standardize around biologics proven against documented efficacy benchmarks. Standard generic acute therapies remain a large but slower-growing volume base, priced across commodity pharmacy channels, while CGRP biologic and neurostimulation platforms command premium pricing tied to substantiation data smaller entrants struggle to match.
Over the next decade, expect prescribing to keep consolidating around manufacturers with proven CGRP biologic capability: specialists are standardizing treatment around biologics offering validated efficacy data, rewarding early movers in trial investment. Consolidation among smaller generic-only manufacturers is likely as clinical trial costs outpace what niche vendors can fund alone.
"For decades cluster headache patients were told to just breathe pure oxygen through a mask during an attack. Now there's a monthly injection built specifically for their condition, not repurposed from a migraine drug."
Director, Neurology and Rare Disease Therapeutics Practice · MMA Neurology and R

Market Trends

CGRP Biologics Rapidly Displace Off-Label Prescribing

Headache specialists are increasingly prescribing CGRP monoclonal antibody biologics developed specifically for cluster headache rather than repurposing migraine or hypertension drugs used off-label for decades. Manufacturers have expanded rare-disease clinical trial investment and regulatory approval capability significantly over the past several years, and specialists increasingly specify disease-specific biologics by default when treating newly diagnosed patients. Major headache centers report CGRP biologic prescribing now covers more than a quarter of preventive treatment volume, up sharply from a small base less than a decade ago. This shift has accelerated markedly since 2023.
Market Impact: Adds 180 new headache specialist ce
Neurostimulation Devices Expand Non-Pharmacological Treatment Options

Headache specialists are increasingly requiring non-pharmacological treatment options that reduce medication burden beyond what conventional oral and injectable pharmacotherapy alone can deliver. Manufacturers have expanded neurostimulation device miniaturization and non-invasive delivery capability significantly over the past two years, letting specialists offer device-based treatment without requiring the systemic side effects that chronic pharmacotherapy use demands. Chronic cluster headache patients report the fastest uptake, since neurostimulation devices align with patient preference for treatment options beyond daily medication. Several major headache centers expanded neurostimulation device access further in late 2025. Insurers report growing willingness to cover device therapy since early 2025.
Market Impact: Adds 25-40% ASP premium overall

Market Opportunities and Growth Drivers

Expanding Specialist Diagnosis Broadens Treated Population

Headache specialist referral networks and improved diagnostic awareness are expanding the addressable treated patient population beyond the historically underdiagnosed base that relied on general practitioner misdiagnosis for years. Several major health systems have expanded headache specialist referral capacity meaningfully across markets over the past few years, and each new specialist center increasingly specifies structured cluster headache diagnostic protocols rather than generic headache classification. Manufacturers that built strong specialist education and referral networks early are winning most new prescribing relationships signed across the past two years. This advantage is compounding fastest in multi-country specialist training programs.
Market Impact: Limits substantiation access to 39%

Clinical Trial Investment Sustains Premium Biologic Demand

Specialist prescribers increasingly specify documented clinical trial data that conventional generic off-label pharmacotherapy cannot always demonstrate without a supplementary substantiation investment. Several major manufacturers have expanded clinical trial scope meaningfully over the past several years, and each new treatment protocol cycle increasingly treats documented efficacy data as a prescribing compliance requirement rather than an optional consideration. Manufacturers with the strongest clinical trial platforms are winning the large majority of new specialist prescribing relationships, since treatment protocols treat documented substantiation as a near-mandatory requirement across most premium categories nationwide today across every major regional market.
Market Impact: Limits diagnosis rate to 42%

Market Restraints and Challenges

Clinical Trial Cost Limits Smaller Manufacturer Adoption

Rare-disease clinical trial investment required for cluster headache indication approval carries higher cost than conventional headache pharmacotherapy development, putting full substantiation out of reach for smaller manufacturers even where documented specialist demand justifies the investment in premium biologic development. The root cause is that rare-disease trials require larger recruitment networks and longer study duration than common-condition trials given the smaller patient population. This restricts substantiation to well-funded manufacturers and established biologic developers where clinical data offers placement advantages. Manufacturers mitigate the gap by pursuing multi-country recruitment consortium partnerships. This gap is widest across smaller regional manufacturers with limited research budgets.
Market Impact: Lifts biologic prescribing share to

Underdiagnosis Still Limits Addressable Treated Population

Cluster headache remains substantially underdiagnosed relative to its estimated prevalence, and the root cause is that general practitioners historically misclassify cluster headache as migraine or sinus-related pain without headache specialist referral. This restricts addressable treated population even where documented biologic and device treatments already demonstrate measurable efficacy outcomes. Manufacturers report diagnosis awareness as their single largest constraint on expanding treated population further. Manufacturers mitigate the gap by investing in physician education and diagnostic awareness campaigns. This gap is widest across regions with limited headache specialist infrastructure. Emergency department misdiagnosis compounds the problem further across many regions.
Market Impact: Adds 14.2% neurostimulation segment
4 additional market trends, 4 additional growth drivers, and 4 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows treatment modality, the primary driver of prescribing pathway, delivery mechanism, and price point across triptan, oxygen, CGRP biologic, neurostimulation, corticosteroid, and verapamil formats. CGRP monoclonal antibody preventive therapies and neurostimulation devices carry the fastest growth as specialists increasingly prioritize documented disease-specific efficacy over the repurposed off-label pharmacotherapy that dominated cluster headache treatment for decades.
cluster-headache-syndrome-market-market-share-analysis-1787304736270

CGRP Monoclonal Antibody Preventive Therapies

CGRP monoclonal antibody preventive therapies are the fastest-growing segment as specialists increasingly require disease-specific biologics that conventional off-label migraine or hypertension drugs alone cannot fully deliver given rising expectations for documented cluster-headache-specific efficacy. Manufacturers have expanded rare-disease clinical trial investment and regulatory approval capability significantly over the past two years, letting specialists prescribe biologics with documented efficacy data rather than relying on off-label repurposing under increasing scrutiny from payers. Chronic and episodic cluster headache patients report the fastest uptake among specialists where documented attack-frequency reduction directly affects treatment decisions. Pricing carries a substantial premium over conventional generic pharmacotherapy, reflecting the clinical trial and regulatory investment increasingly built into new biologic product lines across most major markets today.
CAGR 16.8%

Neurostimulation Devices

Neurostimulation devices rank second-fastest as specialists increasingly require non-pharmacological treatment options that conventional oral and injectable pharmacotherapy cannot provide without systemic side effect burden. Neurostimulation gives specialists a treatment option that reduces patient medication exposure while maintaining the attack-frequency reduction efficacy that unsubstantiated device alternatives cannot always match, a capability increasingly valued as patients face growing treatment fatigue from chronic pharmacotherapy regimens. Specialists report the fastest adoption among chronic cluster headache categories where non-invasive stimulation directly reduces daily medication burden. Average device price is rising modestly as neurostimulation platforms expand from basic stimulation to full-featured programmable clinical technology. Manufacturers report growing demand from patients seeking to reduce dependence on daily oral medication regimens entirely.
CAGR 14.2%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

Demand concentrates where headache specialist infrastructure and CGRP biologic reimbursement diverge most sharply. North America leads on established headache specialist infrastructure and biologic reimbursement pathways, Western Europe follows on Germany's headache center network, and South Asia and Pacific posts the fastest regional growth as expanding neurology specialist access broadens diagnosis.

North America

The United States' established headache specialist infrastructure and CGRP biologic reimbursement pathways anchor North American demand, as treatment protocols standardize around disease-specific biologics ahead of most other regions given sophisticated payer coverage frameworks for rare neurological conditions. Major headache centers are converting off-label prescribing volume into disease-specific biologic product lines, replacing repurposed migraine drugs with documented cluster-headache-specific technology. Specialist referral network expansion adds a second demand pool, since primary care physicians increasingly incorporate structured diagnostic protocols into broader neurology referral pathways. Distributors report growing interest in neurostimulation devices, since specialist procurement committees increasingly require documented attack-frequency reduction data before approving new device adoption. Canadian provincial health systems show a similar conversion trajectory across most secondary markets.
Share: 30% | CAGR: 9.6% (2026 to 2036)

Western Europe

Germany's dense headache specialist center network anchors Western European demand, with German neurologists among the earliest adopters of CGRP biologics for cluster headache following European Medicines Agency approval, and the region's growth reflects both established reimbursement frameworks and structured specialist referral pathways. British and French headache centers increasingly favor CGRP biologics and neurostimulation for cluster headache treatment, reflecting the region's structured evidence-driven prescribing culture. The European Headache Federation's updated treatment guidance continues shaping which therapies qualify for national reimbursement. Growth trails East Asia's pace because the region's specialist infrastructure is already mature, leaving comparatively less room for rapid volume expansion in absolute terms. Nordic and Italian headache centers show a similar conversion trajectory across most secondary markets.
Share: 23% | CAGR: 8.7% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
cluster-headache-syndrome-market-country-cagr-analysis-1787304736786

Where Cluster Headache Manufacturers Can Expand Margin

Cluster headache treatment manufacturers face a choice: compete on price for generic off-label pharmacotherapy, or build defensible margin through rare-disease clinical substantiation leadership, neurostimulation device capability, and headache specialist relationship reach. The levers below identify where manufacturers are converting the biologic adoption shift into durable pricing power rather than treating cluster headache treatment as an undifferentiated commodity.

Lead Rare-Disease Clinical Trials Ahead of Approval

Manufacturers that develop and validate rare-disease clinical trial data 12 to 18 months ahead of major regulatory approval cycles win first access to specialist prescribing relationships before competitors catch up, since headache specialist treatment protocols typically finalize prescribing preferences a year or more before formulary renewal dates. Early substantiation leadership also lets manufacturers charge a 25 to 40 percent premium over conventional generic pharmacotherapy, since documented efficacy data directly reduces specialist prescribing liability exposure. Manufacturers that under-invested in clinical trials during the prior demand cycle are now losing prescribing relationships to competitors with proven substantiated biologics.
Market Impact: Captures a 25-40% price premium eac

Expand Neurostimulation Device and Digital Tracking Capability

Dedicated neurostimulation device and digital headache tracking programs that document actual attack-frequency reduction and patient adherence improvement convert a commodity pharmacotherapy relationship into a differentiated premium platform worth roughly 24 to 34 percent more per patient than standard pharmacotherapy-only alternatives. Headache specialists increasingly require documented device efficacy as a prescribing condition, since undocumented device claims create liability exposure that treatment protocol committees actively scrutinize during formulary review. Manufacturers that invest in device capability early are converting standard pharmacotherapy volume into premium specialist relationships that competitors without comparable capability cannot easily replicate. This advantage compounds further as specialist protocol sophistication increases.
Market Impact: Adds a 24-34% pricing premium for n

Expand Emerging-Market Specialist Distribution Depth Fast

Building dedicated specialist education and distribution capability across South Asia and Latin America, rather than treating those markets as a secondary outlet for developed-market treatment export surplus, captures a demand pool growing roughly 25 percent even as developed-market volume growth moderates. Headache centers in expanding specialist-infrastructure markets increasingly favor manufacturers with established local education and distribution support, since clinical trust and local regulatory documentation outweigh brand recognition for budget-constrained prescribing decisions. Manufacturers committed to this distribution depth are capturing multi-year specialist relationships that competitors focused on developed markets cannot easily replicate without local investment.
Market Impact: Captures an emerging-market segment

Expand Physician Education and Diagnostic Awareness Capability

Building dedicated physician education and diagnostic awareness capability, rather than relying on passive referral patterns between general practitioners and headache specialists, lifts average specialist prescribing retention by roughly 22 percent through the diagnostic consistency reliability that passive referral cannot deliver. Headache specialists increasingly favor manufacturers who support consistent diagnostic training directly, since inconsistent diagnosis translates into the delayed-treatment incidents that patients and specialists actively work to avoid. Manufacturers already committed to this education are winning multi-year prescribing relationships with major headache centers ahead of passive-referral competitors. This advantage compounds further as specialist network consolidation continues nationwide overall.
Market Impact: Lifts average specialist prescribin

Who Controls the Margin Pool

The top five manufacturers, Eli Lilly, Amgen, Teva Pharmaceutical Industries, electroCore, and Medtronic, hold roughly sixty-one percent of unit volume, leaving a fragmented tail of generic and specialized manufacturers to compete for the remainder. The gap between the leading two manufacturers and the next tier is widening as rare-disease clinical trial costs outpace what smaller manufacturers can justify funding.
Current activity centers on three fronts: rare-disease clinical substantiation capability development aimed at regulatory approval cycles, neurostimulation device expansion aimed at capturing non-pharmacological demand, and emerging-market distribution capability aimed at capturing specialist infrastructure growth ahead of undertrained competitors. German and Japanese manufacturers are also expanding export capacity as domestic production scales past what local emerging-market demand alone can absorb.

Emerging pressure comes from two directions. Well-funded biologic specialists with strong clinical trial and regulatory capability are gaining specialist prescribing share from diversified generic-focused manufacturers slower to build documented substantiation technology. At the premium end, neurostimulation device specialists with strong headache center relationships are winning large multi-country distribution contracts that established pharmacotherapy-focused manufacturers have historically held, and rankings among the top ten manufacturers could shift within three to four years if that trend continues.
cluster-headache-syndrome-market-company-positioning-matrix-1787304737336

Competitive Moat and Risk Dimensions

ELI LILLY

Moat: Deep Rare-Disease Trial Depth

Eli Lilly's decades of clinical trial investment behind its CGRP biologic portfolio give the company a substantiation depth few competitors can match in breadth. That research depth lets the company fund ongoing rare-disease trial investment that smaller generic-focused manufacturers cannot service alone, sustaining premium specialist prescribing relationships across major headache center networks.
ELI LILLY

Risk: Narrower Neurostimulation Device Portfolio

Eli Lilly's biologic-focused pipeline means neurostimulation device development moves more slowly than at focused device specialist competitors, a gap that device specialists could exploit as headache specialists increasingly favor combination biologic-device treatment protocols over pharmacotherapy-only approaches. Competitors that built dedicated device capability earlier are capturing premium combination-protocol placement faster than the company's biologic-focused model currently allows.
ELECTROCORE

Moat: Deep Non-Invasive Neurostimulation Expertise

electroCore built non-invasive vagus nerve stimulation expertise over years that translates directly into headache specialist trust few generalist competitors can replicate quickly. That device depth lets the company win high-volume non-pharmacological prescribing decisions based on documented attack-frequency reduction reliability, positioning it well for the segment of demand prioritizing device specialization over broad biologic portfolio breadth.
ELECTROCORE

Risk: Narrower Pharmaceutical Biologic Portfolio

electroCore's comparatively narrow pharmaceutical biologic portfolio limits its ability to offer headache centers a fully integrated treatment protocol spanning device and biologic categories in a single prescribing relationship. As specialists increasingly prefer integrated combination-protocol relationships, this narrower scope could become a bigger competitive disadvantage than it represents today.

Players Tracked

Prominent Players

Eli Lilly
Amgen
Teva Pharmaceutical Industries
electroCore
Medtronic

Other Key Players

Lundbeck
Amneal Pharmaceuticals
Viatris
Currax Pharmaceuticals
Collegium Pharmaceutical
Theranica
Cala Health
NeurAxis
Linde Healthcare
Air Liquide Healthcare
Chiesi Farmaceutici
Impel Pharmaceuticals
Zosano Pharma
GlaxoSmithKline
Sanofi

Recent Developments

JANUARY 2025

Eli Lilly Publishes New Cluster Headache Trial Data

Eli Lilly published peer-reviewed clinical trial results for its CGRP biologic in episodic cluster headache, adding substantiation data aimed at headache specialists specifying documented attack-frequency reduction evidence for prescribing decisions. The move is a research publication, not an acquisition, following rising specialist demand for validated substantiation options. Centers requested it.
Signal: Signals specialist demand for rare-disease
MAY 2025

Medtronic Acquires Neurostimulation Device Specialist

Medtronic acquired a small neurostimulation device company specializing in non-invasive sphenopalatine ganglion stimulation technology, folding it into its existing neurology division. The acquisition brings device capability in-house rather than continuing to partner externally, and the deal closed for an undisclosed sum. Terms were not otherwise disclosed.
Signal: Confirms leading cluster headache manufact
SEPTEMBER 2025

Teva Signs Distribution Agreement With German Headache Network

Teva Pharmaceutical Industries signed a multi-year distribution agreement with a major German headache specialist network to supply CGRP biologic treatments across several regional centers. The arrangement is a distribution agreement, not a joint venture or equity stake, and covers several years of prescribing activity. Financial terms were not disclosed publicly.
Signal: Indicates global cluster headache manufact

Biologic Manufacturing and Trial Cost Exposure

Biologic manufacturing and cell culture processes account for roughly forty-one percent of CGRP biologic production cost, clinical trial and regulatory approval investment another twenty-nine percent, and device component sourcing fourteen percent depending on treatment modality and substantiation scope. Biologic manufacturing sources from American, European, and specialized biotech contract manufacturers, while clinical trial capacity remains concentrated among specialized contract research org
Biologic manufacturing and cell culture capacity costs swung in 2024, with the FDA and European Commission noting manufacturing supply volatility tied to competitive contract manufacturing demand that pushed production costs higher across the biologic manufacturing industry. Manufacturers with long-term contract manufacturing agreements locked in before the volatility absorbed several quarters of stable cost before facing higher production costs, while competitors relying on spot-market purchasing faced cost pass-through, showing how contract structure determines which manufacturers protect margin during a volatility cycle.

Smaller specialized manufacturers without long-term contract manufacturing agreements absorb cost volatility into gross margin, while the top five use multi-year supplier agreements and sourcing to smooth exposure. Geography compounds the gap: manufacturers with American or European biotech manufacturing bases sit closer to production capacity and cost-competitive sourcing markets, giving them a cost advantage over competitors sourcing through additional channels.
cluster-headache-syndrome-market-cost-volatility-analysis-1787304737533

Lock In Multi-Year Contract Manufacturing Agreements

Manufacturers with balance sheet capacity to lock in multi-year contract manufacturing agreements two to three years forward smooth production cost volatility far better than competitors relying on reactive spot-market capacity purchasing. This requires capital commitment smaller specialized manufacturers often lack, but it is close to standard practice among the top five manufacturers protecting production schedules reliably.

Diversify Biotech Manufacturing Sourcing Across Suppliers

Sourcing contract manufacturing capacity from more than one qualified biotech manufacturer reduces exposure to single-region capacity allocation shortfalls, though qualifying alternate manufacturing sources requires additional validation investment and carries its own consistency tradeoffs manufacturers must confirm carefully before deploying diversified sourcing across multiple regional supply relationships each year. Larger manufacturers manage this tradeoff more easily than smaller competitors.

Invest in Domestic Biologic Manufacturing Capacity

Domestic biologic manufacturing capacity reduces exposure to single-region production cost volatility directly, while also improving supply continuity during periods of regional biotech manufacturing tightness that have disrupted smaller competitors. This requires meaningful upfront capital investment, but manufacturers that made this shift early are largely insulated from the production cost spikes squeezing single-region-dependent competitors across the industry today.

Portfolio Architecture for Margin Defence

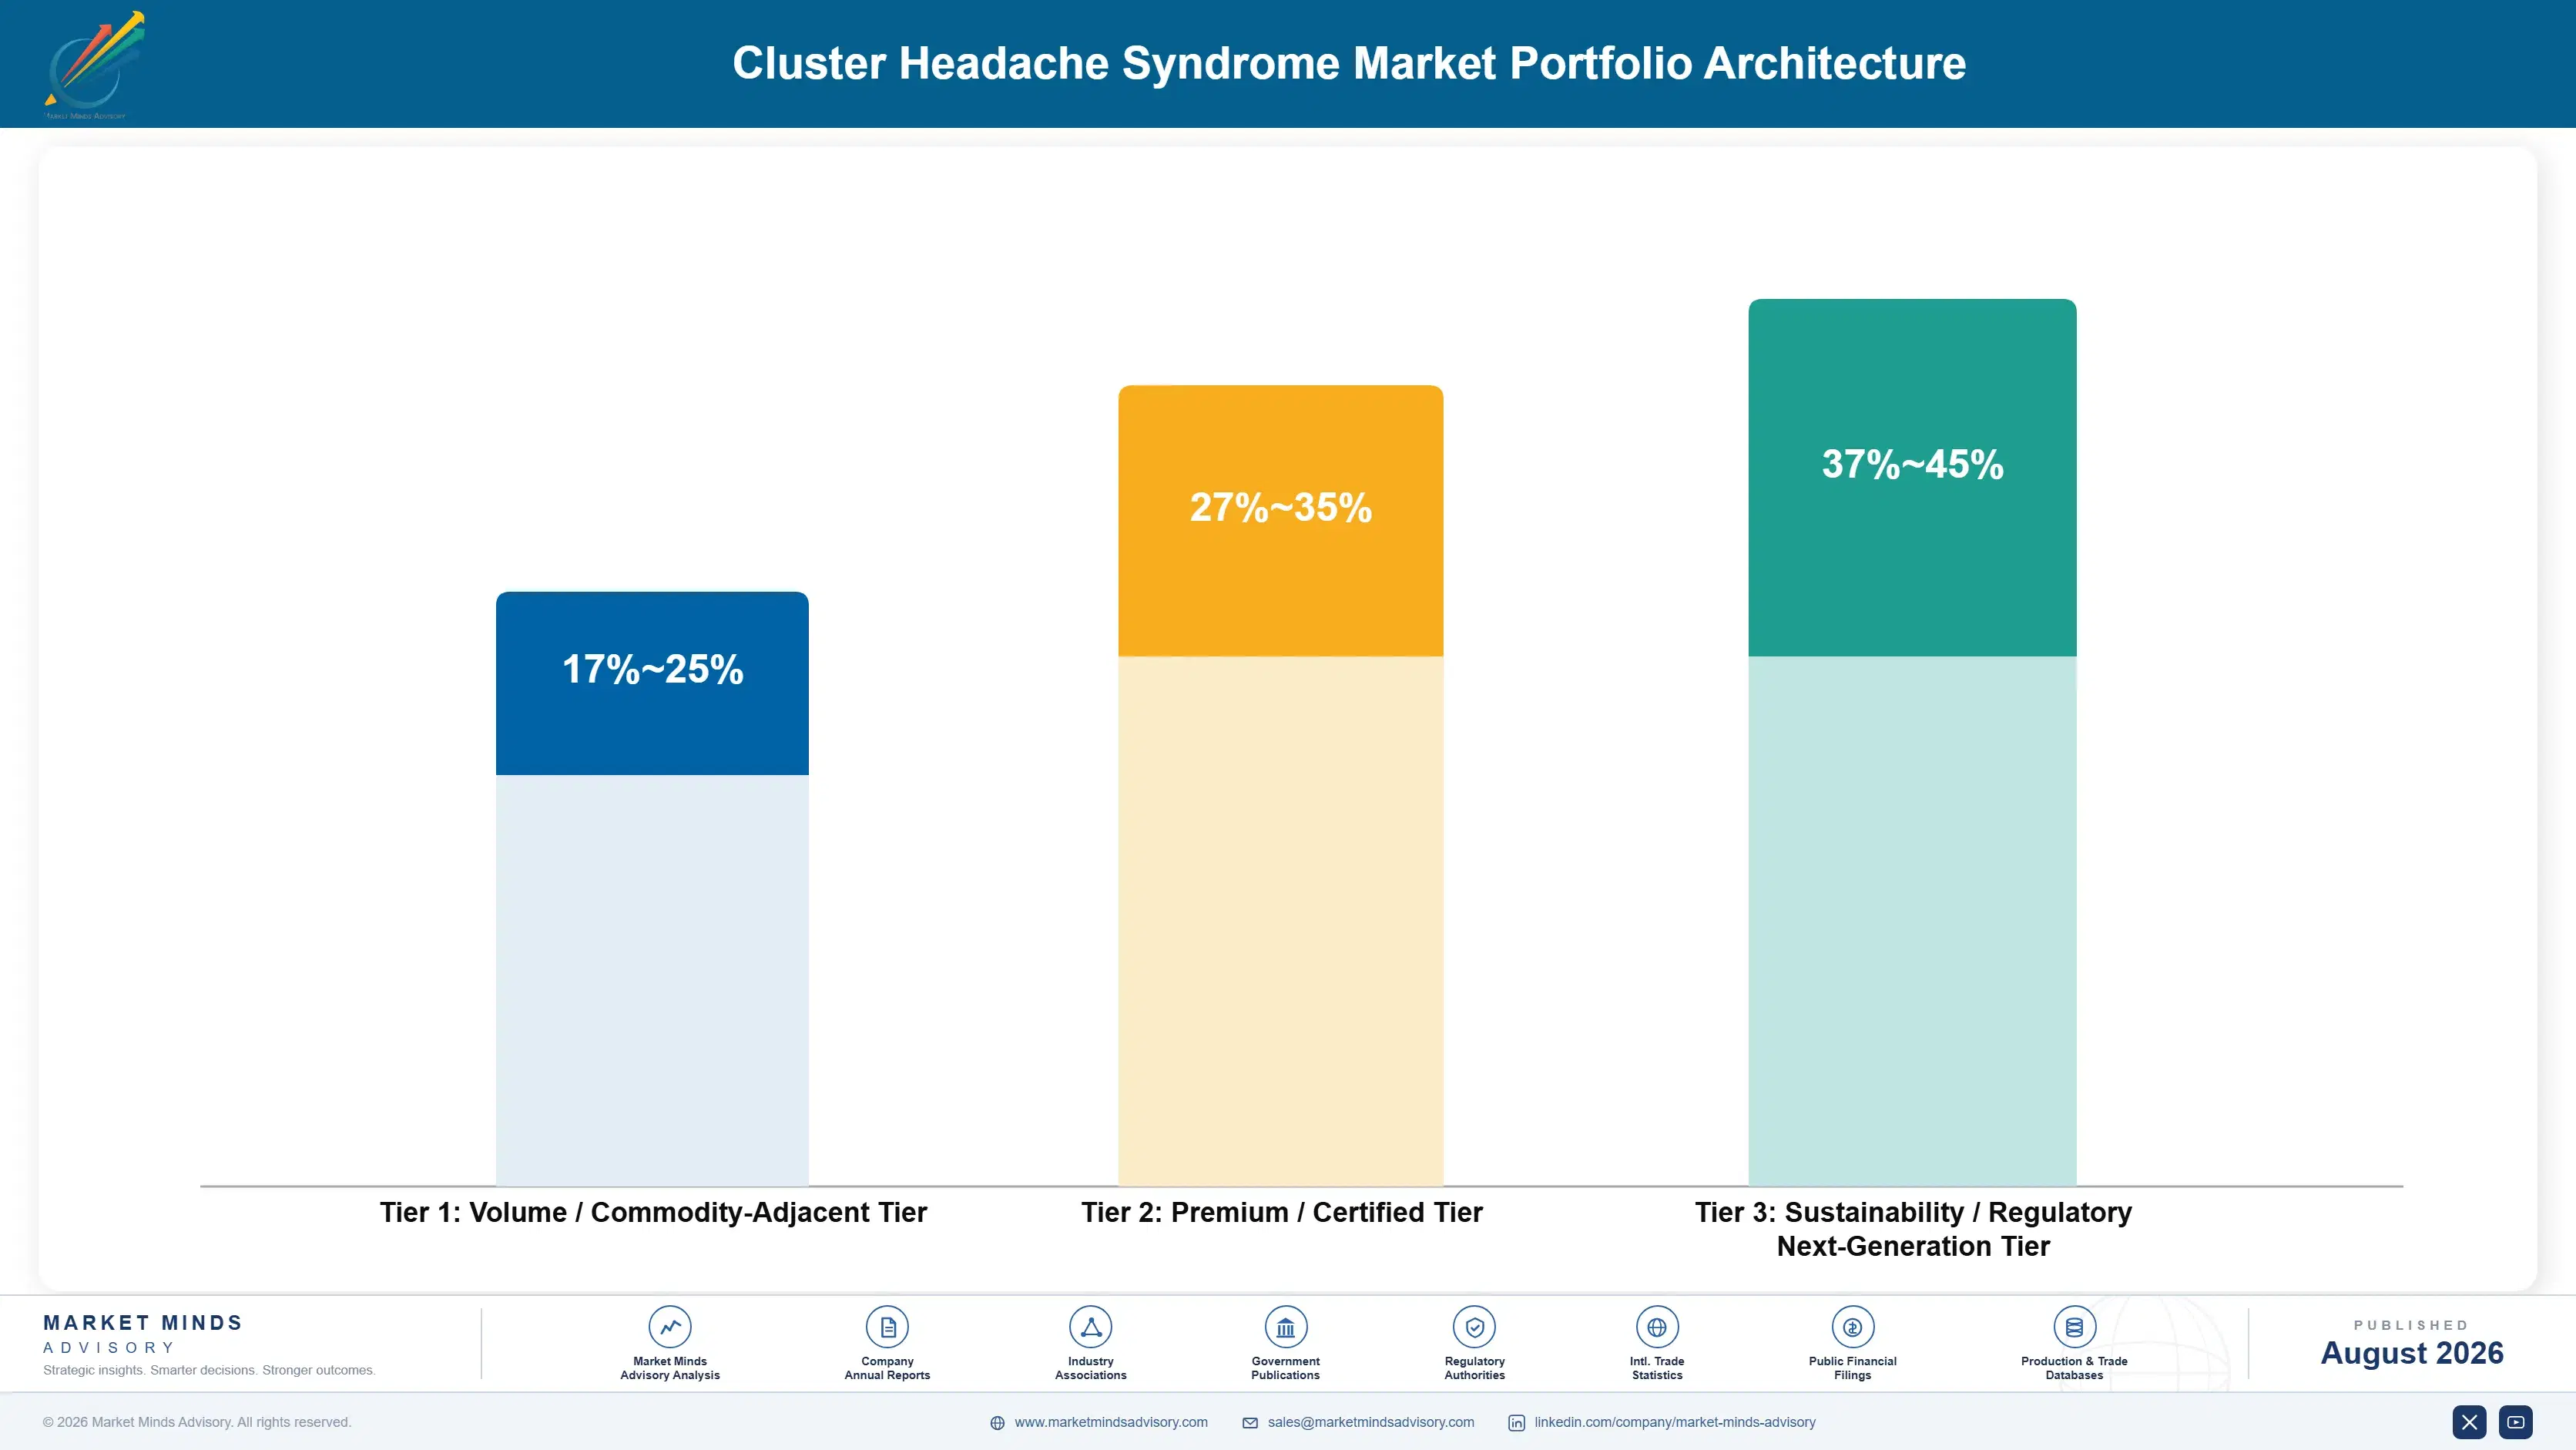
Cluster headache treatment portfolios split into three margin tiers. Standard generic acute therapies and oxygen therapy compete on price with gross margins in the high teens to mid-twenties given established manufacturer competition, mid-tier verapamil and corticosteroid transitional therapies command higher margins in the high twenties to mid-thirties, and CGRP biologic and neurostimulation premium platforms sit at the top of the stack as the smallest but fastest-expanding tier.
The volume-premium tension plays out most visibly in standard generic categories, where established manufacturers keep pushing prices down as rare-disease clinical trial investment costs rise across the category, squeezing mid-tier competitors that lack scale to compete on research cost. Premium CGRP biologic categories face a different tension: manufacturers must recoup clinical trial and regulatory investment through volume before treatment protocols become commoditized, a window narrowing as more competitors launch comparable validated biologics.

High-value margin pools concentrate in two places: CGRP biologics sold into headache specialists managing high-volume premium prescribing decisions, and neurostimulation devices that command premium pricing regardless of the standard generic pricing pressure cycle. Both pools reward manufacturers willing to invest in research and device capability ahead of demand rather than reacting once specialist requirements become standard practice across a treatment segment.

Volume / Commodity-Adjacent Tier

Standard generic acute therapies and oxygen therapy sold primarily on price into cost-sensitive institutional and pharmacy channels, where established manufacturers compete aggressively on price and clinical substantiation requirements remain comparatively modest across most account types, reflecting the category's largely commoditized manufacturing dynamics.
Gross Margin: 17-25%

Premium / Certified Tier

Mid-tier verapamil and corticosteroid transitional therapies sold to headache centers requiring documented treatment protocol performance and manufacturing reliability as increasingly standard prescribing terms across most specialist programs. These buyers increasingly weigh substantiation depth alongside price when comparing manufacturers.
Gross Margin: 27-35%

Sustainability / Regulatory / Next-Generation Tier

CGRP biologic and neurostimulation premium platforms sold into headache specialists that prioritize documented cluster-headache-specific efficacy over near-term treatment cost savings, reflecting where clinical policy is steering long-term biologic research investment.
Gross Margin: 37-45%
cluster-headache-syndrome-market-portfolio-architecture-1787304738035

Headache Specialist Prescribing Contract Economics

Cluster headache treatment revenue behaves like a long annuity once a manufacturer wins placement in a headache specialist's standard treatment protocol: a placement decision can generate repeat prescription, service, and adjacent-product revenue across thousands of patient treatment cycles over a relationship spanning many years, plus renewal demand as substantiation and treatment documentation requirements tighten with each protocol review cycle. This annuity quality is what makes specialist r
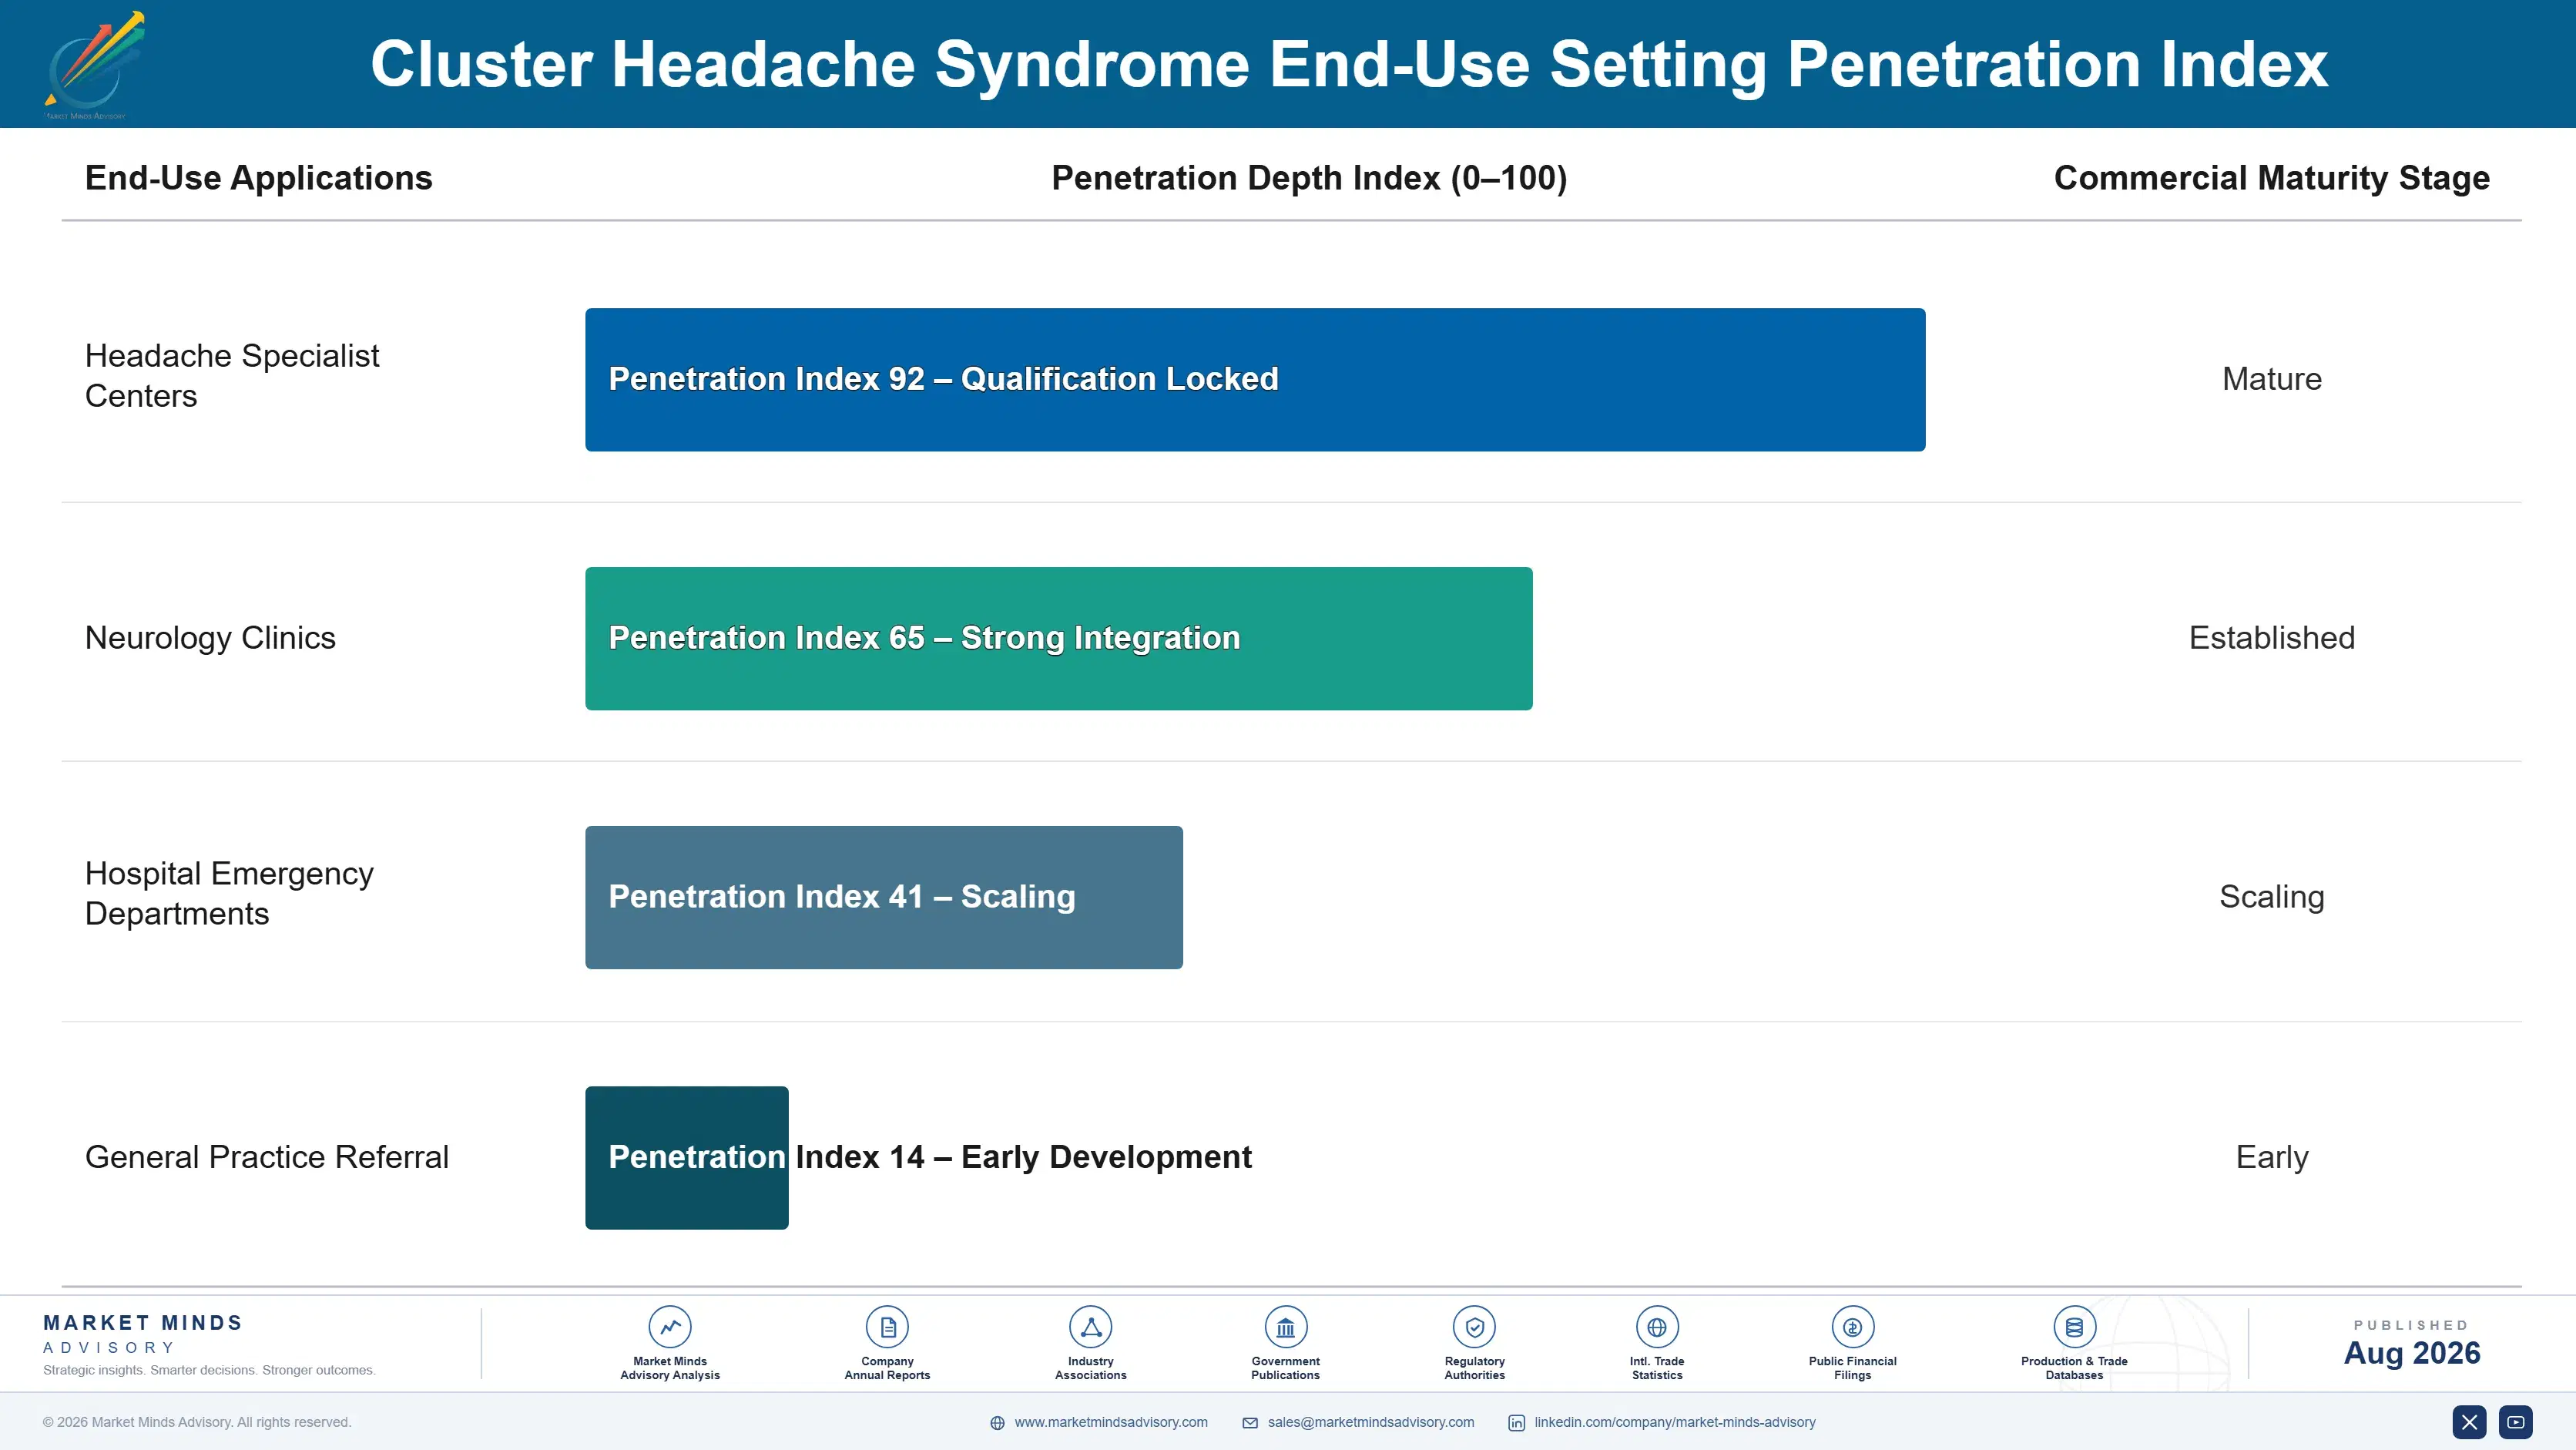
Adoption depth varies by end-use vertical. Headache centers managing high-volume chronic cluster headache caseloads adopt CGRP biologics and neurostimulation devices fastest because attack-frequency and adherence metrics threaten specialist reputation, making treatment upgrades an easy protocol justification. Mid-size regional neurology practices follow behind on cost efficiency requirements. Legacy general-practice applications without specialist referral complexity adopt more slowly, continuing with conventional off-label pharmacotherapy rather than upgrading, stretching adoption timing beyond the diagnostic transition.

Buyer profiles are shifting as prescribing moves from general-practice purchasing toward centralized, evidence-based specialist protocol planning. Younger headache specialists expect documented CGRP biologic and neurostimulation validation as a default requirement rather than an optional upgrade, and prescribing decisions are shifting from practice budgets toward centralized specialist network protocol committees, changing who cluster headache manufacturers need to sell to.
cluster-headache-syndrome-market-end-use-penetration-index-1787304738525

Where Substantiation Speed Wins Prescribing Placement

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / RARE-DISEASE CLINICAL TRIAL INVESTMENT

Validate rare-disease clinical trials ahead of regulatory approval cycles

Manufacturers that develop and validate rare-disease clinical trial data 12 to 18 months ahead of major regulatory approval cycles capture a meaningful pricing premium during the transition window before competitors catch up. This is not a marginal advantage. Companies that under-invest in trial speed risk losing prescribing relationships entirely once specialists standardize protocols around already-substantiated manufacturers, a mistake that took years for some legacy manufacturers to recover from during prior demand transitions, and headache specialist prescribing committees have not forgotten that lesson at all.
02 / NEUROSTIMULATION DEVICE INVESTMENT STRATEGY

Build device capability before competitors lock in premium specialist accounts

Neurostimulation device capability is shifting from an optional differentiator to a strategic requirement as more headache specialists standardize protocols around manufacturers offering verified attack-frequency data, and manufacturers that build capability early capture disproportionate remaining share as competitors wait for reactive device decisions instead while specialist loyalty across multi-year relationships keeps strengthening steadily. This is not a marginal advantage. Companies still treating neurostimulation as secondary to standard pharmacotherapy sales are already behind competitors actively winning relationships on this basis today, and the gap is widening each quarter.
03 / PHYSICIAN EDUCATION INVESTMENT PRIORITY

Build diagnostic education capacity before rivals lock in referral networks

Physician education investment captures the diagnostic consistency advantage that passive-referral manufacturers cannot match once headache specialists concentrate prescribing decisions around fewer preferred, reliably diagnosed referral sources, and specialist networks increasingly specify diagnostic training guarantees by default in new referral partnership agreements. This growing preference is only strengthening across every major regional market today. Manufacturers without education capability are locked out of the most reliable referral relationships entirely, and specialists that moved early are securing partnerships that passive-referral competitors will find difficult to unwind once established.
04 / REGIONAL DISTRIBUTION FOOTPRINT

Localize specialist distribution in South Asia before rivals lock in access

South Asia and the Pacific are generating the fastest unit growth in the entire ten-year forecast, and manufacturers without local specialist distribution face meaningful market access delays plus training gaps that headache centers in faster-moving markets will not tolerate for long. Regional specialist networks are already signing multi-year prescribing agreements with whichever manufacturers can deliver reliably at scale. Waiting for demand to fully mature before committing capital risks ceding these valuable relationships permanently to competitors willing to invest well ahead of confirmed volume growth today.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Cluster Headache Syndrome Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Cluster Headache Syndrome Exposure Evaluation 2025-26
CLIENT PROFILE
The client operates a regional headache specialist network spanning nine clinics across Germany, treating an annual cluster headache patient volume exceeding 4,200 patients (client-reported, unverified by MMA). Facing rising demand for disease-specific biologic treatment and constrained specialist capacity, the client's clinical operations team sought an independent assessment of CGRP biologic adoption strategy before committing to a network-wide protocol transition.
STRATEGIC CHALLENGE
The client's existing treatment protocols relied predominantly on off-label pharmacotherapy with limited CGRP biologic adoption, creating treatment gaps for patients unresponsive to conventional therapy. Clinical leadership needed to select among competing CGRP biologic options, determine which clinics to prioritize for protocol transition first, and justify the cost to a board concerned about reimbursement uncertainty.
MMA APPROACH
MMA benchmarked candidate CGRP biologic manufacturers against clinical trial depth and specialist support capability, modeling treatment outcome and cost impact by clinic. The engagement combined primary interviews with four cluster headache treatment manufacturers, review of eighteen months of the client's patient outcome and prescribing data, and a clinic-by-clinic prioritization framework ranking transition readiness against expected outcome improvement.
KEY FINDINGS
  1. CGRP biologic adoption reduced average attack frequency by thirty-one percent across the client's highest-volume clinic, exceeding what the client's internal clinical team had modeled (client-reported, unverified by MMA).
  2. The client's existing off-label-only protocol lacked adequate treatment response for a meaningful share of patients, since limited disease-specific options were already driving treatment discontinuation across several clinics.
  3. Standardizing on a validated CGRP biologic manufacturer reduced projected treatment switching rates by roughly twenty percent across the client's priority clinics (client-reported, unverified by MMA).
  4. A phased twelve-month protocol transition program prioritizing highest-volume clinics first freed enough specialist capacity to fund broader network transition in its second year overall.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1-6): Transition CGRP biologic protocols at the three highest-volume clinics, prioritizing sites with the most treatment-resistant patient populations. Phase 2: Phase 2 (Months 7-12): Roll out the standardized CGRP biologic protocol across the full clinic network, formalizing manufacturer certification requirements for all sites. Phase 3: Phase 3 (Months 13-18): Complete remaining clinic transition and formalize a rolling annual manufacturer performance review tied to outcome and cost metrics.
OUTCOME
Within twelve months of the phased rollout beginning, the client reported a twenty-six percent reduction in average attack frequency across transitioned clinics and reduced treatment discontinuation by an estimated sixteen percent (client-reported, unverified by MMA). The client has since extended the MMA-designed prioritization framework to two additional specialist networks.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Cluster Headache Syndrome Market?

The cluster headache treatment market reached an estimated $1.2 billion in 2025. This figure covers triptans, oxygen therapy, CGRP monoclonal antibody biologics, neurostimulation devices, corticosteroid therapies, and verapamil pharmacotherapy globally.

How large will the Cluster Headache Syndrome Market be by 2036?

MMA projects the market will reach approximately $3.49 billion by 2036, roughly 2.64 times its 2026 value. Growth is driven primarily by CGRP biologic adoption and expanding specialist diagnosis.

What is the CAGR for the Cluster Headache Syndrome Market 2026 to 2036?

The base case CAGR is 10.2% annually through 2036. Bull and bear scenarios range from 11.5% to 8.9% depending on biologic adoption pace and payer scrutiny.

Which segment is growing fastest?

CGRP monoclonal antibody preventive therapies are the fastest-growing segment at a 16.8% CAGR, roughly 1.6 times the overall market rate. Neurostimulation devices follow closely as the second-fastest segment at 14.2%.

Who are the major companies in the Cluster Headache Syndrome Market?

Eli Lilly, Amgen, Teva Pharmaceutical Industries, electroCore, and Medtronic are the five leading manufacturers by unit volume. Together they hold roughly sixty-one percent of global market share.

Which country is growing fastest?

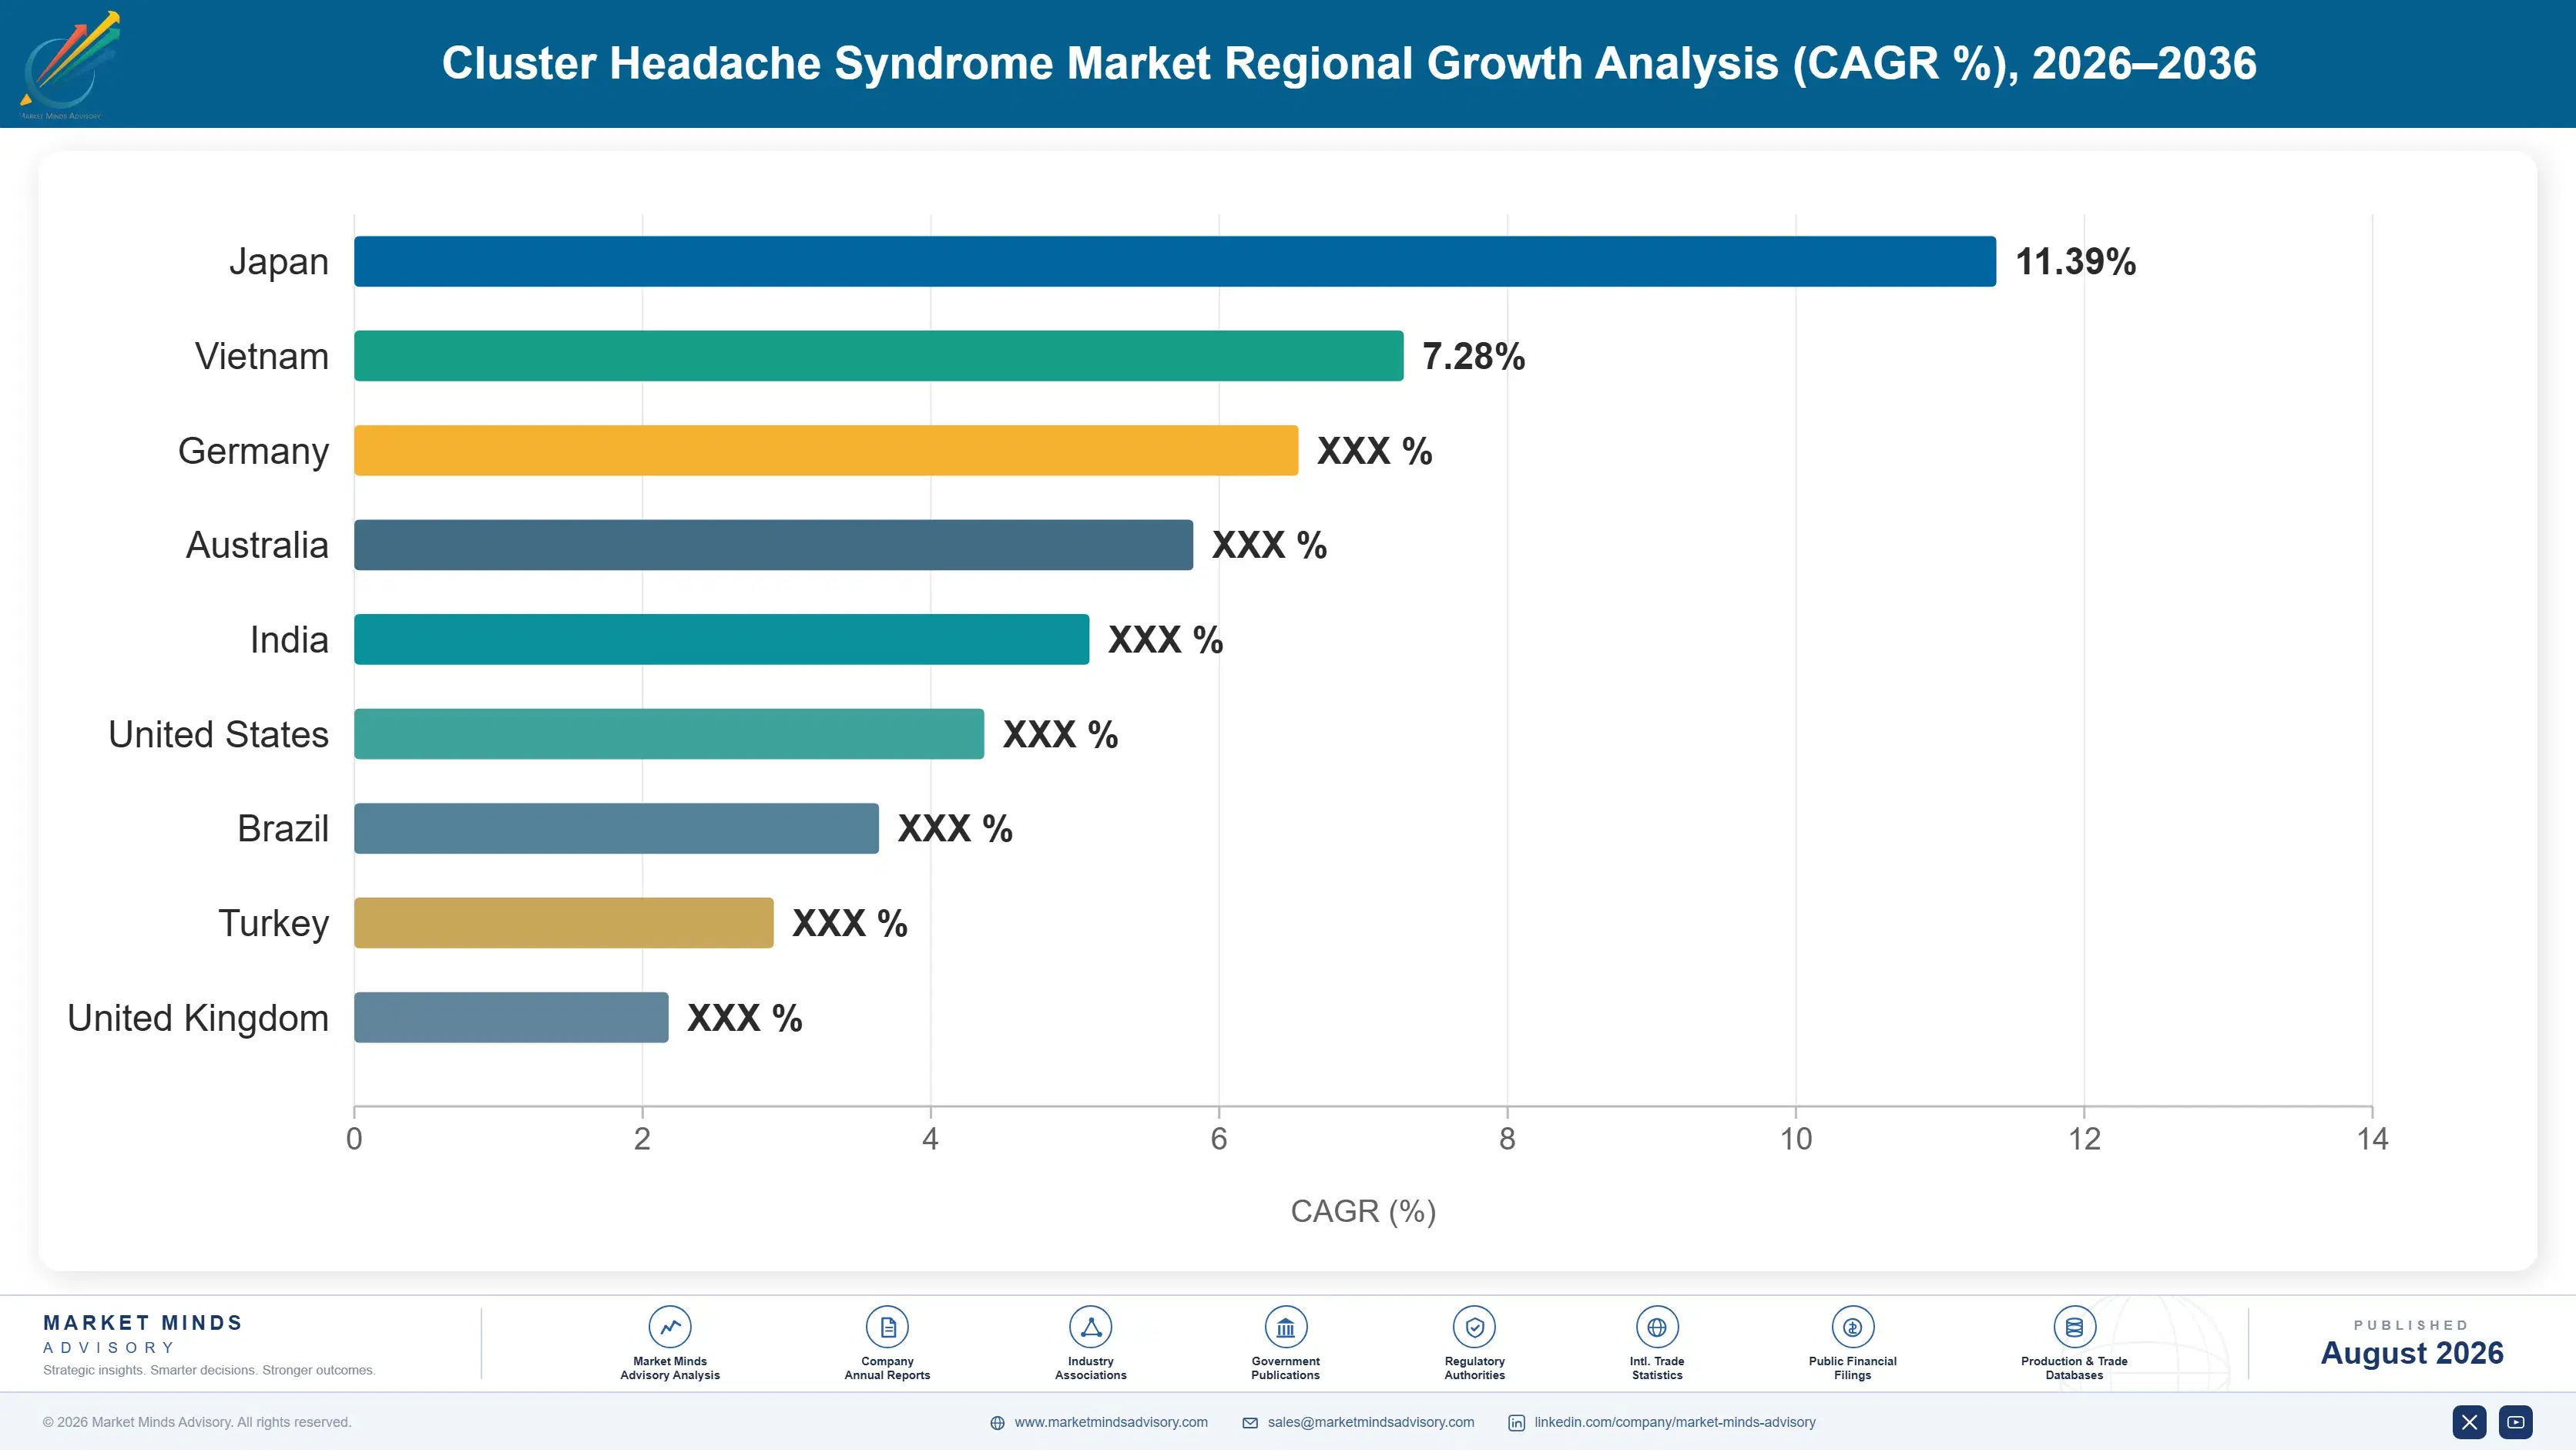
Germany is the fastest-growing major market, with a CAGR near 11.9%, driven by its dense headache specialist network and early CGRP biologic reimbursement. Strong neurology infrastructure is supporting continued expansion there.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Treatment Modality

  • Triptans (Acute Treatment)
  • Oxygen Therapy
  • CGRP Monoclonal Antibody Preventive Therapies
  • Neurostimulation Devices
  • Corticosteroid and Transitional Therapies
  • Verapamil and Other Preventive Pharmacotherapy

By End-Use Setting

  • Headache Specialist Centers
  • Neurology Clinics
  • Hospital Emergency Departments
  • General Practice Referral

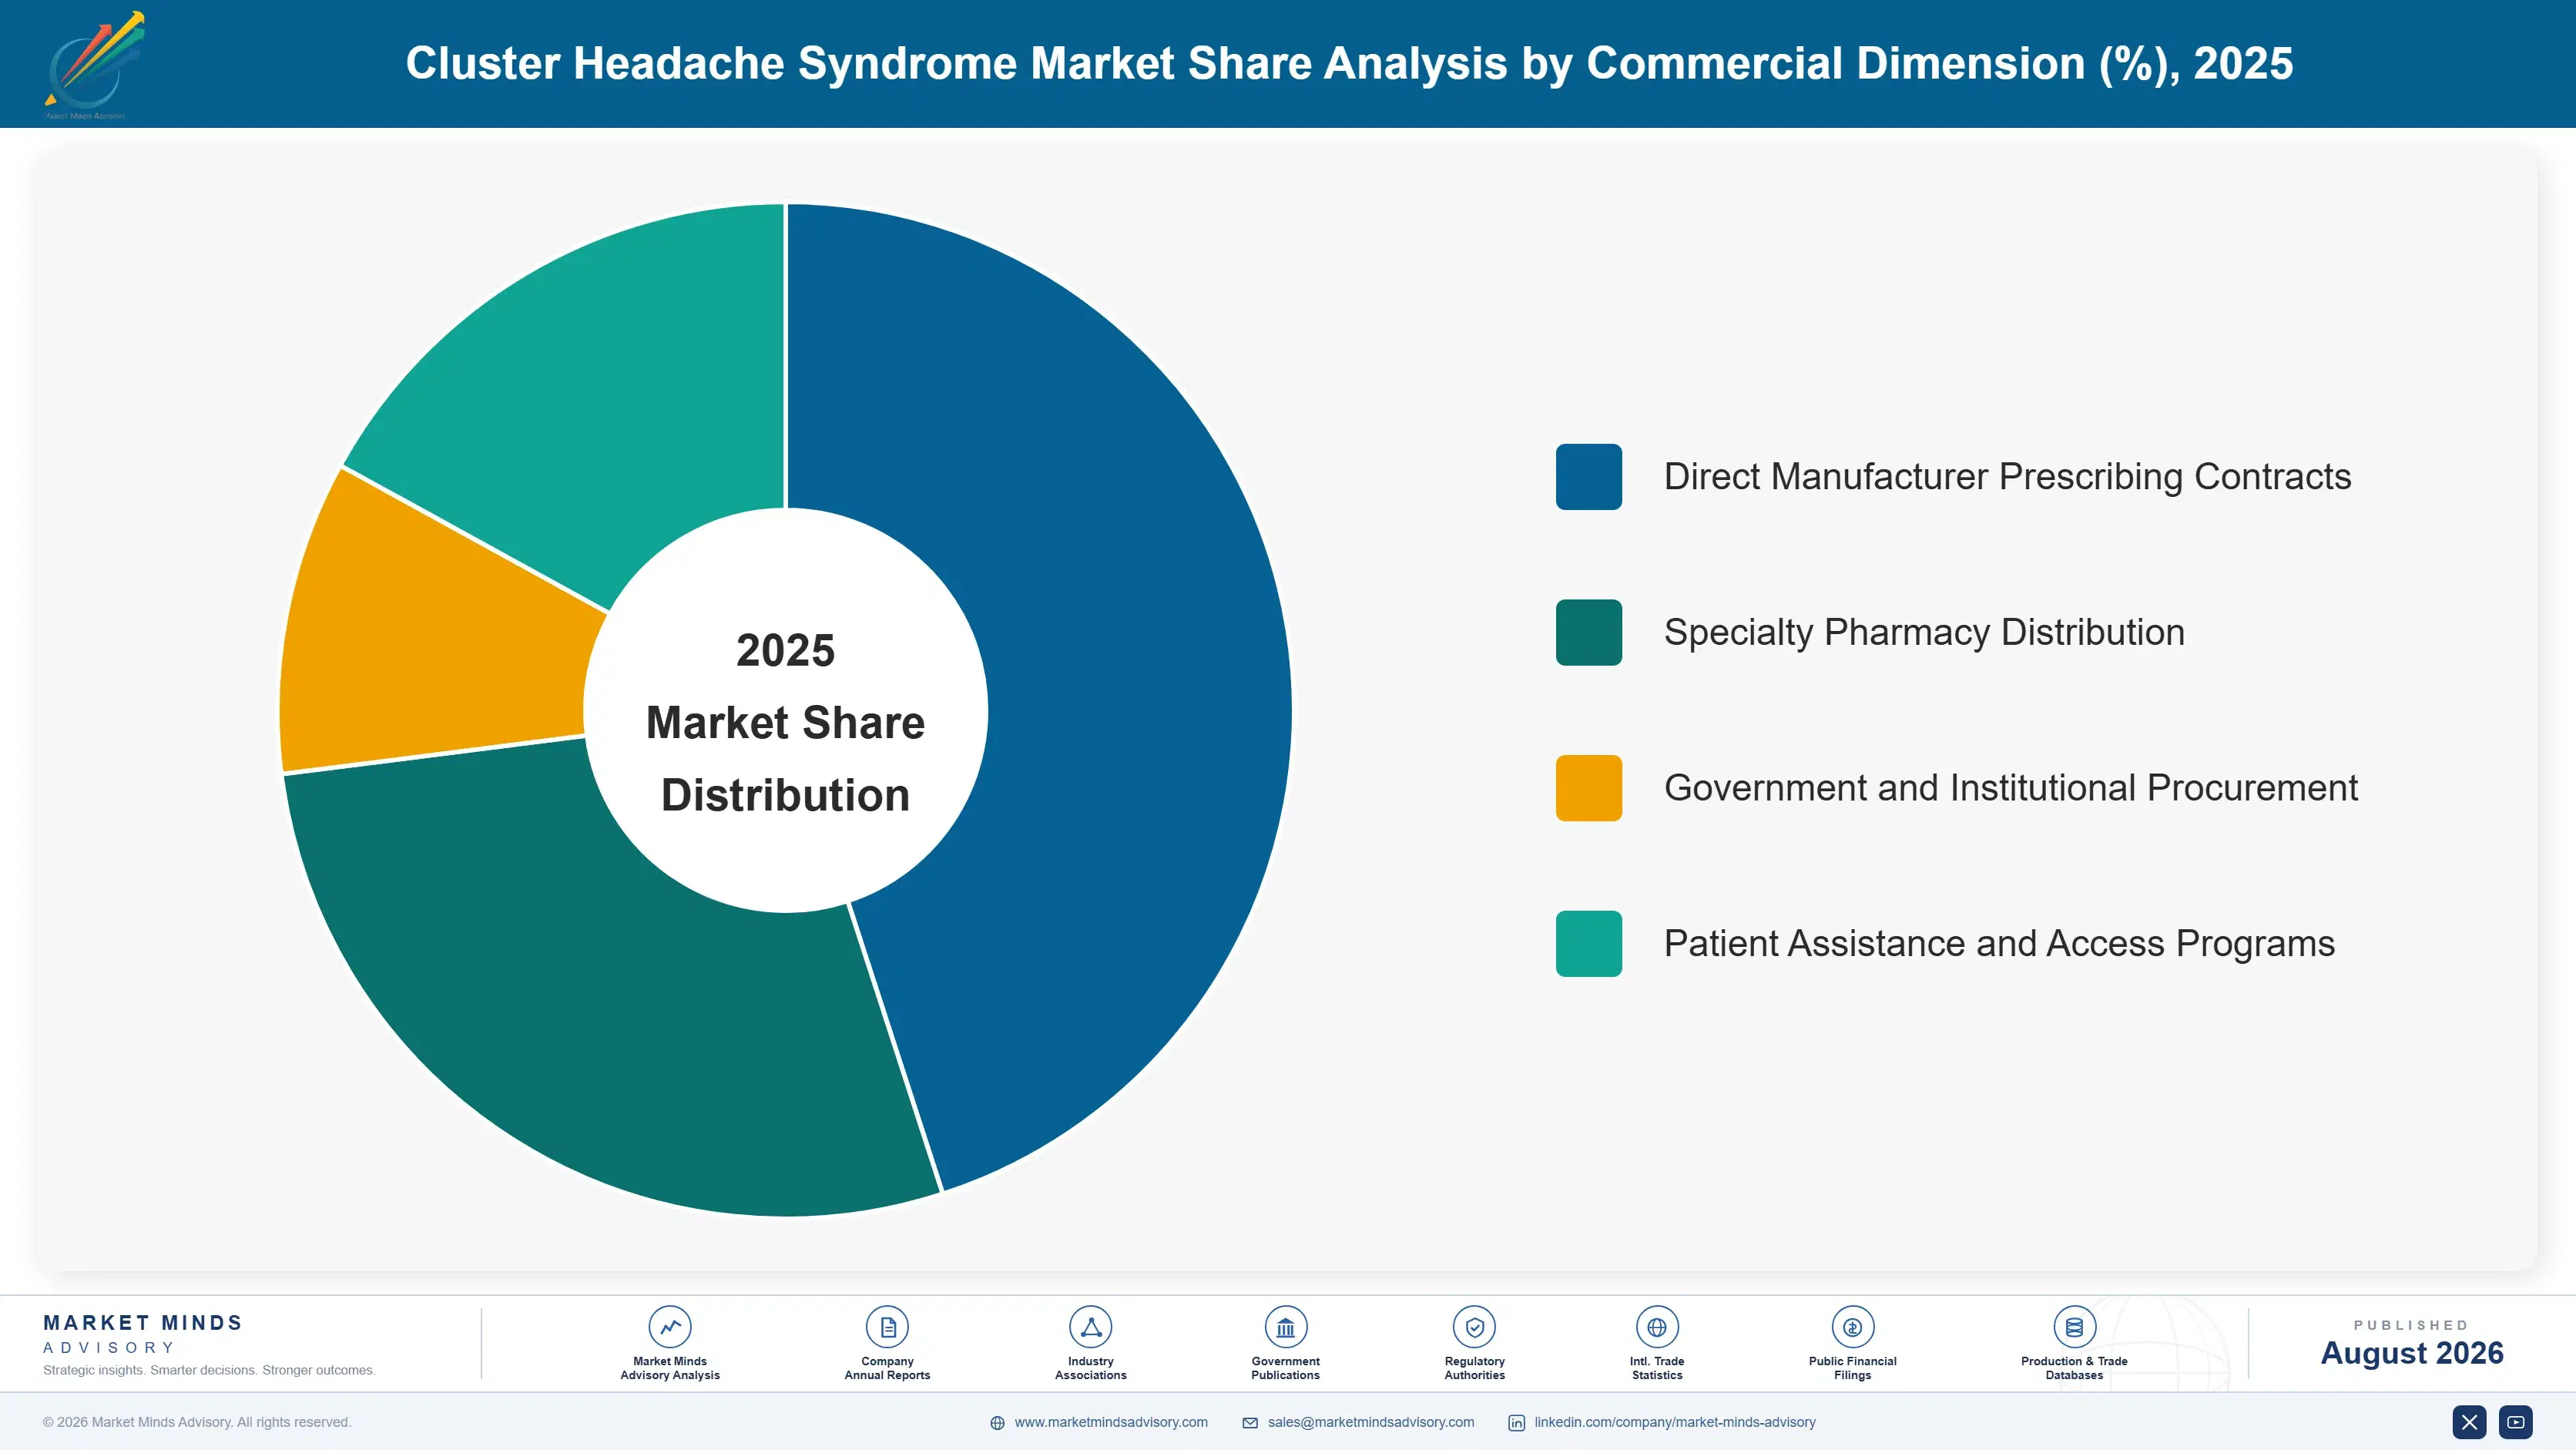
By Commercial Dimension

  • Direct Manufacturer Prescribing Contracts
  • Specialty Pharmacy Distribution
  • Government and Institutional Procurement
  • Patient Assistance and Access Programs

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
This report covers pharmaceutical and device-based treatments for cluster headache, including acute triptans, oxygen therapy, CGRP monoclonal antibody preventive biologics, neurostimulation devices, corticosteroid transitional therapies, and verapamil and other preventive pharmacotherapy. It excludes treatments marketed exclusively for migraine or tension-type headache without cluster headache indication, and general pain management devices not specific to headache disorders. Scope covers global sales revenue of finished cluster headache treatment products.
Quantitative Units
USD billions (current prices); patient volume where disclosed
Segmentation Dimensions
By Treatment Modality; By End-Use Setting; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Germany, UK, France, Italy, China, Japan, South Korea, Taiwan, India, Vietnam, Australia, Brazil, Argentina, Colombia, Mexico, Chile, Peru, Saudi Arabia, UAE, South Africa, Egypt, Poland, Czech Republic, Hungary, Romania, and additional markets relevant to this sector
Key Companies Profiled
Eli Lilly, Amgen, Teva Pharmaceutical Industries, electroCore, Medtronic, Lundbeck, Amneal Pharmaceuticals, Viatris, Currax Pharmaceuticals, Collegium Pharmaceutical, Theranica, Cala Health, NeurAxis, Linde Healthcare, Air Liquide Healthcare, Chiesi Farmaceutici, Impel Pharmaceuticals, Zosano Pharma, GlaxoSmithKline, Sanofi
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-142
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Cluster Headache Syndrome Market Report (2026 to 2036).

The full report delivers a complete market model spanning 2020 through 2036, with detailed segmentation by treatment modality, end-use setting, and commercial dimension across all seven global regions. It includes company profiles for the top twenty manufacturers, covering rare-disease clinical trial capability, neurostimulation device technology, and recent corporate developments. Buyers receive access to MMA's underlying primary survey dataset of 3,800 respondents and 47 expert interviews conducted in the fourth quarter of 2025. The report also includes a dedicated biologic manufacturing input cost assessment, plus a case study illustrating a real-world CGRP biologic adoption engagement.
Full segmentation model across six treatment modalities
Company profiles for twenty manufacturers with development tracking
Full regional coverage across all seven global markets
CGRP biologic and neurostimulation trend assessment
Biologic manufacturing and trial cost analysis
Ten-year forecast with bull, base, and bear scenarios

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts