Market Minds Advisory
Chronic Obstructive Pulmonary Disease Market

Chronic Obstructive Pulmonary Disease Market: Biologic Therapy and the Precision Respiratory Care Transition

Expanding biologic therapy approval for eosinophilic phenotypes and rising smart inhaler adoption are pushing respiratory developers toward precision treatment pathways, forcing legacy triple combination inhaler makers to rebuild their portfolios around connected monitoring platforms.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$21.5BMarket Size 2025
2036 FORECAST VALUE$49.1BBase Case , 2026 to 2036
CAGR 2026 TO 20367.8 %Bull 9.0% / Bear 6.5%
INCREMENTAL OPPORTUNITY$25.9BNet 10- year value creation
EXPANSION MULTIPLE2.12x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

COPD treatment procurement has shifted decisively from standard triple combination inhaler protocols toward biologic and precision phenotype-driven therapies, as pulmonologists increasingly evaluate exacerbation reduction data ahead of raw treatment cost when selecting a primary treatment pathway for every diagnosed patient nationwide.
Biologic therapies for eosinophilic COPD are growing at roughly 1.86x the market average as pulmonologists pursue targeted phenotype intervention over broad triple combination protocols. North America retains the largest revenue base on dense respiratory specialty infrastructure and established biologic reimbursement pathways, while East Asia is compounding fastest as China's expanding COPD diagnosis capacity and air pollution driven disease burden pull demand into the category at an accelerating pace nationwide.
Competitive intensity concentrates among five diversified pharmaceutical developers that hold proprietary biologic and smart inhaler platform technology, leaving smaller regional producers to compete for generic bronchodilator monotherapy market share across most price-sensitive segments. Clinical evidence depth and exacerbation reduction data, not treatment pricing, determine which developers win multi-year pulmonology prescriber relationships. Digital monitoring partnerships are beginning to standardize adherence tracking pathways across affiliated respiratory center networks nationwide.
Market Definition
The COPD market covers pharmaceutical products, devices, and services used to treat chronic obstructive pulmonary disease, spanning triple combination inhaled therapies, biologic therapies for eosinophilic COPD, short-acting and long-acting bronchodilator monotherapies, home oxygen and respiratory support devices, pulmonary rehabilitation and digital monitoring services, and smart inhaler and connected device platforms. Asthma treatments without a confirmed COPD diagnosis are excluded from market scope.
Base Year Value
$21.5B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
7.8% base case. Bull 9.0%. Bear 6.5%.
Fastest Growth Segment
Biologic Therapies for Eosinophilic COPD: 14.5% CAGR
Fastest Growth Country
China: 13.5% CAGR
Fastest Growth Region
South Asia and Pacific: 9.8% CAGR
Largest Region
North America: 30% of 2025 global value
Market Leaders
GlaxoSmithKline plc, AstraZeneca plc, Boehringer Ingelheim International GmbH, Novartis AG, Sanofi SA. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Chronic Obstructive Pulmonary Disease Market Forecast Scenarios

chronic-obstructive-pulmonary-disease-market-size-forecast-scenario-1787306846185
Between 2020 and 2025 the market grew at an estimated 6.8% historical CAGR, accelerating steadily as triple combination inhaler adoption broadened and biologic clinical trial data matured across major developed markets throughout the historical period, while pulmonologists steadily embraced phenotype-driven intervention. Companies investing early in biologic mechanism development captured a disproportionate share of this accelerating demand base.
The base case assumes 7.8% CAGR through 2036, anchored in three commercial mechanisms: expanding respiratory diagnosis and phenotyping infrastructure across major developed and emerging markets requiring proportional treatment and monitoring capacity, rising biologic therapy adoption sustaining base demand for exacerbation reduction over broad bronchodilator protocols alone, and growing smart inhaler platform integration pushing patients toward higher specification connected treatment formats. Pulmonary rehabilitation programme expansion adds a further reinforcing tailwind as digital monitoring demand accelerates across the sector.
A bull scenario, near 9.0% CAGR, assumes faster biologic adoption and accelerated phenotyping infrastructure expansion pull premium treatment orders forward across more patient categories worldwide. The bear case, near 6.5% CAGR, assumes broader healthcare payer scrutiny tightens considerably and providers extend existing triple combination inhaler protocols rather than adopting biologic mechanisms on the standard treatment cycle industry-wide.

Biologic Phenotyping Reshapes Respiratory Treatment Economics

Three forces are converging on COPD treatment demand simultaneously: expanding respiratory diagnosis and phenotyping infrastructure requiring proportional treatment and monitoring capacity, rising biologic therapy adoption sustaining base demand for exacerbation reduction, and growing smart inhaler platform integration pushing patients toward higher specification connected formats. Pulmonologists that once treated COPD as a uniform disease managed through broad bronchodilator protocols now speci
MARKET CONCENTRATION48%Combined revenue share held by top five treatment developers
AVERAGE ANNUAL TREATMENT COST$3,800Blended average cost per patient for standard yearly therapy
EOSINOPHILIC PHENOTYPING RATE31%Share of diagnosed patients receiving confirmatory eosinophil testing
TOP PRODUCING COUNTRYUnited StatesLeading country for installed treatment manufacturing and clinical capacity
EXACERBATION REDUCTION RATE34%Average annual exacerbation reduction achieved with biologic therapy
SMART INHALER ADOPTION SHARE22%Share of prescribed inhalers integrated with connected monitoring platforms
Commercially, the category increasingly resembles a specialty pharmaceutical partnership bundled around phenotyping and adherence monitoring support rather than a transactional prescription purchase. Respiratory centers and pharmaceutical developers commit to recurring multi-year treatment relationships spanning diagnosis, therapy initiation, and exacerbation monitoring, since fragmenting these functions across multiple providers creates care discontinuity that a unified relationship avoids across the disease management lifecycle.
Over the next decade, expect biologic and smart inhaler formats to keep gaining share within the broader respiratory therapeutic budget as clinical evidence accumulates and phenotyping infrastructure matures, continued consolidation among smaller regional developers unable to fund biologic platform development, and growing scrutiny of exacerbation reduction outcome data driving faster clinical adoption cycles across major respiratory center networks worldwide, particularly among academic pulmonology specialty programmes.
"COPD management used to mean the same triple combination inhaler for nearly every patient regardless of phenotype. Now pulmonologists are testing eosinophil counts and prescribing biologics targeted to the underlying inflammatory pathway, and that shift has completely changed how a respiratory pipeline gets valued."
Director, Respiratory Therapeutics Practice · MMA Respiratory Disease Therapeuti

Market Trends

Pulmonologists Shift Toward Phenotype-Driven Biologic Intervention

Respiratory specialists and academic pulmonology centers are increasingly initiating biologic therapy for patients with confirmed eosinophilic phenotype, replacing what were historically broad triple combination inhaler protocols built around uniform symptom management alone across most exacerbation-prone populations served today. Each new biologic intervention commitment requires developers to demonstrate consistent exacerbation reduction data alongside existing treatment capabilities, an evidence bar that has tightened over the past several years across the industry and its prescriber base. Respiratory centers completing successful phenotyping protocol adoption report meaningfully improved patient outcomes, reinforcing biologic therapy as the standard specification for new treatment investment nationwide and internationally.
Market Impact: Adds 2.4 million patients yearly
Smart Inhalers Standardize Adherence Monitoring Protocols

Respiratory centers and digital health platforms are increasingly deploying smart inhaler devices that track medication usage and adherence patterns, replacing what were historically unmonitored standard inhaler devices built around patient self-reporting alone across most treatment adherence pathways. Each new smart inhaler commitment requires manufacturers to demonstrate reliable connectivity alongside existing device capabilities, a service expectation that has tightened over the past several years across the category and its digital health partners. Respiratory centers completing expanded smart inhaler programmes report meaningfully improved adherence rates, reinforcing connected monitoring as the standard specification for new patient investment across every major respiratory center today.
Market Impact: Adds 14% to diagnosed patient popul

Market Opportunities and Growth Drivers

Expanding Respiratory Diagnosis Capacity Drives Base Demand

Expanding respiratory diagnosis and phenotyping infrastructure across major developed and emerging markets continues driving surging COPD treatment demand, proportionally expanding requirements for therapeutic platforms capable of serving a broad range of disease severities across both newly diagnosed patients and established chronic exacerbation populations. Companies report that respiratory centers increasingly expect dedicated biologic and monitoring formats validated specifically for their patient population rather than relying on generic uniform bronchodilator protocols alone. This diagnosis capacity growth is expanding the addressable treatment market well beyond the severe disease categories that historically drove most category demand across the broader respiratory supply chain.
Market Impact: Limits 23% of eligible payer covera

Air Pollution Driven Disease Burden Sustains Demand

Continued exposure to air pollution and occupational respiratory hazards across major developing and industrializing markets is sustaining steady demand for both biologic and standard treatment formats required to reach increasingly broad patient populations facing environmental disease risk factors beyond traditional smoking-related exposure. Companies report that dedicated respiratory screening partnerships can meaningfully reduce time to diagnosis that far exceeds the incremental cost of screening and monitoring infrastructure investment. This environmental disease burden growth is expanding the addressable treatment market well beyond the developed markets that historically drove most category demand across the broader respiratory therapeutics industry worldwide.
Market Impact: Adds 12% access delay

Market Restraints and Challenges

High Biologic Costs Limit Broad Payer Coverage

Biologic COPD therapies carry meaningful cost barriers that limit broader payer coverage, and the root cause is that phenotype-targeted biologic treatments require sustained annual investment that many national health systems and private payers scrutinize heavily against measurable exacerbation reduction outcome data before approving coverage. The commercial impact falls hardest on smaller developers attempting to secure payer formulary placement, since health economic outcomes research can represent a substantial share of total company investment relative to achievable near-term prescription volume. Companies are mitigating this by developing outcome-based value contracts tied to measurable exacerbation reduction rates.
Market Impact: Lifts biologic intervention adoptio

Phenotyping Infrastructure Gaps Complicate Treatment Access

Biologic therapy eligibility carries meaningful phenotyping infrastructure requirements that complicate broader treatment access, and the root cause is that confirming eosinophilic phenotype requires specialized laboratory testing capacity that many community and rural respiratory practices do not have readily available compared to academic specialty centers with dedicated diagnostic resources. The commercial impact falls hardest on developers serving geographically dispersed patient populations, since limited phenotyping access can delay treatment initiation and reduce overall biologic prescription volume. Companies are mitigating this by expanding point-of-care phenotyping technology and partnering with regional reference laboratories.
Market Impact: Lifts smart inhaler adoption 17%
4 additional market trends, 3 additional growth drivers, and 4 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

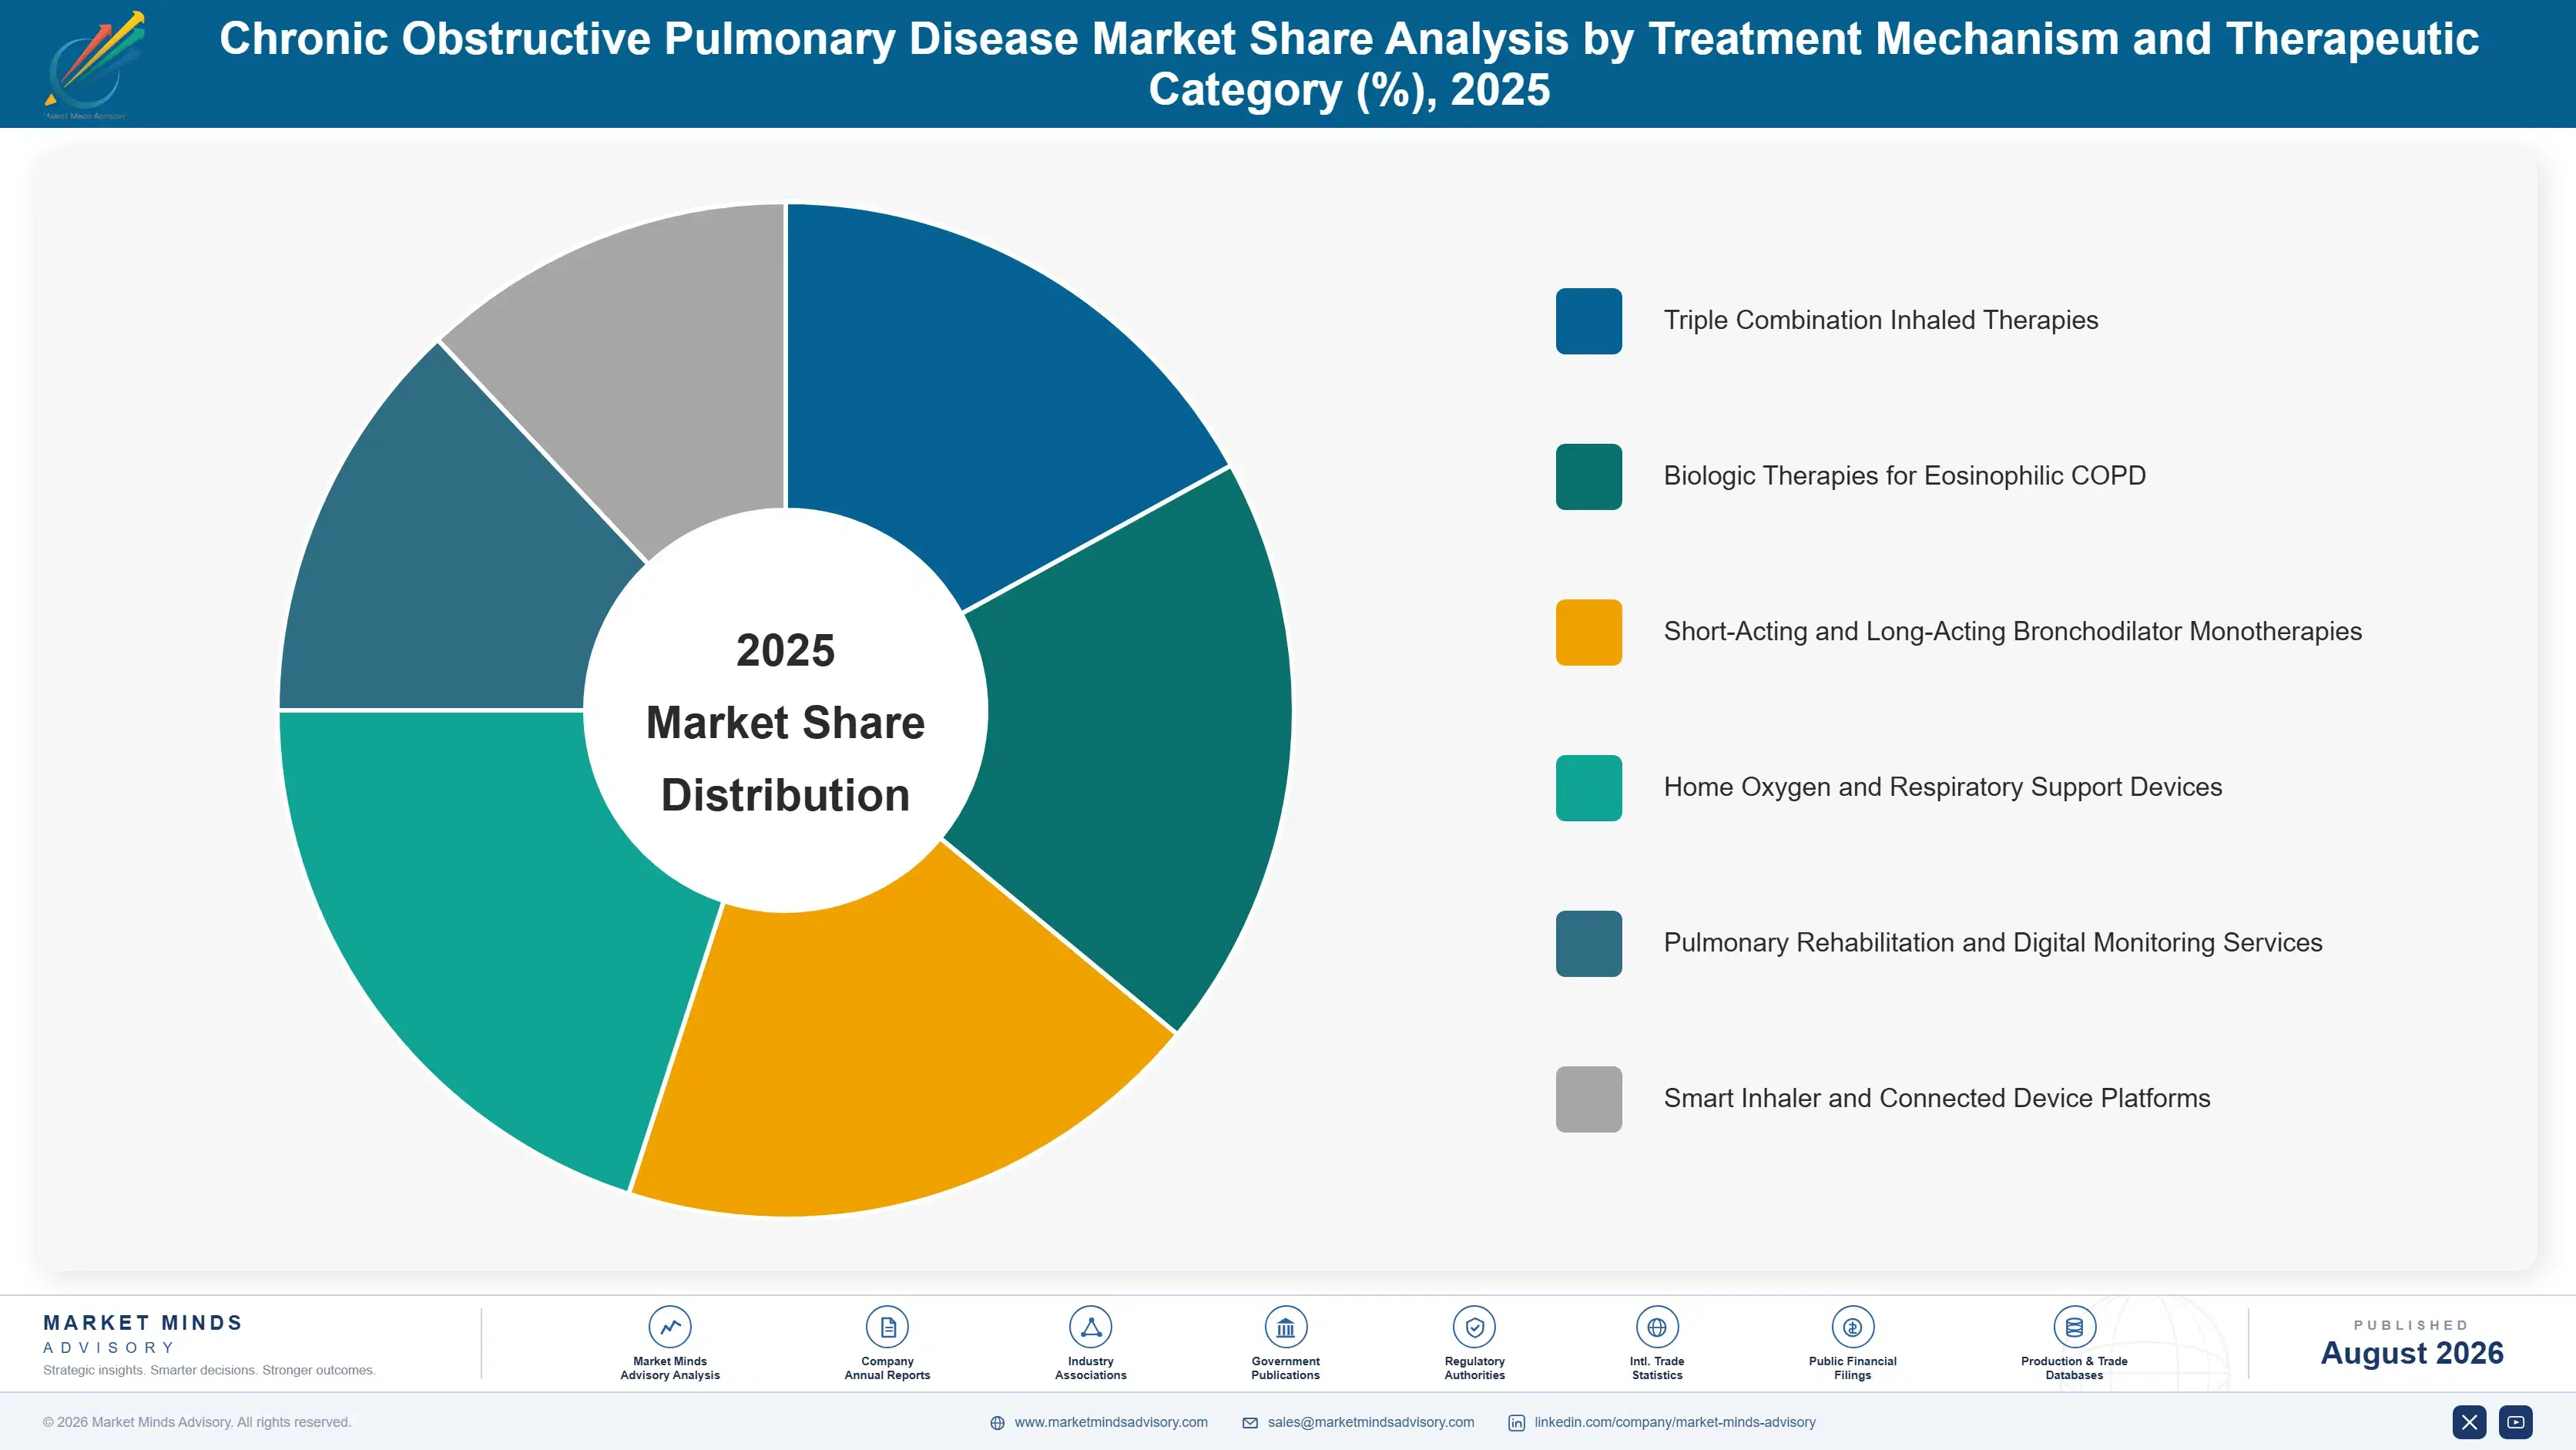
Segmentation follows treatment mechanism and therapeutic category, the single dimension pulmonologists specify against when structuring a COPD treatment protocol. Triple combination inhalers, biologics, bronchodilator monotherapies, and connected devices each serve a distinct disease intervention mechanism, keeping therapeutic and device dimensions cleanly separate across every treatment category served worldwide by respiratory centers and academic hospitals alike.
chronic-obstructive-pulmonary-disease-market-market-share-analysis-1787306846725

Biologic Therapies for Eosinophilic COPD

Biologic therapies for eosinophilic COPD target the underlying inflammatory pathway responsible for exacerbations in patients with elevated eosinophil counts, offering more precise disease intervention than broad-spectrum triple combination inhaler therapy provides for this specific patient subgroup. Adoption is concentrated among academic pulmonology centers and specialty respiratory practices seeking access to phenotype-targeted mechanisms for patients experiencing frequent exacerbations despite standard therapy. Growth outpaces the broader market by roughly 1.86x as clinical trial data accumulates and phenotyping infrastructure develops to support broader patient identification. Companies with proven exacerbation reduction data are capturing outsized share, since building pulmonologist trust in a new biologic brand requires sustained evidence most prescribers are reluctant to adopt without demonstrated long-term performance.
CAGR 14.5%

Triple Combination Inhaled Therapies

Triple combination inhaled therapies combine an inhaled corticosteroid, long-acting beta agonist, and long-acting muscarinic antagonist into a single device, addressing multiple bronchoconstriction and inflammation pathways simultaneously for patients with moderate to severe COPD symptoms. Adoption is concentrated among respiratory specialists managing patients with confirmed symptom burden and exacerbation history requiring more than single-mechanism bronchodilator therapy alone. Growth remains strong as generic competition emerges and prescribers increasingly view combination therapy as a meaningful driver of symptom control beyond single-mechanism treatment alone. Companies completing expanded smart inhaler integration report meaningfully improved patient adherence, reinforcing triple combination therapy as a standard specification within premium respiratory treatment protocols across major pulmonology center networks nationwide.
CAGR 8.0%
Full segment breakdown across 6 segments available in the complete report.

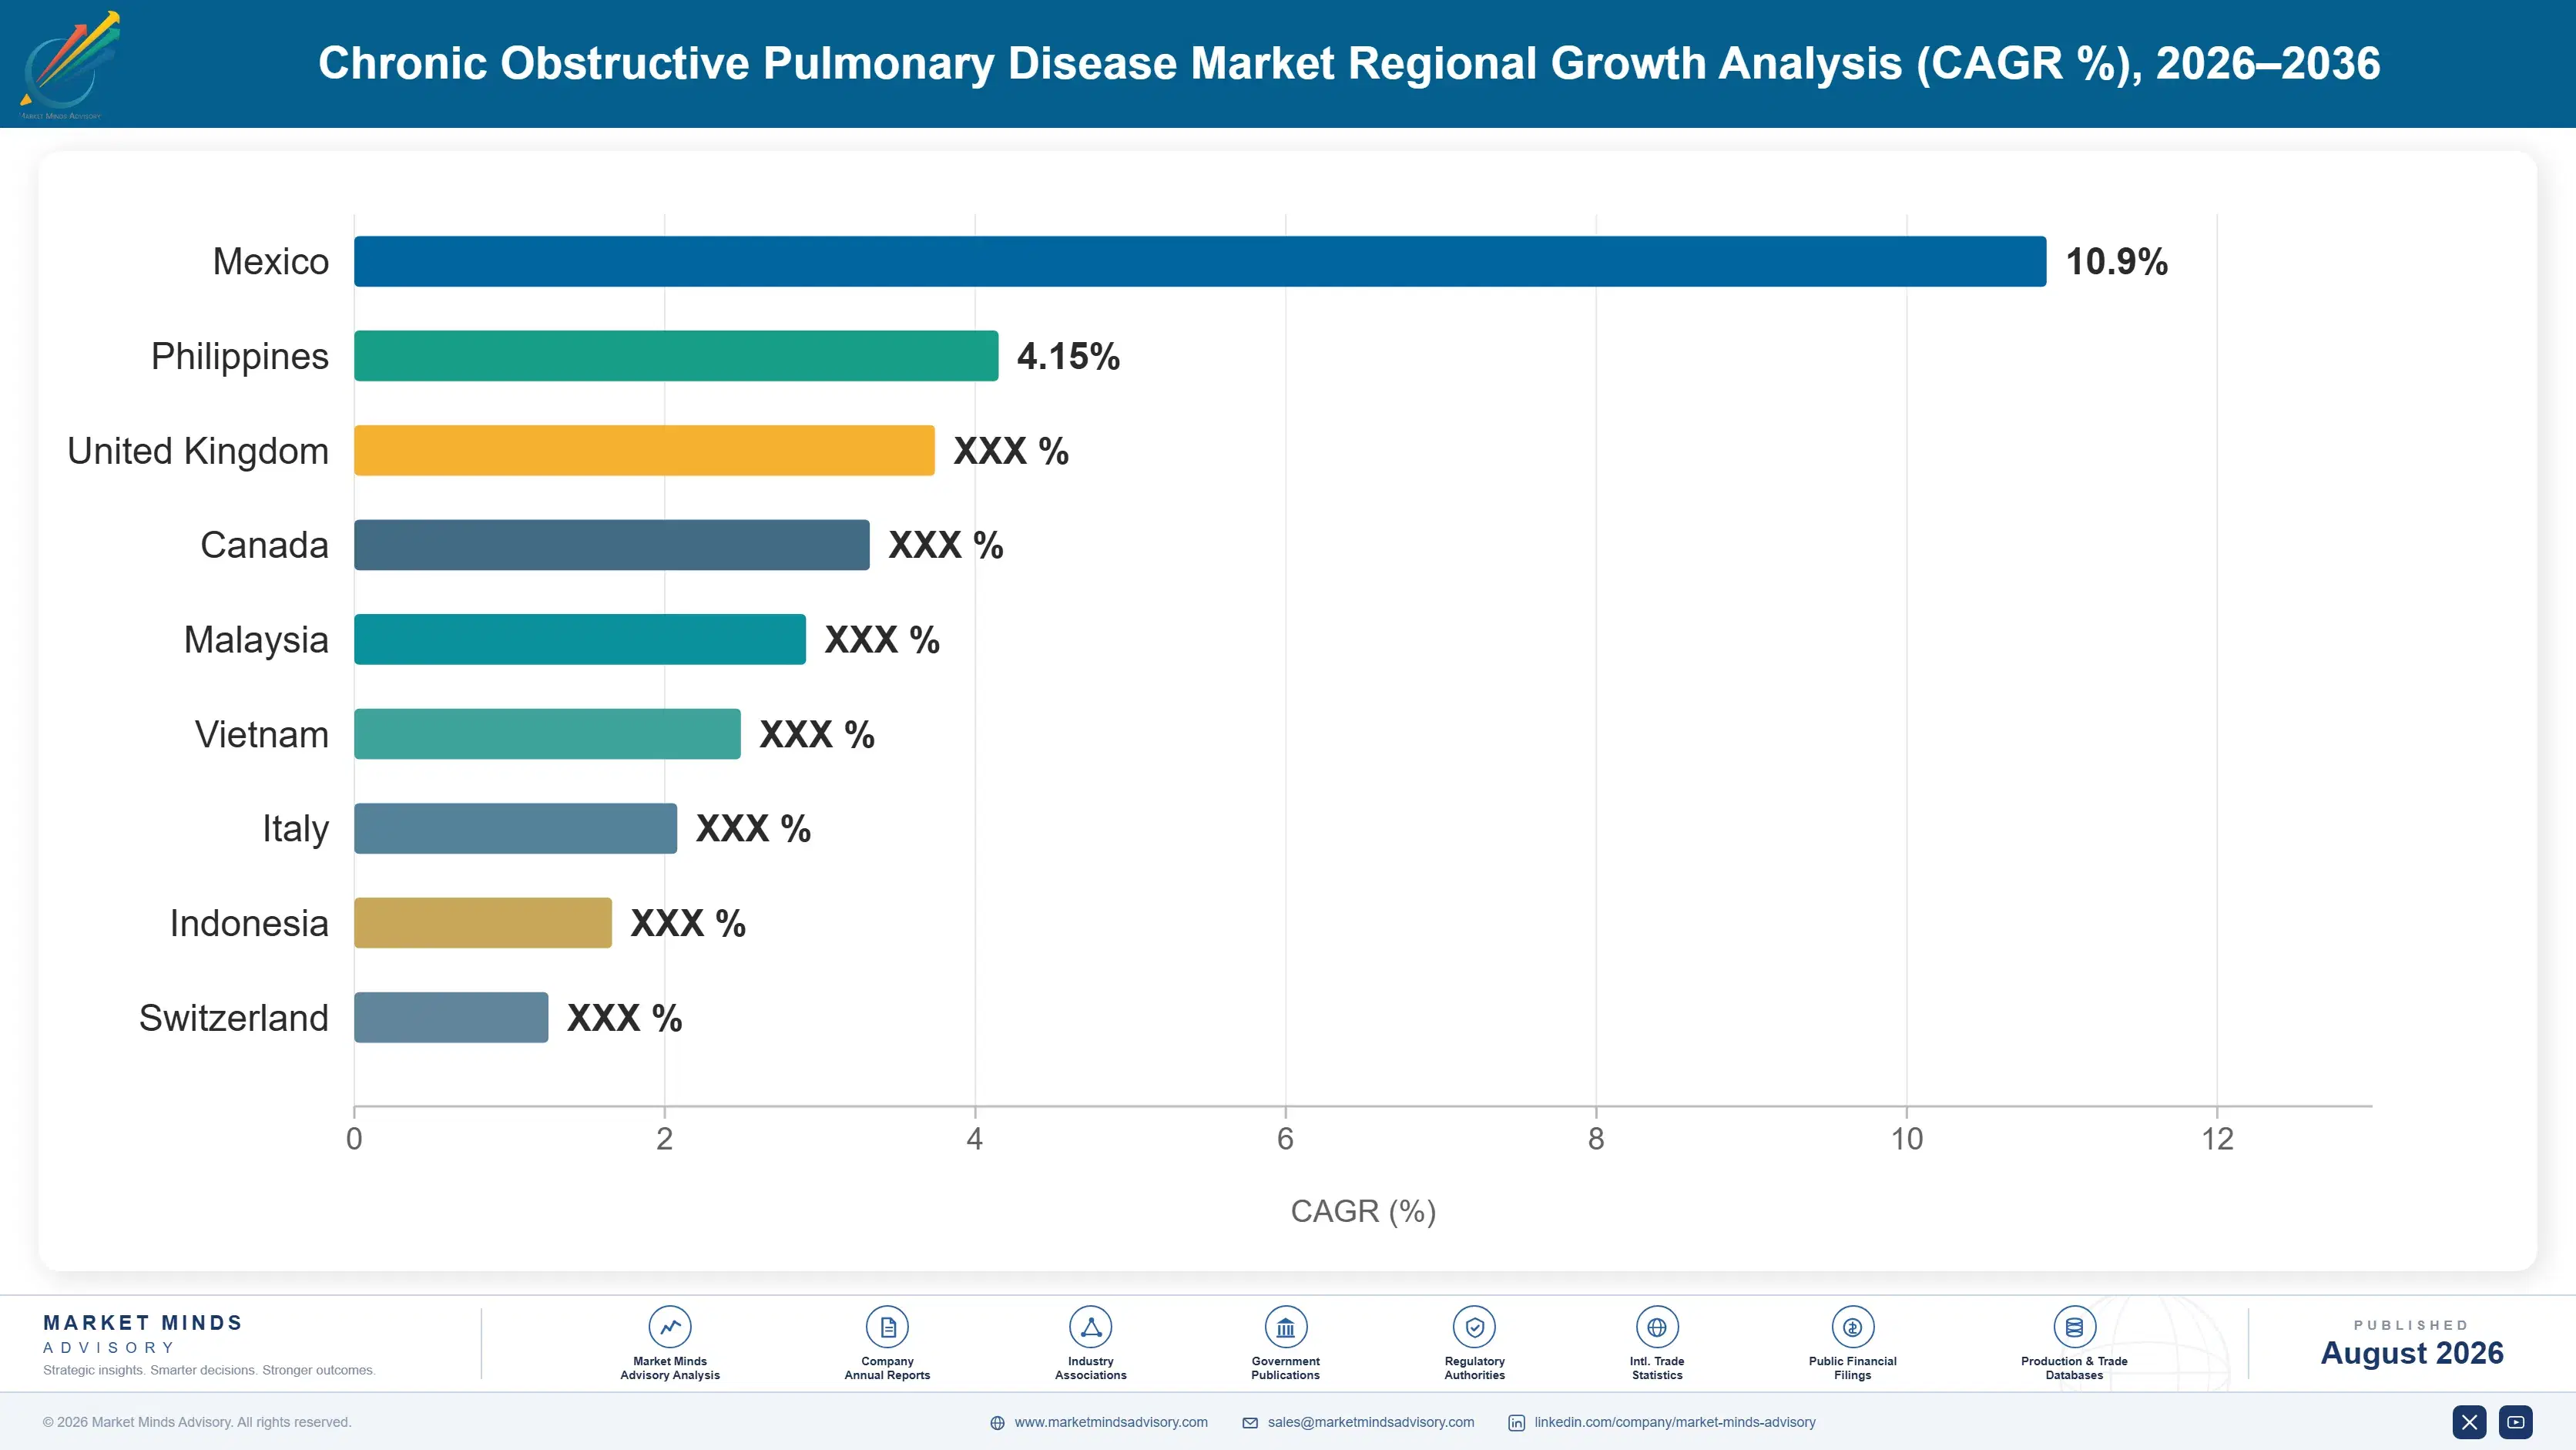
Regional Architecture and Country Demand Map

North America retains the largest revenue base on dense respiratory specialty infrastructure and established biologic reimbursement pathways, while East Asia is compounding fastest as China's expanding COPD diagnosis capacity and air pollution driven disease burden pull demand into the category nationwide across every major respiratory center hub today.

North America

United States respiratory specialty centers, concentrated around major academic pulmonology hubs, anchor the region's demand base as dense treatment infrastructure and established biologic reimbursement pathways drive proportional biologic and smart inhaler demand across the diagnosis pathway. Canadian respiratory networks continue steady treatment adoption tied to established public healthcare procurement systems covering major regional metropolitan markets. Broadening biologic coverage across major private and public insurance programmes continues accelerating phenotype-driven treatment well ahead of many international peer markets facing less developed biologic reimbursement infrastructure. Growth trails East Asia because the region's treatment installed base is comparatively larger and more mature relative to the expanding diagnosis investment driving growth elsewhere in the forecast.
Share: 30% | CAGR: 7.5% (2026 to 2036)

Western Europe

German and French respiratory networks, operating under some of the world's most established pharmaceutical reimbursement frameworks, sustain steady demand for both biologic and triple combination formats tied to national and European Union medical product regulatory frameworks. United Kingdom academic centers continue expanding phenotyping investment tied to growing National Health Service specialty respiratory programmes covering major regional teaching hospital clusters. Regional pharmaceutical developers maintain strong domestic penetration built on established pulmonologist prescribing relationships across the continent. Regional growth trails East Asia and South Asia as the market's already high treatment penetration limits the incremental upside further diagnosis investment expansion alone can provide relative to less mature markets elsewhere in the forecast ahead.
Share: 22% | CAGR: 6.2% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
chronic-obstructive-pulmonary-disease-market-country-cagr-analysis-1787306847245

Monetizing Phenotyping and Adherence Monitoring

Companies are shifting commercial models toward phenotyping partnership programmes, adherence monitoring service contracts, and multi-year treatment bundling agreements rather than one-time prescription sales, since pulmonologist demand for ongoing disease management support now rivals raw treatment pricing as a partnership selection criterion. This mirrors a broader shift across specialty pharmaceutical categories toward relationship-based commercial structures over transactional pricing.

Offering Phenotyping Partnership Access Support Programs

Companies are increasingly offering phenotyping partnership programmes that provide subsidized eosinophil testing and patient identification support across a respiratory center's full diagnosed patient population, converting what was historically a one-time diagnostic decision into recurring referral revenue tied directly to a center's biologic treatment initiation volume. Companies report partnership attach rates above 35% among respiratory centers completing their first phenotyping programme rollout, with renewal rates exceeding 77% once a center experiences a full diagnostic cycle without a service disruption. This partnership assurance increasingly determines brand selection ahead of raw treatment pricing during prescriber decisions.
Market Impact: Lifts recurring referral revenue to

Bundling Adherence Monitoring and Smart Inhaler Programs

Companies are increasingly bundling adherence monitoring and smart inhaler connectivity programmes into treatment purchases, converting a previously separate cost center into predictable recurring revenue while reducing the risk of a patient discontinuing therapy after treatment initiation without adequate monitoring support. Bundled monitoring support typically reduces a respiratory center's own coordination burden meaningfully during the ongoing treatment adherence window and long-term care planning process across departments. Companies report monitoring attach rates rising fastest among centers completing their first biologic prescriptions, with roughly 26% of new patients now including bundled monitoring programmes.
Market Impact: Cuts treatment discontinuation rate

Offering Multi-Year Treatment Access and Support Programs

Companies with dedicated patient support infrastructure are increasingly offering bundled multi-year treatment access programmes that give respiratory networks a lower cost path to comprehensive disease management support without negotiating individual patient assistance separately for each prescription. This bundled support path typically reduces a network's per-patient coordination cost meaningfully compared with individual case management, with bundled programmes now supporting roughly 19% of total new patient enrollments completed annually across major respiratory networks nationwide. Companies report bundling attach rates rising fastest among networks seeking comprehensive multi-year adherence support without significant per-patient investment burden.
Market Impact: Cuts per-patient support cost by ro

Structuring Multi-Region Access and Reimbursement Agreements

Companies are increasingly structuring multi-year access and reimbursement support agreements that extend consistent treatment access standards across a payer network's entire regional coverage territory rather than negotiating each jurisdiction independently, giving payer networks consistent treatment access standards across every operating market served today. Payer networks report administrative cost reductions of roughly 16% once access standardization eliminates the redundant formulary review overhead multiple incompatible jurisdiction standards previously required across their coverage territory. Companies with proven multi-region access support track records spanning dozens of markets are capturing outsized share of these agreements ahead of smaller competitors.
Market Impact: Cuts multi-region access administra

Who Controls the Margin Pool

The top five companies hold roughly 48% combined share, a moderate concentration reflecting both the substantial clinical validation and regulatory approval investment required for meaningful category participation and the fragmented base of smaller regional developers serving local generic bronchodilator relationships. The gap between leading developers and smaller regional producers is widening as respiratory networks restrict shortlists to companies with demonstrated biologic evidence and phe
Current competitive activity centers on three fronts: biologic platform expansion targeting eosinophilic patient demand, smart inhaler connectivity investment supporting broader adherence monitoring, and multi-region access agreement development supporting broader payer coverage. Several regional companies are pursuing partnerships with established reference laboratories rather than building internal phenotyping infrastructure independently, a faster but margin-diluting route to category participation.

Emerging pressure comes from Chinese and Indian pharmaceutical developers moving up the value chain from basic generic bronchodilator formats into certified triple combination and biologic systems sold initially to domestic respiratory networks but increasingly targeting export markets as clinical credibility accumulates. Rankings among the top five could shift if a leader fails to close its biologic therapy or phenotyping partnership gap, since pulmonologists increasingly evaluate evidence depth ahead of price during prescribing decisions.
chronic-obstructive-pulmonary-disease-market-company-positioning-matrix-1787306847762

Competitive Moat and Risk Dimensions

GLAXOSMITHKLINE PLC

Moat: Deep clinical evidence portfolio

GSK's years of accumulated clinical trial data and regulatory approval history give it durable credibility among pulmonologists who weigh proven exacerbation reduction evidence heavily, since qualifying a new respiratory therapy without comparable outcome data carries meaningful prescribing continuity risk. That credibility compounds with every additional real-world evidence study GSK publishes across new patient populations.
GLAXOSMITHKLINE PLC

Risk: Slower niche biologic customization

GSK's established triple combination inhaler franchise can slow its response to niche biologic mechanism opportunities that smaller specialized companies pursue more quickly, occasionally costing it partnerships among developers prioritizing rapid novel mechanism development over comprehensive franchise convenience across smaller emerging therapeutic categories and patient subgroups nationwide.
ASTRAZENECA PLC

Moat: Strong phenotyping network depth

AstraZeneca's long-standing investment in phenotyping partnership and diagnosis infrastructure gives it a design-in advantage with respiratory centers seeking a partner that already understands early phenotype identification workflow nuance rather than building that expertise from scratch. That diagnostic depth compounds with every additional testing partnership AstraZeneca establishes across new respiratory networks and academic centers.
ASTRAZENECA PLC

Risk: Premium pricing limits reach

AstraZeneca's premium biologic pricing structure can limit its reach among smaller, budget-constrained respiratory networks that prioritize lower cost triple combination formats over integrated biologic platform capability, occasionally ceding entry-tier accounts to lower-cost regional competitors focused on price-sensitive procurement segments and rural community markets.

Players Tracked

Prominent Players

GlaxoSmithKline plc
AstraZeneca plc
Boehringer Ingelheim International GmbH
Novartis AG
Sanofi SA

Other Key Players

Regeneron Pharmaceuticals Inc
Chiesi Farmaceutici SpA
Teva Pharmaceutical Industries Ltd
Viatris Inc
Cipla Limited
Sun Pharmaceutical Industries Ltd
ResMed Inc
Koninklijke Philips NV
Invacare Corporation
Inogen Inc
Adherium Limited
Vectura Group Limited
Verona Pharma plc
Theravance Biopharma Inc
Circassia Group plc

Recent Developments

JUNE 2025

GSK Commissions New Clinical Evidence Development Center

GSK commissioned a new dedicated clinical evidence development center for real-world outcomes research, adding meaningful research capacity to address surging demand from payers requiring rapid exacerbation reduction data across their expanding coverage review programmes worldwide. The center also supports faster registry data publication for prescribers.
Signal: Confirms clinical evidence capacity expans
SEPTEMBER 2025

AstraZeneca Signs Multi-Region Phenotyping Partnership Agreement

AstraZeneca signed a multi-year phenotyping partnership agreement with a major regional laboratory network, covering consistent diagnosis standards and direct respiratory center access across dozens of affiliated testing locations nationwide. The agreement is a partnership arrangement rather than a joint venture or acquisition, extending AstraZeneca's multi-region presence considerably.
Signal: Highlights phenotyping partnership bundlin
JANUARY 2026

Sanofi Acquires Regional Smart Inhaler Technology Developer

Sanofi completed the acquisition of a regional smart inhaler technology developer, strengthening its connected monitoring capability and expanding its ability to support respiratory networks navigating adherence tracking requirements across every major market worldwide. The deal reinforces Sanofi's positioning across the broader COPD market.
Signal: Signals continued consolidation of special

Biologic Manufacturing and Device Component Cost Exposure

Specialty biologic manufacturing, inhaler device components, and connectivity module electronics together represent an estimated 40 to 50% of COPD treatment cost of goods sold across most developers. Specialty biologic manufacturing capacity remains concentrated among a small number of qualified contract manufacturing partners, creating a narrower supply base than most broader pharmaceutical categories rely upon for comparable production inputs.
Specialty biologics manufacturing and electronics component cost inflation during 2021 and 2022 raised production costs broadly, and several companies flagged the disruption in annual reports as a persistent cost pressure affecting multiple respiratory therapeutics categories across the sector. Several companies disclosed that manufacturing capacity constraints stretched clinical trial and commercial supply timelines beyond expected windows during the tightest period, forcing some smaller developers to delay shipments or rely on costlier alternative manufacturing sourcing arrangements.

Smaller regional developers carry disproportionate exposure to these input swings since they lack the purchasing scale to negotiate multi-year fixed pricing directly with contract manufacturing partners that the top five companies secure more easily through established relationships. This gap is widest for developers dependent entirely on spot market manufacturing capacity, leaving them vulnerable to margin compression during supply constraint periods.
chronic-obstructive-pulmonary-disease-market-cost-volatility-analysis-1787306847956

Long-Term Biomanufacturing Supply Agreements

Leading companies now lock multi-year manufacturing capacity directly with contract manufacturing partners serving their primary production needs, avoiding the spot market cost volatility that stretched supply timelines during the 2021 to 2022 shortage and protecting patient treatment continuity against disruption across major markets worldwide throughout sustained periods of manufacturing constraint and reagent shortage risk.

Vertical Integration Into Biologics Manufacturing Capacity

Top five companies increasingly build internal biologic manufacturing capability rather than relying entirely on third-party contract producers, smoothing production timelines and insulating supply from the sourcing volatility smaller regional developers remain exposed to directly, a practice that has become standard operational policy since biologic therapy demand accelerated considerably across the industry and among smaller producers.

Diversified Manufacturing Sourcing Across Multiple Partners

Companies without full vertical integration are increasingly qualifying multiple contract manufacturing partners across different geographic regions, reducing exposure to any single facility's capacity constraints or production disruptions and giving companies greater negotiating leverage during periodic manufacturing pricing renewal discussions spanning multiple continents, regulatory jurisdictions, and currency zones served by their supply and distribution networks.

Portfolio Architecture for Margin Defence

Portfolio architecture splits across three tiers: entry priced generic bronchodilator monotherapies competing largely on treatment cost, certified triple combination inhalers carrying clinical evidence value that commands a durable price premium, and next generation biologic and smart inhaler systems bundled with phenotyping and monitoring services. Margins widen meaningfully moving up this ladder as clinical validation and regulatory approval barriers concentrate hardest at entry.
The volume versus premium tension is sharpest in generic bronchodilator monotherapies, where regional manufacturing competition has compressed prices fastest, pushing established developers to defend share through phenotyping and monitoring bundling rather than matching commodity pricing directly on treatment cost alone. Biologic and smart inhaler systems retain the strongest pricing power because clinical investment and multi-year monitoring relationships discourage payers from switching developers mid-treatment, a dynamic strengthening as adoption broadens.

High value margin pools concentrate in biologic and smart inhaler systems paired with continuous phenotyping and monitoring service contracts, where recurring referral revenue and high switching costs together support gross margins well above the portfolio average. Companies are prioritizing capital toward this tier even though it remains a minority of total patient volume treated across the broader portfolio today, betting the mix shifts decisively within the decade ahead.

Volume / Commodity-Adjacent Tier

Basic generic bronchodilator monotherapies competing primarily on treatment price against numerous regional manufacturers, with limited service attach and thin per-patient margins across most transactions and smaller patient populations worldwide.
Gross Margin: 20-28%

Premium / Certified Tier

Certified triple combination inhaler therapies serving complex symptom management cases, where clinical evidence depth and demonstrated exacerbation reduction support durable pricing power across the industry and every managed respiratory account served today.
Gross Margin: 34-42%

Sustainability / Regulatory / Next-Generation Tier

Biologic and smart inhaler systems bundled with phenotyping, monitoring, and disease management services, sold on recurring treatment assurance value rather than prescription pricing alone, increasingly the default specification for new investment.
Gross Margin: 46-54%
chronic-obstructive-pulmonary-disease-market-portfolio-architecture-1787306848451

Monitoring Contracts Anchor Recurring Respiratory Revenue

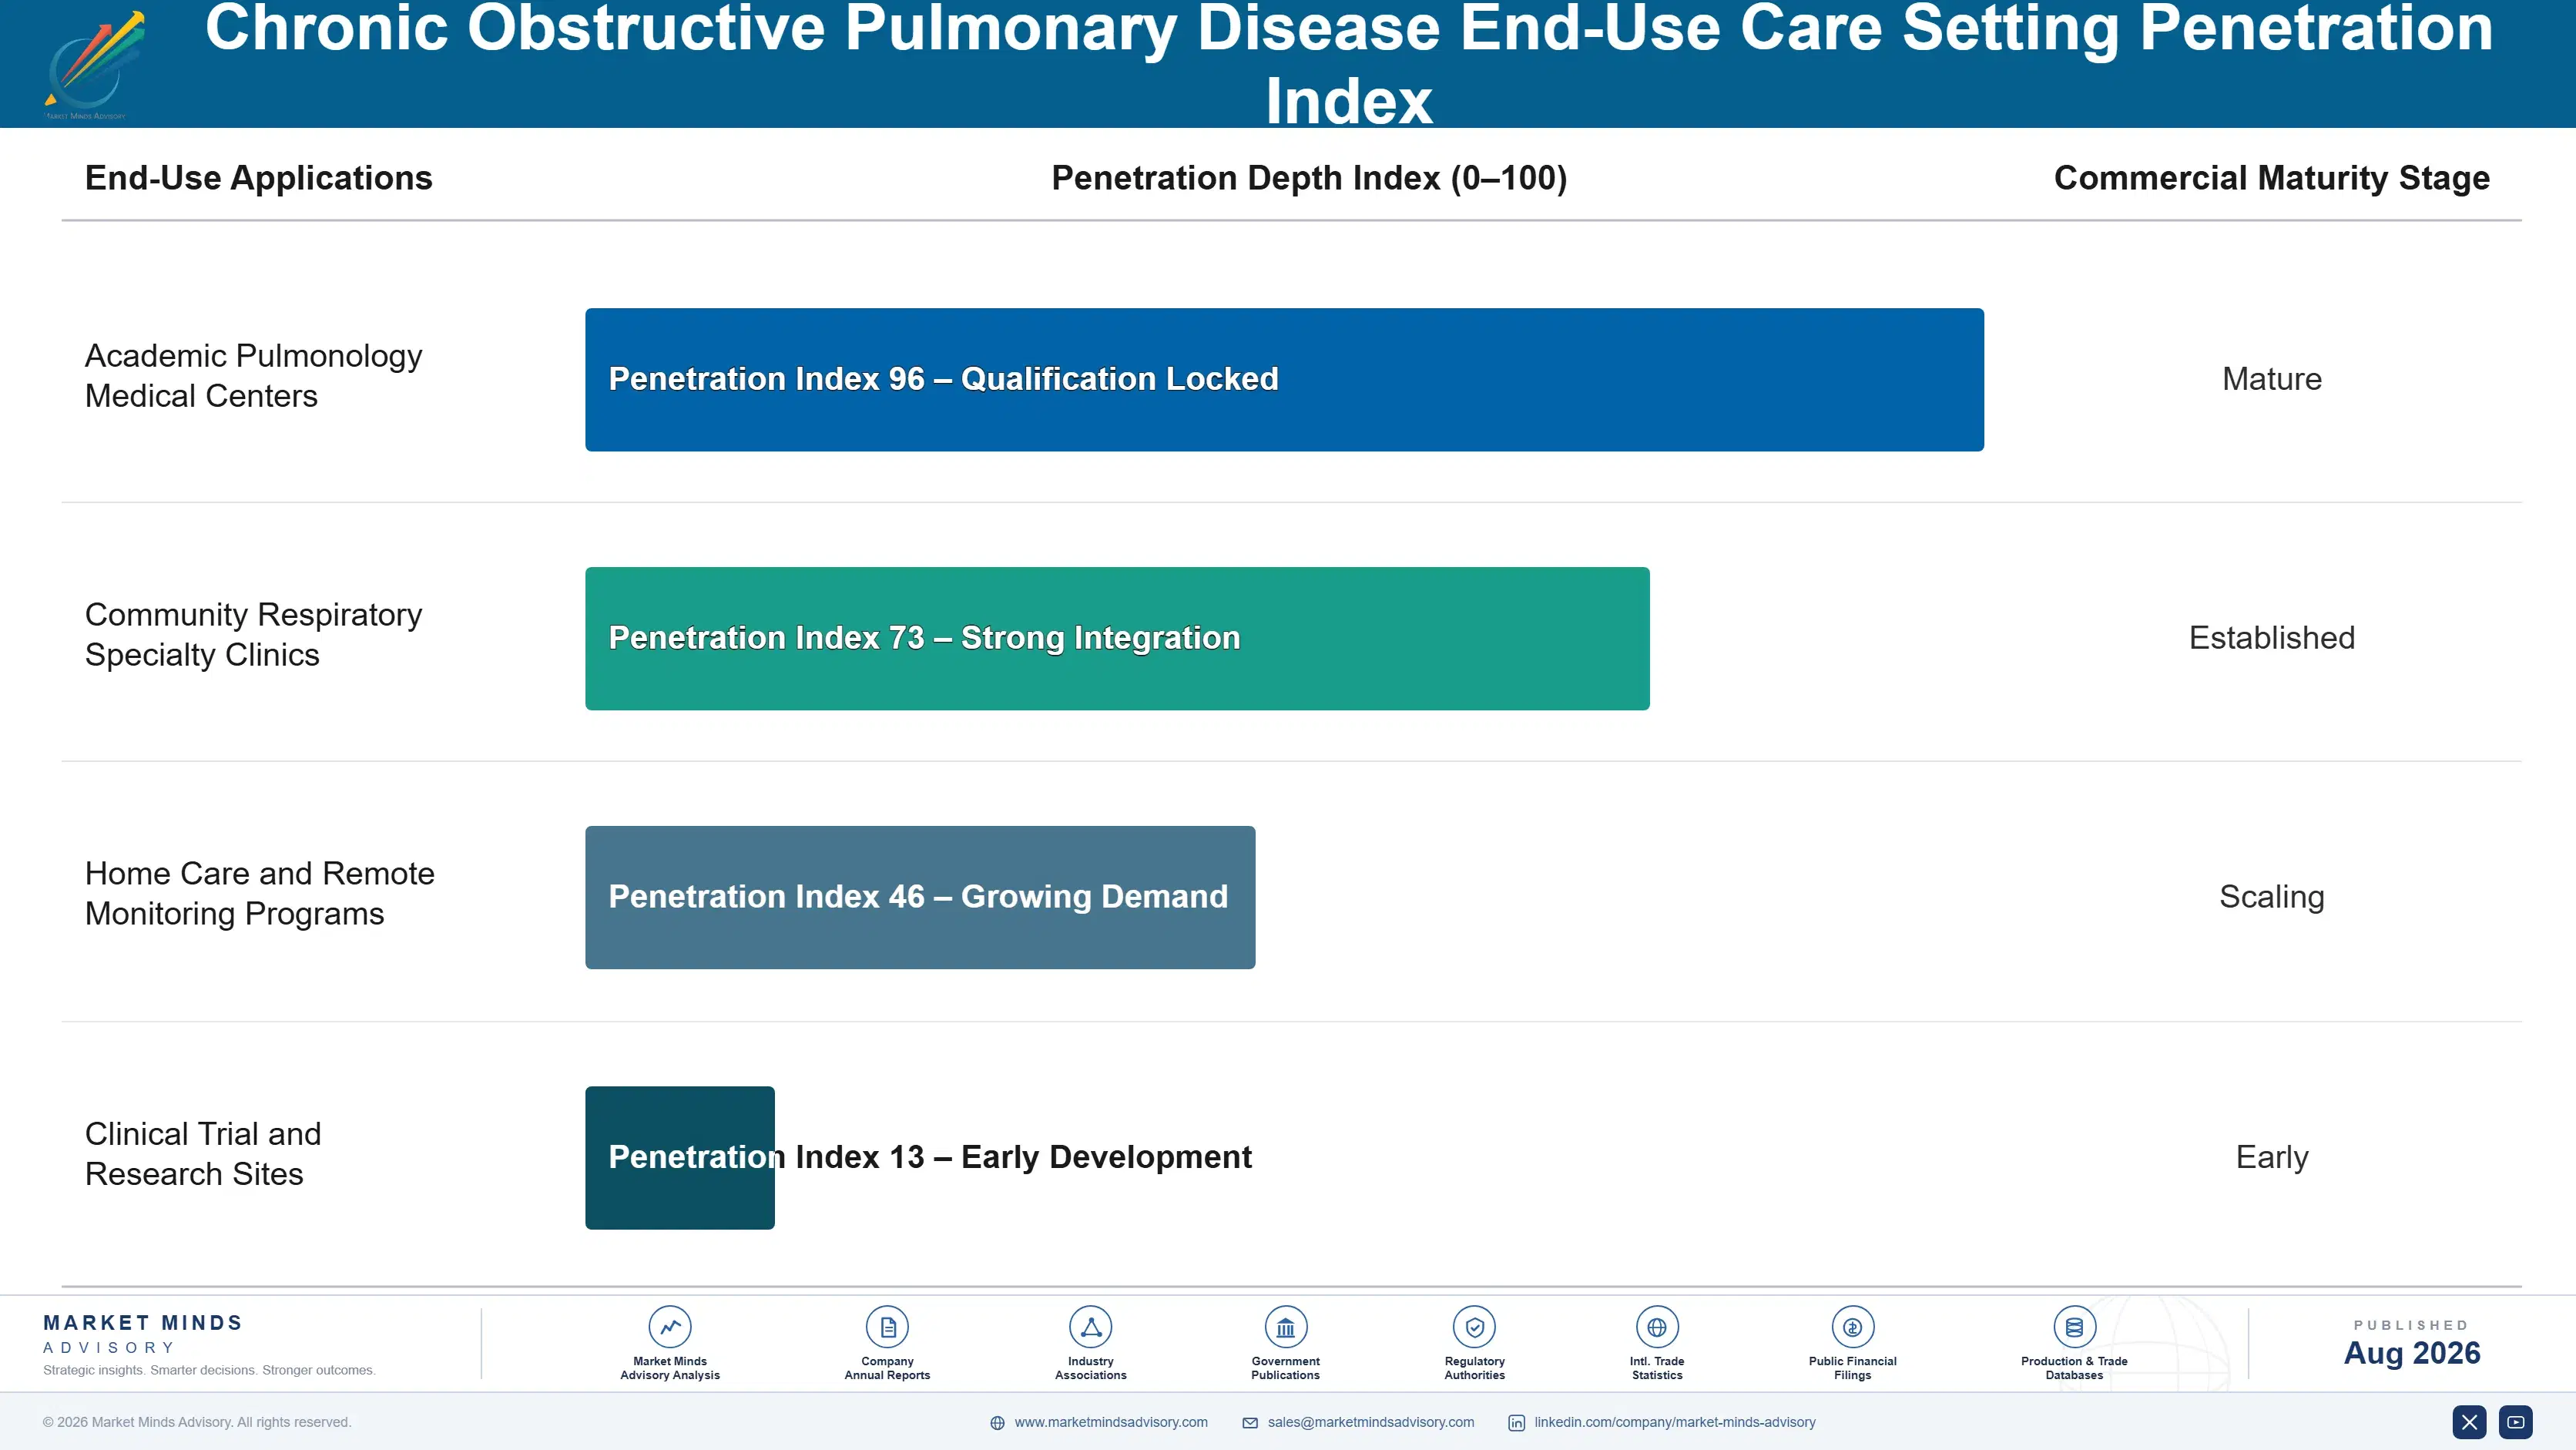
COPD treatment economics function increasingly like an annuity once a phenotyping relationship is established, since phenotyping partnerships, adherence monitoring services, and periodic treatment adjustment support generate recurring revenue for years after the initial diagnosis and treatment initiation closes. This recurring layer now represents a growing share of total category revenue and is the primary reason companies compete aggressively on initial patient diagnosis even at thin entry tie
Adoption depth varies sharply by end use vertical. Large academic respiratory centers run near saturated phenotyping and biologic treatment coverage and generate mostly renewal and monitoring demand, while smaller regional and rural respiratory practices are still building out first time phenotyping coverage, generating a different mix of new patient acquisition revenue layered on the maturing treatment base.

Buyer profiles are shifting generationally as younger pulmonologists who trained on phenotyping and biologic mechanisms during fellowship increasingly influence category growth alongside veteran clinicians who remember when COPD management meant the same triple combination inhaler for nearly every patient regardless of underlying inflammatory pathway. This is accelerating demand for companies with strong diagnosis and monitoring capability even among respiratory networks who historically evaluated treatment suppliers purely on unit cost and prescribing familiarity alone.
chronic-obstructive-pulmonary-disease-market-end-use-penetration-index-1787306848939

Where COPD Treatment Strategy Should Focus

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / CLINICAL EVIDENCE INVESTMENT

Prioritize exacerbation reduction data over marginal pricing

Treatment pricing has become a secondary consideration across most large payer coverage decisions, no longer the primary differentiator given rising pulmonologist expectations for measurable exacerbation reduction across every major patient population segment. Payers now evaluate exacerbation reduction evidence and monitoring infrastructure ahead of marginal price savings that once justified switching treatment brands on their own. Companies that continue competing primarily on standard treatment pricing risk losing share to evidence-focused rivals bundling monitoring, phenotyping, and treatment into a single recurring relationship that is harder to unwind once established.
02 / DIAGNOSIS MONETIZATION STRATEGY

Shift commercial models toward phenotyping and monitoring revenue

Standard bronchodilator margins will keep compressing as regional manufacturers gain share at the entry tier of the category across most emerging markets. Companies that convert phenotyping partnerships, adherence monitoring, and multi-year treatment bundling into contracted recurring revenue will outperform peers still pricing primarily around one-time prescription sales alone. This shift also raises payer switching costs meaningfully, since replacing a treatment relationship requires displacing an entrenched, multi-year phenotyping and monitoring partnership built over years of accumulated pulmonologist trust and shared patient data.
03 / REGIONAL GROWTH PRIORITIZATION

Weight investment toward South Asia and East Asia over mature markets

South Asia and East Asia are compounding faster than Western Europe on both share and CAGR, driven by expanding phenotyping infrastructure, rising domestic clinical capability, and first time diagnosis access across previously underserved regional patient populations. Companies weighting phenotyping and treatment investment toward these regions ahead of competitors will capture a disproportionate share of new patient enrollment revenue. Mature markets, running mostly on renewal demand, simply cannot replicate that category of growth at comparable scale or rate over the coming decade of forecast activity.
04 / PAYER COVERAGE RESPONSE

Build outcome-based contracts ahead of formulary pressure

The gap between rising biologic therapy adoption and tightening payer scrutiny represents a substantial risk that most developers are not yet equipped to manage efficiently given the specialized health economic outcomes infrastructure required. Companies that invest early in dedicated outcome-based value contract programmes will be better positioned to defend formulary placement without the extended payer negotiation timelines currently limiting some competitors today. Companies ignoring this opportunity risk ceding coverage-dependent revenue to competitors who have already solved the reimbursement pressure problem.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Chronic Obstructive Pulmonary Disease Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Chronic Obstructive Pulmonary Disease Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a regional respiratory network operating fourteen pulmonology specialty clinics across multiple metropolitan markets, reporting annual specialty pharmaceutical procurement spending in the tens of millions of dollars across its treatment portfolio (client-reported, unverified by MMA). Its existing sourcing relied on fragmented regional treatment brands with inconsistent phenotyping partnership capability across its distributed clinic network.
STRATEGIC CHALLENGE
Facing rising patient demand for earlier phenotype-driven diagnosis and increasing competitive pressure from phenotyping-integrated peer respiratory networks, clinical leadership sought to consolidate treatment brand partnerships toward fewer testing-capable suppliers within twelve months, while avoiding any disruption to existing patient care schedules across every active clinic worldwide and regional site today.
MMA APPROACH
MMA benchmarked five candidate treatment brand suppliers against phenotyping partnership depth, monitoring programme quality, and total cost of ownership over a five year horizon, then modeled consolidation sequencing to minimize patient care disruption across the client's highest volume clinics during the phased brand standardization programme currently under review by clinical and network leadership.
KEY FINDINGS
  1. Three of five candidate suppliers evaluated could not demonstrate consistent phenotyping partnership coverage across all of the client's active clinic locations reviewed.
  2. Consolidated treatment brand procurement reduced projected annual patient care coordination costs by 29% versus continued fragmented regional sourcing across comparable patient volumes, based on modeling completed during evaluation (client-reported, unverified by MMA).
  3. Centralizing phenotyping partnership management was projected to cut clinical operations administrative workload meaningfully across the client's regional clinic network, according to internal operations modeling completed by the client.
  4. Clinics facing the most imminent patient diagnosis growth carried the highest near term consolidation priority, reprioritizing the client's original sequencing considerably ahead of the initial twelve month plan.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1-4): Complete technical and testing partnership evaluation of the three highest-scoring candidate suppliers identified through careful independent review. Phase 2: Phase 2 (Months 5-9): Execute supplier consolidation across the highest volume respiratory clinics in strict priority sequence today and beyond. Phase 3: Phase 3 (Months 10-12): Finalize network-wide brand standardization and centralized monitoring dashboard fully enabled nationwide, with clinical leadership sign-off completed across every active site.
OUTCOME
The respiratory network completed brand consolidation across all priority clinics within the twelve month window and reported meaningfully improved patient diagnosis outcomes during subsequent internal reviews (client-reported, unverified by MMA). Clinical leadership gained centralized phenotyping visibility previously unavailable across its distributed regional clinic network and treatment partner base.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Chronic Obstructive Pulmonary Disease Market?

The global COPD market reached an estimated $21.5 billion in 2025. Growth is driven by expanding biologic therapy approval and rising smart inhaler adoption worldwide.

How large will the Chronic Obstructive Pulmonary Disease Market be by 2036?

The market is projected to reach approximately $49.1 billion by 2036, roughly 2.12 times its 2026 value. Biologic therapies for eosinophilic COPD drive most of the added value across the category.

What is the CAGR for the Chronic Obstructive Pulmonary Disease Market 2026 to 2036?

The base case CAGR is 7.8% through 2036. Bull and bear scenarios range from roughly 6.5% to 9.0%, depending on biologic adoption pace and phenotyping infrastructure expansion speed.

Which segment is growing fastest?

Biologic therapies for eosinophilic COPD lead at a 14.5% CAGR, about 1.86x the overall market rate. Growth is concentrated among academic pulmonology centers and specialty respiratory practices.

Who are the major companies in the Chronic Obstructive Pulmonary Disease Market?

GlaxoSmithKline, AstraZeneca, Boehringer Ingelheim, Novartis, and Sanofi lead the category. Combined, the top five companies hold roughly 48% of global revenue on a consistent basis.

Which country is growing fastest?

China leads country level growth at an estimated 13.5% CAGR. Expanding diagnosis capacity and air pollution driven disease burden are driving treatment demand across the region's respiratory base.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Treatment Mechanism and Therapeutic Category

  • Triple Combination Inhaled Therapies
  • Biologic Therapies for Eosinophilic COPD
  • Short-Acting and Long-Acting Bronchodilator Monotherapies
  • Home Oxygen and Respiratory Support Devices
  • Pulmonary Rehabilitation and Digital Monitoring Services
  • Smart Inhaler and Connected Device Platforms

By End-Use Care Setting

  • Academic Pulmonology Medical Centers
  • Community Respiratory Specialty Clinics
  • Home Care and Remote Monitoring Programs
  • Clinical Trial and Research Sites

By Commercial Dimension

  • Direct Specialty Pharmacy Distribution
  • Payer and Formulary Access Agreements
  • Phenotyping Laboratory Partnerships
  • Patient Assistance and Support Programs

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The COPD market covers pharmaceutical products, devices, and services used to treat chronic obstructive pulmonary disease, spanning triple combination inhaled therapies, biologic therapies for eosinophilic COPD, short-acting and long-acting bronchodilator monotherapies, home oxygen and respiratory support devices, pulmonary rehabilitation and digital monitoring services, and smart inhaler and connected device platforms. Asthma treatments without a confirmed COPD diagnosis are excluded from market scope.
Quantitative Units
USD billions (current prices); treated patients where disclosed
Segmentation Dimensions
By Treatment Mechanism and Therapeutic Category; By End-Use Care Setting; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Thailand, Malaysia, Singapore, UAE, Saudi Arabia, South Africa, Egypt, Turkey, Poland, Netherlands, Italy, Spain, Switzerland, Argentina, Colombia, Czech Republic, and additional markets relevant to this sector
Key Companies Profiled
GlaxoSmithKline plc, AstraZeneca plc, Boehringer Ingelheim International GmbH, Novartis AG, Sanofi SA, Regeneron Pharmaceuticals Inc, Chiesi Farmaceutici SpA, Teva Pharmaceutical Industries Ltd, Viatris Inc, Cipla Limited, Sun Pharmaceutical Industries Ltd, ResMed Inc, Koninklijke Philips NV, Invacare Corporation, Inogen Inc, Adherium Limited, Vectura Group Limited, Verona Pharma plc, Theravance Biopharma Inc, Circassia Group plc
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-172
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Chronic Obstructive Pulmonary Disease Market Report (2026 to 2036).

The full report delivers a complete quantitative and qualitative assessment of the global COPD market through 2036. It includes detailed segmentation by treatment mechanism and therapeutic category, care setting, and commercial channel, alongside country level sizing across twenty-eight markets covering every major respiratory demand center. Competitive profiles cover twenty companies with clinical evidence depth, phenotyping partnership reach, and manufacturing benchmarking assessed on a consistent revenue basis. Buyers also receive access to the underlying primary survey and expert interview datasets referenced throughout the analysis, along with editable data tables.
Segment level CAGR and sizing tables
Regional and country level market breakdowns
Twenty company competitive profiles and benchmarks
Detailed phenotyping partnership benchmarking matrix overview
Input cost and supply chain risk analysis
Complete primary survey and expert interview datasets included

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts