Market Minds Advisory
Burn Care Market

Burn Care Market: Bioengineered Skin Substitutes Redraw Grafting Economics

Burn surgeons are specifying bioengineered skin substitutes over autografts in cases where donor site availability is limited, forcing legacy wound dressing makers to defend commodity volume against regenerative products priced an order of magnitude higher.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$3.0BMarket Size 2025
2036 FORECAST VALUE$7.0BBase Case , 2026 to 2036
CAGR 2026 TO 20368.0 %Bull 9.2% / Bear 6.8%
INCREMENTAL OPPORTUNITY$3.8BNet 10- year value creation
EXPANSION MULTIPLE2.16x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Burn treatment has split into two distinct care pathways, as bioengineered skin substitutes capture severe, donor-site-limited cases while advanced wound dressings continue serving the broad majority of moderate burn injuries at a fraction of the cost. Purchasing committees increasingly evaluate that split as a genuine capital allocation decision.
Bioengineered skin substitutes are pulling ahead of every other product category, growing considerably faster than advanced dressings as burn surgeons increasingly specify regenerative products for patients with limited donor site availability. Integra LifeSciences and MiMedx still anchor much of the clinical evidence base behind that shift, but Organogenesis is undercutting integration complexity to win regional burn centre accounts, and North America consumes the largest share of that spending on established trauma centre infrastructure.
Competitive character splits between diversified wound care majors defending broad dressing portfolios and specialist regenerative medicine companies competing on graft take rate and healing speed. Regulatory clearance pathways remain more predictable than hospital reimbursement policy, which varies by payer in how it prices regenerative products against grafting. That variability slows regenerative adoption in health systems without dedicated capital planning capacity for premium products currently.
Market Definition
The burn care market covers products and clinical support technologies used in the treatment and management of thermal, chemical, and electrical burn injuries, including bioengineered skin substitutes and grafts, advanced wound dressings, negative pressure wound therapy devices, burn-specific topical pharmaceuticals, debridement products, and burn unit monitoring and support equipment. It excludes general trauma and surgical equipment not burn-specific and cosmetic scar revision procedures unrelated to acute burn treatment.
Base Year Value
$3.0B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
8.0% base case. Bull 9.2%. Bear 6.8%.
Fastest Growth Segment
Bioengineered Skin Substitutes and Grafts: 13.0% CAGR
Fastest Growth Country
India: 12.0% CAGR
Fastest Growth Region
South Asia and Pacific: 10.0% CAGR
Largest Region
North America: 31% of 2025 global value
Market Leaders
Integra LifeSciences Holdings Corporation, MiMedx Group Inc., Organogenesis Holdings Inc., Smith+Nephew plc, Mölnlycke Health Care AB. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

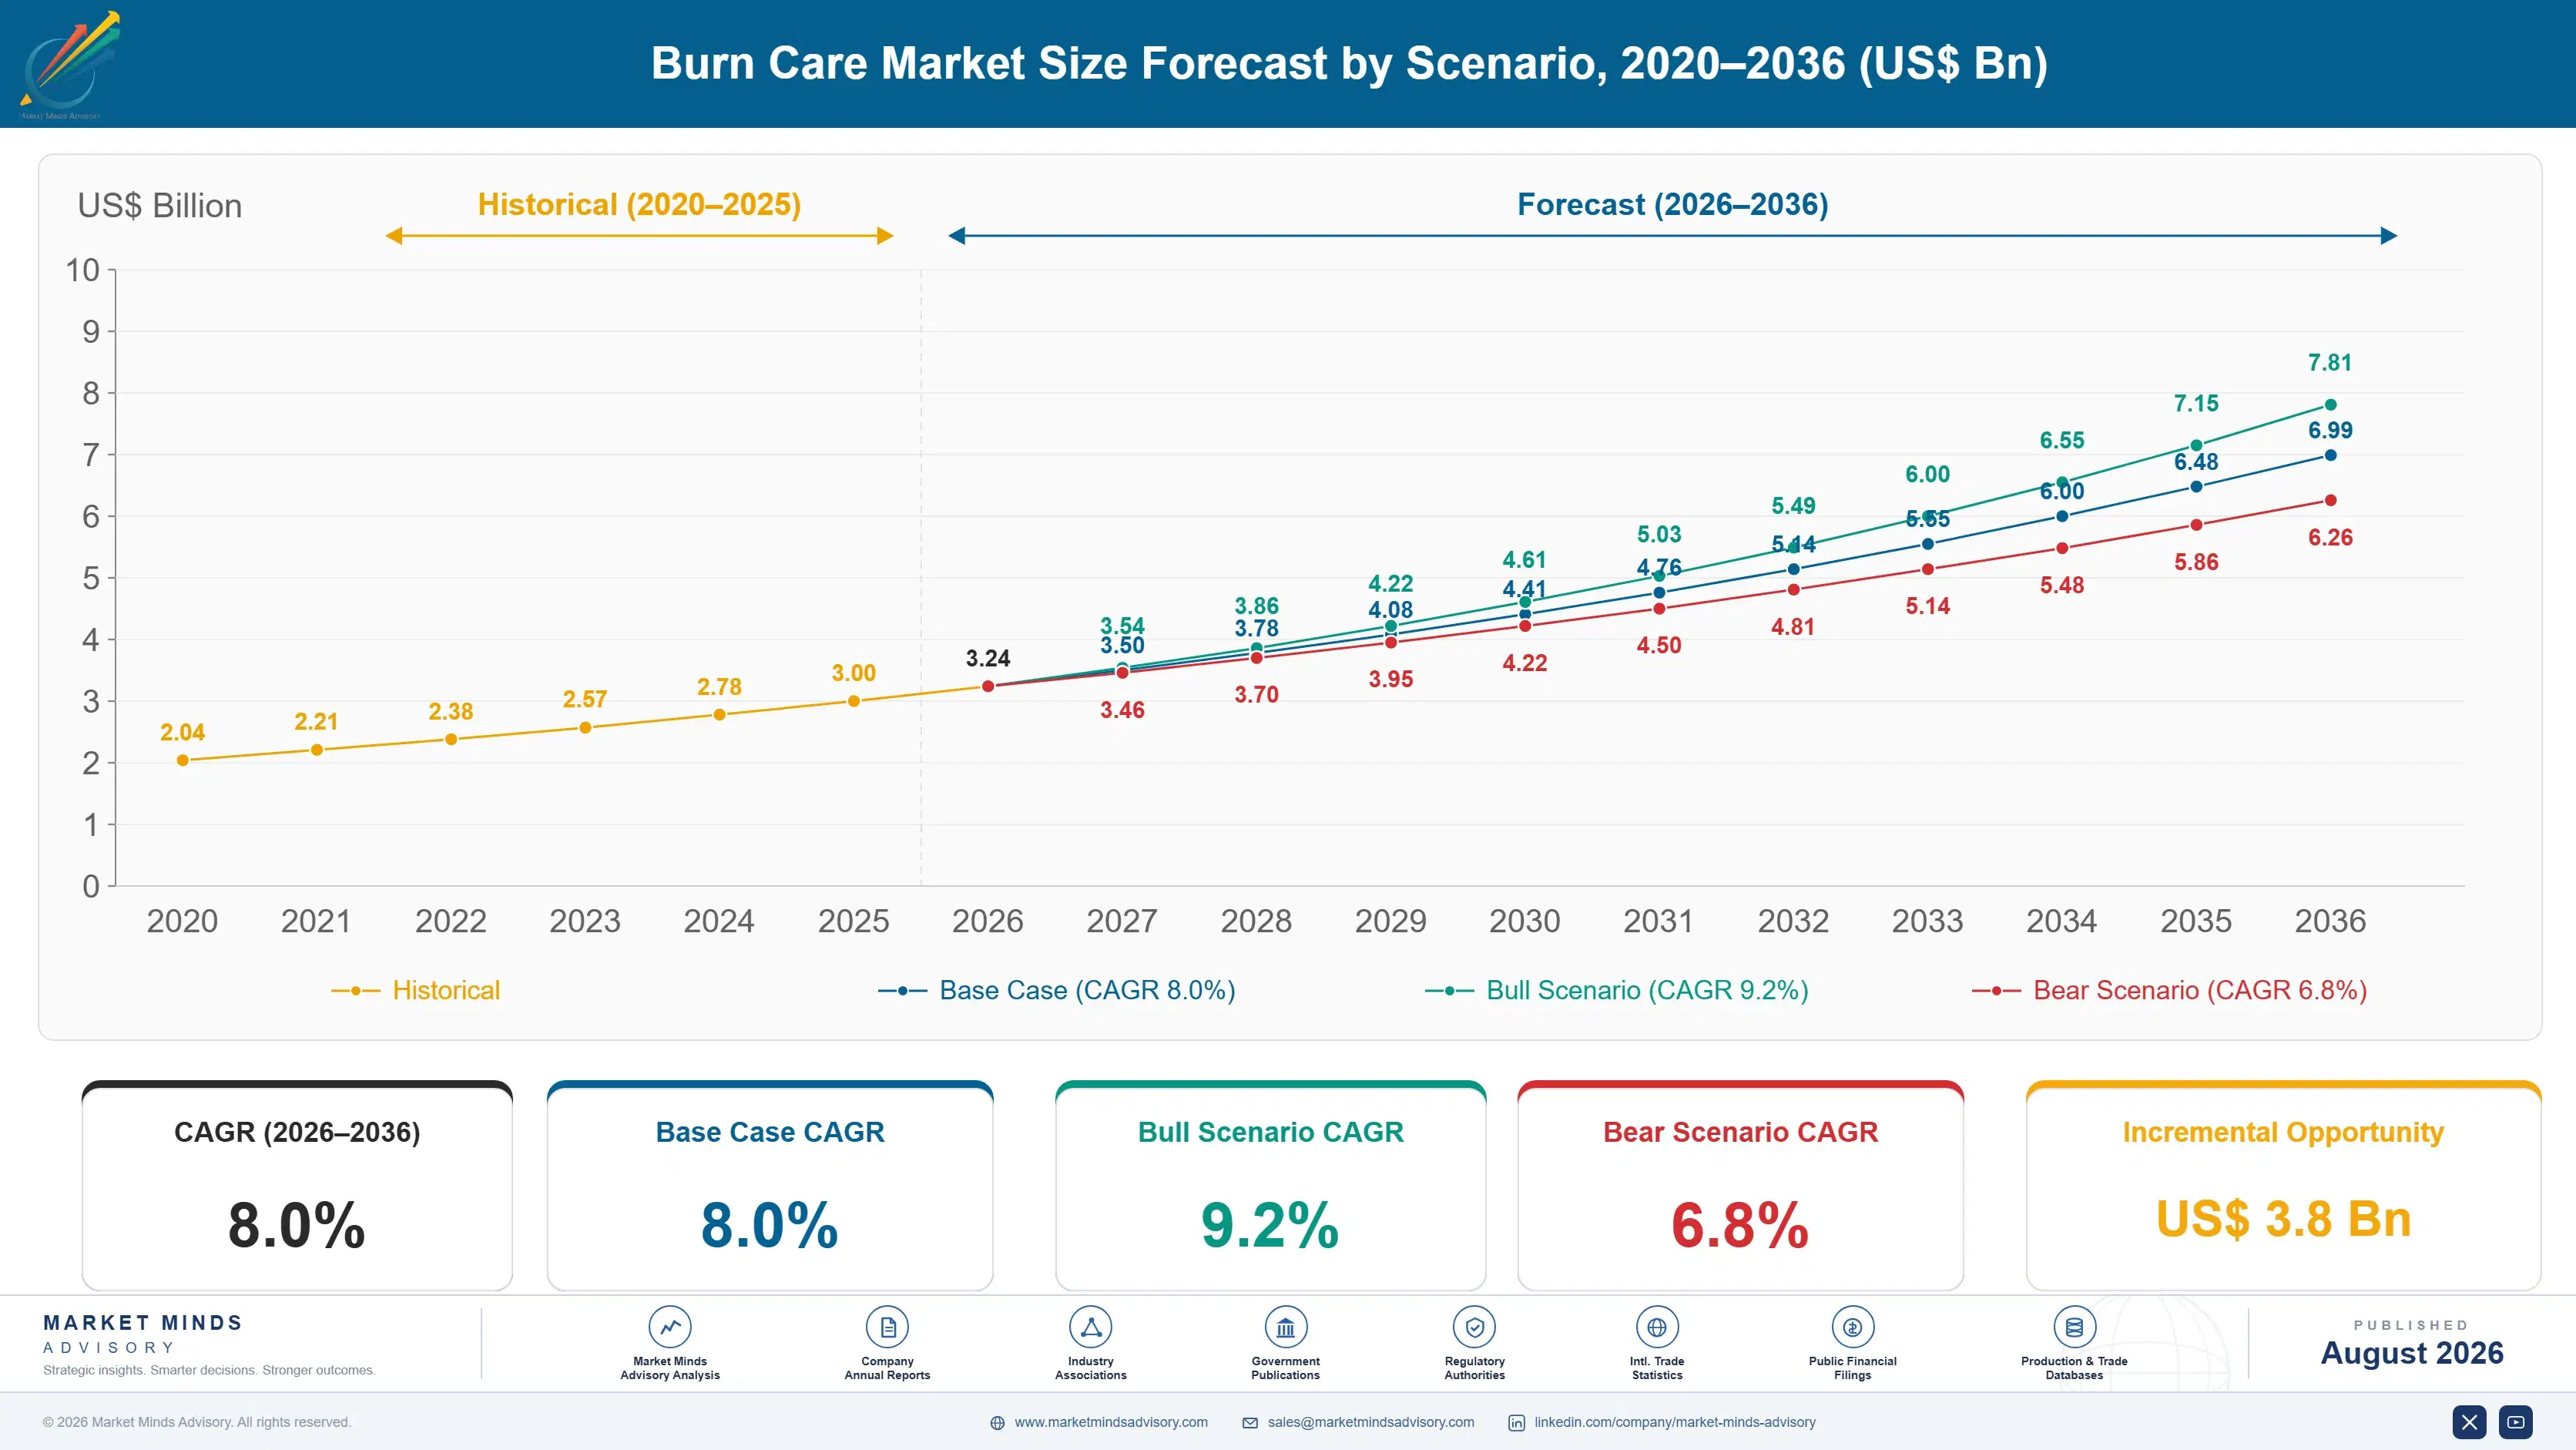
Burn Care Market Forecast Scenarios

burn-care-market-size-forecast-scenario-1787304386007
Between 2020 and 2025 the market grew at a 7.0% historical CAGR, tracking general trauma and wound care spending closely through most of the period. Bioengineered skin substitute adoption only gained real momentum from 2023 onward as outcome evidence accumulated. Reporting that period remained limited given fragmented burn centre procurement disclosure practices. Digital outcome tracking stayed limited to academic centres through that span.
The base case carries the market to an 8.0% CAGR through 2036 on three mechanisms. First, burn surgeons increasingly specify bioengineered skin substitutes for patients with limited donor site availability rather than relying on autografting alone. Second, negative pressure wound therapy adoption grows as burn units target faster wound closure and reduced infection risk. Third, expanding burn centre infrastructure in developing markets keeps pulling new demand into formal specialised treatment pathways.
The bull case reaches 9.2% if payers expand reimbursement parity for bioengineered substitutes against conventional grafting faster than currently modelled, pulling forward burn centre adoption across a compressed timeline. The bear case falls to 6.8% if hospital capital budgets tighten broadly, keeping demand tied mostly to standard dressing replacement rather than new capability specification. That volatility already shows up in extended capital approval timelines.

Why Donor Site Limitations Are Redrawing Grafting Economics

Three forces converge on burn care demand at once. Burn surgeons increasingly specify bioengineered skin substitutes for patients with limited donor site availability rather than relying on autografting alone. Negative pressure wound therapy adoption grows as burn units target faster wound closure and reduced infection risk. And expanding burn centre infrastructure in developing markets keeps pulling new demand into formal treatment pathways. Regulatory bodies are only beginning to standardise r
MARKET CONCENTRATIONCR5: 48%Top five wound care makers hold nearly half
AVERAGE SELLING PRICEUSD 12 to 3,800 per treatment unitPricing spans standard dressings to full bioengineered grafts
TOP PRODUCING COUNTRY SHAREUSA: 28% of units producedRegenerative medicine manufacturing capacity remains heavily concentrated domestically
CAPACITY UTILISATION70 to 82%Certified production lines run consistently near committed capacity
INPUT COST SHARE26 to 34% of COGSBiologic tissue processing and cell culture costs dominate spending
REPLACEMENT CYCLE LENGTHSingle treatment episodeProducts treat one acute injury rather than recurring chronic use
Commercially, the market behaves like specialised regenerative medicine rather than generic wound care supplies. Makers compete on graft take rate, healing speed, and scar outcome data rather than by price alone, because a failed graft forces a costly repeat procedure and extends a patient's hospital stay considerably. That specification discipline protects margin for makers with genuine tissue engineering depth and keeps generic dressing manufacturers out of clinical-grade contracts.
Over the next decade, graft take rate becomes the real differentiator. Makers that combine bioengineered substitute science with faster healing outcome data are capturing the severe-injury contracts increasingly dominating new specification spending, while dressing-only makers lose ground even where basic wound coverage is comparable. That gap is already reshaping which makers win the largest national framework tenders outright.
"A failed graft doesn't just cost the hospital a repeat procedure, it costs the patient another month of recovery and infection risk, so burn surgeons are paying up for take rate data long before they ever ask about the sticker price of the product."
Director, Wound Care and Regenerative Medicine Practice · MMA Medical Devices an

Market Trends

Bioengineered Substitutes Reduce Dependence On Donor Site Grafting

Burn surgeons increasingly specify bioengineered skin substitutes for patients with limited healthy donor site availability, since severe burns covering a large body surface area leave insufficient unburned skin to harvest for conventional autografting. That substitute approach lets surgeons close large wounds in stages without exhausting a patient's limited donor sites entirely, considerably reducing the number of separate harvesting procedures a patient must undergo. Integra LifeSciences and MiMedx have both expanded bioengineered substitute product lines specifically to capture burn centres treating large total body surface area injuries. That reduced burden also cuts overall hospital resource use across each treatment episode.
Market Impact: Formalises 20-25% of trauma care
Negative Pressure Wound Therapy Speeds Burn Wound Closure

Burn units increasingly deploy negative pressure wound therapy devices that apply controlled suction to a wound dressing, since that mechanical stimulation measurably accelerates granulation tissue formation compared with passive dressing alone. That acceleration is letting burn units close wounds and prepare grafting sites considerably faster than conventional dressing protocols achieved previously. 3M and Smith+Nephew have both expanded negative pressure product lines specifically to serve burn units targeting faster wound closure and reduced infection risk. Payers increasingly favour that faster closure given measurably lower complication rates overall. That improvement is reshaping how burn units evaluate device replacement decisions.
Market Impact: Lifts reimbursed volume by 25-30%

Market Opportunities and Growth Drivers

Expanding Trauma Infrastructure Formalises Burn Treatment Access

Growing dedicated burn centre infrastructure in developing markets is pulling burn treatment out of general trauma wards and into formal specialised units that specify certified regenerative products rather than lower-cost, undifferentiated dressing alone. That formalisation is concentrated in urban tertiary hospital networks currently, with rural trauma care still relying on general wound management considerably more often. Health ministries in several fast-growing markets increasingly build dedicated burn centre capacity into national trauma infrastructure planning rather than leaving it to individual hospital discretion. That formalisation is reshaping how ministries plan long-term trauma infrastructure investment.
Market Impact: Limits access to 15% of patients

Published Outcome Data Expands Regenerative Product Reimbursement

Growing published clinical evidence demonstrating superior graft take rates and reduced scarring for bioengineered skin substitutes is pushing payers to expand reimbursement coverage that previously treated these products as an unproven premium option. That evidence has moved bioengineered substitutes from a discretionary surgeon preference into a clinically justified specification for documented severe cases. Payers increasingly cover bioengineered substitutes for large total body surface area burns by default, with moderate-injury coverage expanding as more long-term outcome data accumulates. That evidence base is expanding quickly as more centres adopt bioengineered treatment protocols.
Market Impact: Excludes 20-30% of rural treatment

Market Restraints and Challenges

High Bioengineered Substitute Cost Limits Access In Cost-Sensitive Markets

Bioengineered skin substitutes cost considerably more than conventional wound dressings and autografting, a price gap that public health systems in cost-sensitive markets absorb poorly across constrained trauma care budgets, the root cause being that regenerative product manufacturing requires cell culture and tissue processing infrastructure far more expensive than standard dressing production. That cost gap keeps bioengineered substitute access concentrated in high-income markets with developed reimbursement systems, leaving patients in cost-sensitive regions dependent on conventional treatment regardless of clinical severity. Makers are responding with tiered pricing programmes in select cost-sensitive markets.
Market Impact: Cuts donor harvest procedures 40%

Cold-Chain Logistics Constrain Rural Burn Centre Access

Many bioengineered skin substitutes require cold-chain storage and handling from manufacturing through clinical application, a logistics requirement that rural and smaller burn treatment facilities struggle to maintain reliably, the root cause being that living cell-based products degrade rapidly outside controlled temperature ranges unlike conventional dressings. That logistics constraint keeps comprehensive bioengineered access concentrated in urban tertiary burn centres with dedicated cold-chain infrastructure, leaving rural facilities dependent on conventional grafting. Makers are responding by developing room-temperature-stable formulations specifically for facilities lacking reliable cold-chain capability. Several makers now treat logistics reach as a core strategic differentiator against competitors.
Market Impact: Speeds wound closure by 25-35%
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

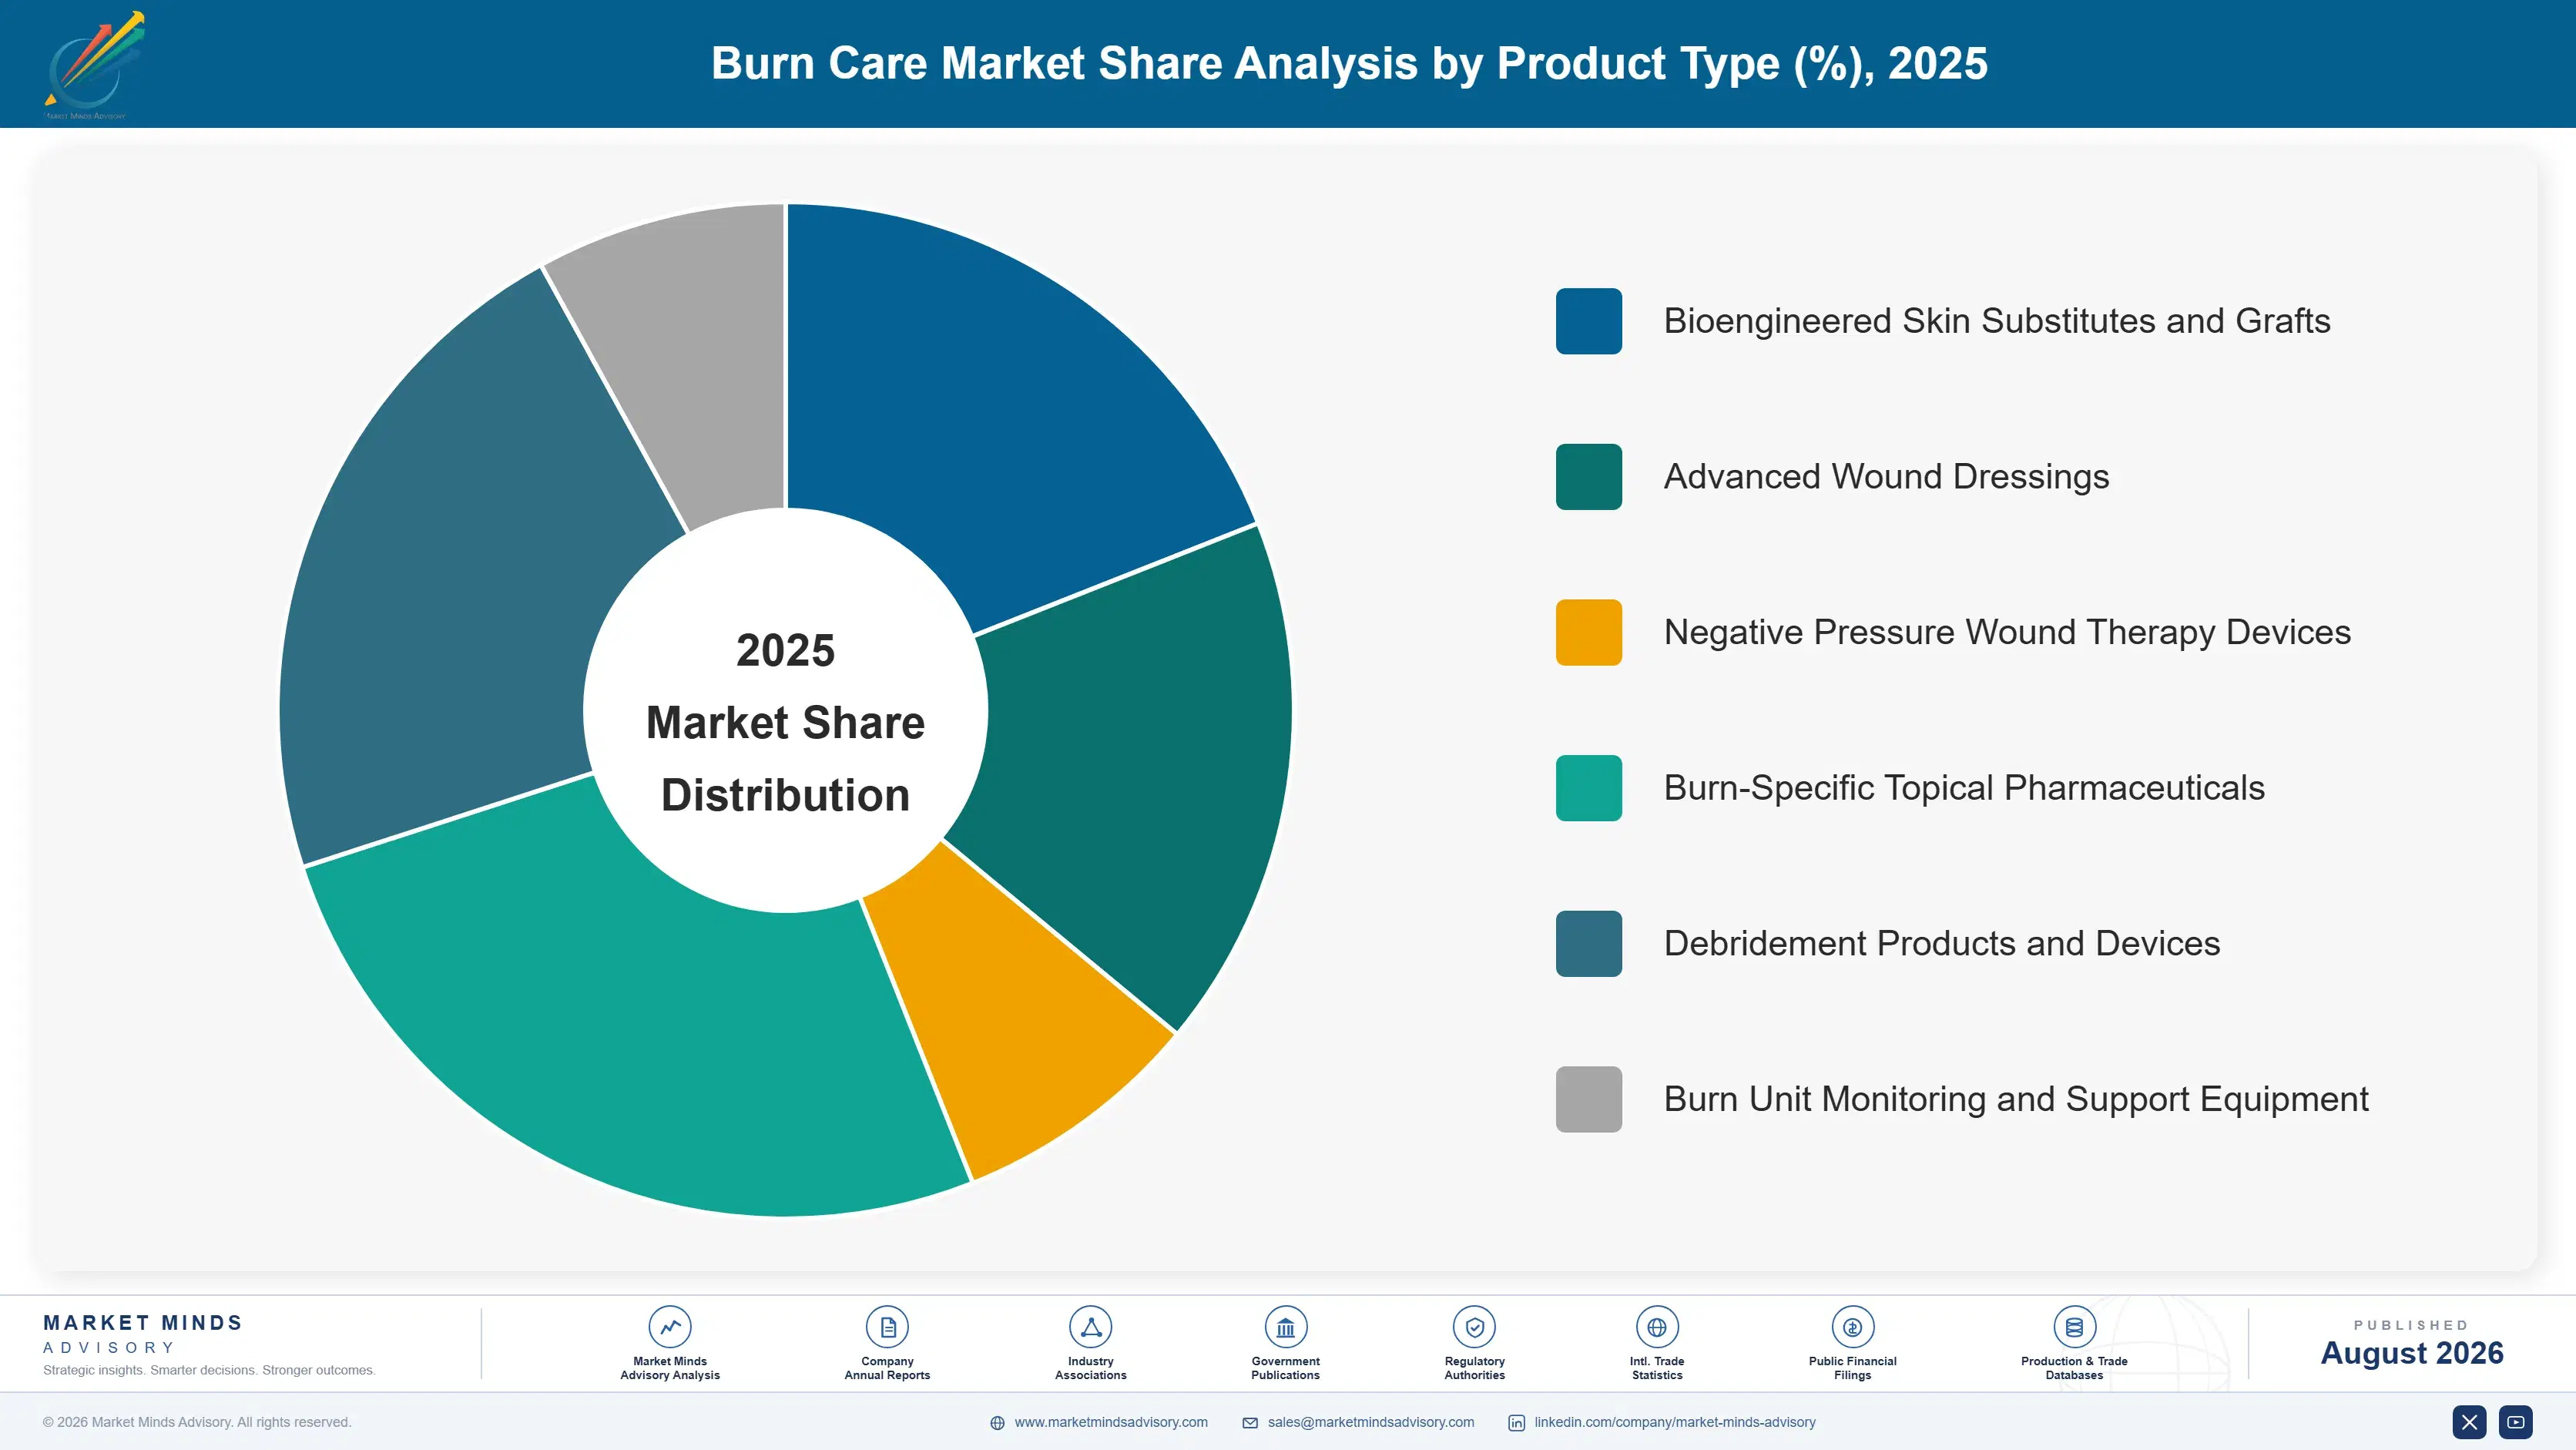
Segmentation follows product type, the single clinical logic that determines treatment mechanism, healing pathway, and manufacturing process. Bioengineered skin substitutes, advanced dressings, negative pressure therapy, topical pharmaceuticals, debridement products, and burn unit equipment each carry genuinely distinct clinical roles evaluated consistently throughout this report. Burn unit monitoring equipment sits within the same evaluated hierarchy consistently throughout.
burn-care-market-market-share-analysis-1787304386543

Bioengineered Skin Substitutes and Grafts

Bioengineered skin substitutes and grafts grow fastest at 13.0%, about 1.63 times the market's 8.0% overall rate, as burn surgeons increasingly specify regenerative products for patients with limited donor site availability rather than relying on autografting alone. Integra LifeSciences and MiMedx still command the largest share of bioengineered substitute prescriptions on established clinical evidence, but Organogenesis and Vericel are expanding competing platforms into overlapping severe-injury treatment categories. Falling manufacturing costs are letting more mid-size burn centres justify their first bioengineered substitute programme without waiting for large academic-centre capital budgets. Adoption concentrates first among patients with large total body surface area burns before spreading into moderate-injury treatment protocols. Payers increasingly reference documented outcome data when approving new coverage expansions.
CAGR 13.0%

Negative Pressure Wound Therapy Devices

Negative pressure wound therapy devices grow second-fastest at 11.0%, driven by burn units seeking measurably faster wound closure and reduced infection risk than passive dressing protocols alone can deliver. Rather than relying on gauze changes and topical antimicrobials alone, negative pressure systems apply controlled suction that accelerates granulation tissue formation and prepares wounds for grafting considerably faster than conventional approaches. 3M and Smith+Nephew have both expanded negative pressure product lines specifically to serve burn units targeting faster closure timelines and reduced hospital stay duration. Adoption is fastest among burn centres managing complex wounds where infection risk and closure speed matter most. Hospital case management teams increasingly reference documented outcome data when selecting suppliers.
CAGR 11.0%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

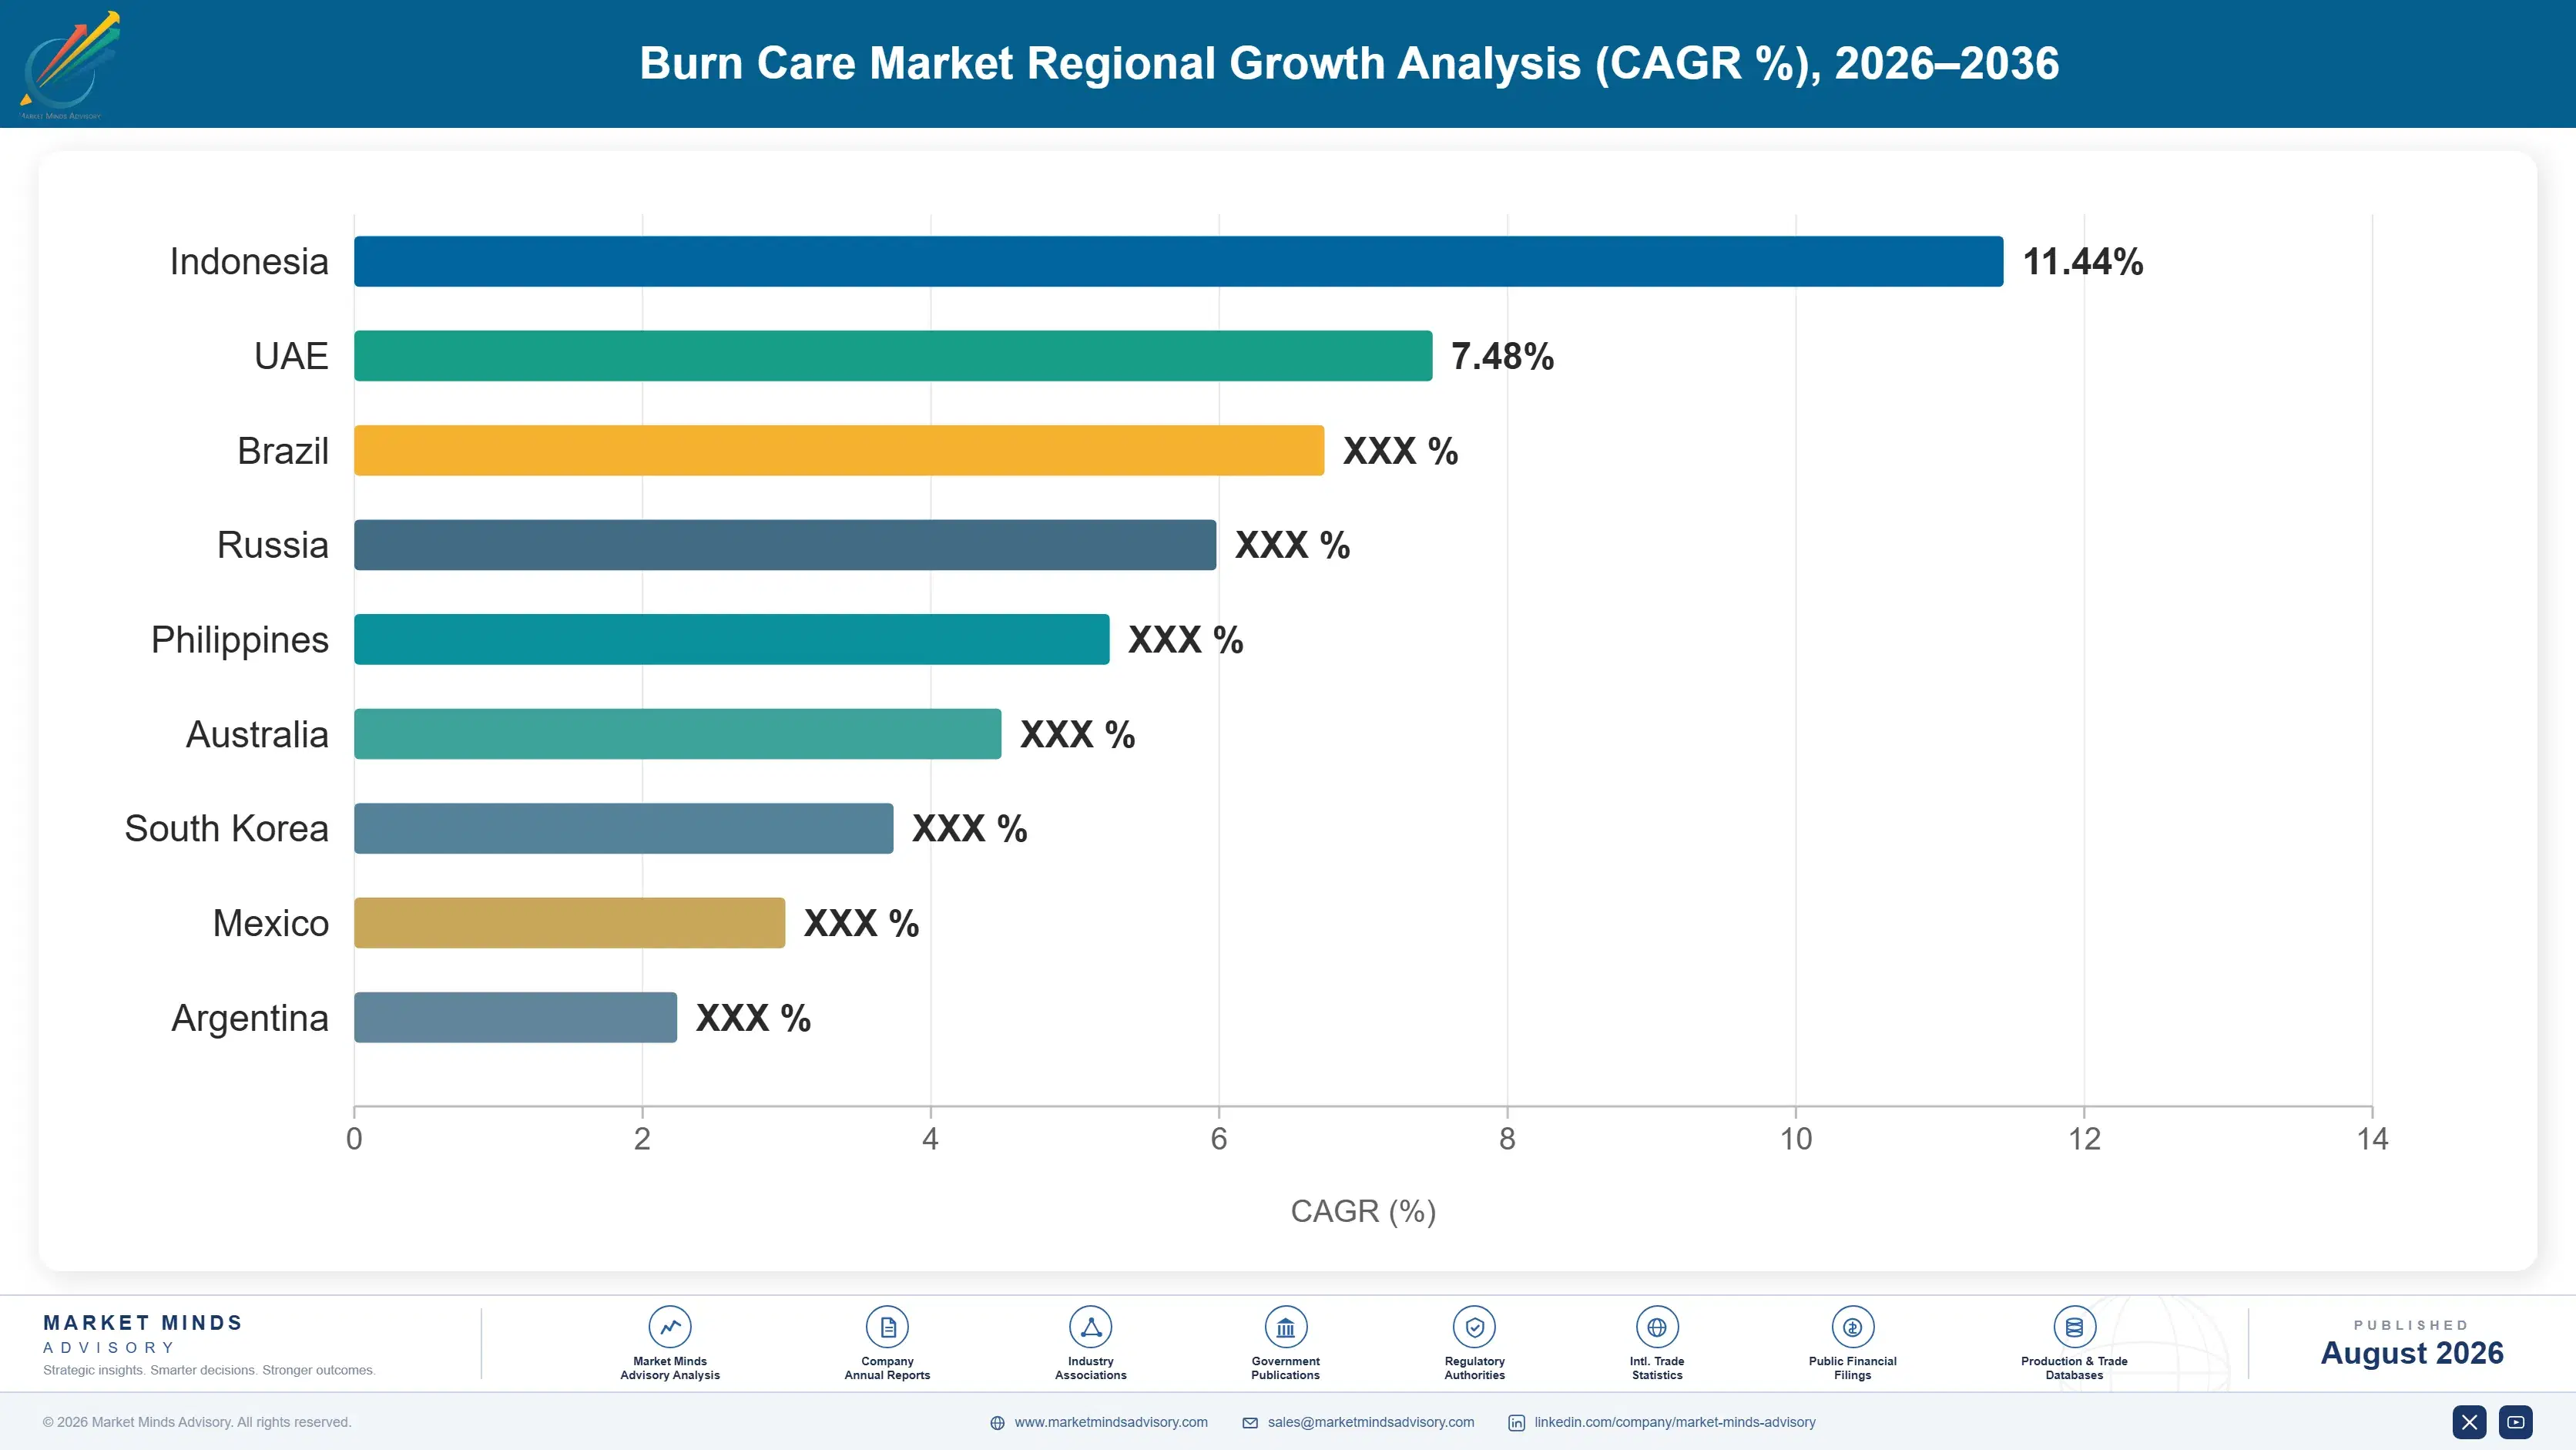
Global demand concentrates where trauma centre infrastructure and reimbursement coverage run deepest. North America leads on established burn centre density and regenerative product reimbursement, East Asia follows on manufacturing scale and rising trauma access, and South Asia and Pacific is closing the gap fastest of any region.

North America

The United States drives regional demand through the country's dense network of verified burn centres and established reimbursement coverage for bioengineered skin substitutes that continues expanding under value-based trauma care payment models. Integra LifeSciences and MiMedx both hold deep incumbency across US burn centre relationships, competing against Organogenesis's growing regenerative product presence. Canada contributes a smaller layer through provincial health system coverage of severe burn cases requiring specialised treatment. Insurance coverage for bioengineered substitutes, now expanding across major US payers, further widens the gap with regions where reimbursement still favours conventional grafting. Growth of 8.5% reflects continued regenerative product adoption and expanding burn centre capacity across the region. That documentation increasingly influences future contract renewal negotiations.
Share: 31% | CAGR: 8.5% (2026 to 2036)

Western Europe

Germany, France, and the United Kingdom anchor demand through established burn centre networks and national health service procurement that continues favouring proven, clinically validated products over unproven newer entrants. Mölnlycke Health Care's domestic manufacturing base gives it genuine home-market advantage across Nordic and broader European burn centre accounts, competing against Smith+Nephew's wider regional presence. Reimbursement for bioengineered substitutes varies considerably by country, with private insurance markets adopting faster than centrally funded national health systems working through longer cost-effectiveness review cycles. Growth of 6.5% trails the global rate as slower national health system procurement caps adoption relative to North America. Reimbursement structures increasingly reward centres with demonstrated outcome evidence and registry participation.
Share: 22% | CAGR: 6.5% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
burn-care-market-country-cagr-analysis-1787304387064

Where Burn Care Makers Can Defend Margin

Burn centre procurement increasingly favours makers who can guarantee both graft take rate and reliable cold-chain delivery. The four levers below capture revenue before a procurement cycle locks its supplier list rather than after, rewarding makers who prove reliability credibly across a centre's full case volume. That reliability increasingly wins the largest national and regional contracts outright.

Bundle Substitutes Into Burn Centre Treatment Protocols

Product specification increasingly happens during burn centre treatment protocol design rather than during later procurement, when treatment pathways and standing order sets are already fixed and costly to change. Makers that place clinical specialists inside protocol design teams from the outset capture the full treatment scope rather than competing for a smaller individual case order later. Integra LifeSciences reports that centres bundling substitutes into initial protocol design carry order values roughly 27% higher than late-stage procurement on comparable case volume. Early involvement also cuts the requalification risk that late-stage substitution otherwise carries.
Market Impact: Lifts order value roughly 27% via p

Sell Outcome Registry And Follow-Up Subscriptions

Burn surgeons increasingly want longitudinal outcome data to support their own clinical decision-making and publication activity, and makers bundling product sales with outcome registry participation are capturing recurring engagement worth 8 to 14% of the original product price annually in follow-up services and data licensing. That recurring layer extends burn centre relationships well past the initial treatment episode and improves loyalty across future procurement cycles considerably. MiMedx has expanded its outcome registry offering specifically to capture this recurring layer. Burn centres increasingly cite that documented outcome data during future procurement renewal decisions.
Market Impact: Adds a durable 8-14% annual recurri

Build Tiered Product Lines For Smaller Burn Centres

Smaller regional burn centres cannot justify the cost of full bioengineered substitute programmes, yet they represent a large, historically underserved segment that larger makers previously found less economical to pursue directly. Makers offering tiered product lines with core substitute capability at a lower price point capture this segment at a fraction of the full-programme cost, cutting the effective entry price by roughly 35% for smaller, budget-constrained centres. Organogenesis has scaled exactly this tiered approach across smaller burn centres since 2024. That tiered approach also builds centre loyalty ahead of larger hospital-grade programme decisions.
Market Impact: Cuts entry price by roughly 35% for

Target National Hospital System Framework Agreements

National and regional hospital systems coordinating burn treatment standards across dozens of affiliated trauma centres increasingly want one certified supplier rather than a different product line at every facility, which shifts the purchasing decision upstream to a small number of national procurement teams. Securing a framework agreement covering a hospital system's full trauma network delivers volume that no number of individual centre orders can match. Smith+Nephew has pursued exactly this framework approach with several national hospital systems since 2023. That framework relationship now spans a meaningful share of Smith+Nephew's national hospital portfolio.
Market Impact: Locks in supply across a full 20+ c

Who Controls the Margin Pool

Concentration sits at CR5 48%, moderate for a category split between diversified wound care majors and specialist regenerative medicine companies. Integra LifeSciences and MiMedx lead on clinical evidence depth and burn centre relationships, while the gap to challengers like Organogenesis is more about graft take rate data than manufacturing scale. All participants are assessed on one consistent basis, burn care product revenue.
Current competitive activity runs across three dimensions. Product development concentrates on tissue engineering to improve graft take rates and reduce scarring. Logistics investment focuses on room-temperature-stable formulations rather than cold-chain-dependent products alone. And account structure centres on national hospital system framework agreements rather than one-off centre orders, a shift that rewards makers with genuine multi-region delivery capability.

Emerging pressure comes from specialist regenerative medicine companies scaling behind faster graft take rate innovation, winning severe-injury cases that diversified wound care majors once assumed were theirs by default. Rankings will shift toward makers who combine bioengineered substitute depth with proven outcome data, since that combination is what large burn centres are now specifying by default. Makers without a credible regenerative roadmap face the sharpest erosion over the coming decade.
burn-care-market-company-positioning-matrix-1787304387588

Competitive Moat and Risk Dimensions

INTEGRA LIFESCIENCES HOLDINGS CORPORATION

Moat: Deep clinical evidence and trust

Integra LifeSciences holds decades of accumulated clinical evidence behind its bioengineered substitute portfolio, giving it a genuine credibility advantage winning large burn centre contracts that newer entrants without comparable evidence history cannot easily replicate quickly. That evidence depth is difficult for newer entrants to replicate quickly at scale.
INTEGRA LIFESCIENCES HOLDINGS CORPORATION

Risk: Exposed to cold-chain logistics limits

Integra LifeSciences's core substitute products require cold-chain handling that limits reach into rural and smaller burn centres, leaving room for makers offering room-temperature-stable formulations to capture facilities its logistics model cannot economically serve. That exposure grows as room-temperature-stable competitors capture facilities its cold-chain model cannot serve.
MIMEDX GROUP INC.

Moat: Deep tissue engineering expertise

MiMedx draws on decades of accumulated placental tissue processing and regenerative medicine expertise, giving it a genuine advantage in substitute formulation quality that competitors without comparable core tissue engineering depth cannot easily replicate quickly. That processing depth is difficult for newer entrants to replicate quickly at comparable scale.
MIMEDX GROUP INC.

Risk: Narrower portfolio limits diversification

MiMedx's concentration in regenerative tissue products leaves it more exposed than diversified competitors to reimbursement policy shifts specifically targeting bioengineered substitute pricing, since it lacks a broad conventional dressing portfolio to offset that exposure. That exposure grows whenever payers reconsider bioengineered product pricing tiers broadly.

Players Tracked

Prominent Players

Integra LifeSciences Holdings Corporation
MiMedx Group Inc.
Organogenesis Holdings Inc.
Smith+Nephew plc
Mölnlycke Health Care AB

Other Key Players

3M Company
ConvaTec Group plc
Coloplast A/S
Baxter International Inc.
Vericel Corporation
PolyNovo Limited
Avita Medical Inc.
Kerecis ehf
Tissue Regenix Group plc
Urgo Medical
Medline Industries LP
Hollister Incorporated
Cardinal Health Inc.
B. Braun Melsungen AG
Essity AB

Recent Developments

MARCH 2025

Integra LifeSciences launches room-temperature-stable skin substitute

Integra LifeSciences introduced a new bioengineered skin substitute formulation that eliminates cold-chain storage requirements for rural and smaller burn centres. This was an organic product launch rather than an acquisition, extending Integra's addressable facility coverage. The reformulated product ships to distributor accounts across major markets starting this quarter.
Signal: Room-temperature stability is becoming a g
SEPTEMBER 2025

MiMedx acquires specialty outcome registry technology company

MiMedx completed the acquisition of a specialty burn outcome registry technology company with proprietary longitudinal tracking software. The deal brought advanced registry capability in-house, expanding MiMedx's data offering considerably beyond its prior product-only line. The acquired team now operates within MiMedx's dedicated outcome registry division.
Signal: Outcome registry technology is becoming a
JULY 2025

Smith+Nephew signs framework agreement with national hospital system

Smith+Nephew entered a multi-year framework agreement to supply negative pressure and advanced dressing products across a national hospital system's burn centre network. The agreement was a commercial supply contract, not a joint venture or equity transaction, covering the system's facility base. Similar agreements are now under discussion elsewhere.
Signal: Multi-year, multi-facility framework agree

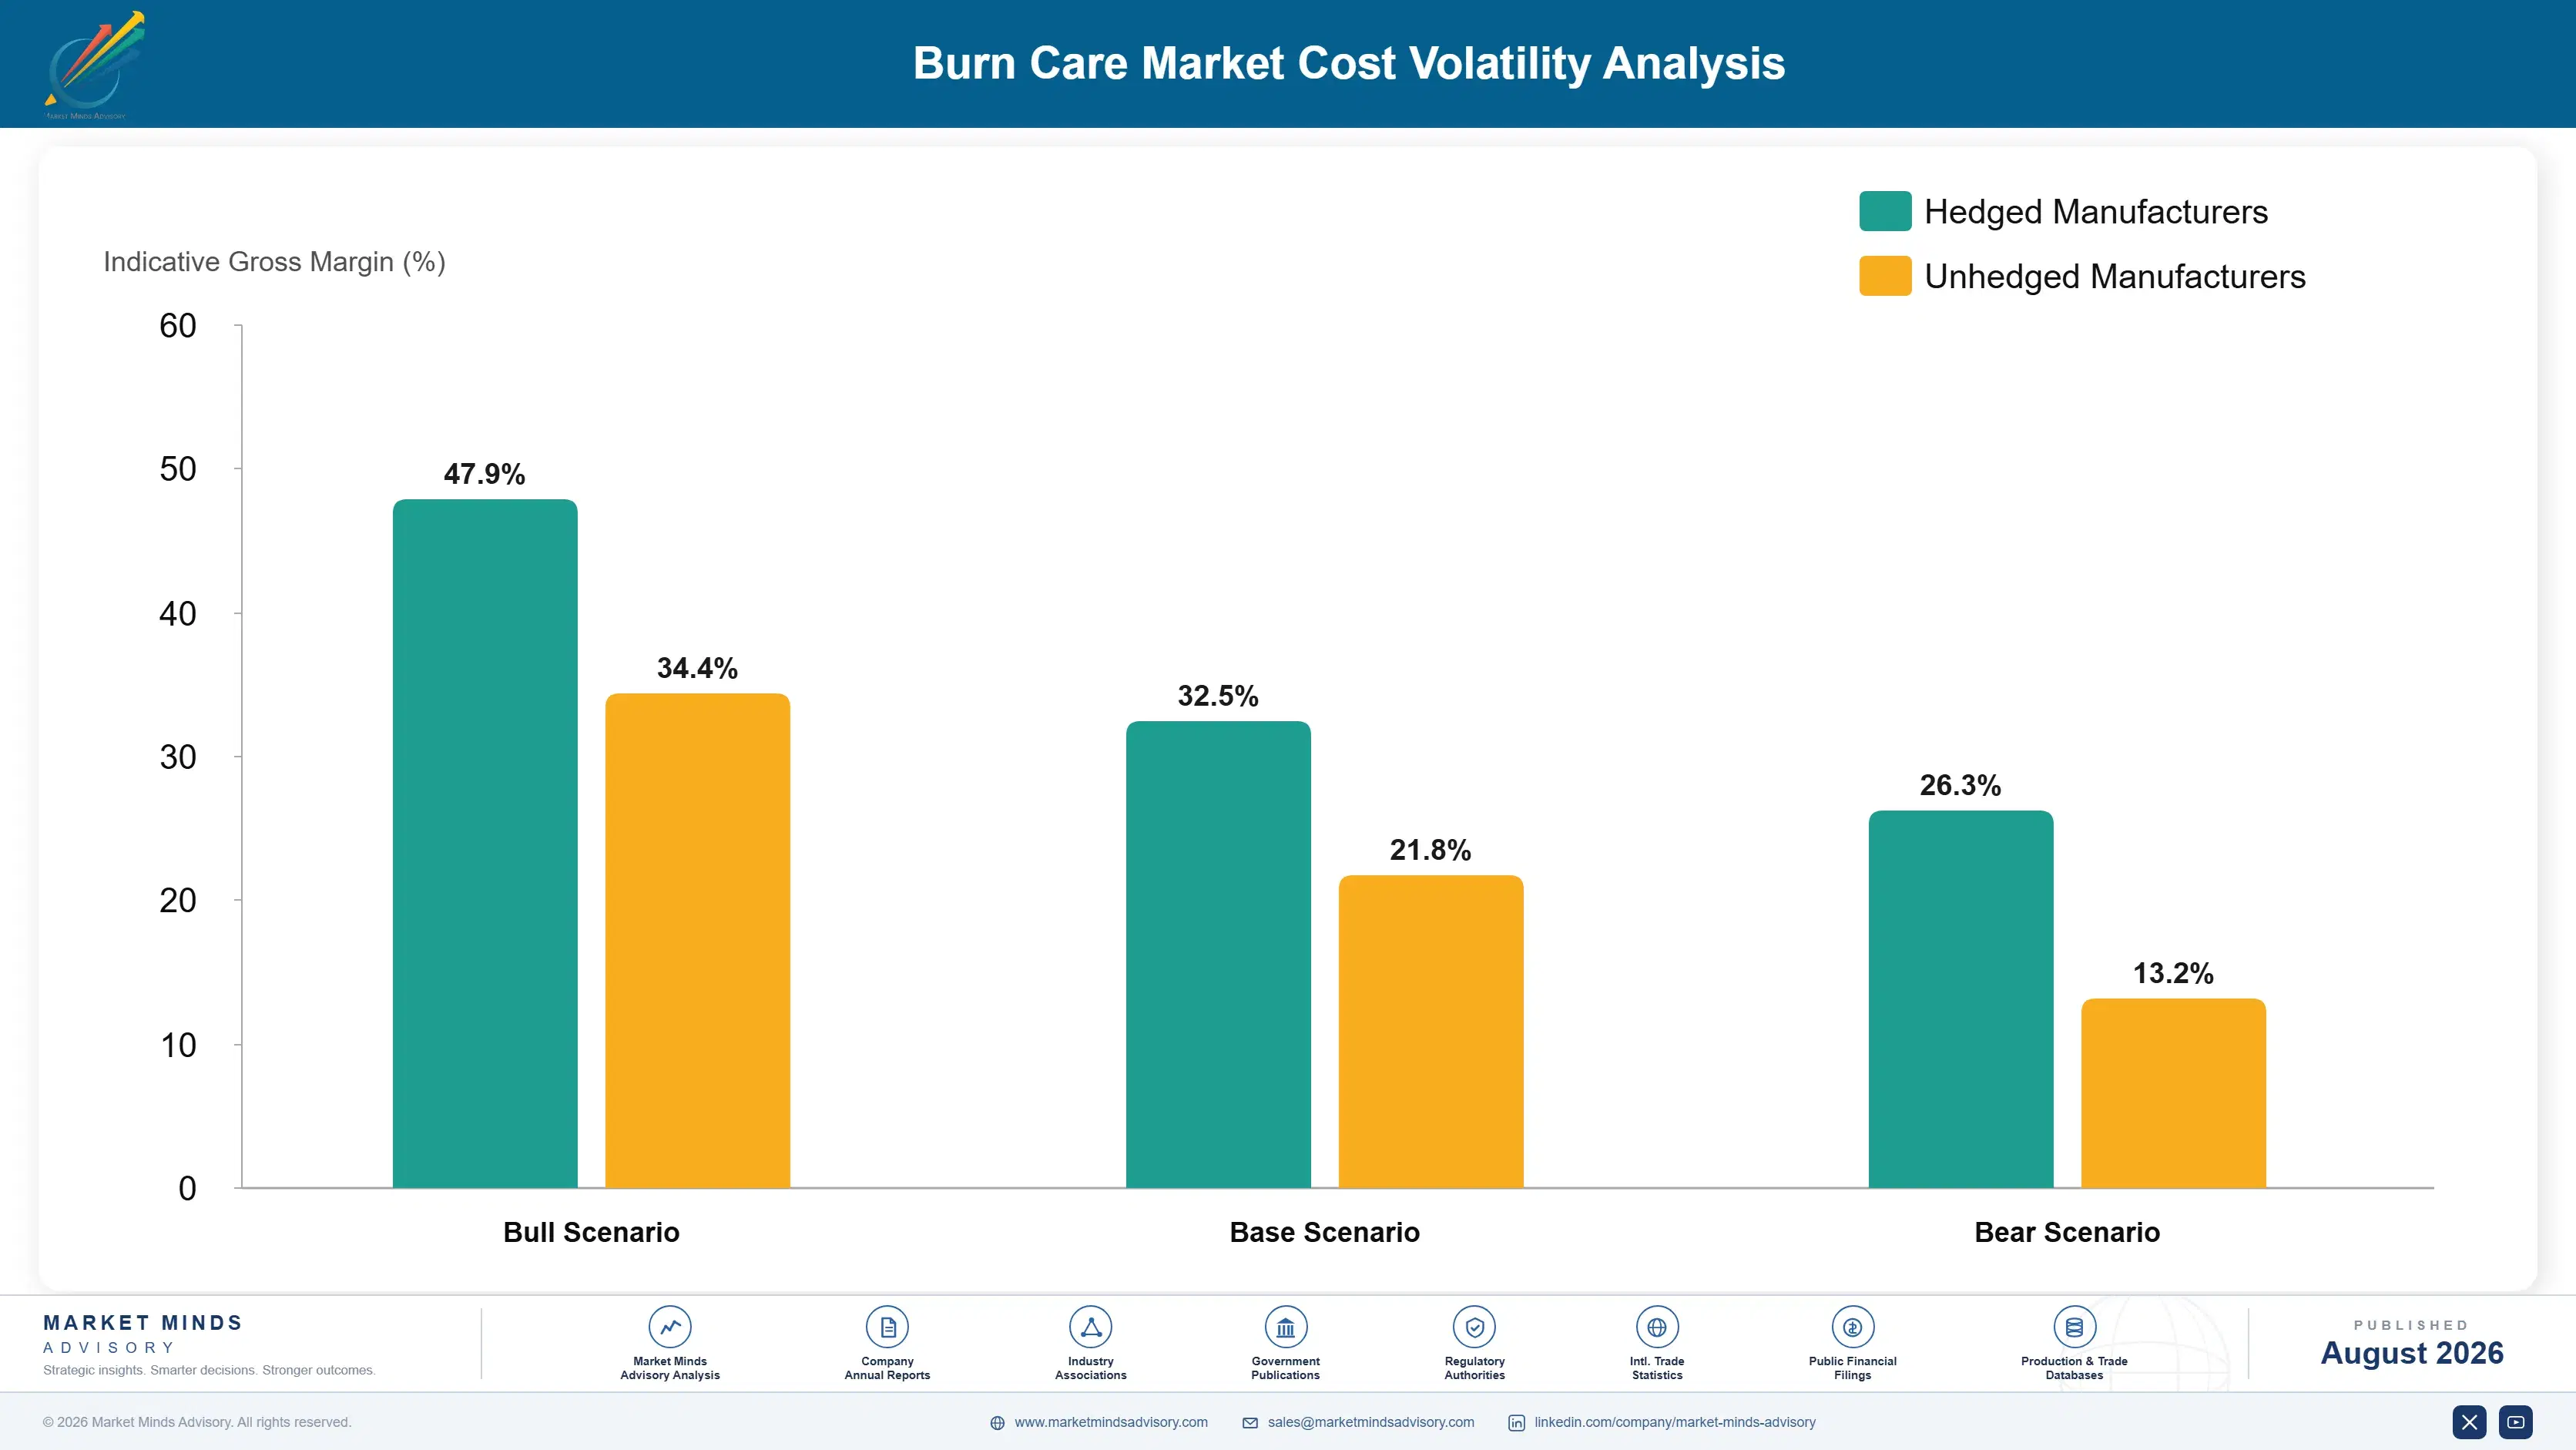
Biologic Tissue Processing And Cell Culture Exposure

Biologic tissue processing and cell culture production, including placental tissue and dermal scaffold sourcing, runs 26 to 34% of COGS, sourced from a concentrated set of specialised regenerative medicine manufacturers that also supply the wider tissue engineering industry. Cold-chain distribution and packaging add a further 14 to 20%, with quality testing and sterilisation accounting for most of the remainder.
The global cold-chain logistics disruption running through 2021 and 2022 hit bioengineered substitute distribution directly, since living cell-based products depend on specialised temperature-controlled shipping capacity that faced significant strain during broader pandemic-era supply chain congestion. MiMedx's 2022 Annual Report disclosed elevated distribution costs and extended delivery times, attributing part of the pressure to cold-chain capacity constraints that persisted through much of the year overall. overall.

Exposure varies sharply by player type. Vertically integrated majors like MiMedx manufacture much of their own tissue processing capability in-house, insulating them from the worst allocation constraints, while smaller specialists depend on third-party processing facilities and absorb price spikes directly into thinner margins. Geography matters too, since makers with domestic processing face different exposure than those depending on imported biologic materials.
burn-care-market-cost-volatility-analysis-1787304387783

Develop Room-Temperature-Stable Product Formulations

Reformulating substitutes to eliminate cold-chain dependency reduces logistics cost and expands addressable facility coverage considerably beyond what temperature-controlled products can reach. Several makers adopted room-temperature formulation development as a strategic priority after the 2021 disruption exposed how vulnerable cold-chain-dependent distribution genuinely was. That approach held even as broader logistics markets stabilised across the industry.

Vertically Integrate Tissue Processing Where Feasible

Manufacturing tissue processing capability in-house rather than sourcing it externally insulates the largest makers from allocation shortages during industry-wide supply disruptions. Smaller specialists lacking that scale have instead pursued long-term supply agreements with established processing facilities to secure priority allocation, reducing spot-market exposure considerably. That investment continued even as broader supply markets stabilised somewhat.

Diversify Cold-Chain Distribution Across Multiple Carriers

Qualifying distribution through multiple specialised cold-chain logistics providers, rather than a single carrier, keeps a disruption at any one provider from halting delivery to burn centres entirely. Makers coordinating multi-carrier distribution have meaningfully reduced delivery disruption risk during regional logistics constraints and severe weather events. That improvement has continued across most product lines facing pressure.

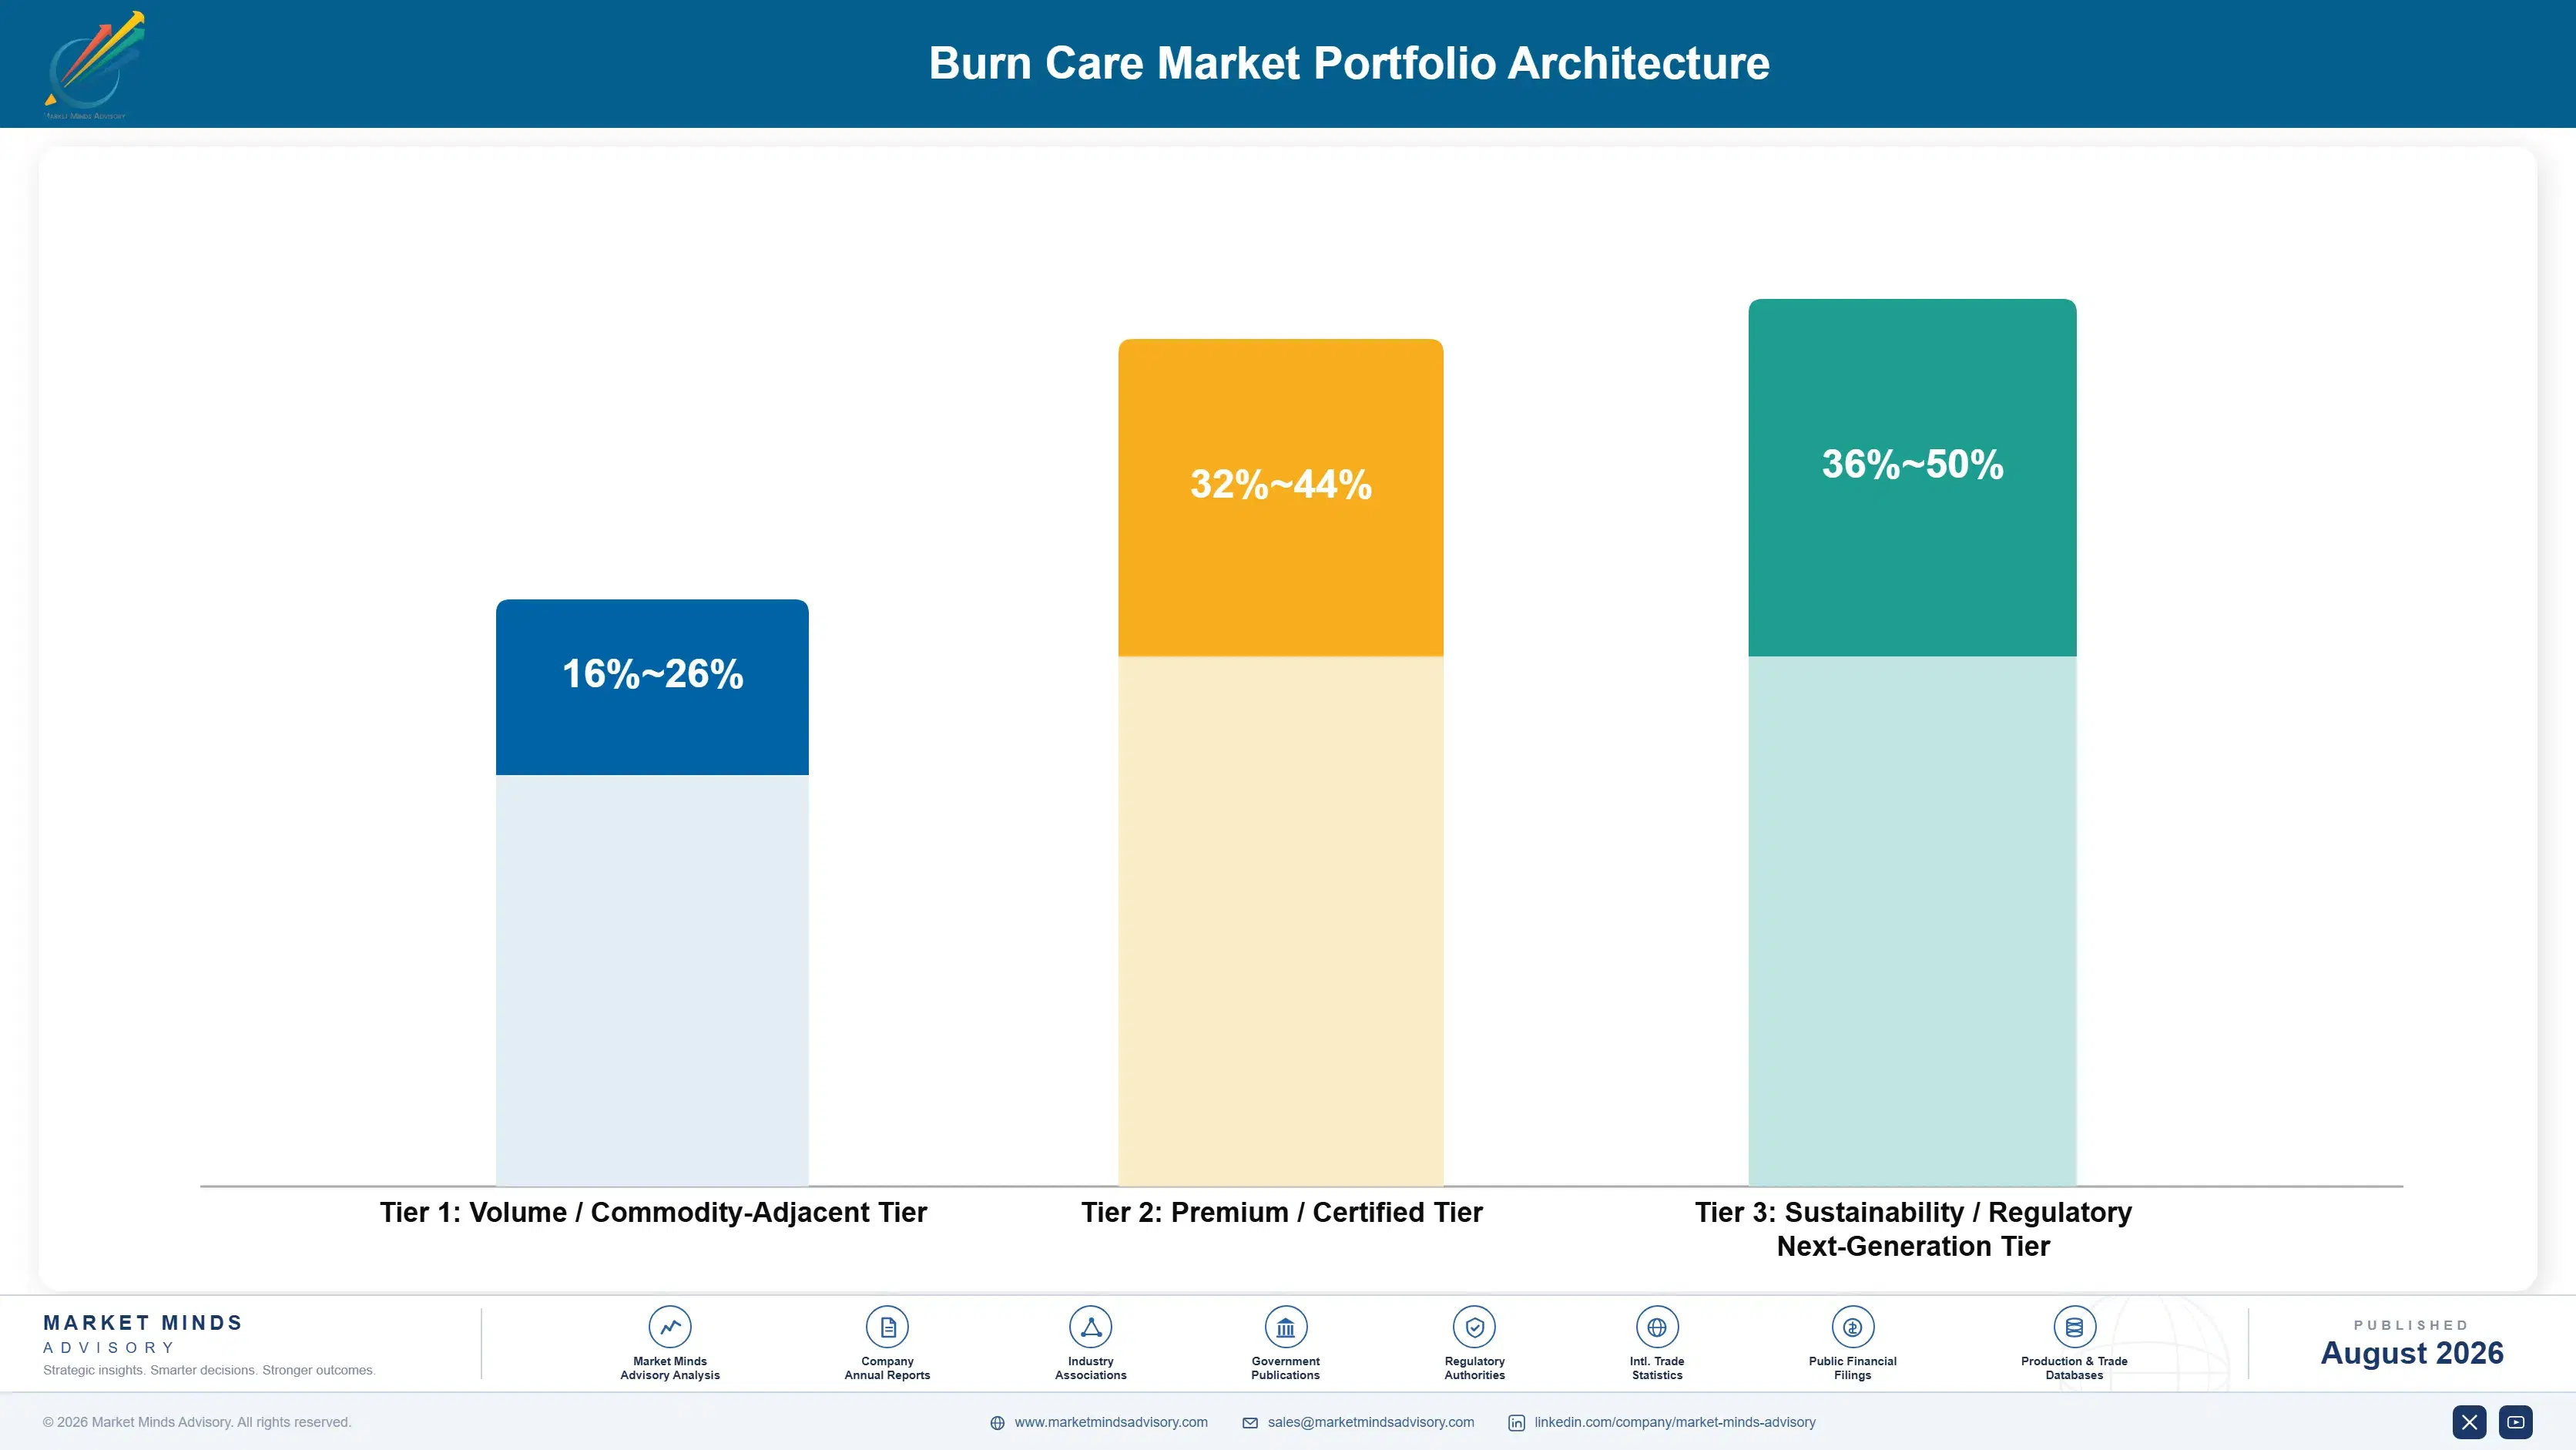
Portfolio Architecture for Margin Defence

The portfolio splits into three tiers with real margin separation, and the gap between tiers has widened as bioengineered substitute depth becomes a genuine differentiator rather than an add-on feature. Volume-tier standard dressings compete on price against generic alternatives and earn modestly. Premium bioengineered and framework-contracted products earn considerably more because they solve a genuine donor site limitation problem that burn centres cannot engineer around cheaply.
The tension is between standard dressing volume and per-case bioengineered margin. Makers selling standard dressings in bulk push hard on unit price, while national hospital systems standardising on bioengineered framework agreements pay for graft take rate and outcome evidence rather than negotiating down to the last dollar on every unit. Makers serving both buyer types run genuinely different sales motions under one brand.

High-value pools concentrate in bioengineered substitutes sold with outcome registry programmes and national framework agreements, where switching cost is highest and price sensitivity lowest. Legacy standard dressing business remains large in volume but persistently thin in margin, as burn centres treat it as a commodity purchase rather than a differentiated one. Makers investing in both regenerative capability and framework relationships are best positioned to capture that concentration going forward.

Volume / Commodity-Adjacent Tier

Standard advanced wound dressings sold into routine burn treatment protocols, priced against generic alternatives. Margin stays thin because buyers negotiate primarily on unit price rather than outcome data. Buyers rarely differentiate between makers on anything beyond delivery speed and price.
Gross Margin: 16-26%

Premium / Certified Tier

Bioengineered substitutes and framework-contracted products sold into hospital systems standardising national treatment specifications. Buyers pay for graft take rate and outcome evidence rather than for product alone. Delivery timelines and outcome evidence matter as much as the product specification itself.
Gross Margin: 32-44%

Sustainability / Regulatory / Next-Generation Tier

Room-temperature-stable regenerative systems bundled with outcome registry subscriptions sold to national hospital systems and large burn centres. Margin reflects both technology differentiation and recurring revenue. Few makers currently combine both elements convincingly at meaningful commercial scale.
Gross Margin: 36-50%
burn-care-market-portfolio-architecture-1787304388276

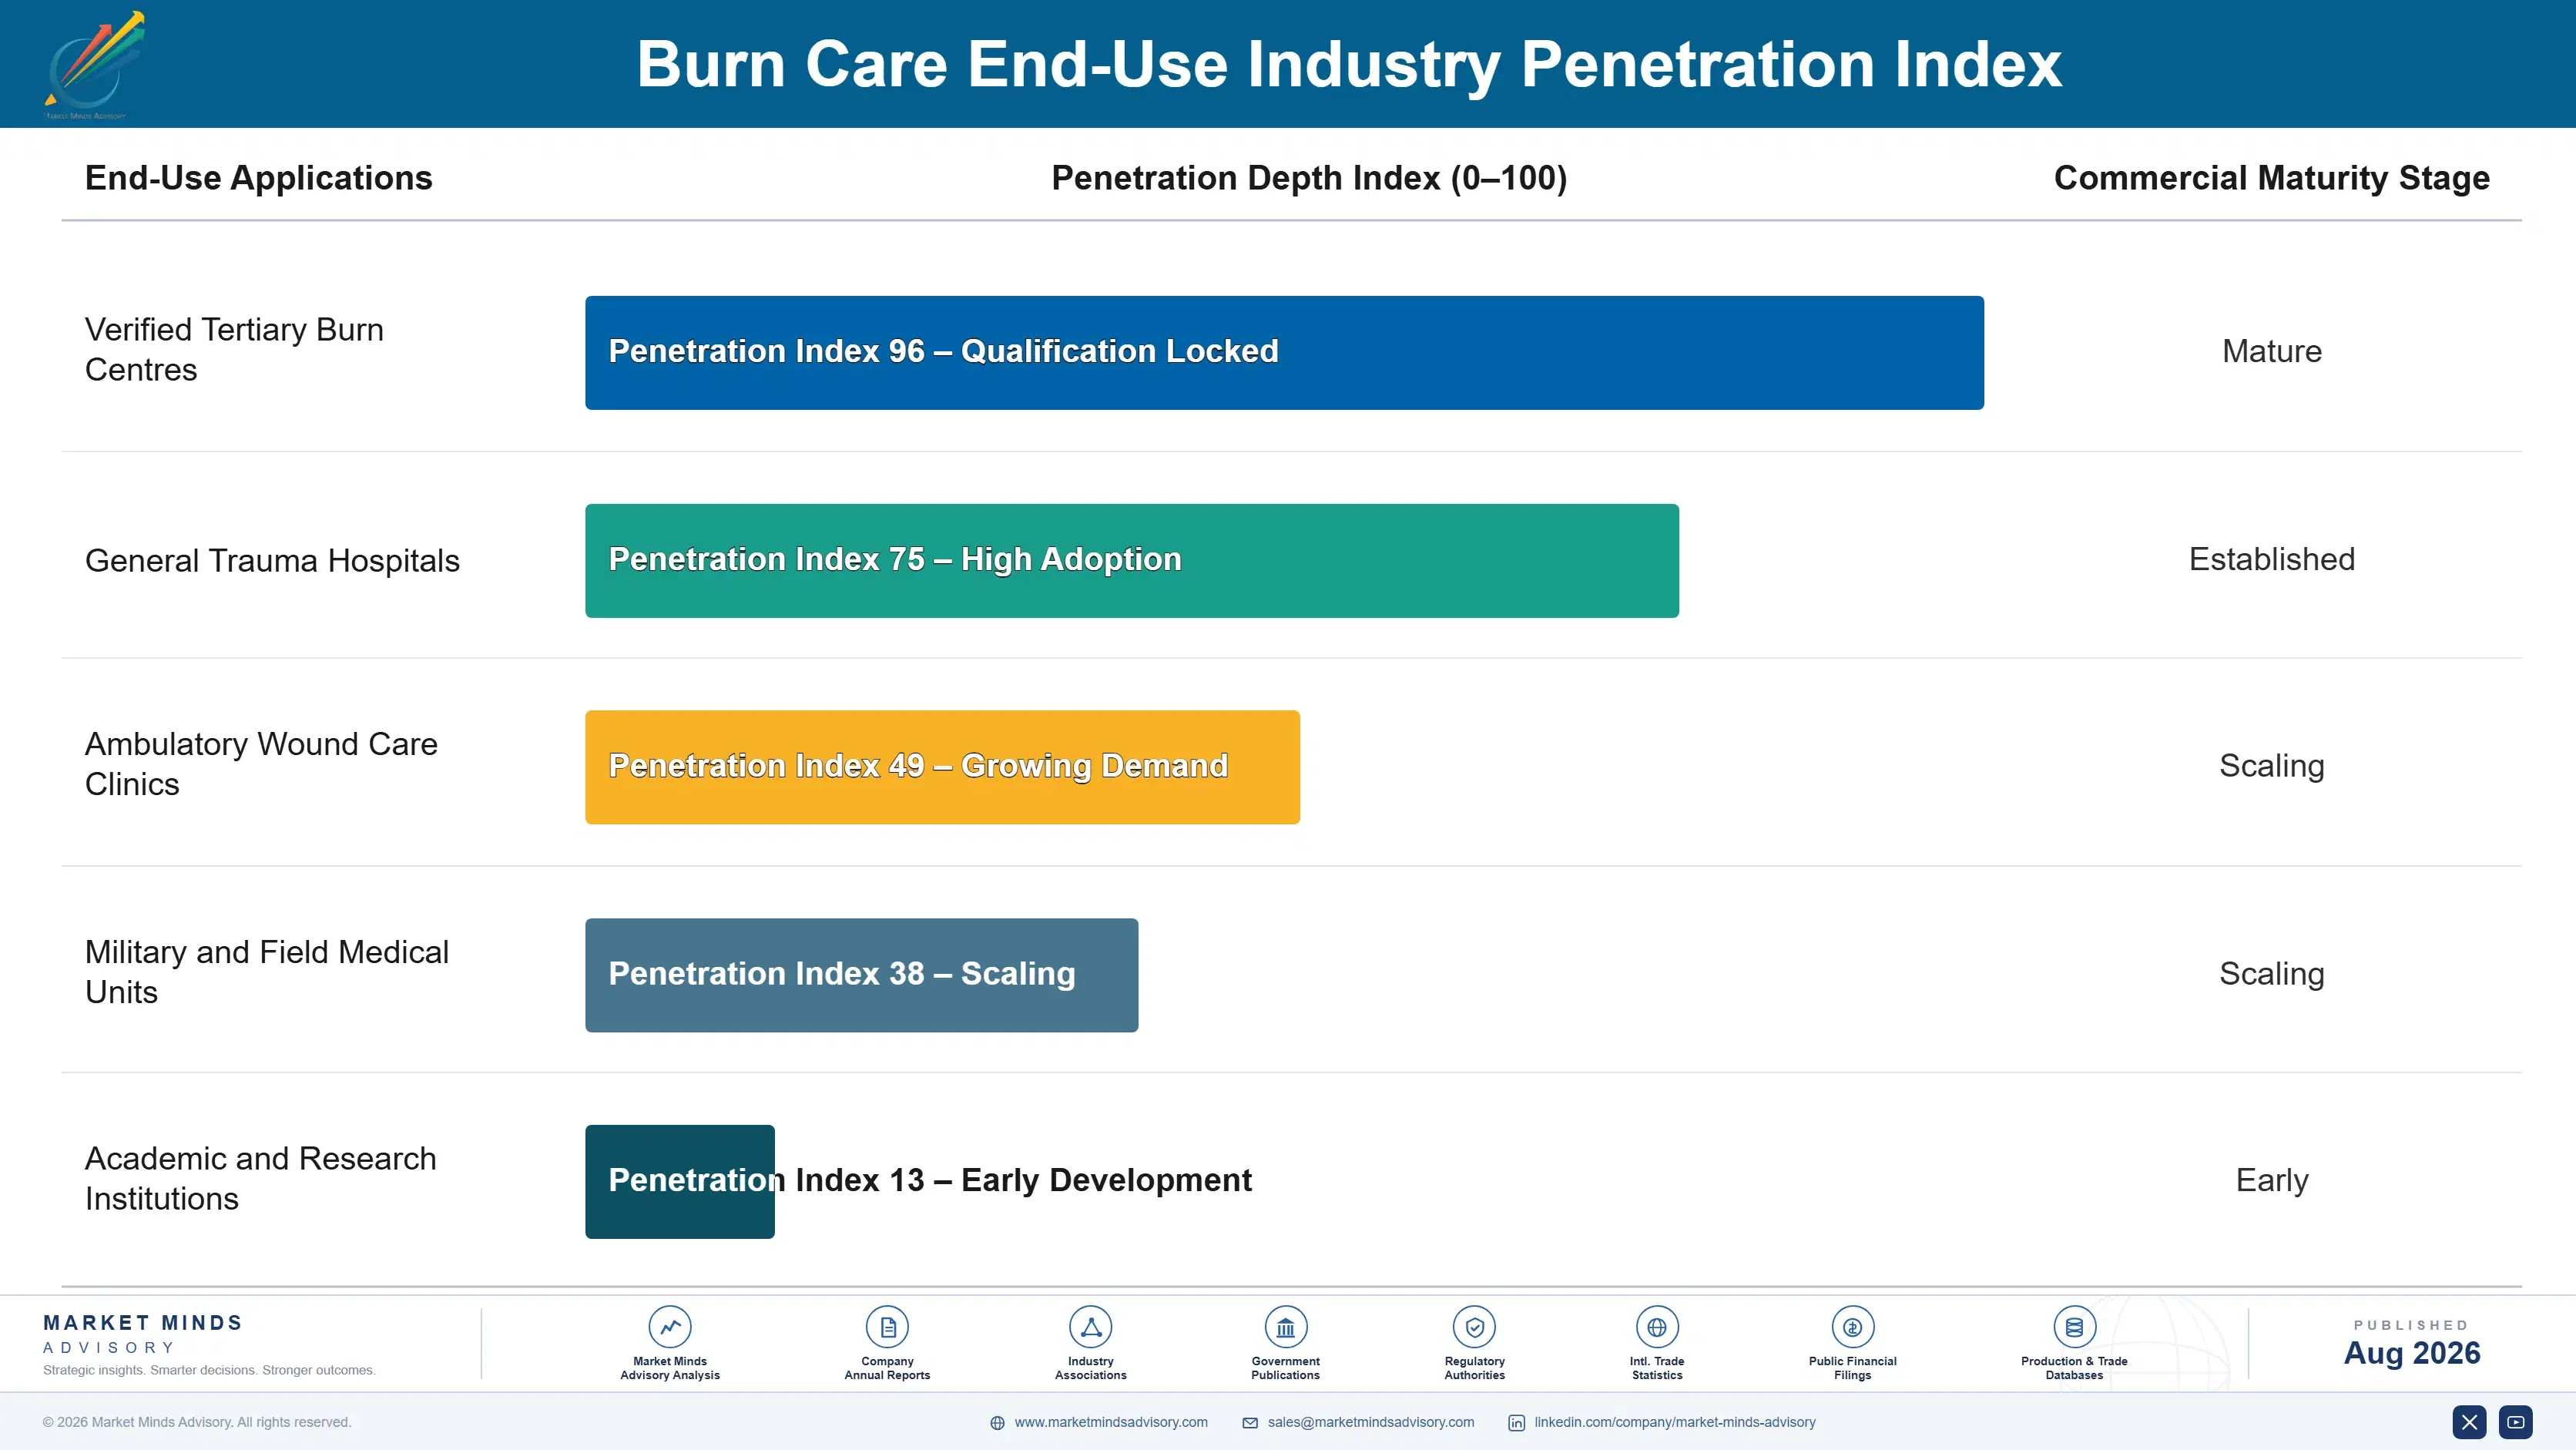
Episodic Demand Anchored To Trauma Volume

Demand behaves differently from chronic therapy markets, since each treatment episode addresses a single acute injury rather than recurring ongoing use, but burn centres standardising on a certified platform generate predictable procurement volume tied directly to their trauma caseload. That caseload predictability, plus the underlying capacity expansion demand it eventually triggers, gives makers a reliable revenue base tied to trauma centre designation rather than individual patient renewal cy
Adoption depth varies sharply by end-use vertical. Verified tertiary burn centres adopt bioengineered substitutes fastest and deepest, since severe case concentration directly justifies the premium cost. General trauma hospitals follow closely on advanced dressing adoption for moderate injuries. Smaller community hospitals adopt more slowly, often waiting for a case volume threshold or referral pattern shift to force the product decision.

Buyer profiles are shifting generationally. Procurement once sat with individual surgeons evaluating single product lines; it now increasingly involves hospital system standards committees who specify treatment protocols before a single burn centre selects its supplier. That shift moves the real purchasing decision earlier into the planning cycle. Makers who engage standards committees early win preferred status ahead of individual decisions.
burn-care-market-end-use-penetration-index-1787304388763

Where Burn Care Value Concentrates

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / BIOENGINEERED SUBSTITUTE STRATEGY

Graft Take Rate Now Decides Long-Run Category Position

Bioengineered skin substitutes are growing at 13.0%, about 1.63 times the market's 8.0% overall rate, and that gap is widening as surgeons increasingly specify regenerative products for donor-site-limited patients over conventional autografting alone. Makers still anchored on standard dressings alone risk losing the fastest-growing, highest-margin national framework contracts to rivals offering proven bioengineered capability already deployed at scale. The window to build credible bioengineered capability is closing within this forecast period, and makers who act now capture the largest contracts before rivals catch up.
02 / OUTCOME REGISTRY STRATEGY

Documented Take Rate Data Is Becoming Table Stakes

National hospital systems increasingly refuse to specify substitutes without documented outcome registry participation, since a novel product lacking long-term take rate data represents a genuine liability risk during a real severe-case treatment decision. Makers who build this registry capability capture recurring engagement and preferred-vendor status that product-only competitors cannot easily replicate at comparable scale. Those without a credible outcome platform will find themselves excluded from the largest national framework agreements, losing status to better-equipped rivals with structured registry platforms already deployed at scale.
03 / NATIONAL FRAMEWORK CHANNEL

Multi-Facility Frameworks Will Outgrow Single-Centre Sales

National hospital systems are increasingly folding burn product specification into corporate standards rather than leaving it to individual surgeons, concentrating real purchasing power in a small number of framework decisions that smaller makers cannot easily access at scale. Makers who secure framework status with major hospital systems capture volume across an entire trauma network that no number of individual centre orders can replicate. Those still selling purely centre by centre risk being locked out of this fastest-growing channel entirely today.
04 / COLD-CHAIN LOGISTICS PRESSURE

Room-Temperature Formulations Will Keep Reshaping Distribution

Makers developing room-temperature-stable formulations have scaled fast enough to reach rural and smaller burn centres that cold-chain-dependent competitors once assumed were unreachable by default, and that reach advantage is starting to spread into standard urban centre procurement as well. Makers competing purely on clinical evidence against logistics reach will struggle to hold share over any meaningful time horizon. The more durable response is investing in both formulation stability and evidence depth, categories where legacy incumbents still visibly lag behind newer entrants.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Burn Care Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Burn Care Exposure Evaluation 2025-26
CLIENT PROFILE
A regional trauma hospital system operating three verified burn centres approached MMA after growing severe burn case referrals began exceeding its conventional grafting capacity. The client reported that donor site limitations in complex cases were driving referrals to competing academic centres offering bioengineered substitute treatment (client-reported, unverified by MMA). Leadership viewed this as both a growth constraint and a competitive risk.
STRATEGIC CHALLENGE
The system had relied primarily on conventional autografting across its three centres for over a decade without a bioengineered substitute programme, assuming existing capacity remained adequate. Rising referral loss forced leadership to confront how far behind current regenerative treatment capability its centres had fallen, with a limited capital budget available.
MMA APPROACH
MMA benchmarked the system's referral loss and case outcomes against comparable trauma systems already operating bioengineered substitute programmes, quantifying the competitive improvement a programme would deliver. We evaluated tiered product options specifically sized to each centre's case mix, and modelled a phased rollout schedule against the system's existing capital planning cycle.
KEY FINDINGS
  1. The system's conventional-only approach showed considerably higher referral loss for severe cases than comparable systems already operating bioengineered programmes, based on benchmarking performed during the review.
  2. A tiered bioengineered rollout concentrated at the system's highest-acuity centre addressed most of the referral loss without requiring investment across all three centres immediately.
  3. Two of three suppliers evaluated could deliver tiered programmes within the system's compressed budget cycle; the third offered only its full-featured line at a considerably higher price point.
  4. Phasing the rollout across three budget cycles rather than requesting full funding at once considerably improved the proposal's approval odds with system leadership (client-reported, unverified by MMA).
CLIENT PROFILE
A regional trauma hospital system operating three verified burn centres approached MMA after growing severe burn case referrals began exceeding its conventional grafting capacity. The client reported that donor site limitations in complex cases were driving referrals to competing academic centres offering bioengineered substitute treatment (client-reported, unverified by MMA). Leadership viewed this as both a growth constraint and a competitive risk.
STRATEGIC CHALLENGE
The system had relied primarily on conventional autografting across its three centres for over a decade without a bioengineered substitute programme, assuming existing capacity remained adequate. Rising referral loss forced leadership to confront how far behind current regenerative treatment capability its centres had fallen, with a limited capital budget available.
MMA APPROACH
MMA benchmarked the system's referral loss and case outcomes against comparable trauma systems already operating bioengineered substitute programmes, quantifying the competitive improvement a programme would deliver. We evaluated tiered product options specifically sized to each centre's case mix, and modelled a phased rollout schedule against the system's existing capital planning cycle.
KEY FINDINGS
  1. The system's conventional-only approach showed considerably higher referral loss for severe cases than comparable systems already operating bioengineered programmes, based on benchmarking performed during the review.
  2. A tiered bioengineered rollout concentrated at the system's highest-acuity centre addressed most of the referral loss without requiring investment across all three centres immediately.
  3. Two of three suppliers evaluated could deliver tiered programmes within the system's compressed budget cycle; the third offered only its full-featured line at a considerably higher price point.
  4. Phasing the rollout across three budget cycles rather than requesting full funding at once considerably improved the proposal's approval odds with system leadership (client-reported, unverified by MMA).
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 6 months): Deploy the bioengineered substitute programme at the system's highest-acuity centre first, prioritising the most severe case referrals. Phase 2: Phase 2 (6 to 18 months): Extend the programme to remaining centres across the system's remaining budget cycle, validating referral retention at each site. Phase 3: Phase 3 (18 to 36 months): Fold the bioengineered programme into the system's standing trauma care standard going forward, reviewing outcomes annually.
OUTCOME
The system deployed the bioengineered substitute programme at its highest-acuity centre within the original budget cycle and reported measurably reduced referral loss during subsequent quarters. The phased rollout approach has since extended to its two remaining centres facing comparable competitive pressure (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Burn Care Market?

The market was valued at USD 3.0 billion in 2025, with demand concentrated in bioengineered skin substitutes and advanced wound dressings across major global trauma care markets.

How large will the Burn Care Market be by 2036?

The market is projected to reach USD 7.00 billion by 2036, an expansion multiple of 2.16 times its 2026 value. Bioengineered substitute adoption drives much of that growth.

What is the CAGR for the Burn Care Market 2026 to 2036?

The base case CAGR is 8.0%, with a bull case of 9.2% and a bear case of 6.8%. The range reflects uncertainty around bioengineered substitute reimbursement policy.

Which segment is growing fastest?

Bioengineered skin substitutes grow fastest at 13.0%, about 1.63 times the overall market rate, as surgeons increasingly specify regenerative products for donor-site-limited severe burn patients.

Who are the major companies in the Burn Care Market?

Integra LifeSciences, MiMedx, Organogenesis, Smith+Nephew, and Mölnlycke Health Care lead the market at CR5 48%, reflecting genuine clinical evidence and centre relationship depth built over decades.

Which country is growing fastest?

India grows fastest at 12.0%, driven by high burn injury incidence and rapidly expanding specialised burn centre infrastructure. The United States remains the largest market by spending.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Product Type

  • Bioengineered Skin Substitutes and Grafts
  • Advanced Wound Dressings
  • Negative Pressure Wound Therapy Devices
  • Burn-Specific Topical Pharmaceuticals
  • Debridement Products and Devices
  • Burn Unit Monitoring and Support Equipment

By End-Use Industry

  • Verified Tertiary Burn Centres
  • General Trauma Hospitals
  • Ambulatory Wound Care Clinics
  • Military and Field Medical Units
  • Academic and Research Institutions

By Commercial Dimension

  • National Hospital System Framework Agreements
  • Standard Unit and Distributor Sales
  • Outcome Registry Participation Programmes
  • Direct Burn Centre Procurement Channel

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The burn care market comprises products and clinical support technologies used in the treatment and management of thermal, chemical, and electrical burn injuries, spanning bioengineered skin substitutes and grafts, advanced wound dressings, negative pressure wound therapy devices, burn-specific topical pharmaceuticals, debridement products, and burn unit monitoring and support equipment. General trauma and surgical equipment not burn-specific and cosmetic scar revision procedures unrelated to acute burn treatment are excluded.
Quantitative Units
USD billions (current prices); treatment units and case episodes where applicable
Segmentation Dimensions
By Product Type; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Thailand, Malaysia, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Integra LifeSciences Holdings Corporation, MiMedx Group Inc., Organogenesis Holdings Inc., Smith+Nephew plc, Mölnlycke Health Care AB, 3M Company, ConvaTec Group plc, Coloplast A/S, Baxter International Inc., Vericel Corporation, PolyNovo Limited, Avita Medical Inc., Kerecis ehf, Tissue Regenix Group plc, Urgo Medical, Medline Industries LP, Hollister Incorporated, Cardinal Health Inc., B. Braun Melsungen AG, Essity AB
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-MED-112
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Burn Care Market Report (2026 to 2036).

The full MMA Burn Care report sizes the market across six product types, five end-use verticals, four commercial dimensions, and seven regions through 2036. It profiles twenty participants on a consistent product revenue basis, scoring each on tissue engineering depth, logistics reliability, and burn centre relationship reach. Scenario models quantify how outcome evidence, reimbursement policy, and trauma centre infrastructure expansion move both demand and realised pricing. The report also includes delivered-cost modelling by product type and a national framework benchmarking tool built for hospital procurement and trauma strategy teams.
Product type cost and outcome benchmarking
Trauma case volume and adoption tracker by region
National framework agreement structure and pricing tracker
Reimbursement policy comparison and coding tracker
Biologic tissue supply chain risk screen
Outcome registry revenue and retention forecasting model

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts