Market Minds Advisory
Bronchiectasis Therapeutic Market

Bronchiectasis Therapeutic Market: DPP1 Inhibition and the First Disease-Specific Therapy Era

The first disease-specific bronchiectasis therapy has reshaped a category historically managed entirely with off-label antibiotics and mucolytics, as payers renegotiate formulary tiers around DPP1 inhibitor exacerbation reduction data rather than symptomatic airway clearance alone.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$2.2BMarket Size 2025
2036 FORECAST VALUE$6.8BBase Case , 2026 to 2036
CAGR 2026 TO 203610.8 %Bull 12.0% / Bear 9.5%
INCREMENTAL OPPORTUNITY$4.4BNet 10- year value creation
EXPANSION MULTIPLE2.79x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Bronchiectasis treatment has shifted from a symptom management category built entirely on off-label antibiotics and mucolytics to a disease-specific therapeutic field, as pulmonologists increasingly specify DPP1 inhibitor therapy as a core exacerbation prevention strategy rather than reserving pharmacologic intervention for acute flare episodes alone, particularly across academic pulmonology centers.
DPP1 inhibitor therapeutics are growing at roughly 2.04x the market average as the first disease-specific approved therapy expands prescribing across newly diagnosed and previously undertreated patient populations. North America retains the largest revenue base on dense pulmonology infrastructure and first-mover reimbursement access, while East Asia is compounding fastest as China's expanding respiratory disease diagnosis capacity pulls demand into the category nationwide across provincial hospital networks.
Competitive intensity concentrates among five specialty respiratory manufacturers that increasingly bundle disease-specific pharmacologics, inhaled antibiotics, and airway clearance devices into a single comprehensive bronchiectasis management platform, leaving smaller generic producers to compete on price for standalone mucoactive agents. Clinical exacerbation reduction data, not symptomatic relief alone, increasingly determines which suppliers win multi-year pulmonology practice and health system contracts today. Group purchasing organizations are beginning to standardize formulary selection across affiliated pulmonology practice networks nationwide and internationally.
Market Definition
The bronchiectasis therapeutic market covers pharmaceutical therapies and airway clearance devices used to manage bronchiectasis, a chronic respiratory condition characterized by permanent airway damage and impaired mucus clearance, spanning DPP1 inhibitor therapeutics, inhaled antibiotics, mucoactive agents, bronchodilators, airway clearance devices, and anti-inflammatory biologics. It includes both disease-specific approved therapies and therapies used off-label to manage bronchiectasis symptoms. Cystic fibrosis-specific bronchiectasis treatment sold under a separate CF indication is excluded.
Base Year Value
$2.2B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
10.8% base case. Bull 12.0%. Bear 9.5%.
Fastest Growth Segment
DPP1 Inhibitor Therapeutics: 22.0% CAGR
Fastest Growth Country
India: 13.8% CAGR
Fastest Growth Region
South Asia and Pacific: 12.9% CAGR
Largest Region
North America: 34% of 2025 global value
Market Leaders
Insmed Incorporated, Zambon, AstraZeneca, Chiesi Farmaceutici, Boehringer Ingelheim. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Bronchiectasis Therapeutic Market Forecast Scenarios

bronchiectasis-therapeutic-market-size-forecast-scenario-1787304542804
Between 2020 and 2025 the market grew at an estimated 8.8% historical CAGR, accelerating sharply following the first disease-specific therapy approval that fundamentally reshaped how pulmonologists approach exacerbation prevention across newly diagnosed and previously undertreated patient populations nationwide. Diagnostic awareness campaigns launched during this period expanded the recognized patient population considerably across most major healthcare markets.
The base case assumes 10.8% CAGR through 2036, anchored in three mechanisms: expanding DPP1 inhibitor prescribing across newly diagnosed and previously undertreated bronchiectasis patients, rising diagnostic awareness and imaging capacity improving disease recognition rates across major healthcare markets, and growing anti-inflammatory biologic development targeting the underlying disease pathology rather than symptomatic management alone. Airway clearance device innovation adds a reinforcing tailwind as portable technology improves patient adherence to daily clearance regimens.
A bull scenario, near 12.0% CAGR, assumes faster DPP1 inhibitor indication expansion and accelerated diagnostic capacity growth pull prescribing forward across more healthcare systems. The bear case, near 9.5% CAGR, assumes payer formulary restrictions on the premium-priced disease-specific therapy slow adoption and pulmonologists continue relying primarily on established off-label antibiotic and mucolytic regimens across most practices.

Disease-Specific Therapy Reshapes Pulmonology Treatment Protocols

Three forces are converging on bronchiectasis therapeutic demand simultaneously: expanding DPP1 inhibitor prescribing following the first disease-specific approval, rising diagnostic awareness and imaging capacity improving disease recognition rates, and growing anti-inflammatory biologic development targeting underlying disease pathology across the affected population. Pulmonologists that once treated bronchiectasis reactively during exacerbations now specify preventive pharmacologic interventi
MARKET CONCENTRATION42%Combined revenue share held by top five respiratory manufacturers
DPP1 THERAPY MONTHLY COST$4,200Blended average list price for a monthly disease-specific prescription
DIAGNOSIS-TO-TREATMENT GAP3-5 yrsTypical delay between symptom onset and confirmed diagnosis today
EXACERBATION REDUCTION RATE21%Clinical trial reported reduction in annual exacerbation frequency
TOP CONSUMING COUNTRYUnited StatesLeading country for bronchiectasis therapy spending volume overall
DIAGNOSED PATIENT PENETRATION38%Share of estimated prevalent patients with a confirmed diagnosis today
Commercially, the category increasingly resembles a chronic disease management relationship bundled around adherence support and exacerbation monitoring rather than an episodic antibiotic prescription. Health systems and specialty pharmacies commit to multi-year patient support programmes spanning disease-specific pharmacologics, airway clearance devices, and monitoring services, since fragmenting these functions across multiple vendors creates care coordination gaps that a unified relationship avoids across the treatment pathway.
Over the next decade, expect DPP1 inhibitor therapeutics to keep gaining share within the broader bronchiectasis budget as diagnostic capacity expands and indication awareness grows, continued consolidation among smaller generic mucolytic producers unable to fund disease-specific pharmaceutical development, and growing scrutiny of exacerbation outcomes driving faster adoption cycles across major pulmonology practice networks worldwide, particularly among value-based care participants.
"Pulmonologists used to manage bronchiectasis the way they managed a chronic cough, treating each flare as it came. Now the first question during a diagnosis visit is whether the patient qualifies for disease-specific therapy, because preventing the next exacerbation has become the actual treatment goal rather than just responding to it."
Director, Respiratory Disease and Specialty Pharmaceuticals Practice · MMA Bronc

Market Trends

Disease-Specific Therapy Approval Reshapes Treatment Guidelines

Pulmonology societies are increasingly updating clinical treatment guidelines to incorporate disease-specific DPP1 inhibitor therapy as a first-line preventive option for patients with frequent exacerbation history, replacing what were historically symptom-driven treatment algorithms built entirely around antibiotics and mucolytics prescribed reactively during flare episodes. Each guideline update increasingly requires payers to reconsider prior authorization criteria that were originally designed around off-label prescribing patterns rather than an approved disease-specific indication. Pulmonology practices adopting updated guidelines report meaningfully increased disease-specific therapy prescribing, reinforcing guideline-driven adoption as the primary growth mechanism across major treatment centers and referral networks today.
Market Impact: Adds 180,000 new diagnoses annually
Diagnostic Awareness Campaigns Expand Recognized Patient Population

Respiratory disease awareness campaigns and improved high-resolution CT imaging availability are increasingly expanding the recognized bronchiectasis patient population beyond the historically underdiagnosed base that persisted for decades due to symptom overlap with other chronic respiratory conditions. Each new diagnostic capacity expansion increasingly requires primary care physicians to consider bronchiectasis alongside more commonly diagnosed conditions like chronic obstructive pulmonary disease during initial respiratory symptom workup. Healthcare systems investing in expanded diagnostic capacity report meaningfully increased confirmed diagnosis rates, reinforcing diagnostic investment as a critical driver of addressable market expansion across the broader respiratory disease category.
Market Impact: Adds 24% to preferred formulary pla

Market Opportunities and Growth Drivers

Rising Diagnostic Capacity Expands Addressable Patient Base

Expanding high-resolution CT imaging availability and growing pulmonologist awareness of bronchiectasis as a distinct clinical entity continue driving improved diagnosis rates across major healthcare markets, proportionally expanding the treatable patient population beyond the historically underdiagnosed base. Healthcare systems report that patients newly diagnosed following expanded imaging access frequently present with more advanced disease than would be expected under earlier detection protocols, a clinical reality reinforcing the urgency of continued diagnostic investment. This diagnostic capacity growth is expanding the addressable therapeutic market well beyond the small population of severe, previously recognized cases that historically drove most category demand.
Market Impact: Limits 34% of eligible patients

Clinical Guideline Updates Drive Formulary Preference Shifts

Updated pulmonology clinical treatment guidelines incorporating disease-specific DPP1 inhibitor therapy as a preferred preventive option are increasingly driving payer formulary preference shifts away from purely symptomatic off-label treatment approaches that dominated the category for decades across most healthcare systems. Payers report that guideline-endorsed disease-specific therapy increasingly determines formulary tier placement decisions independent of legacy prescribing pattern inertia built up over years of off-label use. This evidence-driven formulary shift is pulling forward prescribing transitions that might otherwise have proceeded more gradually absent formal guideline endorsement from major pulmonology societies worldwide.
Market Impact: Excludes 62% of estimated prevalent

Market Restraints and Challenges

High Disease-Specific Therapy Pricing Limits Broad Adoption

Disease-specific DPP1 inhibitor therapy carries substantially higher monthly treatment costs than established off-label generic antibiotics and mucolytics, and the root cause is the complex small-molecule development programme and limited competitive supply behind the first-in-class therapeutic mechanism entering the market. The commercial impact falls hardest on smaller health systems and patients facing high cost-sharing requirements, since a single therapy prescribing decision can represent a meaningful share of an entire respiratory disease formulary budget line. Manufacturers are mitigating this by offering patient assistance programmes and outcomes-based contracting arrangements tailored to cost-sensitive populations.
Market Impact: Lifts guideline-driven prescribing

Persistent Underdiagnosis Constrains Addressable Market Growth

Bronchiectasis remains substantially underdiagnosed relative to its estimated true prevalence, and the root cause is that symptoms frequently overlap with more commonly recognized respiratory conditions, leading primary care physicians to pursue alternative diagnostic pathways before considering bronchiectasis specifically as the underlying cause. The commercial impact falls hardest on manufacturers dependent on new patient identification to sustain growth, since a substantial share of the addressable population remains outside the diagnosed and treated pool entirely. Manufacturers are mitigating this by funding physician education programmes and diagnostic awareness campaigns targeting primary care referral pathways nationwide.
Market Impact: Expands diagnosed population by 26%
4 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows therapeutic and technology type, the single dimension pulmonologists specify against when structuring a bronchiectasis management protocol for a specific patient. DPP1 inhibitors, inhaled antibiotics, mucoactive agents, bronchodilators, airway clearance devices, and anti-inflammatory biologics each address a distinct clinical mechanism, keeping pharmacologic and device dimensions separate across every treatment line and care setting served today.
bronchiectasis-therapeutic-market-market-share-analysis-1787304543404

DPP1 Inhibitor Therapeutics

DPP1 inhibitor therapeutics represent the first disease-specific approved treatment for bronchiectasis, working by inhibiting neutrophil serine protease activation to reduce the chronic airway inflammation that drives disease progression and exacerbation frequency across affected patients over time. Adoption is concentrated among pulmonologists managing patients with frequent exacerbation history who have exhausted symptomatic management approaches without adequate disease control despite prior treatment. Growth outpaces the broader market by roughly 2.04x as the first-in-class mechanism expands prescribing across newly diagnosed and previously undertreated patient populations nationwide and internationally. Manufacturers with proven exacerbation reduction data and established payer relationships are capturing outsized share, since qualifying formulary access requires extensive clinical evidence most competitors cannot yet replicate at scale.
CAGR 22.0%

Anti-Inflammatory Biologic Therapeutics

Anti-inflammatory biologic therapeutics target specific immune pathways implicated in bronchiectasis airway damage progression, offering an emerging complementary approach to DPP1 inhibition for patients with persistent inflammation despite disease-specific pharmacologic treatment already underway across their existing regimen. Adoption is concentrated among academic pulmonology centers managing complex, treatment-refractory patients requiring additional therapeutic intervention beyond first-line options currently available. Growth remains strong as biologic developers advance multiple candidates through clinical trials targeting complementary inflammatory mechanisms across the broader disease pathway and patient population. Manufacturers completing successful clinical trial programmes report meaningfully improved treatment-refractory patient outcomes, reinforcing biologic therapeutics as an emerging standard within comprehensive bronchiectasis management protocols at leading centers nationwide.
CAGR 15.5%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

North America retains the largest revenue base on dense pulmonology infrastructure and first-mover reimbursement access, while East Asia is compounding fastest as China's expanding respiratory disease diagnosis capacity pulls demand into the category nationwide and across every provincial hospital network today.

North America

United States pulmonology practices and specialty pharmacies, concentrated around major academic respiratory disease centers, anchor the region's leading revenue base as first-mover DPP1 inhibitor reimbursement access and rapid guideline adoption drive proportional therapy uptake across the healthcare system. Canadian provincial health systems continue steady bronchiectasis therapy adoption tied to centralized formulary review programmes covering major regional pulmonology networks. Dense diagnostic imaging infrastructure across major United States health systems continues supporting improved disease recognition rates well ahead of many international peer healthcare systems. This share sits above the standard regional band, reflecting genuine concentration of first-mover disease-specific therapy reimbursement access and pulmonology infrastructure within United States institutions rather than an estimation error.
Share: 34% | CAGR: 11.5% (2026 to 2036)

Western Europe

German and French pulmonology centers, operating under centralized national formulary review frameworks, sustain steady demand for both disease-specific therapy and established antibiotic and mucolytic regimens tied to national respiratory disease treatment guidelines. United Kingdom National Health Service pulmonology programmes continue expanding DPP1 inhibitor access tied to national clinical guideline updates covering major teaching hospital respiratory centers. Regional generic manufacturers, including several established European respiratory specialty producers, maintain meaningful domestic penetration built on decades of inhaled antibiotic and mucolytic manufacturing expertise. Regional growth trails East Asia and North America as centralized pricing negotiation frameworks limit the premium pricing upside disease-specific therapy manufacturers can capture relative to less regulated markets elsewhere in the forecast.
Share: 24% | CAGR: 9.2% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
bronchiectasis-therapeutic-market-country-cagr-analysis-1787304543986

Monetizing Adherence Support and Outcomes Contracting

Manufacturers are shifting commercial models toward patient adherence support programmes, value-based outcomes contracting, and diagnostic partnership agreements rather than transactional prescription sales, since payer demand for budget predictability now rivals therapeutic novelty as a formulary negotiation criterion. This mirrors a broader shift across specialty pharmaceutical categories toward relationship-based commercial structures over transactional pricing models.

Offering Structured Patient Adherence Support Programs Broadly

Manufacturers are increasingly offering structured patient adherence support programmes that provide ongoing clinical monitoring, medication reminders, and exacerbation tracking across a prescribed patient's treatment journey, converting what was historically a one-time prescription fulfillment into recurring engagement tied directly to demonstrated adherence outcomes and renewal rates. Manufacturers report adherence programme attach rates above 44% among newly prescribed patients, with continued enrollment rates exceeding 81% once a patient experiences a full quarter of documented symptom improvement. This adherence assurance increasingly determines prescriber confidence ahead of marginal efficacy differences during treatment initiation decisions across most practices.
Market Impact: Lifts adherence programme revenue t

Structuring Value-Based Outcomes Contracting Agreements Broadly

Manufacturers are increasingly structuring value-based outcomes contracts that tie a portion of disease-specific therapy payment to demonstrated exacerbation reduction, giving payers a lower financial risk path to broader formulary coverage of premium-priced therapy across their covered population and enrolled patients. This outcomes-based path typically reduces payer budget risk meaningfully while preserving manufacturer revenue upside tied to real-world effectiveness data collected across enrolled patients. Manufacturers report roughly 23% of new payer agreements now include outcomes-based terms, rising fastest among payers facing the greatest budget pressure around disease-specific therapy adoption decisions.
Market Impact: Expands covered lives by roughly 21

Bundling Diagnostic Partnership and Referral Support Services

Manufacturers are increasingly bundling diagnostic partnership programmes with primary care referral support into their commercial strategy, converting what was historically a passive awareness campaign into an active patient identification pipeline feeding directly into pulmonology treatment centers and affiliated clinics. Bundled diagnostic support typically accelerates a health system's patient identification meaningfully compared with passive awareness campaigns conducted independently across separate departments and referral pathways. Manufacturers report diagnostic partnership attach rates rising fastest among health systems seeking to expand their addressable diagnosed patient population, with roughly 28% of new manufacturer initiatives now including bundled referral support.
Market Impact: Cuts diagnosis-to-treatment gap by

Offering Direct Patient Access and Financial Assistance Programs

Manufacturers are increasingly offering direct-to-patient financial assistance programmes that reduce out-of-pocket costs for patients facing high formulary tier placement or coverage gaps, converting what was historically lost prescription volume into captured revenue through manufacturer-subsidized access channels reaching underserved populations nationwide. These programmes typically restore meaningful patient access among cost-sensitive populations who would otherwise abandon disease-specific therapy entirely, with assistance programmes now supporting roughly 18% of total prescription volume nationwide. Manufacturers report assistance programme attach rates rising fastest among patients facing the highest formulary tier cost-sharing requirements today.
Market Impact: Recovers roughly 22 percentage poin

Who Controls the Margin Pool

The top five manufacturers hold roughly 42% combined share, a moderate concentration reflecting both the first-mover advantage held by the disease-specific therapy originator and the fragmented generic base that still dominates unit volume across established antibiotic and mucolytic categories. The gap between the leading specialty manufacturers and smaller generic producers is widening as payers increasingly restrict preferred formulary placement to manufacturers with clinical exacerbation evid
Current competitive activity centers on three fronts: disease-specific therapy indication expansion supporting broader eligible patient populations, anti-inflammatory biologic pipeline development targeting complementary treatment-refractory mechanisms, and diagnostic partnership development supporting expanded patient identification. Several smaller manufacturers are pursuing licensing partnerships with disease-specific therapy originators rather than developing proprietary mechanisms independently, a faster but margin-diluting route to category participation.

Emerging pressure comes from Indian and Chinese generic manufacturers moving up the value chain from basic antibiotics and mucolytics into specialty respiratory formulations sold initially to domestic pulmonology practices but increasingly targeting export markets as regulatory approvals accumulate. Rankings among the top five could shift meaningfully once biosimilar competition eventually approaches the disease-specific therapy category, since payers increasingly evaluate long-term cost trajectory alongside near-term formulary decisions.
bronchiectasis-therapeutic-market-company-positioning-matrix-1787304544556

Competitive Moat and Risk Dimensions

INSMED INCORPORATED

Moat: First-mover disease-specific therapy

Insmed's status as originator of the first approved disease-specific bronchiectasis therapy gives it durable credibility among pulmonologists who weigh proven exacerbation reduction data heavily, since qualifying an alternative therapy without comparable clinical history carries meaningful treatment continuity risk. That credibility compounds with every additional favorable real-world outcomes publication Insmed generates across its growing patient base.
INSMED INCORPORATED

Risk: Narrow single-product revenue concentration

Insmed's revenue remains heavily concentrated in its single disease-specific therapy relative to diversified respiratory portfolio competitors, occasionally exposing it to formulary or pricing pressure risk that a broader product portfolio would help diversify across multiple revenue streams and therapeutic categories over time.
ZAMBON

Moat: Deep inhaled antibiotic expertise

Zambon's decades of accumulated inhaled antibiotic manufacturing and clinical expertise give it durable credibility among pulmonologists who weigh proven infection management heavily, since switching inhaled antibiotic suppliers without comparable clinical history carries meaningful treatment continuity risk across established patient relationships. That expertise compounds with every additional certified formulation Zambon supports.
ZAMBON

Risk: Limited disease-specific therapy presence

Zambon's portfolio remains comparatively concentrated in established antibiotic and mucolytic categories rather than the newer disease-specific therapy mechanism, occasionally limiting its ability to compete for large bundled comprehensive management contracts that increasingly emphasize disease-modifying treatment approaches over symptomatic relief alone.

Players Tracked

Prominent Players

Insmed Incorporated
Zambon
AstraZeneca
Chiesi Farmaceutici
Boehringer Ingelheim

Other Key Players

Grifols
Vertex Pharmaceuticals
Electromed
Hillrom
Trudell Medical International
PARI Pharma
Teva Pharmaceutical Industries
GlaxoSmithKline
Cipla
Sun Pharmaceutical Industries
Bayer
Merck and Co
Novartis
Genentech (Roche)
Circassia Pharmaceuticals

Recent Developments

AUGUST 2025

Insmed Reports Expanded Real-World Exacerbation Reduction Data

Insmed reported expanded real-world evidence demonstrating sustained exacerbation reduction among patients prescribed its disease-specific bronchiectasis therapy across a growing multi-year patient registry spanning several countries. The data release targets payers evaluating long-term formulary coverage decisions ahead of upcoming annual contract renewal cycles nationwide.
Signal: Confirms real-world evidence generation re
NOVEMBER 2025

AstraZeneca Signs Multi-Year Outcomes Contract With National Payer

AstraZeneca signed a multi-year value-based outcomes contract with a major national health insurer, tying a portion of disease-specific therapy payment to demonstrated exacerbation reduction benchmarks across the covered population. The agreement is a pricing arrangement rather than a joint venture or acquisition, extending AstraZeneca's payer relationship considerably.
Signal: Highlights outcomes-based contracting as t
FEBRUARY 2026

Chiesi Farmaceutici Acquires Regional Airway Clearance Device Manufacturer

Chiesi Farmaceutici completed the acquisition of a regional airway clearance device manufacturer, strengthening its comprehensive bronchiectasis management portfolio and expanding its ability to bundle pharmacologic and device therapies together. The deal reinforces Chiesi's positioning to compete against leading integrated respiratory disease management platforms worldwide.
Signal: Signals continued consolidation of airway

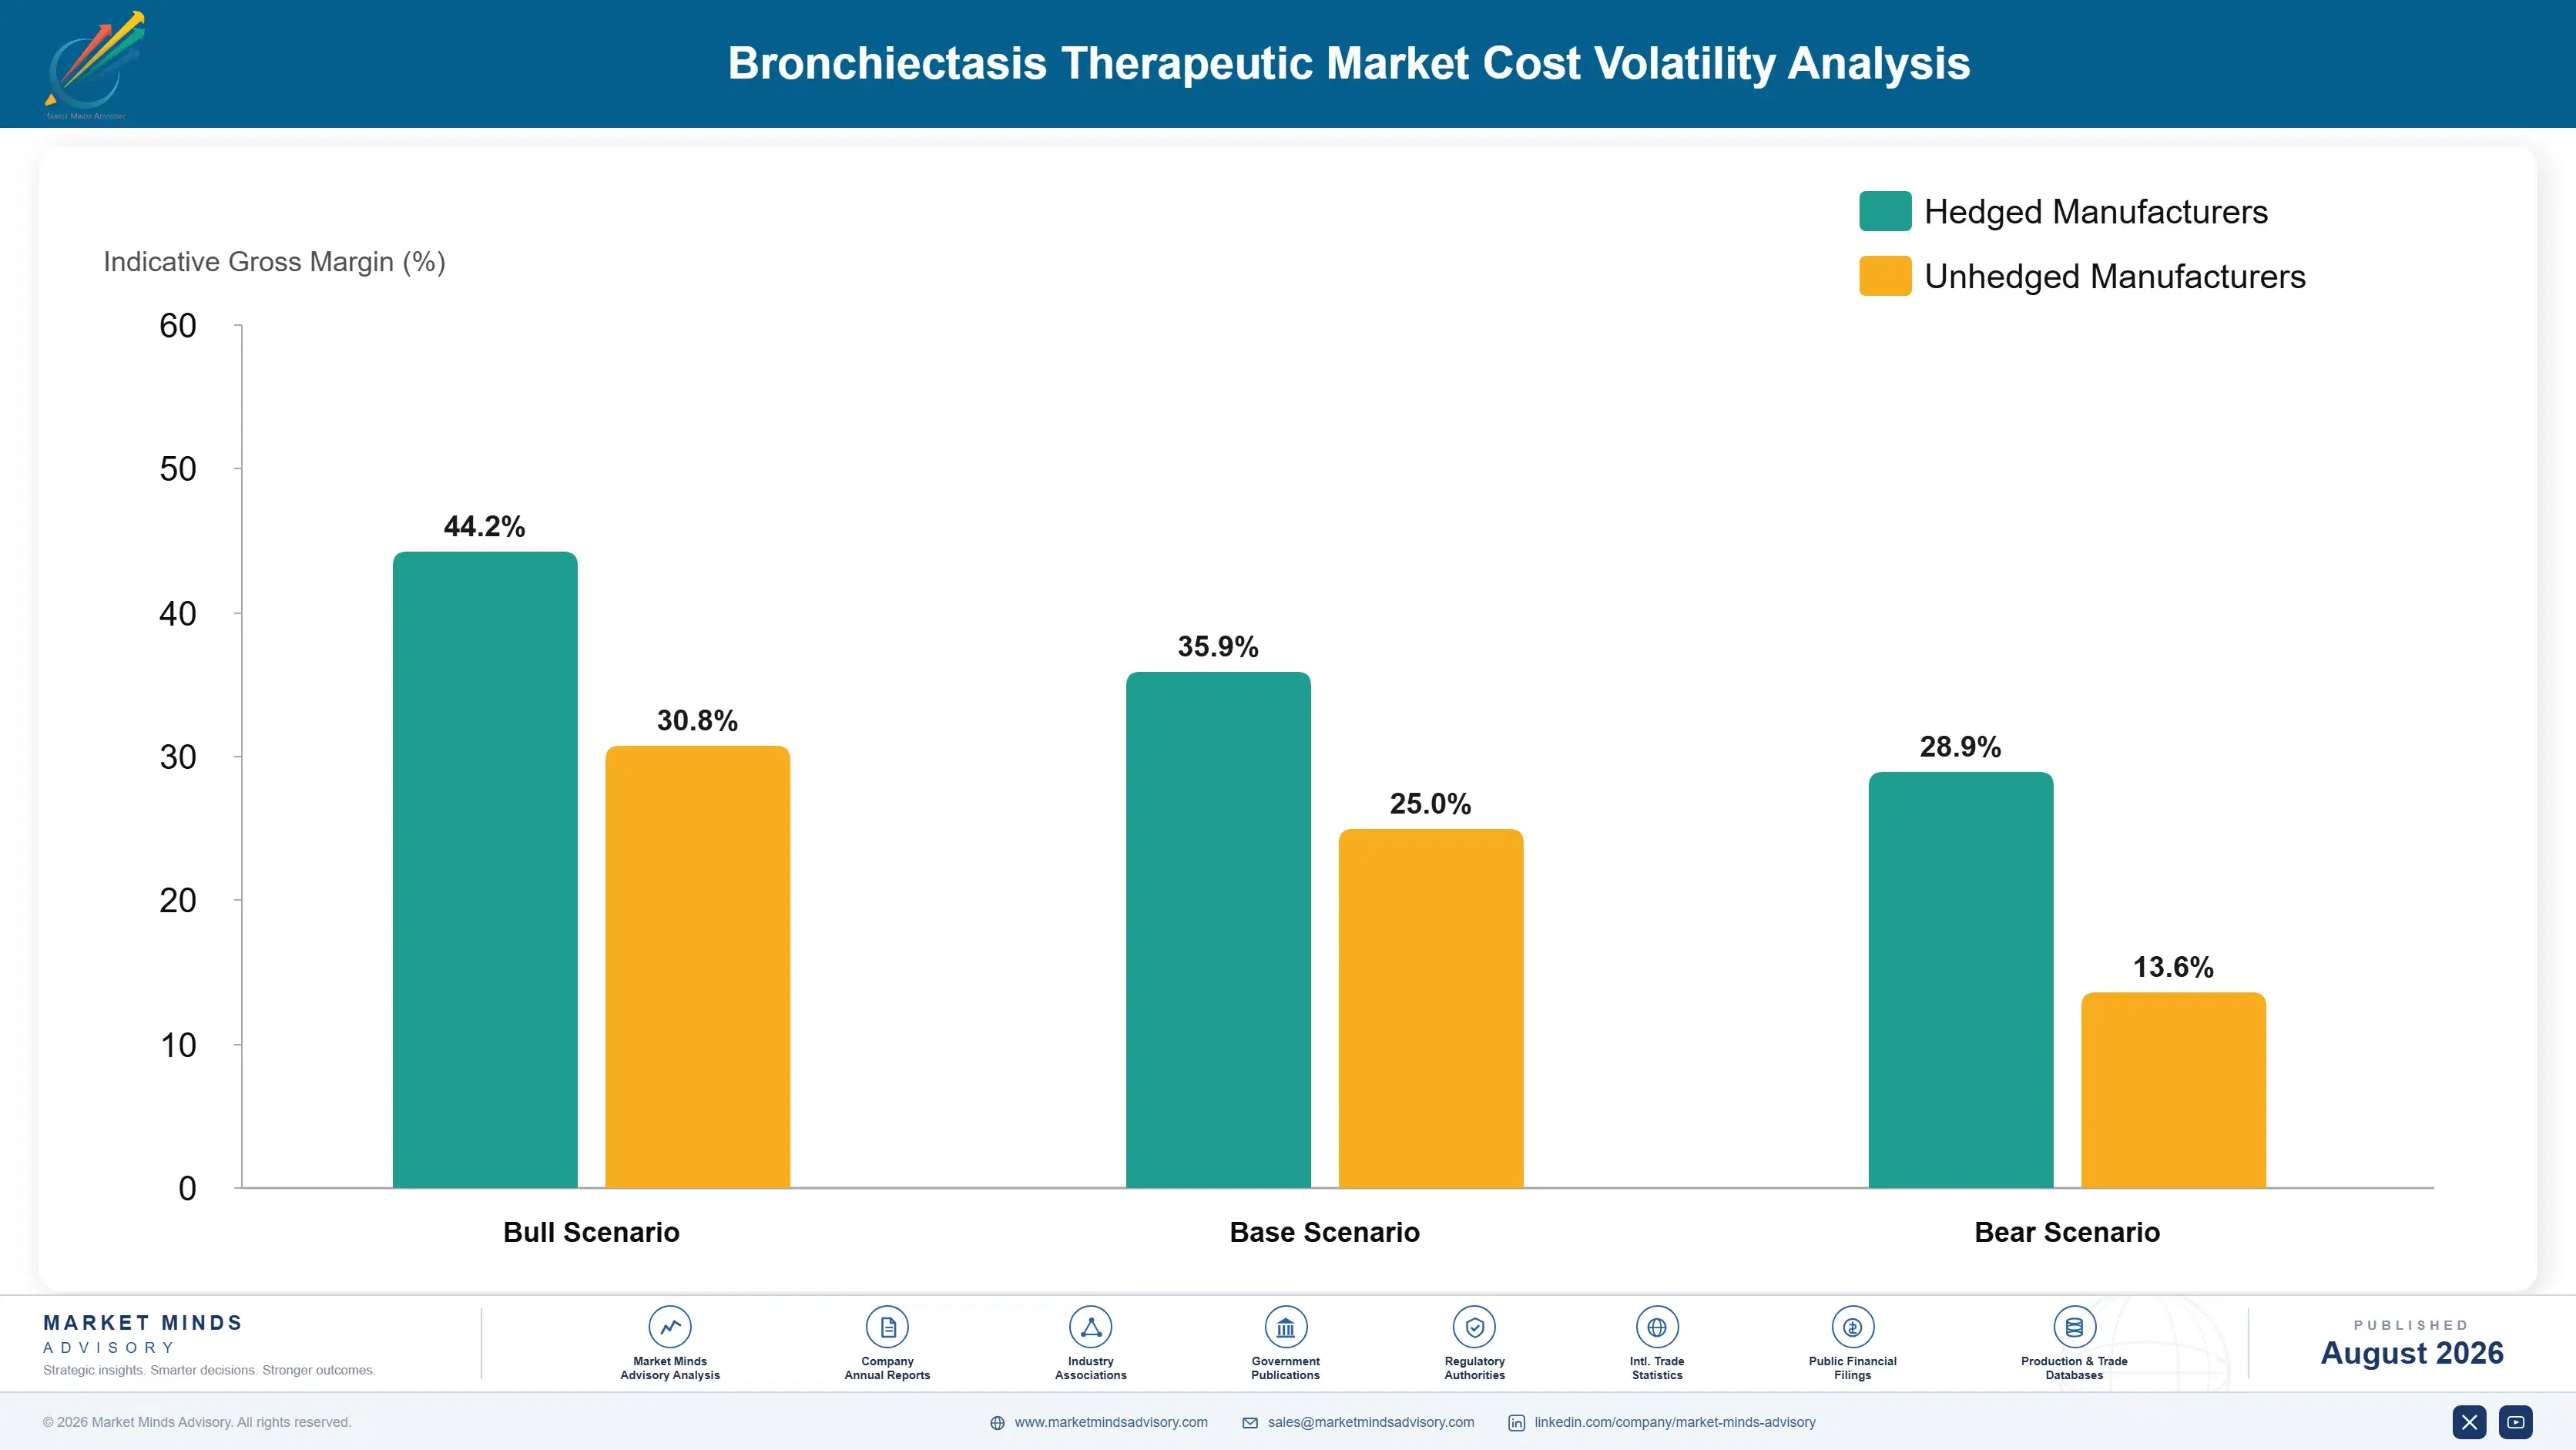
Small Molecule Manufacturing Cost Exposure

Small molecule active pharmaceutical ingredient synthesis, specialized inhaler device manufacturing, and clinical trial infrastructure together represent an estimated 38 to 48% of bronchiectasis therapeutic cost of goods sold across most manufacturers. Small molecule synthesis capacity for the disease-specific therapeutic class remains concentrated among a small number of qualified specialty producers, creating a narrower supply base than most broader respiratory pharmaceutical categories rely u
Contract manufacturing capacity constraints during the therapy's initial launch phase significantly limited production scale-up broadly, and the originator manufacturer flagged the disruption in annual reports as a persistent cost and timeline pressure affecting broader specialty pharmaceutical launch categories simultaneously across the industry. The manufacturer disclosed that qualifying additional contract manufacturing capacity took considerably longer than initially projected, forcing continued allocation constraints during the critical early commercial launch period across major markets.

Smaller manufacturers carry disproportionate exposure to these input constraints since they lack the purchasing scale to secure priority access to limited small molecule manufacturing capacity that the top five manufacturers increasingly control through direct ownership. This gap is widest for manufacturers dependent entirely on third-party contract manufacturing, leaving them more vulnerable to capacity allocation decisions than vertically integrated competitors with internal production capability.
bronchiectasis-therapeutic-market-cost-volatility-analysis-1787304544771

Vertical Integration Into Small Molecule Manufacturing Capacity

Leading manufacturers are increasingly acquiring or building internal small molecule manufacturing capacity rather than relying entirely on third-party contract manufacturers, reducing exposure to capacity allocation constraints that limited production scale-up during the therapy's initial commercial launch period and protecting long-term supply reliability across major markets worldwide throughout sustained demand growth affecting the wider category.

Long-Term Contract Manufacturing Capacity Agreements

Top five manufacturers increasingly lock multi-year capacity agreements directly with qualified contract manufacturers serving small molecule and inhaler device production, smoothing production access and insulating supply from the allocation volatility smaller manufacturers remain exposed to directly, a practice that has become standard procurement policy since the launch period began and continues expanding steadily today.

Diversified Clinical Trial Site Network Development

Manufacturers are increasingly diversifying clinical trial site networks across multiple geographic regions rather than concentrating enrollment in a single country, reducing exposure to any single site's regulatory or enrollment disruption risk and giving manufacturers greater flexibility to accelerate development timelines across the broader clinical evidence generation programme and regulatory submission strategy.

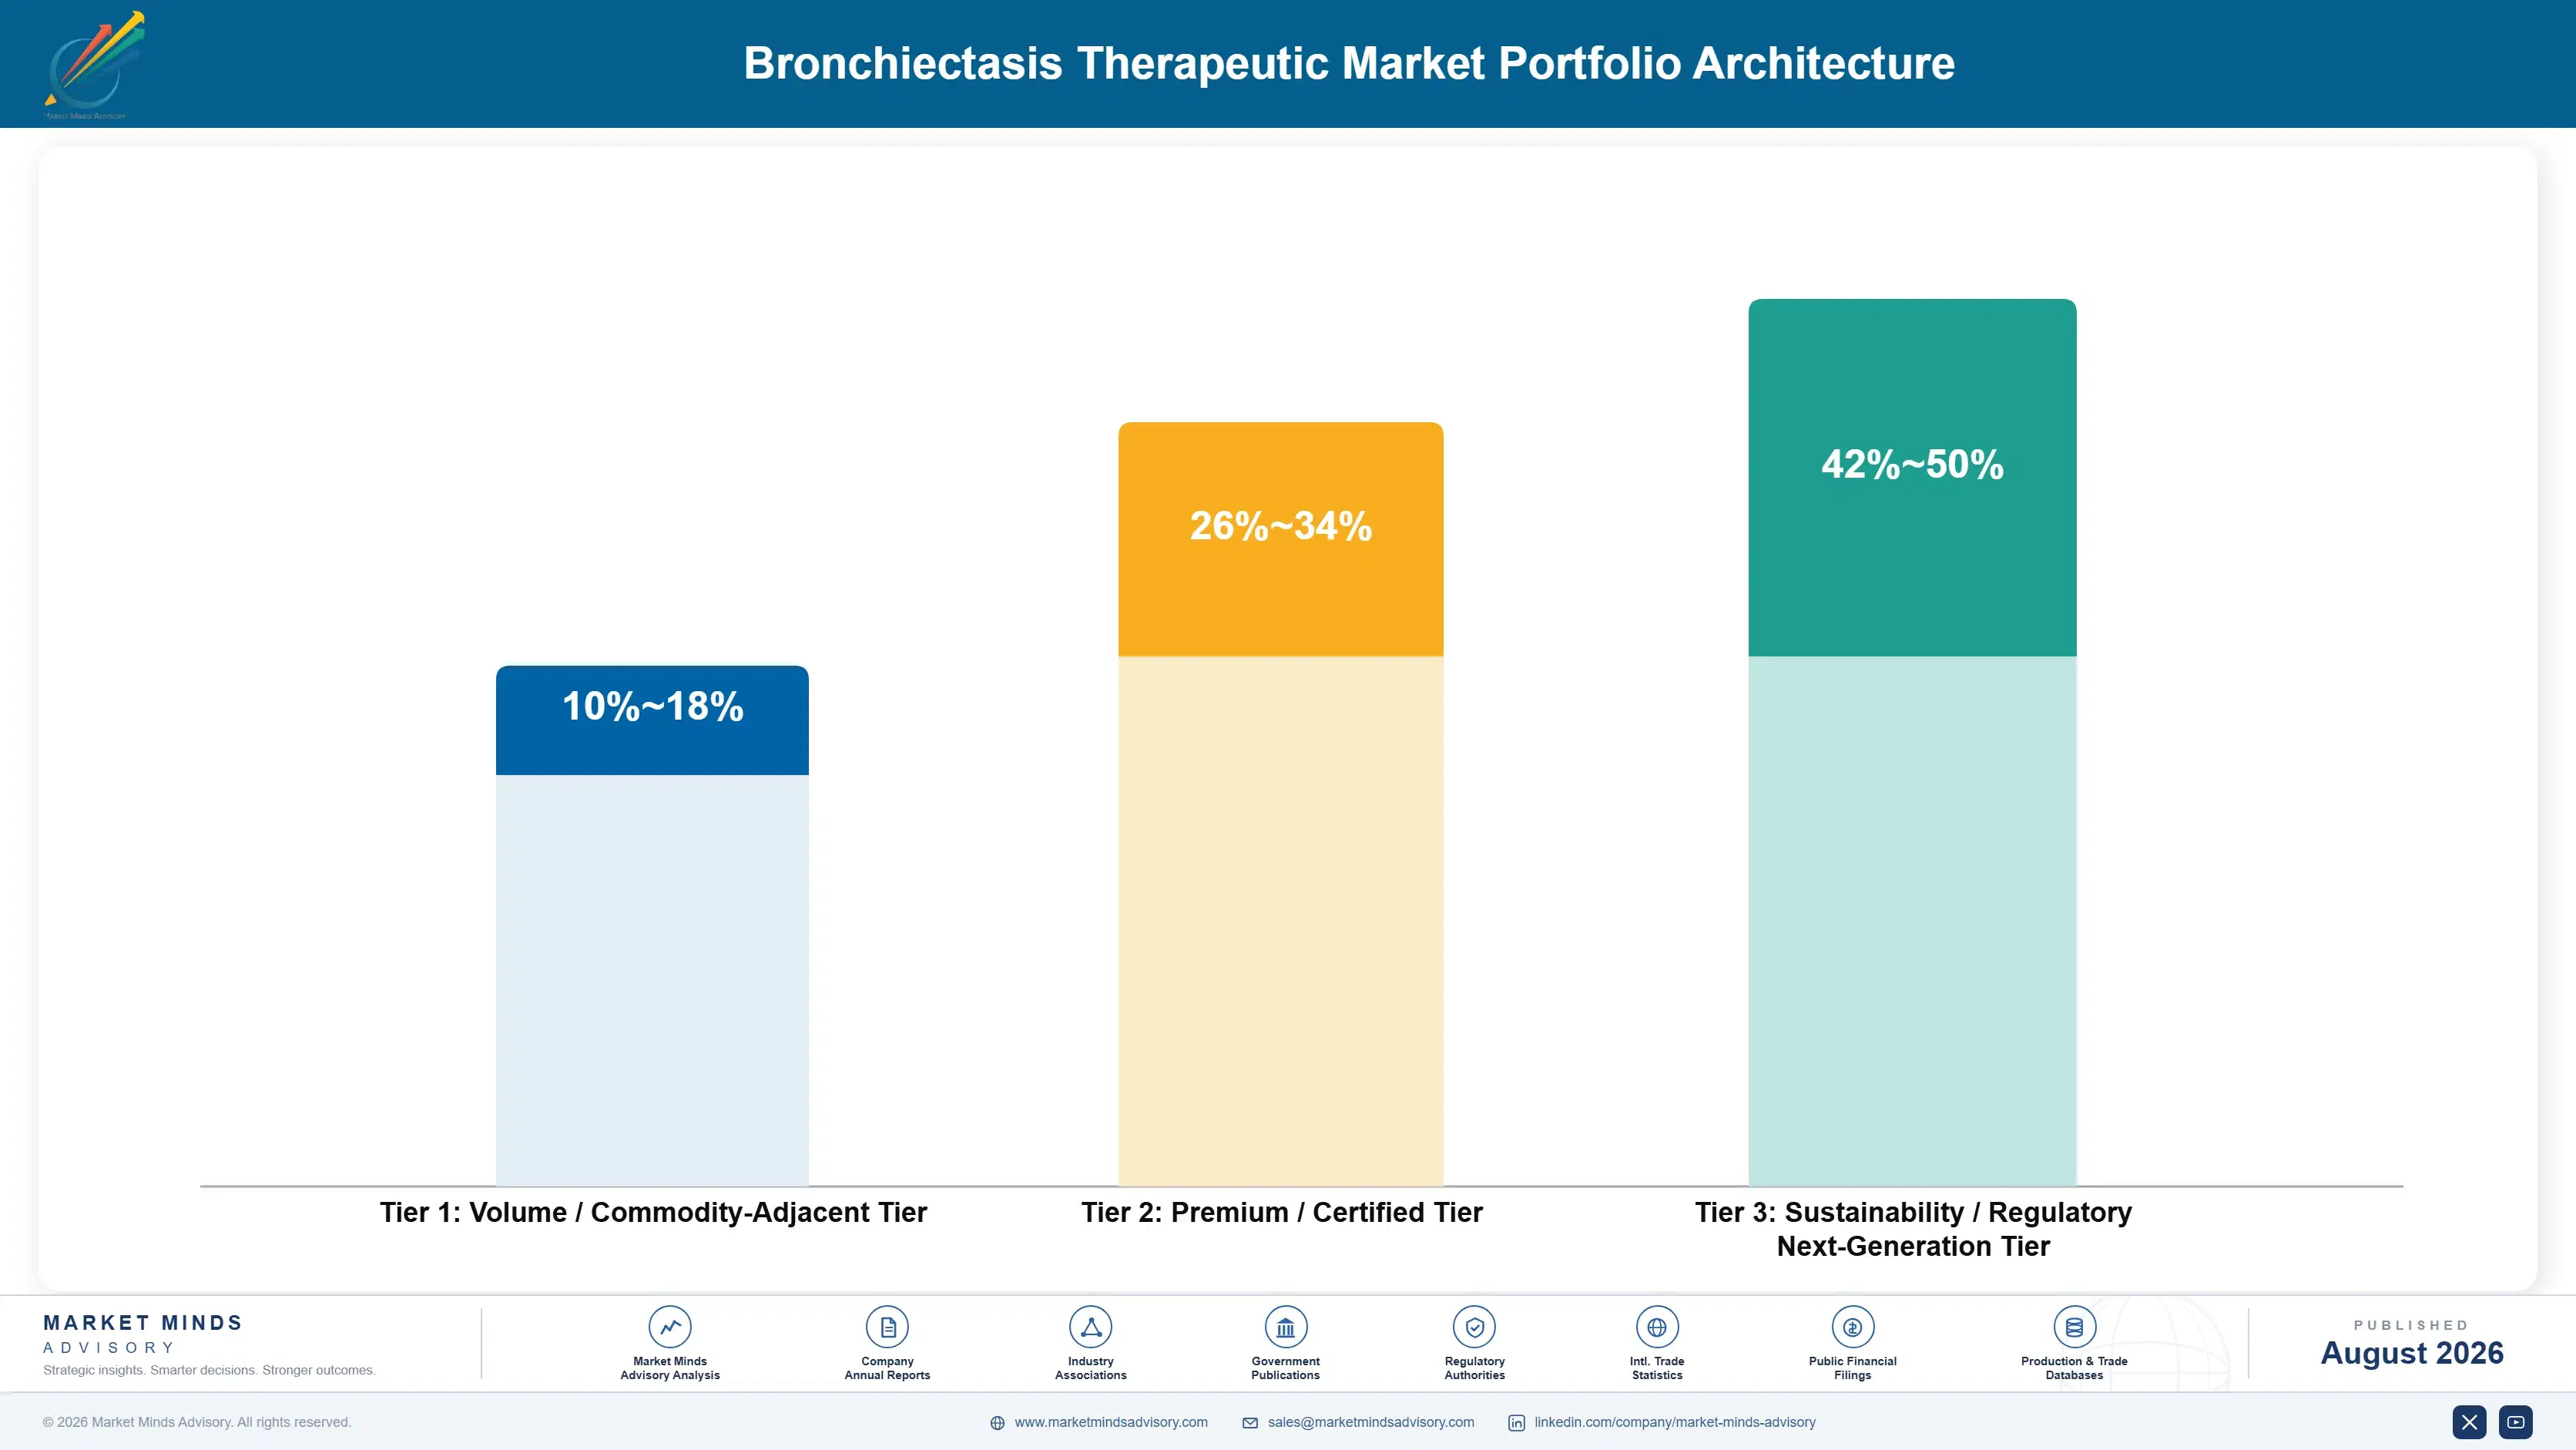
Portfolio Architecture for Margin Defence

Portfolio architecture splits across three tiers: entry priced generic antibiotics and mucolytics competing largely on cost, certified branded inhaled antibiotics and airway clearance devices carrying clinical evidence value that commands a durable price premium, and next generation disease-specific therapeutics bundled with adherence and outcomes contracting services. Gross margins widen meaningfully moving up this ladder as clinical evidence and manufacturing barriers concentrate hardest at th
The volume versus premium tension is sharpest in generic antibiotics and mucolytics, where price competition among smaller regional producers has compressed margins fastest, pushing established manufacturers to defend share through portfolio bundling rather than matching generic pricing directly. Disease-specific therapy retains the strongest pricing power because clinical evidence barriers and outcomes-based contracting discourage payers from switching mid-contract, a dynamic strengthening as adoption broadens.

High value margin pools concentrate in disease-specific therapeutics paired with continuous adherence support and outcomes contracts, where recurring revenue and high switching costs together support gross margins well above the portfolio average. Manufacturers are consequently prioritizing capital toward this tier even though it remains a minority of total prescription volume shipped across the broader portfolio today, betting the mix shifts within the decade.

Volume / Commodity-Adjacent Tier

Generic antibiotics and mucolytics competing primarily on unit price against regional producers, with limited service attach and thin per-unit margins across most transactions, particularly among smaller emerging market health systems with constrained budgets.
Gross Margin: 10-18%

Premium / Certified Tier

Certified branded inhaled antibiotics and airway clearance devices serving formulary-preferred respiratory applications, where clinical evidence depth and reliability support durable pricing across the industry, especially among academic pulmonology centers managing high patient volumes.
Gross Margin: 26-34%

Sustainability / Regulatory / Next-Generation Tier

Disease-specific DPP1 inhibitor and biologic therapeutics bundled with adherence support, outcomes contracting, and patient access programme services, sold on recurring exacerbation-reduction value rather than unit pricing alone, increasingly the default specification.
Gross Margin: 42-50%
bronchiectasis-therapeutic-market-portfolio-architecture-1787304545330

Adherence Contracts Anchor Recurring Prescription Revenue

Bronchiectasis therapeutic economics function increasingly like an annuity once a disease-specific prescribing relationship is established, since adherence support programmes, outcomes contracts, and periodic prescription renewal generate recurring revenue for years after the initial treatment decision closes. This recurring layer now represents a growing share of total category revenue and is the primary reason manufacturers invest heavily in early prescriber relationships even at thin generic
Adoption depth varies sharply by end use vertical. Large academic pulmonology centers run near saturated disease-specific therapy relationships and generate mostly renewal and adherence support demand, while smaller community pulmonology practices are still building out first time disease-specific prescribing familiarity, generating a different mix of new prescription revenue layered on the maturing academic center base.

Buyer profiles are shifting generationally as younger pulmonologists who trained during the disease-specific therapy era increasingly influence prescribing decisions alongside veteran physicians who remember when bronchiectasis had no approved disease-specific treatment option at all. This is accelerating demand for manufacturers with strong clinical evidence and adherence support capability even among prescribers who historically evaluated respiratory therapy purely on symptomatic relief and cost specifications alone.
bronchiectasis-therapeutic-market-end-use-penetration-index-1787304545839

Where Bronchiectasis Treatment Strategy Should Focus

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / DISEASE-SPECIFIC THERAPY INVESTMENT

Prioritize exacerbation reduction evidence over symptomatic relief claims

Symptomatic relief has become table stakes across established generic therapies, no longer a meaningful differentiator in prescriber selection for large pulmonology practice decisions. Physicians now evaluate exacerbation reduction data and disease-modifying evidence ahead of marginal symptomatic gains that once justified a treatment choice on their own. Manufacturers that continue competing primarily on symptom management claims risk losing share to disease-modifying focused rivals bundling pharmacologics, adherence support, and outcomes contracting into a single recurring revenue relationship that is far harder to unwind once established across a health system account.
02 / SERVICE MONETIZATION STRATEGY

Shift commercial models toward adherence and outcomes contract revenue

Generic tier margins will keep compressing as regional producers gain share at the entry tier of the category across most emerging markets. Manufacturers that convert adherence support, outcomes-based pricing, and diagnostic partnerships into contracted recurring revenue will outperform peers still pricing primarily around one-time prescription fulfillment alone. This shift also raises prescriber switching costs meaningfully, since replacing a qualified therapy relationship requires displacing an entrenched, multi-year adherence and outcomes relationship built over years of accumulated clinical trust across every managed patient population.
03 / REGIONAL GROWTH PRIORITIZATION

Weight investment toward South Asia and East Asia over mature markets

South Asia and East Asia are compounding faster than Western Europe on both share and CAGR, driven by expanding diagnostic capacity, rising healthcare access, and first time treatment adoption across previously underserved regional pulmonology networks. Manufacturers weighting sales and diagnostic investment toward these regions ahead of competitors will capture a disproportionate share of first time diagnosis and treatment revenue. Mature markets, running mostly on renewal demand, simply cannot replicate that category of growth at comparable scale or rate over the coming decade of forecast activity.
04 / DIAGNOSTIC AWARENESS RESPONSE

Fund diagnostic partnerships to expand the addressable patient base

The gap between estimated true bronchiectasis prevalence and confirmed diagnosis rates represents a substantial growth opportunity that most manufacturers are not yet equipped to capture efficiently given persistent primary care awareness gaps. Manufacturers that invest early in diagnostic partnership and physician education programmes will be better positioned to expand the treatable patient population without the extended awareness timelines currently limiting category growth. Manufacturers ignoring this opportunity risk ceding a growing share of undiagnosed patient revenue to competitors who have already solved the diagnostic awareness problem first.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Bronchiectasis Therapeutic Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Bronchiectasis Therapeutic Exposure Evaluation 2025-26
CLIENT PROFILE
The client operates a regional pulmonology practice network across the midwestern United States, managing several thousand active bronchiectasis patients across multiple affiliated clinical sites and referral partnerships (client-reported, unverified by MMA). Its existing treatment approach relied primarily on off-label antibiotics and mucolytics across most patients, with limited disease-specific therapy prescribing experience among its clinical staff.
STRATEGIC CHALLENGE
Following the disease-specific therapy approval and updated clinical guidelines, practice leadership sought to systematically transition eligible high-exacerbation patients onto disease-specific treatment within twelve months, while managing payer prior authorization requirements and building clinical staff confidence with the new therapeutic mechanism across every affiliated site and referral partnership.
MMA APPROACH
MMA benchmarked patient identification criteria, payer prior authorization pathways, and clinical staff training requirements against comparable practice network transitions, then modeled adoption sequencing to prioritize the highest-exacerbation patients first during the phased transition programme currently under review by clinical and administrative leadership teams.
KEY FINDINGS
  1. Roughly one third of the practice's active patients met updated clinical guideline criteria for disease-specific therapy eligibility upon detailed review.
  2. Structured prior authorization support reduced projected patient access delay by 38% versus standard payer submission processes across comparable practices, based on modeling completed during evaluation (client-reported, unverified by MMA).
  3. Clinical staff training was projected to cut prescribing hesitancy meaningfully among physicians unfamiliar with the new therapeutic mechanism, according to internal practice survey data collected.
  4. Patients with the highest historical exacerbation frequency carried the greatest near term treatment benefit, reprioritizing the practice's original transition sequence considerably ahead of the initial twelve month plan.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1-4): Identify and prioritize the highest-exacerbation patients meeting updated clinical guideline eligibility criteria today. Phase 2: Phase 2 (Months 5-9): Execute structured prior authorization submissions and clinical staff training across all affiliated practice sites nationwide. Phase 3: Phase 3 (Months 10-12): Monitor early treatment outcomes and refine patient identification criteria based on real-world adherence data collected.
OUTCOME
The practice network completed its disease-specific therapy transition within the twelve month window and reported meaningfully improved exacerbation outcomes among transitioned patients during subsequent internal clinical reviews (client-reported, unverified by MMA). Practice leadership gained structured prior authorization and adherence tracking capability previously unavailable across its distributed clinical network.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Bronchiectasis Therapeutic Market?

The global bronchiectasis therapeutic market reached an estimated $2.2 billion in 2025. Growth is driven by the first disease-specific therapy approval and expanding diagnostic awareness across major healthcare markets.

How large will the Bronchiectasis Therapeutic Market be by 2036?

The market is projected to reach approximately $6.8 billion by 2036, roughly 2.79 times its 2026 value. DPP1 inhibitor therapeutics drive most of the added value across the category.

What is the CAGR for the Bronchiectasis Therapeutic Market 2026 to 2036?

The base case CAGR is 10.8% through 2036. Bull and bear scenarios range from roughly 9.5% to 12.0%, depending on indication expansion pace and diagnostic capacity growth.

Which segment is growing fastest?

DPP1 inhibitor therapeutics lead at a 22.0% CAGR, about 2.04x the overall market rate. Growth is concentrated among newly diagnosed and previously undertreated patient populations.

Who are the major companies in the Bronchiectasis Therapeutic Market?

Insmed Incorporated, Zambon, AstraZeneca, Chiesi Farmaceutici, and Boehringer Ingelheim lead the category. Combined, the top five suppliers hold roughly 42% of global revenue on a consistent basis.

Which country is growing fastest?

India leads country level growth at an estimated 13.8% CAGR. An exceptionally large underdiagnosed patient population and expanding diagnostic capacity are driving first time treatment access.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Therapeutic and Technology Type

  • DPP1 Inhibitor Therapeutics
  • Inhaled Antibiotic Therapeutics
  • Mucoactive and Airway Clearance Agents
  • Bronchodilator Therapeutics
  • Airway Clearance Devices
  • Anti-Inflammatory Biologic Therapeutics

By End-Use Care Setting

  • Academic Pulmonology Centers
  • Community Pulmonology Practices
  • Hospital Respiratory Departments
  • Specialty Pharmacy Channels

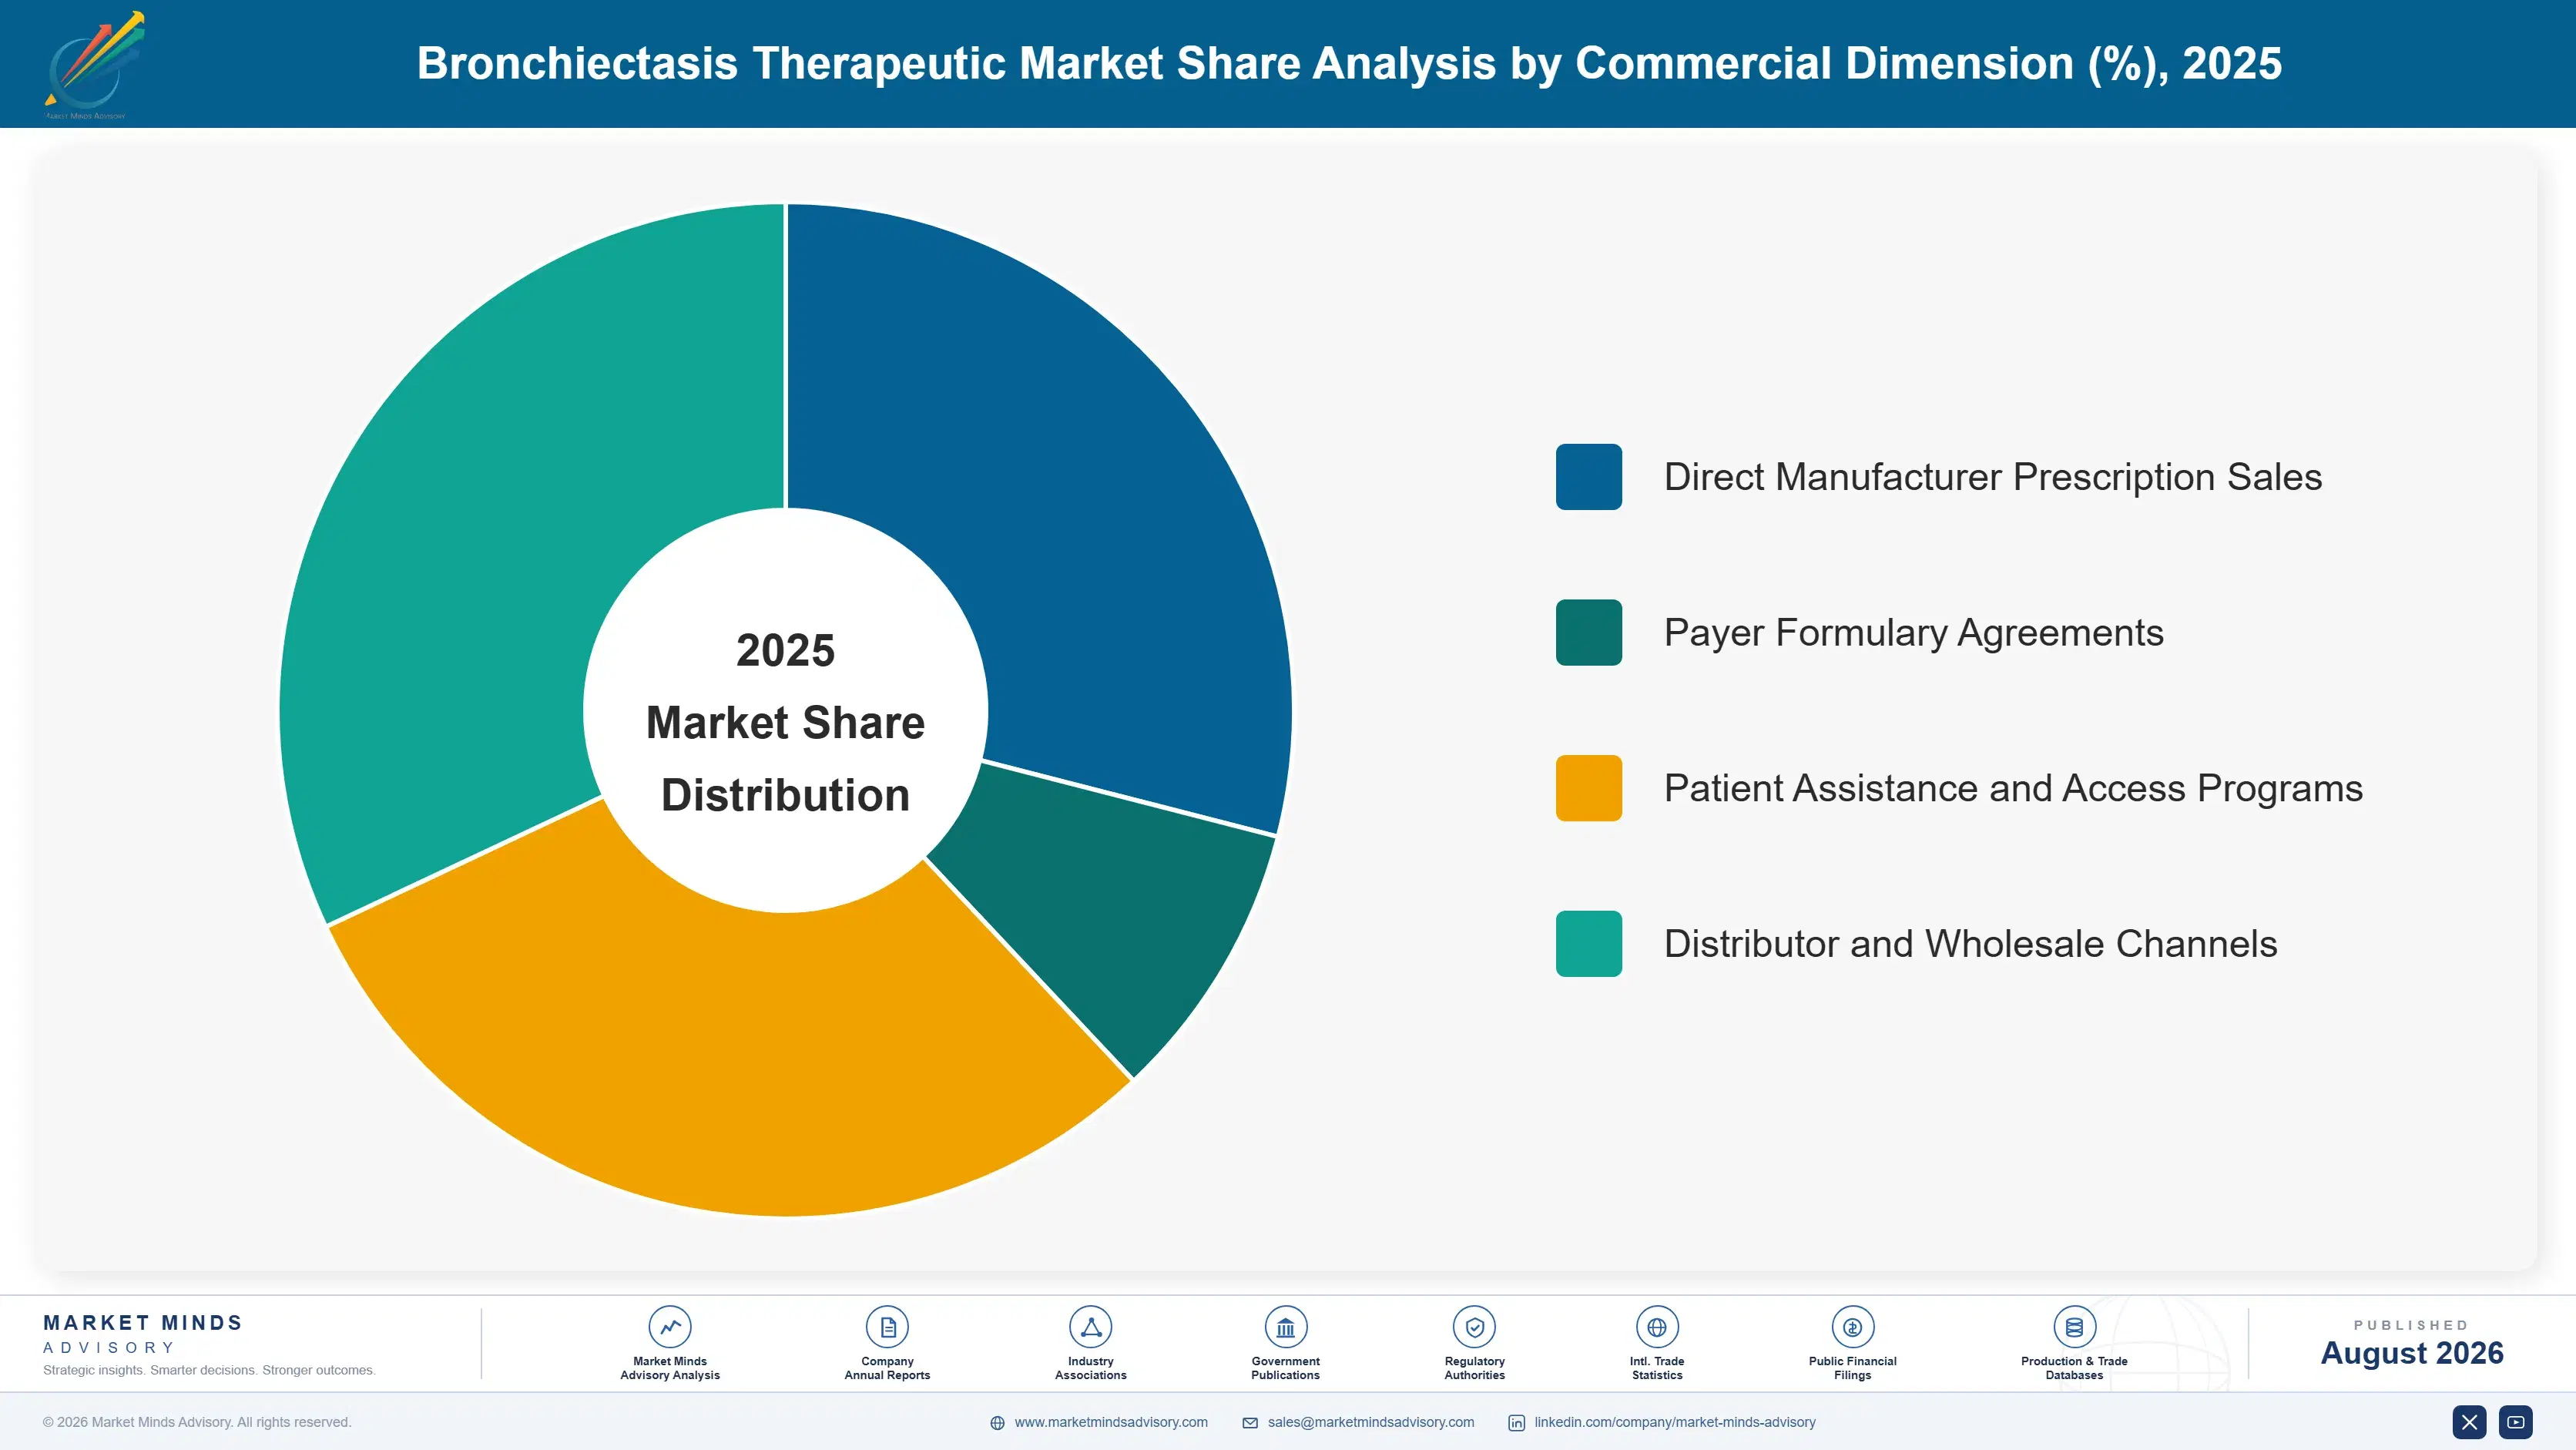
By Commercial Dimension

  • Direct Manufacturer Prescription Sales
  • Payer Formulary Agreements
  • Patient Assistance and Access Programs
  • Distributor and Wholesale Channels

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The bronchiectasis therapeutic market covers pharmaceutical therapies and airway clearance devices used to manage bronchiectasis, a chronic respiratory condition characterized by permanent airway damage and impaired mucus clearance, spanning DPP1 inhibitor therapeutics, inhaled antibiotics, mucoactive agents, bronchodilators, airway clearance devices, and anti-inflammatory biologics. It includes both disease-specific approved therapies and off-label symptomatic treatment approaches.
Quantitative Units
USD billions (current prices); treated patient volume where disclosed
Segmentation Dimensions
By Therapeutic and Technology Type; By End-Use Care Setting; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Thailand, Malaysia, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Insmed Incorporated, Zambon, AstraZeneca, Chiesi Farmaceutici, Boehringer Ingelheim, Grifols, Vertex Pharmaceuticals, Electromed, Hillrom, Trudell Medical International, PARI Pharma, Teva Pharmaceutical Industries, GlaxoSmithKline, Cipla, Sun Pharmaceutical Industries, Bayer, Merck and Co, Novartis, Genentech (Roche), Circassia Pharmaceuticals
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-139
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Bronchiectasis Therapeutic Market Report (2026 to 2036).

The full report delivers a complete quantitative and qualitative assessment of the global bronchiectasis therapeutic market through 2036. It includes detailed segmentation by therapeutic and technology type, care setting, and commercial channel, alongside country level sizing across thirty markets covering every major respiratory disease demand center. Competitive profiles cover twenty companies with clinical evidence, pipeline, and diagnostic partnership benchmarking assessed on a consistent revenue basis. Buyers also receive access to the underlying primary survey and expert interview datasets referenced throughout the analysis, along with editable data tables.
Segment level CAGR and sizing tables
Regional and country level market breakdowns
Twenty company competitive profiles and benchmarks
Detailed clinical evidence benchmarking matrix
Input cost and supply chain risk analysis
Primary survey and expert interview datasets completely included

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts