Market Minds Advisory
Breast Cancer Drug Market

Breast Cancer Drug Market: Antibody-Drug Conjugates Redraw the Treatment Sequence

Antibody-drug conjugates are displacing traditional chemotherapy earlier in the treatment sequence as oncologists chase deeper response rates in HER2-low populations, while CDK4/6 inhibitor franchises defend their hormone receptor-positive stronghold against emerging combination regimens.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$38.0BMarket Size 2025
2036 FORECAST VALUE$106.3BBase Case , 2026 to 2036
CAGR 2026 TO 20369.8 %Bull 11.0% / Bear 8.6%
INCREMENTAL OPPORTUNITY$64.5BNet 10- year value creation
EXPANSION MULTIPLE2.55x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Oncologists are moving antibody-drug conjugates earlier into the treatment sequence as HER2-low expansion data reshapes which patients qualify for targeted therapy ahead of conventional chemotherapy, pushing prescribing patterns toward a meaningfully different standard of care this year across most major treatment centres and their affiliated networks.
Antibody-drug conjugates are pulling ahead of every other drug class as oncologists chase deeper response rates that hormone therapy and traditional chemotherapy alone cannot reliably deliver. North America concentrates the largest share of commercial volume given its premium drug pricing structure and dense concentration of oncology biopharma commercial infrastructure, while China is growing fastest as expanding national reimbursement drug list coverage and domestic biotech production pull volume toward local prescribing.
Competitive character splits between large diversified pharma companies defending broad oncology portfolios across multiple drug classes and specialist biotechs staking commercial success on a single breakthrough mechanism proven across early trial data. Tightening regulatory scrutiny on combination trial design, combined with rising demand for HER2-low and triple-negative indications, is raising the clinical evidence bar that smaller developers increasingly struggle to clear without meaningful capital investment and dedicated regulatory affairs staff of their own each cycle.
Market Definition
The breast cancer drug market covers hormone therapy, CDK4/6 inhibitors, HER2-targeted therapies, antibody-drug conjugates, immune checkpoint inhibitors, and traditional chemotherapy drugs used in breast cancer treatment. It excludes diagnostic testing, radiation therapy, surgical intervention, and supportive care medications administered alongside primary treatment.
Base Year Value
$38.0B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
9.8% base case. Bull 11.0%. Bear 8.6%.
Fastest Growth Segment
Antibody-Drug Conjugates: 16.8% CAGR
Fastest Growth Country
China: 13.2% CAGR
Fastest Growth Region
South Asia and Pacific: 11.9% CAGR
Largest Region
North America: 32% of 2025 global value
Market Leaders
Roche Holding AG, AstraZeneca plc, Novartis AG, Pfizer Inc., Gilead Sciences, Inc. Source: MMA Analysis based on company annual reports and investor filings.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Breast Cancer Drug Market Forecast Scenarios

breast-cancer-drug-market-size-forecast-scenario-1787297952166
Growth from 2020 to 2025 compounded near 8.0%, held back early by pandemic-era screening deferrals that delayed new diagnoses and treatment starts across most major markets for well over a year, then accelerated as deferred diagnoses resumed and antibody-drug conjugate approvals expanded eligible patient populations through the back half of the historical period and its underlying prescribing cycles.
Three mechanisms carry the base case to 9.8%. First, expanding antibody-drug conjugate adoption, which delivers deeper response rates that hormone therapy and traditional chemotherapy alone cannot reliably provide across comparable HER2-low populations and their expanding label indications. Second, growing CDK4/6 inhibitor combination regimens, which extend hormone receptor-positive treatment duration beyond standalone endocrine therapy. Third, expanding Chinese reimbursement coverage, which drives substantial new prescribing volume well beyond traditional Western commercial markets and their established payer structures.
The bull case at 11.0% assumes antibody-drug conjugate combination data reads out favorably across earlier treatment lines sooner than current trial timelines suggest, pulling forward regulatory submissions considerably. The bear case at 8.6% assumes payer pricing pressure intensifies across several major markets simultaneously and slows follow-on reimbursement negotiations for newly approved combination regimens and their broader launch plans.

Antibody-Drug Conjugates Redraw the Treatment Sequence

Three forces converge on this market simultaneously and reshape prescribing patterns considerably. Antibody-drug conjugate adoption keeps expanding as oncologists chase deeper response rates that hormone therapy and traditional chemotherapy alone cannot reliably provide across comparable HER2-low populations. CDK4/6 inhibitor combination regimens keep growing, extending hormone receptor-positive treatment duration beyond standalone endocrine therapy. Chinese reimbursement coverage keeps expandin
MARKET CONCENTRATIONCR5 52%Reflects a market shaped by large diversified oncology portfolios
AVERAGE TREATMENT COSTUSD 8,000-18,000 per monthVaries substantially by drug class and treatment line sequencing
TOP PRODUCING COUNTRY SHAREUSA 31%Reflects concentrated commercial infrastructure and premium pricing structure
HER2-LOW ELIGIBLE EXPANSION42%Share of previously ineligible patients now qualifying for targeted therapy
TRADE INTENSITY38%Share of finished doses crossing borders before reaching treatment centres
COMBINATION REGIMEN SHARE56%Share of active treatment protocols now pairing multiple drug classes
Commercially, the market splits between large diversified pharma companies defending broad oncology portfolios across multiple drug classes simultaneously and specialist biotechs staking commercial success on a single breakthrough mechanism proven across early clinical data. Large diversified companies capture value through combination trial breadth and existing commercial infrastructure, while specialist biotechs compete primarily on mechanism differentiation and speed to pivotal readout.
Looking ahead, expanding antibody-drug conjugate adoption, growing combination regimens, and rising Chinese reimbursement coverage will shape which companies capture the fastest-growing demand pools over the coming decade, rewarding those who invested early in both mechanism differentiation and combination trial design rather than those relying solely on monotherapy data carried over from earlier development cycles and product catalogs.
"Chemotherapy used to be the fallback when targeted therapy ran out of road. Now the antibody-drug conjugate is often the first call, and that sequencing shift has rewritten who wins the prescribing decision."
Director, Oncology Pharmaceuticals Practice · MMA Healthcare - Oncology Pharmace

Market Trends

HER2-Low Expansion Broadens Antibody-Drug Conjugate Eligibility

Regulatory agencies keep expanding antibody-drug conjugate approvals into HER2-low patient populations that earlier trial designs excluded entirely, pushing prescribing patterns toward agents that deliver deeper response rates conventional chemotherapy cannot reliably provide across comparable receptor expression levels. Oncologists previously reserving antibody-drug conjugates for HER2-positive disease increasingly rewrite treatment protocols to include HER2-low patients earlier in the sequence, since delayed access to targeted therapy carries meaningful survival cost. Companies with validated HER2-low indications already proven across comparable trial populations are capturing prescribing share that competitors still awaiting label expansion cannot secure.
Market Impact: Chinese prescribing volume grew 27%

CDK4/6 Combination Regimens Extend Treatment Duration

CDK4/6 inhibitor combination regimens keep expanding across most major hormone receptor-positive treatment protocols as oncologists pursue extended progression-free survival that standalone endocrine therapy cannot reliably deliver across comparable patient populations. This shift is reshaping which companies can compete profitably for large payer contracts, since achieving validated combination data requires clinical trial investment that smaller specialist developers increasingly cannot match on comparable research budgets. Companies with proven combination platforms are winning payer formulary positions that competitors relying on monotherapy data increasingly cannot match on documented efficacy and long-term survival outcomes across comparable patient cohorts.
Market Impact: Triple-negative prescribing grew 19%

Market Opportunities and Growth Drivers

Chinese Reimbursement Coverage Expands Very Rapidly

China's National Reimbursement Drug List continues expanding oncology coverage as domestic hospital systems pursue broader patient access than previous restrictive reimbursement rules increasingly could not sustain given persistent demand growth simultaneously and aggressively across most major provincial hospital networks. Each newly added drug listing requires substantial price negotiation meeting national procurement standards rather than informal regional-level access arrangements. Chinese hospital systems increasingly treat reimbursement listing as a critical input in commercial launch planning rather than a downstream pricing decision, pushing companies further into negotiation earlier in the approval process than before.
Market Impact: Combination pricing fell over 16%

Triple-Negative Indication Expansion Broadens Overall Demand

Triple-negative breast cancer treatment options keep expanding across most major oncology programmes as companies pursue immune checkpoint inhibitor and antibody-drug conjugate combinations that earlier chemotherapy-only protocols could not reliably support across comparable survival outcomes and patient cohorts. Oncologists increasingly favor companies with documented triple-negative trial credentials in treatment protocol decisions, pushing developers to treat this indication as a commercial priority rather than a niche category. Companies with proven triple-negative platforms are winning prescribing share that competitors relying on conventional chemotherapy increasingly cannot match on documented survival data and long-term outcomes.
Market Impact: Adds 6 to 12 months

Market Restraints and Challenges

Payer Pricing Pressure Squeezes Combination Regimen Margin

Payer pricing pressure on newly approved combination regimens has intensified considerably faster than single-agent pricing pressure across recent years, squeezing margin on reimbursement negotiations that bundle two or more premium-priced drug classes together. The root cause is payer resistance to stacking full list prices for each component drug when combined clinical benefit does not scale proportionally with combined cost. The commercial impact falls hardest on smaller specialist developers lacking negotiating leverage with major payers. Several companies now offer outcomes-based contracting and bundled pricing models that address payer concerns directly across most major reimbursement negotiations.
Market Impact: HER2-low prescribing volume rose 31%

Manufacturing Complexity Delays Antibody-Drug Conjugate Supply

Antibody-drug conjugate manufacturing complexity is delaying commercial supply timelines even when clinical trial data and regulatory approval proceed on schedule without complication elsewhere in the launch process. The root cause traces to limited specialised conjugation manufacturing capacity outpacing rapidly expanding commercial demand across most active launch programmes globally. The commercial impact includes delayed market entry and rising per-dose production costs that erode launch economics companies originally budgeted for. Several companies now secure dedicated manufacturing slots years in advance and are expanding in-house conjugation capacity where capital allows it across their broader manufacturing footprint.
Market Impact: Combination regimen adoption grew 24%
4 additional market trends, 3 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows drug mechanism class rather than breast cancer subtype, since a single drug commonly advances across hormone receptor-positive, HER2-positive, and triple-negative indications simultaneously under distinct clinical protocols. This reflects how companies actually organise pipeline development, manufacturing, and commercial catalog structure internally across their own operating divisions and regional commercial teams worldwide today and beyond.
breast-cancer-drug-market-market-share-analysis-1787297952702

Antibody-Drug Conjugates

Antibody-drug conjugates combine a targeting antibody with a cytotoxic payload delivered directly to cancer cells, most valued where oncologists pursue deeper response rates than hormone therapy and traditional chemotherapy alone reliably deliver across comparable HER2 expression levels. Growth outpaces every other category as oncologists increasingly move these agents earlier into the treatment sequence rather than reserving them for later treatment lines. Companies with validated HER2-low indications already proven across comparable trial populations are capturing prescribing share that competitors still awaiting label expansion cannot secure at comparable scale. The United States and China drive the bulk of current volume given their concentration of active oncology commercial investment and regulatory support infrastructure.
CAGR 16.8%

Immune Checkpoint Inhibitors

Immune checkpoint inhibitors block regulatory pathways that allow tumours to evade immune detection, most valued where oncologists pursue durable response in triple-negative and high-risk populations that hormone therapy and standard chemotherapy alone cannot reliably provide. Growth is second-fastest across the segmentation, driven by expanding combination protocols pairing checkpoint inhibitors with chemotherapy or antibody-drug conjugates ahead of standalone use. Companies with validated checkpoint combination data are capturing triple-negative prescribing share that competitors still relying on chemotherapy alone increasingly cannot match on documented survival outcomes. Pricing reflects that complexity, commanding meaningfully higher per-cycle value than standard chemotherapy alternatives. The United States leads current adoption, with China and Germany expanding comparable checkpoint combination programme capacity steadily each year.
CAGR 13.5%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

North America holds the largest share given its premium drug pricing structure and dense concentration of oncology biopharma commercial infrastructure across most major markets. China is growing fastest as expanding national reimbursement drug list coverage and domestic biotech production pull volume toward local prescribing nationwide.

North America

The United States drives the overwhelming majority of regional demand through sustained premium drug pricing and the earliest commercial launch pattern of any major market, with Pfizer and Gilead anchoring domestic commercial infrastructure across most large academic cancer centres and their affiliated community oncology networks. Domestic supplier headquarters presence, spanning Pfizer, Gilead, and Puma Biotechnology among others, supports deep distribution reach that imported competitors struggle to match on launch speed. Canada contributes a meaningful base through its own public reimbursement system, particularly institutions tied to national oncology drug formularies and academic research collaborations. Clinical evidence depth remains the binding factor shaping prescribing selection across much of the region, more so than raw list pricing alone.
Share: 32% | CAGR: 9.2% (2026 to 2036)

Western Europe

Germany anchors regional demand through its dense hospital network and concentration of academic oncology centres running combination trials ahead of most regional peers and their comparable clinical programmes. Switzerland contributes significant volume through Roche and Novartis serving public and private hospital systems internationally from domestic manufacturing bases spanning decades of accumulated oncology development knowledge. The United Kingdom adds further volume through the National Health Service's centralised procurement framework serving hospital trusts directly. The region's strong public healthcare funding framework sustains steady prescribing demand independent of export market cycles entirely. Growth trails the global average because much of the region's own prescribing base already carries modern combination protocols installed during previous funding cycles.
Share: 23% | CAGR: 8.2% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
breast-cancer-drug-market-country-cagr-analysis-1787297953212

Where Companies Can Capture More Value

Companies sit between intensifying payer pricing pressure and rising demand for antibody-drug conjugate and combination regimen platforms, a position that offers several distinct paths to capture more value than a standalone monotherapy launch provides, particularly as outcomes-based contracting and specialist manufacturing gain commercial importance among payer buyers. The four levers below reflect where value is genuinely shifting across the industry.

Pursue Combination Partnerships With Checkpoint Leaders

Companies navigating intensifying payer pricing pressure increasingly prefer partnering with established checkpoint inhibitor franchises rather than pursuing standalone monotherapy approval, since that pairing reduces commercial risk considerably compared with proving efficacy alone against a moving competitive bar. Merck and AstraZeneca have both expanded dedicated combination partnership programmes covering deals worth well over USD 500 million combined across recent years of active licensing activity in the sector. That structure builds commercial relationships considerably stickier than standalone launches, since switching partners mid-programme would force developers to restart trial design entirely and requalify every downstream regulatory submission.
Market Impact: Combination partnership deals now exceed USD 500 million

Expand Dedicated Conjugation Manufacturing Capacity Now

Antibody-drug conjugate demand represents a considerably more defensible margin pool than standard chemotherapy demand alone could ever support, since conjugate pricing commands roughly 5 times standard chemotherapy per-cycle value across most major producing markets tracked in this report. Companies expanding dedicated conjugation manufacturing capacity capture launch contracts that generalist competitors increasingly cannot match, generating meaningful revenue through phased capacity conversion that unfolds across multiple budget cycles rather than a single capital purchase decision made all at once across the company's broader capital and product development plan and its supporting regulatory strategy.
Market Impact: Conjugate pricing exceeds chemotherapy by roughly 5 times

Build Direct Payer Outcomes-Based Contracts Early

Payers increasingly consolidate reimbursement decisions through outcomes-based contracting, and companies who maintain direct relationships built on documented clinical outcomes capture recurring formulary revenue considerably more predictable than one-off list-price negotiations alone ever provide, often worth USD 3 million or more annually across a comparable payer relationship. That relationship also generates early visibility into upcoming formulary renewal cycles before competitors even learn a negotiation is coming their way. Building this relationship depth should rank above chasing every available list-price negotiation across the wider payer market and its unpredictable funding cycles and shifting formulary priorities.
Market Impact: Outcomes contracts renew across 3 to 5 year cycles

Expand Chinese Reimbursement Presence Now Aggressively

Chinese prescribing demand is scaling quickly, growing near 13% annually, as domestic hospital systems expand reimbursement coverage requiring validated pricing negotiation meeting national procurement standards across most major provincial hospital networks and their satellite clinics. Companies establishing local regulatory and commercial support presence early are winning multi-year reimbursement listings before competitors relying solely on import channels can match local pricing and access speed across comparable market scale. That early-mover position compounds considerably as China's oncology sector keeps climbing through the remainder of the decade ahead of most other regional markets.
Market Impact: Chinese demand grows near 13% each year now

Who Controls the Margin Pool

Concentration sits at a moderate 52% for the top five, reflecting a market shaped by large diversified pharma companies defending broad oncology portfolios and numerous specialist biotechs competing on single-mechanism breakthroughs. The gap between leaders and challengers comes down to combination trial depth rather than raw pipeline breadth alone. All participants here are assessed on one basis, annual breast cancer drug revenue, excluding broader oncology portfolio revenue outside this indica
Competition runs along three lines. First, combination trial depth, since companies with documented combination data win payer formulary positions competitors still awaiting readouts cannot bid on. Second, manufacturing scalability, as payers increasingly demand consistent supply bundled into standard reimbursement agreements. Third, regulatory alignment speed, particularly for companies pursuing fast-growing Chinese reimbursement markets directly.

Pressure is building from two directions. Chinese biotechs are narrowing the pipeline development gap considerably faster than expected, squeezing prescribing share established Western companies previously captured on brand reputation alone. Meanwhile larger diversified pharma companies keep acquiring specialist oncology developers to fill capability gaps rather than build organically, consolidating the field further. Rankings should favor companies combining combination trial depth with genuine manufacturing scale.
breast-cancer-drug-market-company-positioning-matrix-1787297953734

Competitive Moat and Risk Dimensions

ROCHE HOLDING AG

Moat: Deep HER2 franchise heritage

Roche's decades-long presence in HER2-targeted therapy through Herceptin, Perjeta, and Kadcyla gives it deep credibility with oncologists navigating sequencing decisions, supporting premium pricing that narrower specialist competitors cannot command. Its scale supports engineering investment in next-generation conjugates that smaller developers typically cannot match on comparable research budgets.
ROCHE HOLDING AG

Risk: Legacy franchise erosion risk

Roche's older HER2 franchise faces gradual erosion from newer antibody-drug conjugates with stronger efficacy data, leaving it potentially exposed to prescribing share loss as oncologists shift toward AstraZeneca's Enhertu and comparable next-generation options in similar indications. Faster-moving rivals could keep eroding its franchise value over the coming years.
ASTRAZENECA PLC

Moat: Leading antibody-drug conjugate platform

AstraZeneca's Enhertu partnership with Daiichi Sankyo holds the deepest published clinical trial base in HER2-low antibody-drug conjugate therapy, letting it capture prescribing share that competitors without comparable trial data cannot yet match. Its commercial infrastructure supports rapid launch execution that smaller specialist developers typically cannot match on speed.
ASTRAZENECA PLC

Risk: Partnership economics limit margin

AstraZeneca's profit-sharing arrangement with Daiichi Sankyo on Enhertu leaves it capturing a smaller share of total revenue than a wholly owned asset would provide, leaving margin more exposed to partnership renegotiation risk than fully proprietary competitors enjoy across their comparable oncology franchises and broader commercial portfolios.

Players Tracked

Prominent Players

Roche Holding AG
AstraZeneca plc
Novartis AG
Pfizer Inc.
Gilead Sciences, Inc.

Other Key Players

Daiichi Sankyo Company, Limited
Eli Lilly and Company
Merck & Co., Inc.
Bristol Myers Squibb Company
Seagen Inc.
Puma Biotechnology, Inc.
Sanofi S.A.
Menarini Group
Zymeworks Inc.
Byondis B.V.
Innovent Biologics, Inc.
Jiangsu Hengrui Medicine Co., Ltd.
BeiGene, Ltd.
Amgen Inc.
Sun Pharmaceutical Industries Ltd.

Recent Developments

MARCH 2025

AstraZeneca reports pivotal HER2-low expansion data for Enhertu

AstraZeneca reported pivotal trial data expanding Enhertu's HER2-low indication into earlier treatment lines, showing durable response rates that support a planned regulatory submission for broader label expansion. This was a clinical data readout rather than an acquisition, extending AstraZeneca's commercial positioning ahead of most direct platform competitors.
Signal: Companies are increasingly prioritising HER2-low expansion data for earlier treatment line label submissions and regulatory approvals.
OCTOBER 2024

Pfizer completes acquisition of Seagen to expand conjugate pipeline

Pfizer completed its acquisition of Seagen to strengthen its antibody-drug conjugate portfolio rather than continue developing comparable technology internally for select applications across its broader oncology pipeline and partnership roadmap. This was a confirmed acquisition, extending Pfizer's conjugate engineering capability directly and permanently across its oncology division.
Signal: Larger pharmaceutical companies are acquiring specialty conjugate developers to internalise platform capability rather than license it.
MAY 2025

Novartis signs multi-year supply agreement across Chinese hospital network

Novartis signed a multi-year Kisqali supply agreement covering validated pricing arrangements across an expanding Chinese hospital network reimbursement programme currently under active development across multiple provinces. This was a confirmed supply agreement rather than an acquisition, extending Novartis's East Asian presence directly and substantially over time.
Signal: Pricing supply agreements are increasingly tied to national reimbursement expansion cycles rather than standalone one-off tenders.

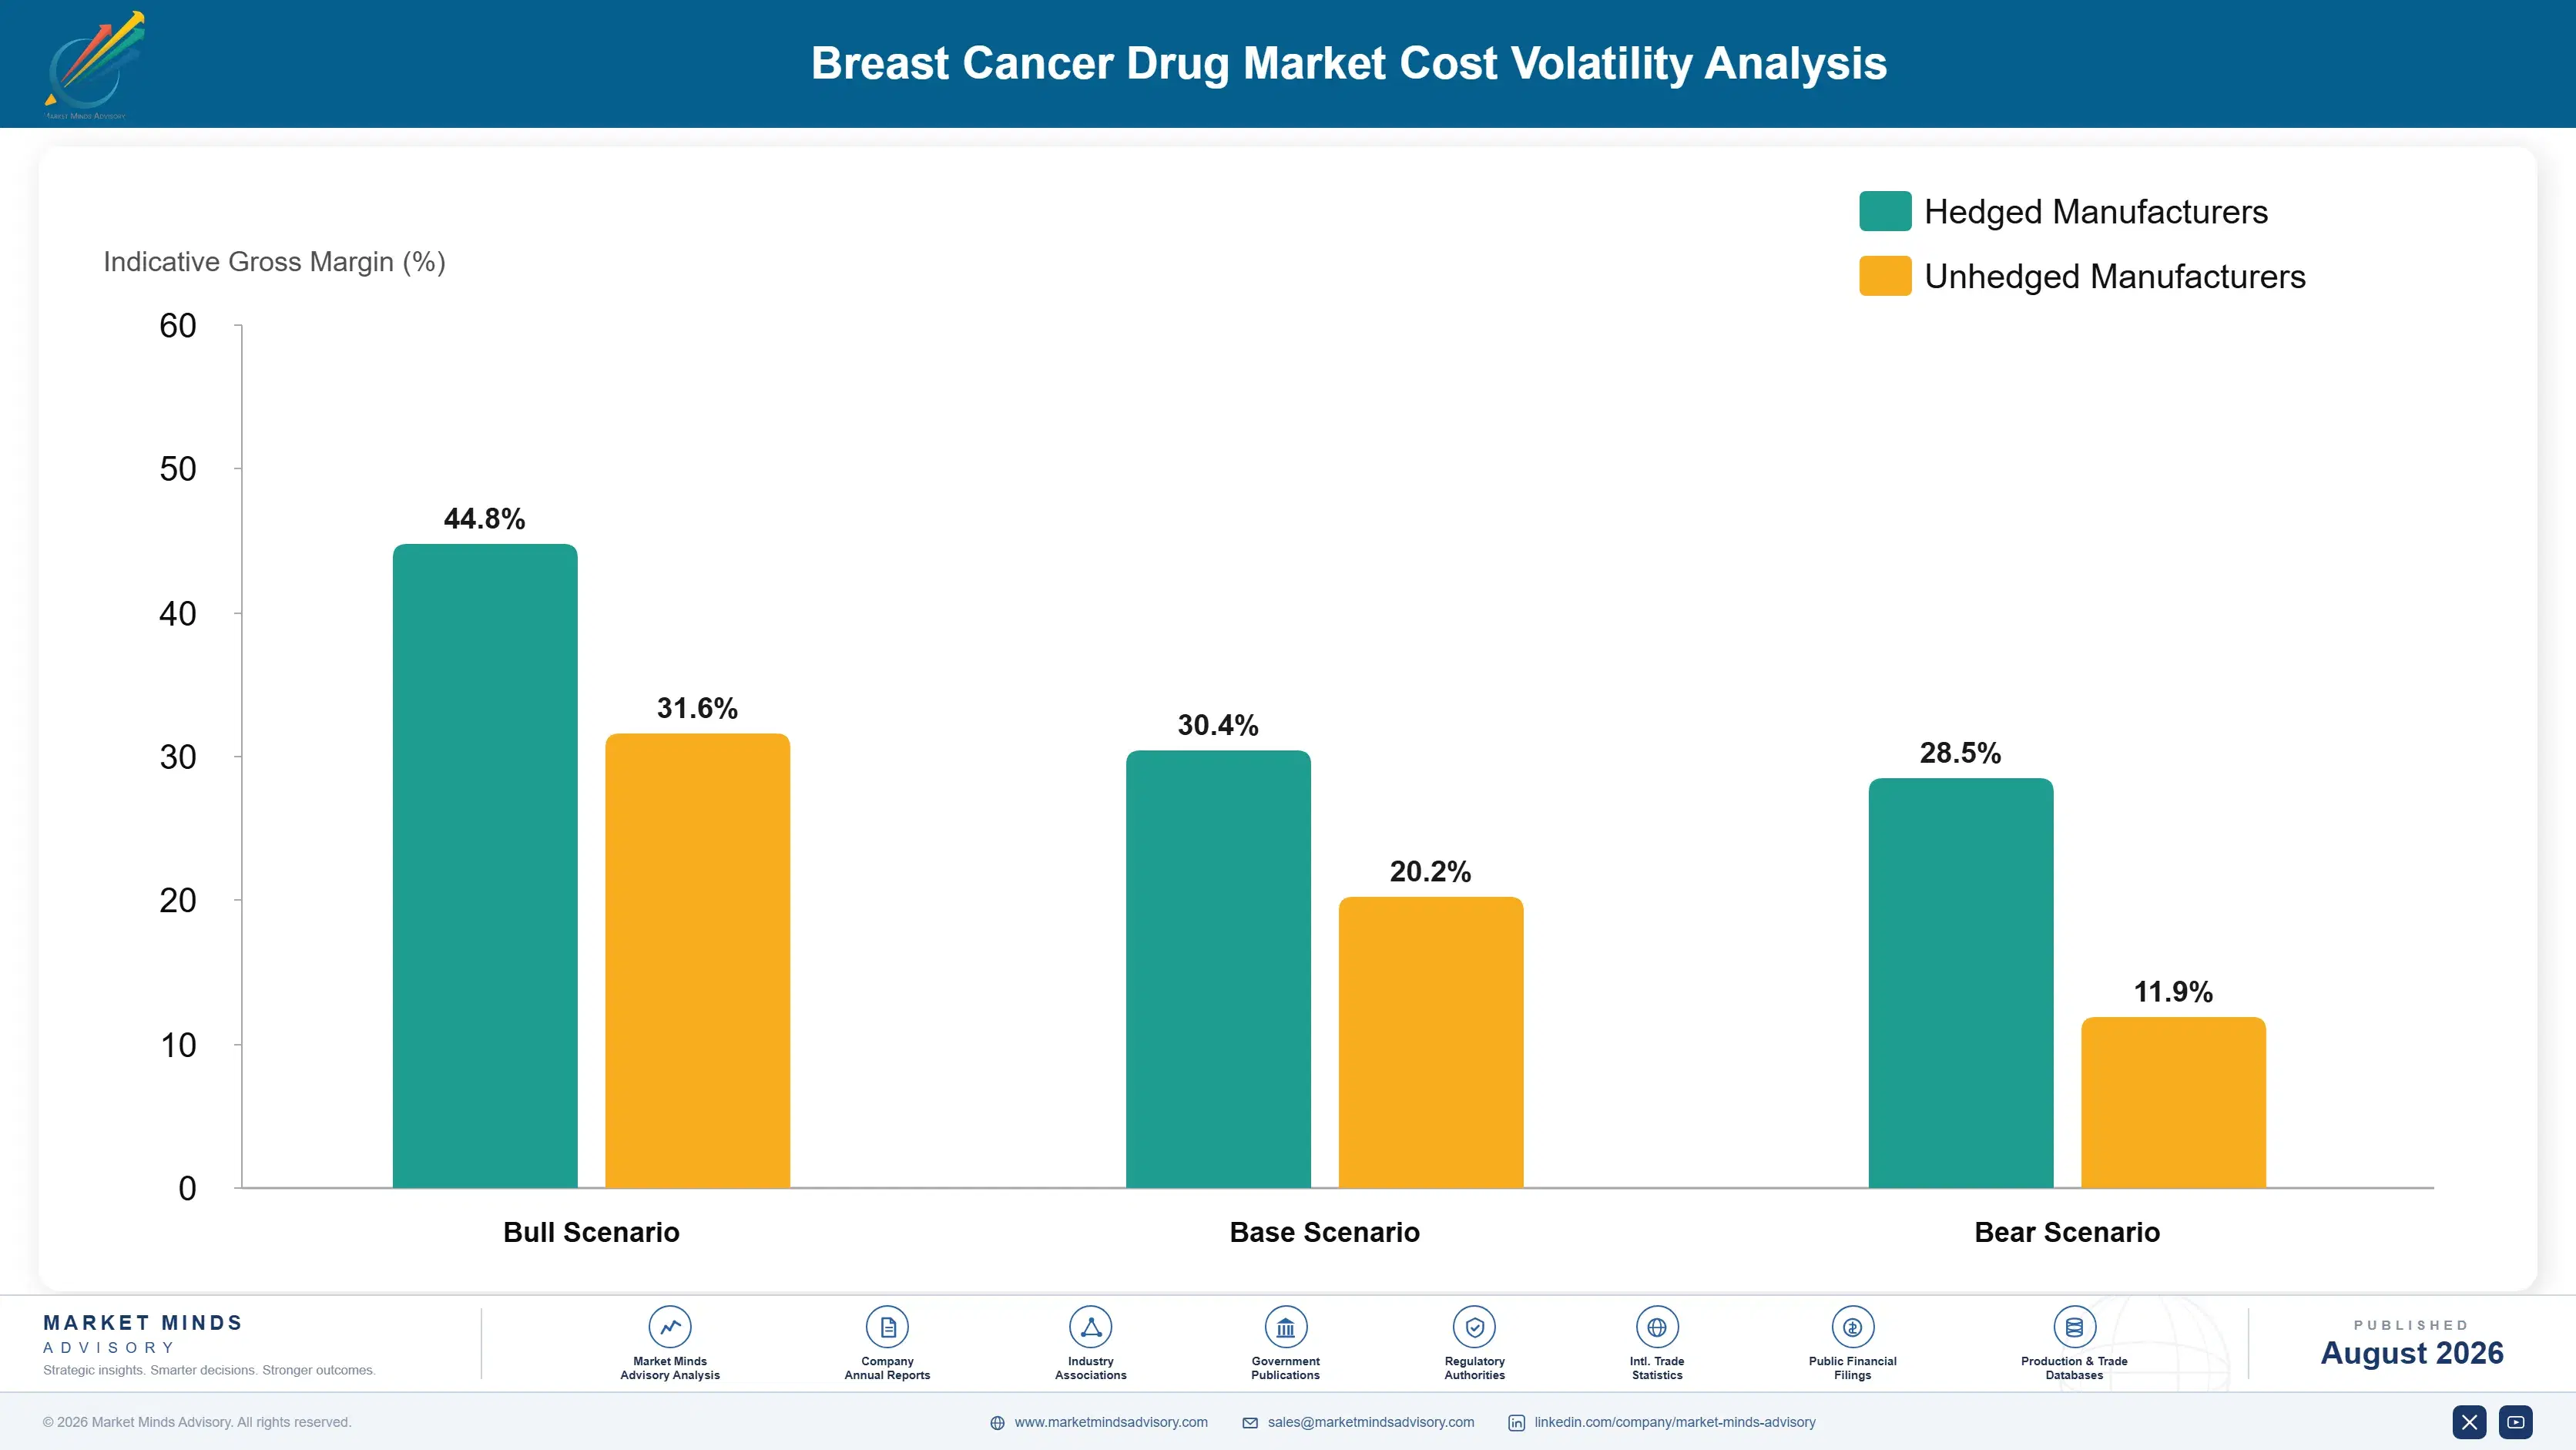
Conjugation Chemistry and Biologic Input Exposure

Monoclonal antibody production, cytotoxic payload synthesis, and conjugation chemistry together make up roughly 56% of production cost, with antibody production sourced through a concentrated group of specialty biologics manufacturers companies cannot meaningfully influence on their own, and payload synthesis sourced through specialty chemistry suppliers subject to their own certification requirements, capacity limits, and periodic quality audits.
Monoclonal antibody and payload input costs rose considerably through 2024, with published industry data and company annual reports showing sustained upward pricing pressure tied to constrained specialty biologics manufacturing capacity and rising global oncology demand competing directly with companies for available production capacity across every major producing region. Several companies absorbed a meaningful share of the cost increase rather than risk losing fixed-price payer supply agreements already signed before the volatility began that year, eroding margin more than budgeted.

Larger diversified pharma companies with greater manufacturing scale negotiate more favorable antibody and payload economics than smaller specialist biotechs, who typically lack comparable volume leverage with upstream biologics and chemistry suppliers across most specialty markets. That gap widens further for companies dependent on a small number of qualified conjugation sources, since switching sources requires renewed qualification testing taking several months to complete.
breast-cancer-drug-market-cost-volatility-analysis-1787297953928

Qualify Multiple Antibody and Payload Suppliers

Companies qualifying two or more sources for critical antibody and payload components reduce single-source dependency risk considerably, though the qualification process itself requires meaningful upfront testing investment and lead time before a second source becomes usable in volume production supporting validated regulatory performance requirements across every product family and payer contract currently active under development.

Negotiate Multi-Year Index-Linked Supply Contracts

Companies negotiating multi-year antibody and payload supply contracts with indexed pricing formulas protect margin predictability better than those repricing purchases annually, a structure that requires accepting somewhat higher baseline pricing in exchange for materially reduced volatility exposure across the full contract term negotiated with each upstream supplier directly and renewed periodically as demand shifts over time.

Build Cost Escalation Clauses Into Payer Agreements

Companies building input cost escalation clauses directly into multi-year payer supply agreements pass volatility through to buyers rather than absorbing it against thin launch margin, a structure that protects profitability during price spikes though it requires negotiating leverage smaller companies often lack against larger payer systems and group purchasing organisations with considerably more purchasing scale.

Portfolio Architecture for Margin Defence

The portfolio splits into three tiers with sharply different economics. Traditional chemotherapy and generic hormone therapy form the volume tier, competing largely on price and payer tender terms with margin set by manufacturing scale and distribution efficiency. Antibody-drug conjugates and checkpoint inhibitors earn considerably more because biologics manufacturing complexity and combination trial requirements both resist the commoditisation pressure hitting generic products. Combination-part
The tension runs between winning generic and chemotherapy volume on price and payer access, and building conjugate or checkpoint capability that protects margin over the long run. A company chasing every available generic tender eventually gets squeezed as regional producers undercut aggressively on price, yet building next-generation capability requires clinical investment thin-margin generic sales rarely fund adequately on their own.

High-value pools concentrate where biologics manufacturing complexity, combination trial depth, or payer-partnership capability limit competition: antibody-drug conjugates serving HER2-low populations, checkpoint inhibitors serving triple-negative patients, and outcomes-partnership-backed relationships spanning multiple years of recurring reimbursement. Traditional chemotherapy sits at the other end, competing almost entirely on price and payer access.

Volume / Commodity-Adjacent Tier

Traditional chemotherapy and generic hormone therapy for mainstream treatment protocols, competing largely on price and payer access with thin, scale-dependent margin across most tenders and formulary negotiations reviewed each cycle.
Gross Margin: 22-36%

Premium / Certified Tier

Antibody-drug conjugates and checkpoint inhibitors with validated combination trial documentation serving oncology and payer customers, priced for biologics complexity and documented survival performance built over years of clinical testing and regulatory engagement.
Gross Margin: 40-56%

Sustainability / Regulatory / Next-Generation Tier

Combination-partnership-integrated platforms with connected outcomes documentation, priced on clinical evidence and access value that extends well beyond raw treatment economics and standard pricing alone across most payer segments and provider relationships.
Gross Margin: 44-60%
breast-cancer-drug-market-portfolio-architecture-1787297954424

High-value Sub-segments and Strategic Watch-out

Antibody-Drug Conjugates

High value and high growth at 16.8%, the fastest category, as oncologists chase deeper response rates that hormone therapy and traditional chemotherapy alone cannot reliably deliver across nearly every major producing region tracked closely throughout this entire report and the coming forecast decade ahead and beyond.
Gross Margin: 40-56%

Immune Checkpoint Inhibitors

High value with strong growth at 13.5%, driven by expanding combination protocols pairing checkpoint inhibitors with chemotherapy or antibody-drug conjugates ahead of standalone use across most regulated categories tracked carefully in this full report across the coming decade and its underlying survey data and interviews.
Gross Margin: 40-56%

CDK4/6 Inhibitors

The volume core by prescribing count, growing near 8.4% as standard hormone receptor-positive combination applications remain the largest category even as growth concentrates in conjugate and checkpoint formats elsewhere across the broader portfolio, margin mix, and evolving supplier catalog structure tracked closely over time and cycles.
Gross Margin: 22-36%

Traditional Chemotherapy

The strategic watch-out, growing slowest at roughly 3.6% and facing steady commoditisation as standard cytotoxic applications become a bundled combination component rather than a genuinely differentiated standalone purchase decision across most regional tenders reviewed carefully throughout this full analysis and its underlying survey data today.
Gross Margin: 18-30%

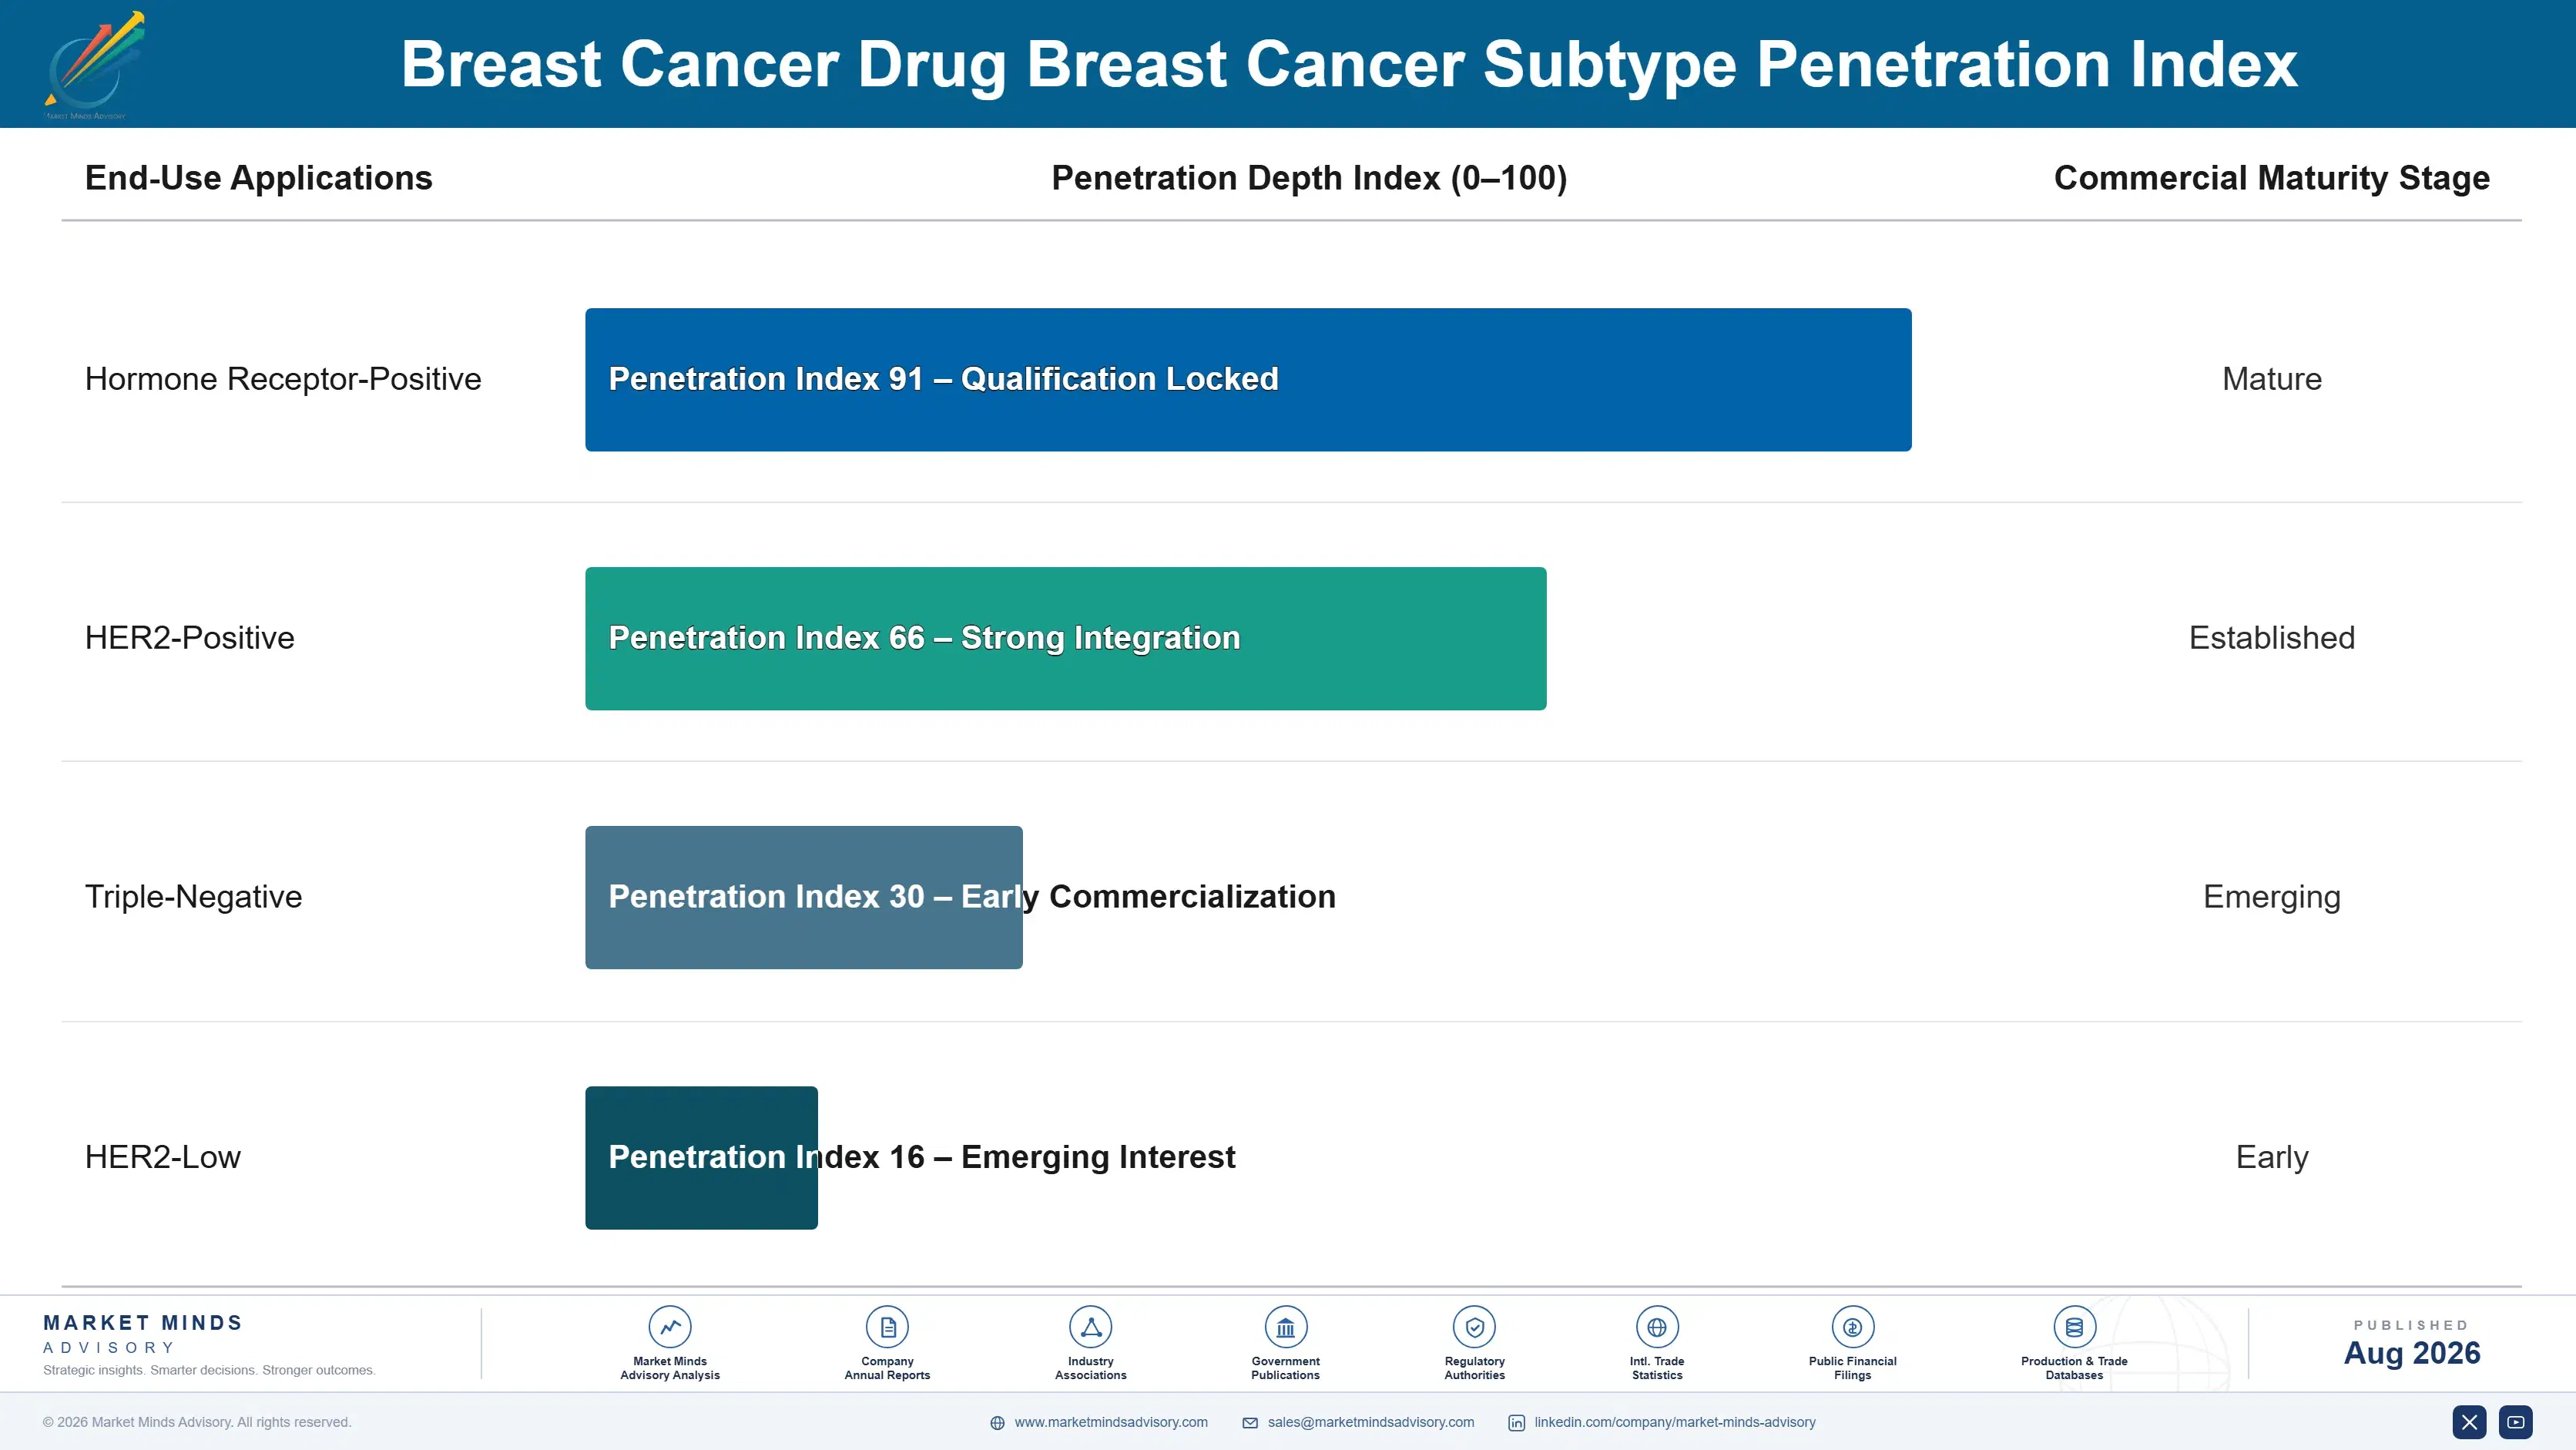
Recurring Prescribing Revenue Through Treatment Cycles

Drug revenue increasingly behaves like an annuity layered on top of the original formulary listing rather than a one-time transaction. Every combination arm addition, label expansion, and reimbursement renewal extends the payer relationship well beyond initial launch, and companies with validated combination data capture follow-on prescribing with lower friction than switching to an unproven alternative therapy would require of a demanding oncologist.
Adoption depth varies considerably by end-use vertical. Large academic cancer centres have the deepest, most established combination adoption given research funding and clinical trial participation that make unconverted protocols extremely costly in reputational terms, while community oncology practices are earlier in adopting comparable combination-documented regimens and still weighing reimbursement cost against demonstrated outcome improvement. Specialty pharmacy networks sit differently, adopting premium conjugate platforms quickly given the recurring, high-value nature of oncology dispensing.

A generational shift is underway in oncology prescribing teams across most major markets. Younger oncologists increasingly treat combination trial data and outcomes documentation as baseline prescribing requirements rather than differentiators, a shift that is compressing the commercial advantage early-adopting companies once held over competitors still running largely monotherapy-focused product catalogs carried over from earlier development decades.
breast-cancer-drug-market-end-use-penetration-index-1787297954913

Where Companies Should Focus Next

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / COMBINATION PARTNERSHIP STRATEGY

Partnering with checkpoint leaders separates leaders from challengers

Companies navigating intensifying payer pricing pressure increasingly prefer partnering with established checkpoint inhibitor franchises rather than pursuing standalone monotherapy approval, since that pairing reduces commercial risk considerably compared with proving efficacy alone against a moving competitive bar. That structure builds commercial relationships considerably stickier than standalone launches, since switching partners mid-programme would force developers to restart trial design entirely. Companies without comparable partnerships remain exposed as payers increasingly expect combination data rather than monotherapy alone, and that expectation only keeps hardening each funding cycle.
02 / CONJUGATION MANUFACTURING EXPANSION

Dedicated conjugation capacity beats commodity chemotherapy volume

Antibody-drug conjugate demand represents a considerably more defensible margin pool than standard chemotherapy demand alone could ever support, since conjugate pricing commands roughly 5 times standard chemotherapy per-cycle value across most major producing markets tracked in this report. Companies expanding dedicated conjugation manufacturing capacity capture launch contracts that generalist competitors increasingly cannot match, generating meaningful revenue through phased capacity conversion unfolding across multiple budget cycles. Building this capacity should rank above chasing standard chemotherapy tenders exclusively across every major treatment protocol.
03 / PAYER OUTCOMES CONTRACTING

Direct outcomes contracts beat one-off list-price negotiations

Payers increasingly consolidate reimbursement decisions through outcomes-based contracting, and companies who maintain direct relationships built on documented clinical outcomes capture recurring formulary revenue considerably more predictable than one-off list-price negotiations alone ever provide across a comparable regional footprint. That relationship also generates early visibility into upcoming formulary renewal cycles before competitors even learn a negotiation is coming their way. Building this relationship depth should rank above chasing every available list-price negotiation across the wider payer market and its unpredictable funding cycles.
04 / CHINESE MARKET EXPANSION

Early presence in Chinese reimbursement expansion compounds over time

Chinese prescribing demand is scaling quickly as domestic hospital systems expand reimbursement coverage requiring validated pricing negotiation meeting national procurement standards across most major provincial hospital networks and their satellite clinics. Companies establishing local regulatory and commercial support presence early are winning multi-year reimbursement listings before competitors relying solely on import channels can match local pricing and access speed. That early position compounds considerably as China's oncology sector keeps climbing through the remainder of the decade, rewarding early movers meaningfully over slower-moving competitors.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Breast Cancer Drug Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Breast Cancer Drug Exposure Evaluation 2025-26
CLIENT PROFILE
A mid-size oncology biotech advancing a phase two antibody-drug conjugate programme across two breast cancer indications engaged MMA while evaluating whether to pursue standalone development or seek a combination partnership with an established checkpoint inhibitor franchise ahead of pivotal trial design decisions spanning the following two fiscal years. The client reported limited internal payer contracting capacity for navigating outcomes-based negotiations independently (client-reported, unverified by MMA).
STRATEGIC CHALLENGE
Leadership needed to decide whether partnering with a large pharmaceutical company would accelerate pivotal trial design and payer access faster than continuing standalone development, while also weighing which potential partners offered manufacturing support flexible enough to sequence two indications without disrupting ongoing preclinical commitments already under signed academic collaboration agreements.
MMA APPROACH
MMA benchmarked five qualified pharmaceutical partners on combination trial track record, manufacturing capacity flexibility, and total deal economics against the client's two-indication development plan in considerable detail. We modelled a phased partnership sequence prioritising the highest-priority indication first across the pipeline. We then assessed each partner's payer contracting capacity given the client's aggressive trial timeline.
KEY FINDINGS
  1. Partnering on the highest-priority indication first would capture roughly 47% of projected payer access acceleration within the programme's first eighteen months of operation.
  2. Two of five candidate partners could not guarantee manufacturing capacity meeting the client's aggressive trial timeline across both indications reliably or within budget.
  3. A combination partnership would reduce projected pivotal trial failure risk by an estimated 23% once fully operational across the entire partnered programme segment.
  4. The leading partner's payer contracting team would reduce the client's own negotiation preparation burden by several months per filing cycle overall, freeing internal staff time.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (0 to 9 months): Finalise partner selection and structure combination terms for the highest-priority indication identified across both programmes. Phase 2: Phase 2 (9 to 18 months): Complete second-indication partnership terms, sequenced carefully around ongoing preclinical commitments across both indications and timelines. Phase 3: Phase 3 (18 to 30 months): Complete pivotal trial design and renegotiate payer contracting terms under the newly established partnership structure.
OUTCOME
The biotech completed priority indication partnership negotiations within the targeted eleven-month window and reported payer access acceleration tracking close to the modelled estimate across the partnered programme segment. Projected pivotal trial failure risk also declined measurably under the combination structure, though full thirty-month transition figures were not yet available at the time of reporting (client-reported, unverified by MMA).

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Breast Cancer Drug Market?

The global breast cancer drug market is valued at USD 38.0 billion in 2025, covering hormone therapy, CDK4/6 inhibitors, HER2-targeted therapies, antibody-drug conjugates, and immune checkpoint inhibitors.

How large will the Breast Cancer Drug Market be by 2036?

The market is projected to reach USD 106.27 billion by 2036, roughly 2.55 times its 2026 value of USD 41.72 billion, driven by antibody-drug conjugate adoption and combination regimens.

What is the CAGR for the Breast Cancer Drug Market 2026 to 2036?

The base case CAGR is 9.8%, with a bull case of 11.0% if combination data reads out favorably across earlier treatment lines sooner, and a bear case of 8.6% under tighter payer pricing pressure.

Which segment is growing fastest?

Antibody-Drug Conjugates lead at a 16.8% CAGR, roughly 1.71 times the overall market rate, as oncologists chase deeper response rates beyond hormone therapy and traditional chemotherapy.

Who are the major companies in the Breast Cancer Drug Market?

Roche, AstraZeneca, Novartis, Pfizer, and Gilead Sciences lead the market, together holding roughly 52% of breast cancer drug revenue generated worldwide each year currently and reliably.

Which country is growing fastest?

China leads at a 13.2% CAGR as expanding national reimbursement drug list coverage and domestic biotech production pull volume toward local prescribing across major provinces.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Drug Mechanism Class

  • Hormone Therapy
  • CDK4/6 Inhibitors
  • HER2-Targeted Therapies
  • Antibody-Drug Conjugates
  • Immune Checkpoint Inhibitors
  • Traditional Chemotherapy

By Breast Cancer Subtype

  • Hormone Receptor-Positive
  • HER2-Positive
  • Triple-Negative
  • HER2-Low

By Commercial Dimension

  • Direct Hospital Sales
  • Specialty Pharmacy Channels
  • Payer Formulary Contracts
  • Combination Partnership Deals

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The breast cancer drug market covers hormone therapy, CDK4/6 inhibitors, HER2-targeted therapies, antibody-drug conjugates, immune checkpoint inhibitors, and traditional chemotherapy drugs used in breast cancer treatment. It excludes diagnostic testing, radiation therapy, surgical intervention, and supportive care medications administered alongside primary treatment.
Quantitative Units
USD billions (current prices); annual prescribing volume where applicable
Segmentation Dimensions
By Drug Mechanism Class; By Breast Cancer Subtype; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Switzerland, Netherlands, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Italy, Spain, Sweden, Israel, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Roche Holding AG, AstraZeneca plc, Novartis AG, Pfizer Inc., Gilead Sciences, Inc., Daiichi Sankyo Company, Limited, Eli Lilly and Company, Merck & Co., Inc., Bristol Myers Squibb Company, Seagen Inc., Puma Biotechnology, Inc., Sanofi S.A., Menarini Group, Zymeworks Inc., Byondis B.V., Innovent Biologics, Inc., Jiangsu Hengrui Medicine Co., Ltd., BeiGene, Ltd., Amgen Inc., Sun Pharmaceutical Industries Ltd.
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-146
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Breast Cancer Drug Market Report (2026 to 2036).

The full report delivers granular sizing and forecasts across all six drug mechanism segments and seven global regions through 2036. It profiles twenty companies across large diversified pharma companies and specialist oncology biotechs, benchmarking combination trial depth, manufacturing scalability, and regulatory alignment speed in considerable detail. Analysts detail conjugation chemistry cost exposure, portfolio margin tiers, and demand architecture by end-use vertical across major global markets and their evolving reimbursement environments. Buyers receive both the standalone report and full access to underlying data tables supporting every figure and forecast presented throughout.
Six-segment drug mechanism sizing and full forecasts
Seven-region global market share breakdown detail
Twenty-company detailed competitive profile benchmarking analysis
Conjugation chemistry cost exposure mitigation analysis
Portfolio margin tier benchmarking economics framework
Anonymised client engagement outcome case study

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts