Market Minds Advisory
Andersen-Tawil Syndrome Treatment Market

Andersen-Tawil Syndrome Treatment Market: Channelopathy Management and Genetic Diagnostic Expansion

Rare disease genetics centers are converting Andersen-Tawil Syndrome from a symptom-managed cardiac and neuromuscular curiosity into a genetically confirmed, protocol-driven treatment pathway as KCNJ2 testing access expands across specialized arrhythmia referral networks worldwide.

Lead Analyst

Alice Ballenger

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$0.3BMarket Size 2025
2036 FORECAST VALUE$1.5BBase Case , 2026 to 2036
CAGR 2026 TO 203613.8 %Bull 15.1% / Bear 12.5%
INCREMENTAL OPPORTUNITY$1.1BNet 10- year value creation
EXPANSION MULTIPLE3.75x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Rare disease genetics centers worldwide are converting Andersen-Tawil Syndrome from a symptom-managed curiosity into a genetically confirmed treatment pathway as KCNJ2 testing access expands rapidly. Confirmed diagnosis is now the trigger for structured antiarrhythmic and device therapy planning, not an afterthought left to trial and error.
North America anchors global demand, home to the largest concentration of diagnosed patients and specialized channelopathy referral centers, even as Medtronic plc, Abbott Laboratories, and Boston Scientific Corporation compete for implantable device contracts alongside generic antiarrhythmic suppliers across major referral networks. Emerging gene and RNA-targeted therapies are the fastest-growing category, still early-stage relative to established beta-blocker and antiarrhythmic regimens but increasingly the focus of specialist pipeline investment and academic research funding worldwide.
Five suppliers, Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Teva Pharmaceutical Industries, and Viatris Inc, hold roughly 42 percent of global treatment revenue, a concentration built on device manufacturing scale and generic distribution reach that smaller specialty biotechs cannot easily match. Expanding genetic testing infrastructure and growing clinical recognition of KCNJ2 mutations are pulling diagnosis, and treatment initiation, earlier into the patient journey than history would predict.
Market Definition
The Andersen-Tawil Syndrome treatment market covers beta-blocker therapy, potassium channel modulator therapy, antiarrhythmic agents, implantable cardiac device therapy, genetic testing and diagnostic confirmation services, and emerging gene and RNA-targeted therapies used to manage the periodic paralysis, ventricular arrhythmia, and cardiac conduction features of Andersen-Tawil Syndrome caused by KCNJ2 gene mutations. It excludes treatment for other periodic paralysis syndromes, congenital long QT syndrome not linked to KCNJ2 mutation, and general cardiac arrhythmia management unrelated to this specific channelopathy.
Base Year Value
$0.3B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
13.8% base case. Bull 15.1%. Bear 12.5%.
Fastest Growth Segment
Emerging Gene and RNA-Targeted Therapies: 22.4% CAGR
Fastest Growth Country
United States: 13.3% CAGR
Fastest Growth Region
South Asia and Pacific: 15.8% CAGR
Largest Region
North America: 30% of 2025 global value
Market Leaders
Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Teva Pharmaceutical Industries, Viatris Inc. Source: MMA Analysis based on company annual reports and investor filings.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

Andersen-Tawil Syndrome Treatment Market Forecast Scenarios

andersen-tawil-syndrome-treatment-market-2-size-forecast-scenario-1787303120334
Diagnosis and treatment volumes for Andersen-Tawil Syndrome grew steadily from 2020 through 2025 as genetic testing panels increasingly included KCNJ2 screening for patients presenting with unexplained periodic paralysis or ventricular arrhythmia across major healthcare systems. The segment grew at roughly a 12.8 percent historical compound rate as specialized reference centers expanded diagnostic throughput nationwide, aided by growing physician awareness of the syndrome's distinctive clinical presentation.
MMA's base case assumes 13.8 percent compound growth through 2036, anchored in three mechanisms. First, expanding genetic testing panel adoption is pulling diagnosis forward across a growing number of cardiology and neuromuscular referral centers worldwide. Second, rising clinical recognition of KCNJ2-linked presentations is reducing the historical multi-year diagnostic delay that many patients previously experienced. Third, emerging gene and RNA-targeted therapy development is drawing specialty biotech investment into a category previously served only by repurposed generic antiarrhythmics.
A bull scenario near 15.1 percent follows if an emerging targeted therapy receives regulatory clearance ahead of current development timelines across major reference markets. The bear case near 12.5 percent materialises if genetic testing reimbursement policy tightens enough that smaller regional centers delay panel adoption, extending the diagnostic gap that has historically constrained treatment initiation for undiagnosed patients worldwide.

Genetic Confirmation Reshapes Treatment Protocol Design

Andersen-Tawil Syndrome has moved from a diagnosis of exclusion, reached only after years of unexplained periodic paralysis episodes and unremarkable standard cardiac workups, into a genetically confirmable condition that specialized centers can identify within a single testing cycle. That shift is reshaping how referring physicians plan the entire treatment pathway, since a confirmed KCNJ2 mutation now triggers a specific antiarrhythmic and device therapy protocol rather than a trial-and-error
MARKET CONCENTRATION42%Five suppliers hold a meaningful combined global share
AVERAGE ANNUAL TREATMENT COST$34,000Reflects combined pharmacological and device-based patient management overall
NORTH AMERICA PATIENT SHARE30%Largest concentration of diagnosed patients and referral centers
GENETIC TESTING COST SHARE22%Share of total spend tied to diagnostic confirmation services
DEVICE THERAPY ADOPTION RATE38%Share of diagnosed patients receiving implantable cardiac devices
DIAGNOSTIC DELAY REDUCTION3.5 yearsAverage shortening of time to confirmed genetic diagnosis
Commercial activity concentrates in antiarrhythmic pharmacotherapy and implantable device placement, where manufacturing scale and cardiologist relationship depth give the five largest suppliers durable advantages. Genetic testing and diagnostic confirmation services remain a smaller but fast-scaling category, increasingly ordered directly by cardiac genetics specialists. Emerging gene and RNA-targeted therapies round out demand across the most severe, treatment-resistant patient subset.
The next decade will be shaped less by incremental antiarrhythmic reformulation than by how fast diagnostic infrastructure and specialist referral networks can shorten the time between symptom onset and confirmed genetic diagnosis. Suppliers that can bundle testing, pharmacotherapy, and device support into a single specialist-coordinated pathway capture a disproportionate share of new referral center relationships worldwide.
"Ten years ago most of these patients were misdiagnosed as having a seizure disorder. Now a single genetic panel gets them into the right treatment protocol within weeks."
Director, Rare Cardiac Channelopathy Practice · MMA Rare Channelopathy Therapeut

Market Trends

KCNJ2 Genetic Panel Adoption Accelerates Early Diagnosis

Cardiac genetics centers increasingly include KCNJ2 mutation screening in standard periodic paralysis and unexplained ventricular arrhythmia panels, converting a diagnosis that once required years of specialist referral into a confirmable result within a single testing cycle. Centers with the broadest panel adoption report that genetic confirmation now happens during initial cardiac genetics consultation rather than after multiple inconclusive standard workups. Invitae Corporation and Blueprint Genetics both report that Andersen-Tawil-specific panel orders have grown meaningfully faster than general arrhythmia panel orders across the same referral networks over the past several years.
Market Impact: Sustains a 46% diagnosis-linked dem
Implantable Device Guidelines Expand Eligible Patient Population

Cardiology societies are increasingly recommending implantable cardiac device evaluation for genetically confirmed Andersen-Tawil patients with documented ventricular arrhythmia history, extending device therapy demand into a patient population that previously relied on pharmacotherapy alone until a cardiac event forced escalation to more invasive care. Referral centers report that device evaluation is now a standard step in the confirmed-diagnosis pathway rather than a late-stage intervention reserved for the most severe presentations. Medtronic plc and Abbott Laboratories both report that channelopathy-linked device orders are a meaningful and growing share of their specialty cardiac rhythm management business today.
Market Impact: Adds 9pp to addressable reimbursed

Market Opportunities and Growth Drivers

Expanding Genetic Testing Infrastructure Sustains Diagnosis Growth

Genetic testing infrastructure investment across major healthcare systems is sustaining diagnosis growth regardless of broader healthcare capital spending cycles, since every patient presenting with unexplained periodic paralysis or ventricular arrhythmia symptoms represents a potential KCNJ2 testing candidate independent of overall market sentiment or budget conditions. Reference centers with dedicated cardiac genetics programmes report that testing volume growth has remained steady even during periods of broader healthcare budget tightening. This diagnosis-driven demand gives suppliers unusually predictable baseline revenue compared with other rare disease categories that depend more heavily on discretionary specialist referral timing.
Market Impact: Limits trial-ready cohorts to rough

Rare Disease Reimbursement Policy Expansion Broadens Access

Healthcare payers across major markets continue to expand reimbursement coverage for rare disease genetic testing and specialty pharmacotherapy, and expanded coverage increasingly makes confirmed diagnosis and structured treatment accessible to patient populations that historically faced significant cost barriers. Payers implementing new rare disease coverage policies report that treatment specification decisions now weigh long-term cost offset from avoided misdiagnosis and repeated inconclusive testing as heavily as upfront diagnostic cost. This coverage-driven expansion is pulling smaller regional cardiology practices toward genetic referral earlier than historical patterns would have predicted across the broader system.
Market Impact: Delays treatment by 3-5 years

Market Restraints and Challenges

Small Diagnosed Population Limits Clinical Trial Recruitment

Andersen-Tawil Syndrome's extremely low prevalence represents the dominant constraint on therapeutic development, and the root cause is straightforward: a globally small diagnosed patient pool makes it difficult for specialty biotechs to recruit the trial cohorts that regulatory approval pathways typically require for novel targeted therapies. That constraint slows how quickly gene and RNA-targeted therapy candidates can progress through clinical development relative to more prevalent channelopathies, periodically forcing developers to rely on international multi-site recruitment strategies. Sponsors including Milestone Pharmaceuticals are mitigating the gap by pooling recruitment across multiple national rare disease registries.
Market Impact: Cuts diagnostic delay by 3.5 years

Diagnostic Misclassification Slows Overall Treatment Initiation

Andersen-Tawil Syndrome's overlapping periodic paralysis and cardiac symptoms are frequently misclassified as other channelopathies or general arrhythmia disorders, and the root cause is a genuine clinical constraint: the syndrome's dysmorphic features are subtle enough that non-specialist physicians often miss the referral trigger for genetic testing entirely. That misclassification delays treatment initiation by years in many diagnosed cases, periodically forcing patients through avoidable standard antiarrhythmic trials before genetic confirmation redirects their care. Centogene N.V. and other diagnostic providers are mitigating the constraint by expanding physician education programmes targeting general cardiology practices.
Market Impact: Expands device eligibility by rough
3 additional market trends, 4 additional growth drivers, and 2 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

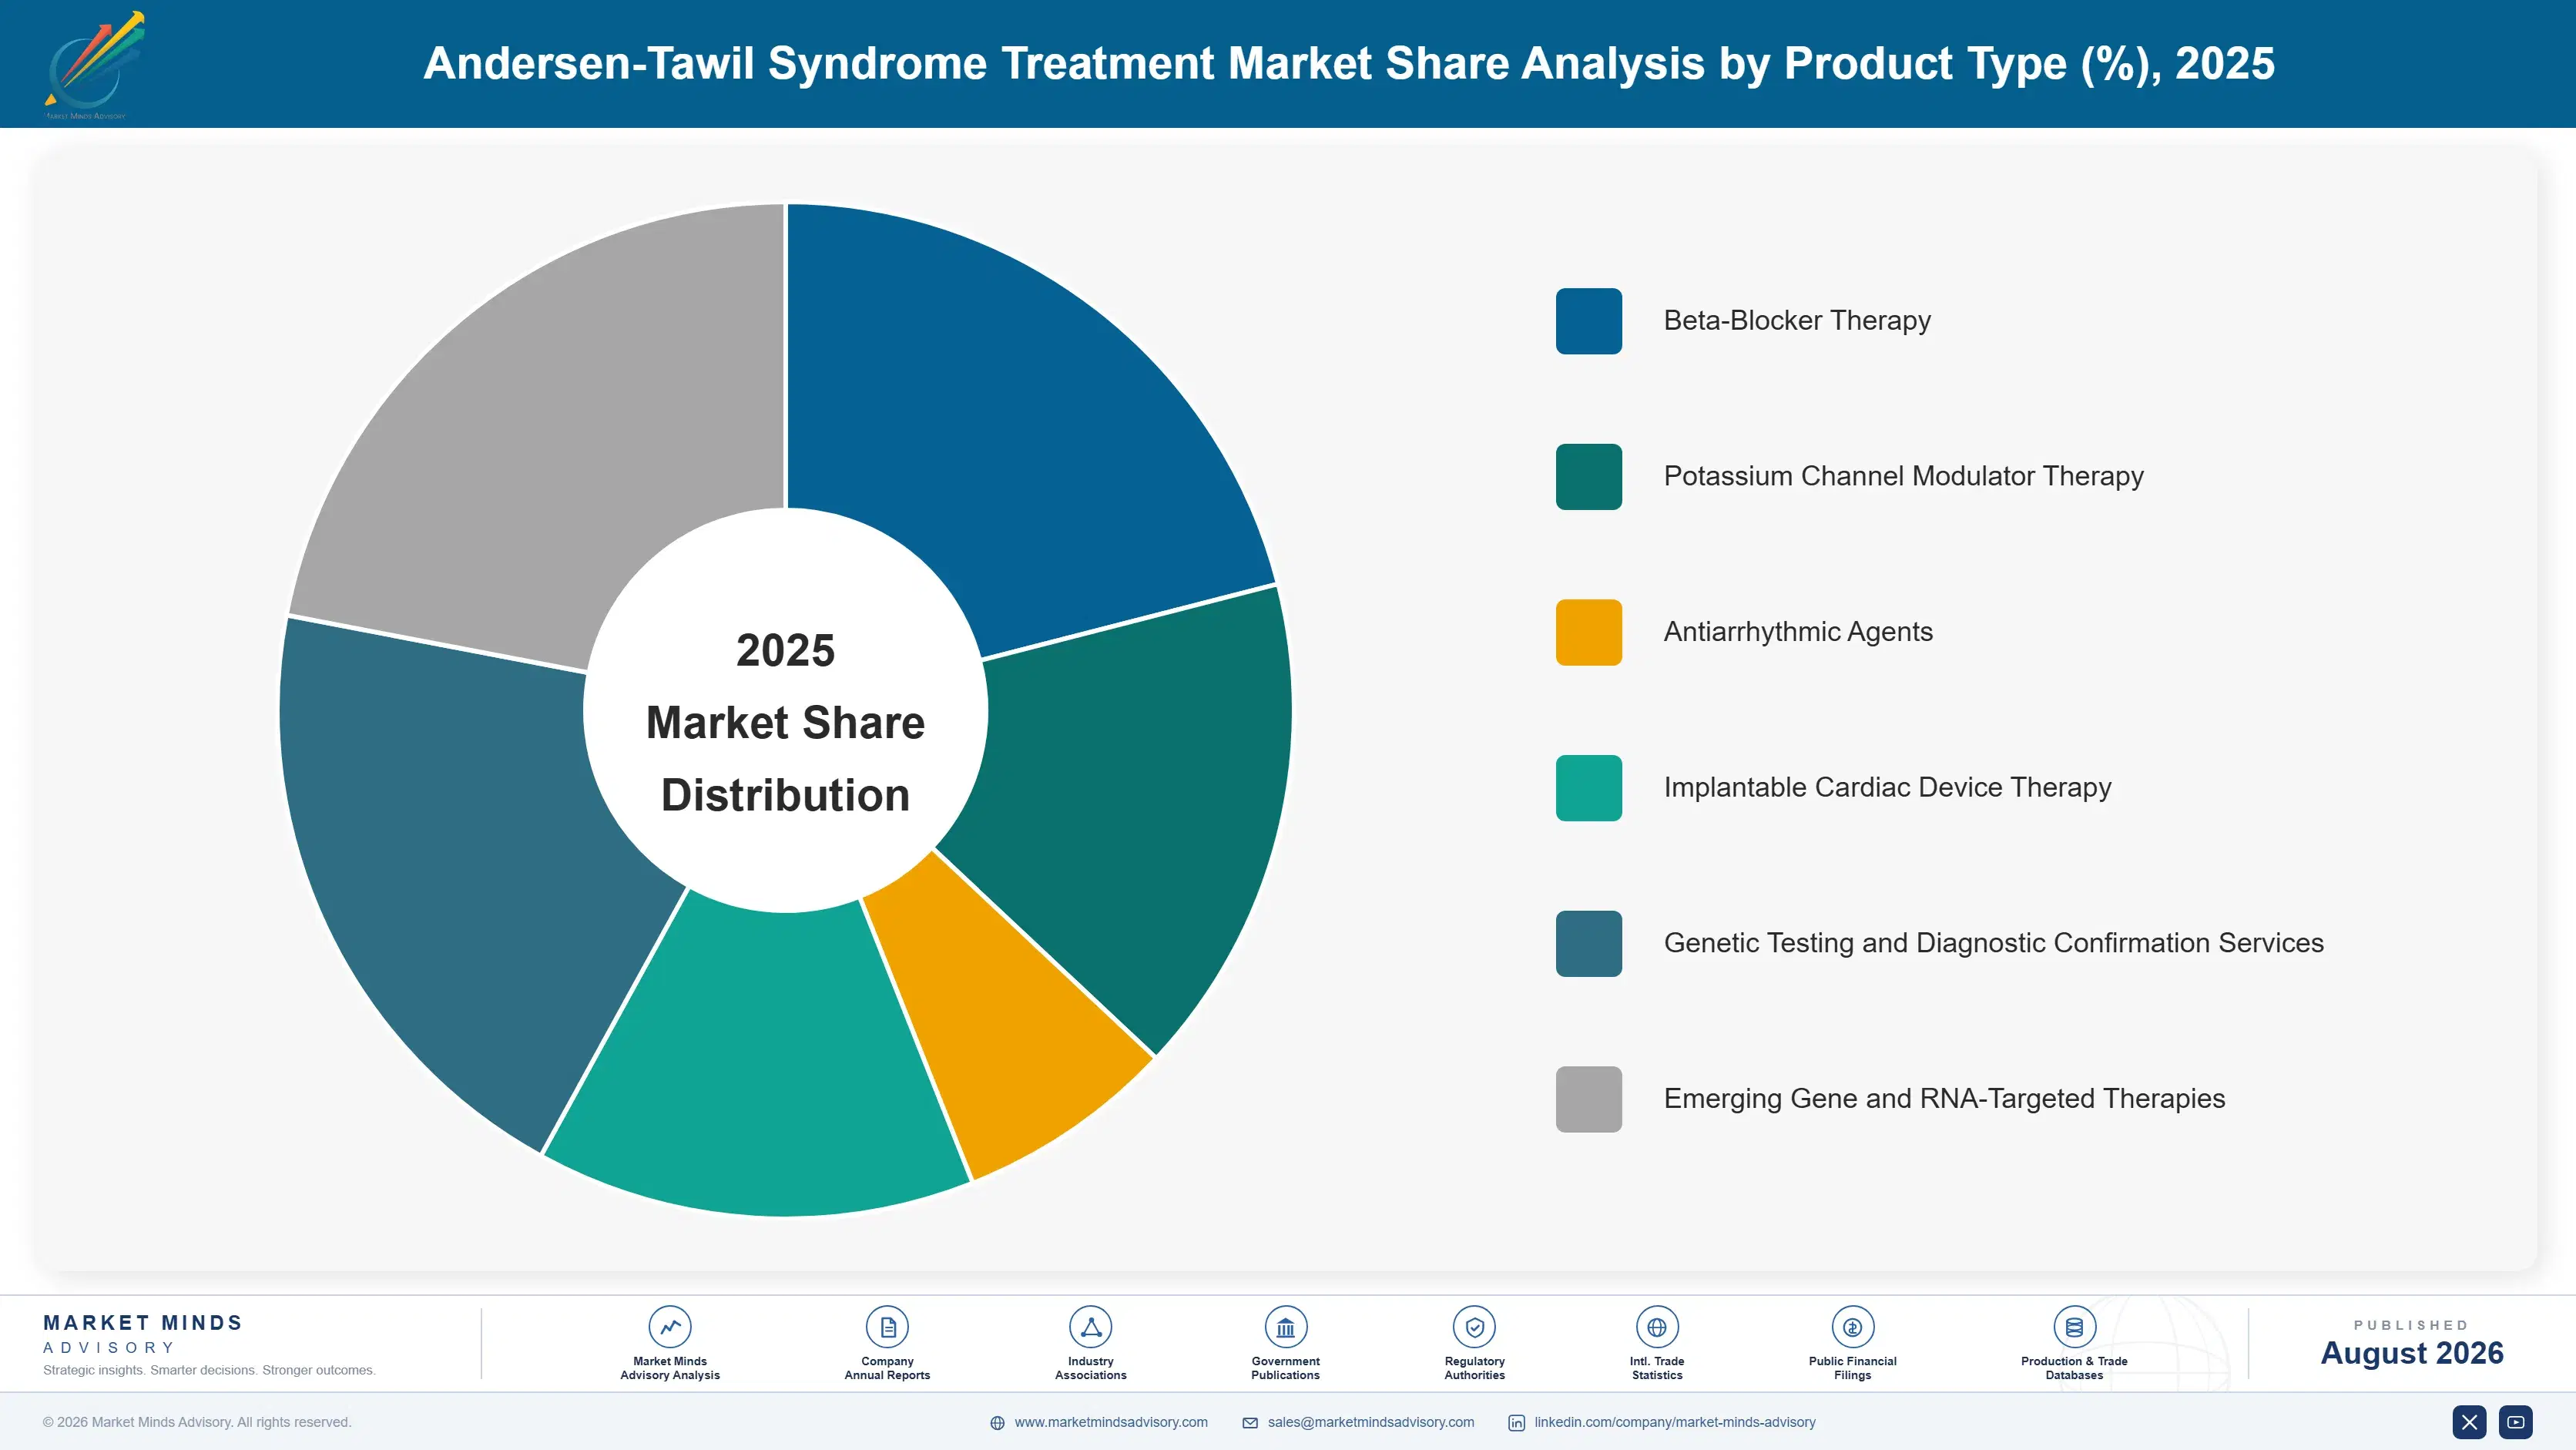
MMA segments the Andersen-Tawil Syndrome treatment market by treatment modality, the classification cardiac genetics specialists and referring cardiologists actually specify and procure against across every major clinical setting worldwide today. Six categories cover the addressable market, spanning pharmacotherapy, implantable device intervention, and diagnostic confirmation services across every major referral pathway and specialist network today.
andersen-tawil-syndrome-treatment-market-2-market-share-analysis-1787303121269

Emerging Gene and RNA-Targeted Therapies

Emerging gene and RNA-targeted therapies are growing fastest because they directly address the underlying KCNJ2 channel dysfunction that beta-blockers and standard antiarrhythmics can only partially manage through symptom control rather than root-cause correction. Milestone Pharmaceuticals and Acesion Pharma both lead early development in this segment given their channelopathy-specific pipeline focus and the specialist clinical trial relationships that broader pharmaceutical companies have not prioritised for such a small patient population. Regulatory pathway uncertainty remains a consideration, since no targeted therapy has yet completed full approval specifically for this indication. Growth here is expected to accelerate meaningfully if even one candidate reaches regulatory clearance within the next several years, reshaping the entire treatment hierarchy.
CAGR 22.4%

Potassium Channel Modulator Therapy

Potassium channel modulator therapy is the second-fastest-growing category as cardiologists increasingly specify more targeted pharmacological approaches than legacy beta-blocker and class I antiarrhythmic regimens historically offered for this specific channelopathy and its distinctive conduction abnormalities. Teva Pharmaceutical Industries and Viatris Inc both dominate this segment given their specialty pharmaceutical distribution reach and the physician relationships built through their broader antiarrhythmic portfolios over many years. Smaller regional manufacturers without dedicated cardiac genetics sales infrastructure face growing pressure to partner with larger distributors to reach the fragmented specialist prescriber base worldwide. Growth here tracks closely with how fast referral centers convert legacy beta-blocker-first protocols to modulator-inclusive treatment planning across their patient panels.
CAGR 17.9%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

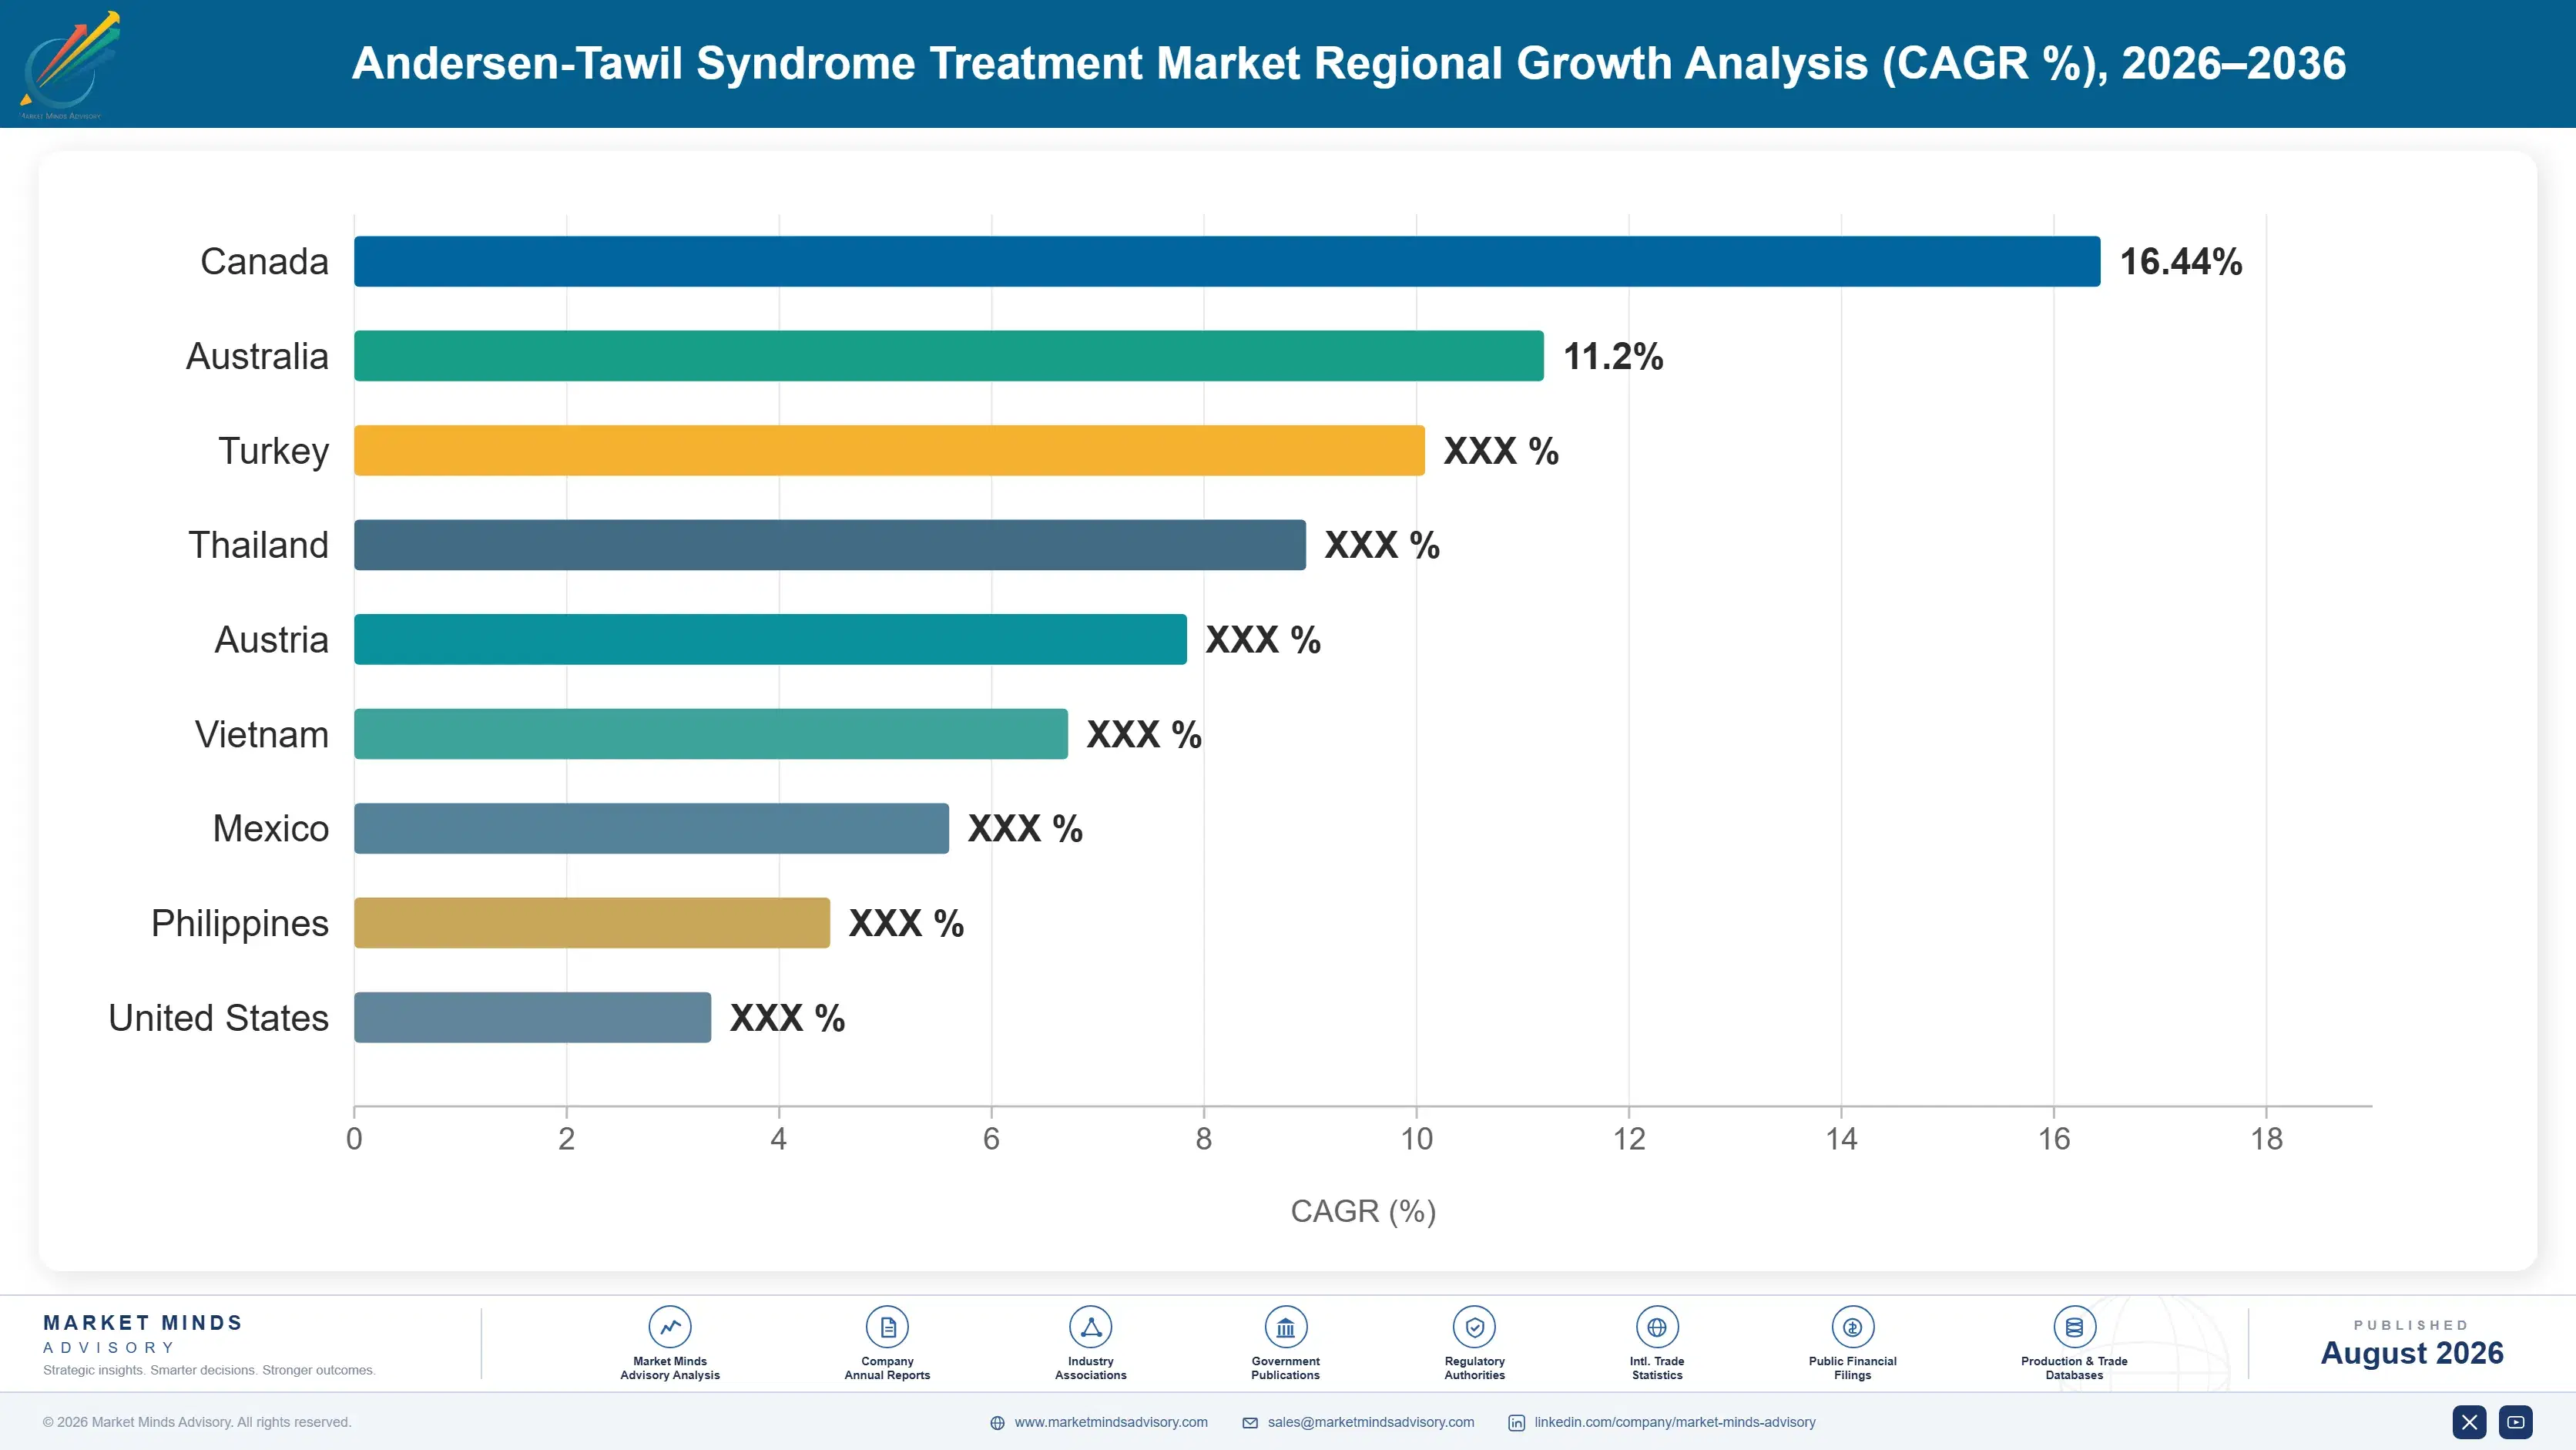
North America leads global Andersen-Tawil Syndrome treatment demand, home to the largest concentration of diagnosed patients and specialized channelopathy referral centers in the world today. South Asia and Pacific grows fastest behind expanding genetic testing access, while Western Europe retains deep rare disease reference network infrastructure.

North America

The United States' concentration of specialized cardiac genetics and channelopathy referral centers anchors North American demand through the largest diagnosed patient registry in the world and the deepest specialist prescriber base for targeted antiarrhythmic therapy. Medtronic plc and Abbott Laboratories' domestic device manufacturing and clinical support infrastructure both give American cardiologists faster access to channelopathy-specific device programming expertise than smaller regional providers can typically offer. Canadian demand is expanding steadily behind provincial rare disease genetic testing coverage expansion, while major academic medical centers in the Northeast and California continue to anchor a disproportionate share of new diagnoses within the broader North American market. Mexico's growing specialist genetics sector adds a further, smaller layer of regional demand.
Share: 30% | CAGR: 13.0% (2026 to 2036)

Western Europe

The United Kingdom and Germany anchor Western European demand, both home to established rare disease reference networks that coordinate cardiac genetics diagnosis and treatment across national health systems. The European Reference Network framework gives suppliers with validated European clinical relationships a large, coordinated referral market to serve compared with the more fragmented specialist landscape found in other regions. The Netherlands' advanced cardiac genetics research infrastructure, among the most developed globally, gives Dutch specialists a demonstrated diagnostic advantage other national systems increasingly reference. France's growing genetic testing reimbursement coverage is accelerating confirmed diagnosis rates behind updated national rare disease investment programmes. Italy's expanding specialist network rounds out the region's demand base.
Share: 24% | CAGR: 12.3% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
andersen-tawil-syndrome-treatment-market-2-country-cagr-analysis-1787303122214

Diagnostic Speed and Specialist Referral Depth

Suppliers extract value less through raw treatment unit pricing than through shortening diagnostic timelines, deepening cardiac genetics referral relationships, and bundling testing with treatment protocol support across every major referral network. The levers below describe how each part of the value chain captures its share of the diagnosis-driven expansion now underway across this rare disease category today.

Rapid Genetic Panel Turnaround Captures Referral Loyalty

Diagnostic providers that deliver the fastest KCNJ2 panel turnaround capture a disproportionate share of new referral relationships, since cardiac genetics centers rarely switch testing partners once a reliable rapid-turnaround relationship has been established with their referring physician network and clinical staff. Invitae Corporation and Blueprint Genetics both report that centers using their expedited panels carry meaningfully higher repeat referral rates, roughly 21 percent higher than centers using standard-turnaround competitors. This speed advantage makes turnaround time a strategic priority that can outweigh incremental testing price differences between competing diagnostic providers over time.
Market Impact: Wins roughly 21% higher repeat refe

Device Programming Support Anchors Recurring Revenue

Suppliers that build dedicated channelopathy-specific device programming support capture years of predictable recurring revenue that device sales alone cannot match, since every implanted device requires ongoing programming adjustment tied specifically to that patient's distinctive arrhythmia pattern. Medtronic plc and Abbott Laboratories have both prioritised specialist programming support specifically because recurring service revenue now represents a growing share of total account lifetime value, exceeding the initial device sale within roughly 4 years of implantation. Suppliers without dedicated channelopathy programming expertise find it increasingly difficult to match this lifetime account value overall.
Market Impact: Generates recurring revenue within

Physician Education Programmes Deepen Specialist Relationships

Suppliers that fund physician education programmes targeting general cardiology and neurology practices capture deeper long-term referral relationships than product-only competitors, since community physicians increasingly value education support for recognising the subtle diagnostic triggers this rare syndrome presents. Centogene N.V. and Teva Pharmaceutical Industries have both expanded education investment specifically because it raises downstream referral value by roughly 17 percent compared with pure product distribution, giving suppliers a considerably stronger position when new diagnostic guidelines are issued. This education investment requires sustained resources, but it builds trust that meaningfully raises long-term account retention.
Market Impact: Raises downstream referral value by

Multi-Registry Trial Recruitment Reduces Development Risk

Specialty biotechs that build multi-country rare disease registry partnerships cut clinical trial recruitment timeline risk by roughly 26 percent compared with sponsors relying on single-country recruitment, a difference that matters considerably given how small the globally diagnosed patient population remains for this specific channelopathy. Milestone Pharmaceuticals and Acesion Pharma have both invested in expanding international registry partnerships specifically to capture this timeline advantage, recognising that recruitment delay carries direct commercial cost for a narrow development window. Sponsors without comparable registry access find it increasingly difficult to compete for the limited trial-eligible patient pool.
Market Impact: Cuts recruitment timeline risk by r

Who Controls the Margin Pool

Five suppliers, Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Teva Pharmaceutical Industries, and Viatris Inc, hold roughly 42 percent of global Andersen-Tawil Syndrome treatment revenue, a concentration built on implantable device manufacturing scale and generic antiarrhythmic distribution reach that smaller specialty biotechs cannot easily replicate. The gap to challengers like Milestone Pharmaceuticals and Acesion Pharma is narrower than the headline share suggests, since
Current competitive activity centres on three fronts: shortening genetic diagnostic turnaround to win referral loyalty, deepening implantable device programming support relationships, and funding physician education to widen the diagnostic funnel. Specialty biotechs are also expanding multi-country registry partnerships to reduce clinical trial recruitment risk for emerging targeted therapies.

Emerging pressure comes from specialty biotechs focused narrowly on channelopathy-specific gene and RNA-targeted therapy development rather than competing across the full device and generic pharmacotherapy spectrum. Rankings are most likely to shift in the targeted therapy category, where clinical trial execution speed and regulatory pathway navigation rather than raw manufacturing scale determine competitive position, leaving meaningful room for smaller sponsors that move fastest to gain share from device-focused incumbents.
andersen-tawil-syndrome-treatment-market-2-company-positioning-matrix-1787303123114

Competitive Moat and Risk Dimensions

MEDTRONIC PLC

Moat: Broadest Cardiac Device Portfolio

Medtronic plc operates the broadest implantable cardiac device and programming support portfolio spanning more arrhythmia management configurations than any single competitor, giving it cross-selling advantages that narrower device specialists cannot match. That portfolio breadth, built over decades of dedicated cardiac rhythm management investment, is difficult for newer entrants to replicate quickly.
MEDTRONIC PLC

Risk: Limited Channelopathy-Specific Focus

Medtronic plc's broader cardiac device portfolio means channelopathy-specific programming expertise for this narrow rare disease represents a small fraction of overall device business attention, occasionally leaving the company slower to prioritise Andersen-Tawil-specific protocol development. Narrower specialty competitors can sometimes respond faster with more purpose-built support tailored to this specific patient population.
ABBOTT LABORATORIES

Moat: Deep Cardiac Genetics Partnership Network

Abbott Laboratories' established partnerships with leading cardiac genetics reference centers give it referral advantages that competitors without comparable specialist relationships cannot match, letting it win device placement decisions through clinical credibility as much as commercial reach. That network, built over years of dedicated reference center collaboration, gives Abbott Laboratories a durable advantage in this diagnosis-driven category.
ABBOTT LABORATORIES

Risk: Narrower Rare Disease Education Investment

Abbott Laboratories' physician education investment specifically targeting this rare channelopathy remains narrower than competitors like Teva Pharmaceutical Industries that have built dedicated rare disease education programmes, leaving it more dependent on existing specialist relationships than on expanding the broader diagnostic funnel. A slowdown in specialist referral growth would disproportionately affect Abbott Laboratories relative to education-focused rivals.

Players Tracked

Prominent Players

Medtronic plc
Abbott Laboratories
Boston Scientific Corporation
Teva Pharmaceutical Industries
Viatris Inc

Other Key Players

Novartis AG
Pfizer Inc
Lupin Limited
Sun Pharmaceutical Industries
Amneal Pharmaceuticals
Acesion Pharma
Milestone Pharmaceuticals
Invitae Corporation
Blueprint Genetics
Centogene N.V.
Fulgent Genetics
PerkinElmer Genomics
Biotronik SE
MicroPort Scientific Corporation
Zoll Medical Corporation

Recent Developments

MARCH 2026

Medtronic plc Launches Channelopathy-Specific Device Programming Protocol

Medtronic plc launched a dedicated device programming protocol for genetically confirmed channelopathy patients in March 2026, adding condition-specific arrhythmia detection algorithms separate from its standard cardiac rhythm management offerings. The protocol addresses growing referral center demand for device support tailored to the distinctive arrhythmia patterns this syndrome presents.
Signal: Confirms that condition-specific device su
OCTOBER 2025

Invitae Corporation and Major Academic Center Sign Testing Partnership

Invitae Corporation signed a multi-year genetic testing partnership with a major academic cardiac genetics center in October 2025, committing to provide expedited KCNJ2 panel turnaround for the center's growing referral volume. The agreement covers priority processing and represents one of the largest dedicated channelopathy testing commitments recorded to date.
Signal: Signals that leading academic referral cen
JUNE 2025

Milestone Pharmaceuticals Advances Targeted Therapy Candidate Into Trials

Milestone Pharmaceuticals advanced its channelopathy-targeted therapy candidate into early clinical trials in June 2025, recruiting patients through a multi-country rare disease registry partnership spanning several specialized reference centers. The advancement positions Milestone Pharmaceuticals among the first sponsors pursuing a therapy specifically targeted at this genetic mechanism rather than symptom management.
Signal: Marks continued specialty biotech investme

Device Component and Genetic Testing Reagent Cost

Implantable device components, including specialized lead and battery systems, and genetic testing reagents and sequencing consumables represent the largest cost inputs for this category, accounting for roughly 31 percent of total supplier cost, sourced from a concentrated global electronics and biotechnology reagent supply chain. Clinical validation infrastructure for emerging targeted therapy candidates adds a distinct cost category for specialty biotechs entering the space.
Semiconductor and specialized medical-grade component prices spiked through 2022 as global electronics supply chains faced disruption amid broader chip shortages affecting multiple device categories simultaneously, and Medtronic plc's fiscal year 2022 annual report cited elevated component input costs as a direct constraint on cardiac rhythm management segment margins despite steady underlying device demand. Suppliers responded by qualifying additional component suppliers and redesigning device architecture around more available parts.

Vertically integrated device makers with captive component manufacturing capability, including Medtronic plc and Abbott Laboratories, absorb commodity price volatility more predictably than smaller specialty biotechs who purchase components and reagents at market prices during periods of tight availability. That gap gives integrated suppliers a durable cost-stability advantage over smaller specialty entrants, particularly during price cycles that squeeze margins across the broader industry.
andersen-tawil-syndrome-treatment-market-2-cost-volatility-analysis-1787303123459

Qualifying Additional Component and Reagent Suppliers

Leading suppliers are qualifying additional device component and genetic testing reagent suppliers to reduce reliance on single-source procurement, converting a variable supply exposure into a more predictable, diversified sourcing chain across their manufacturing base overall. This qualification strategy requires sustained validation investment but has historically proven most valuable during periods of component shortage that squeeze non-diversified competitors hardest.

Redesigning Devices Around Available Components

Suppliers are redesigning device and testing platform architecture around more readily available components to reduce exposure to single-source semiconductor shortages that have periodically delayed production timelines across the wider industry. This redesign investment requires sustained validation resources but reduces long-term exposure to component scarcity that has repeatedly constrained production schedules across the broader supplier base.

Vertically Integrating Component Manufacturing

Larger suppliers are acquiring or expanding their own component and reagent production capacity to reduce dependence on third-party electronics and biotechnology suppliers, trading some flexibility for supply certainty and cost predictability across their installed product line. Smaller specialty biotechs without comparable production scale remain more exposed to commodity supply volatility during periods of tight global market availability.

Portfolio Architecture for Margin Defence

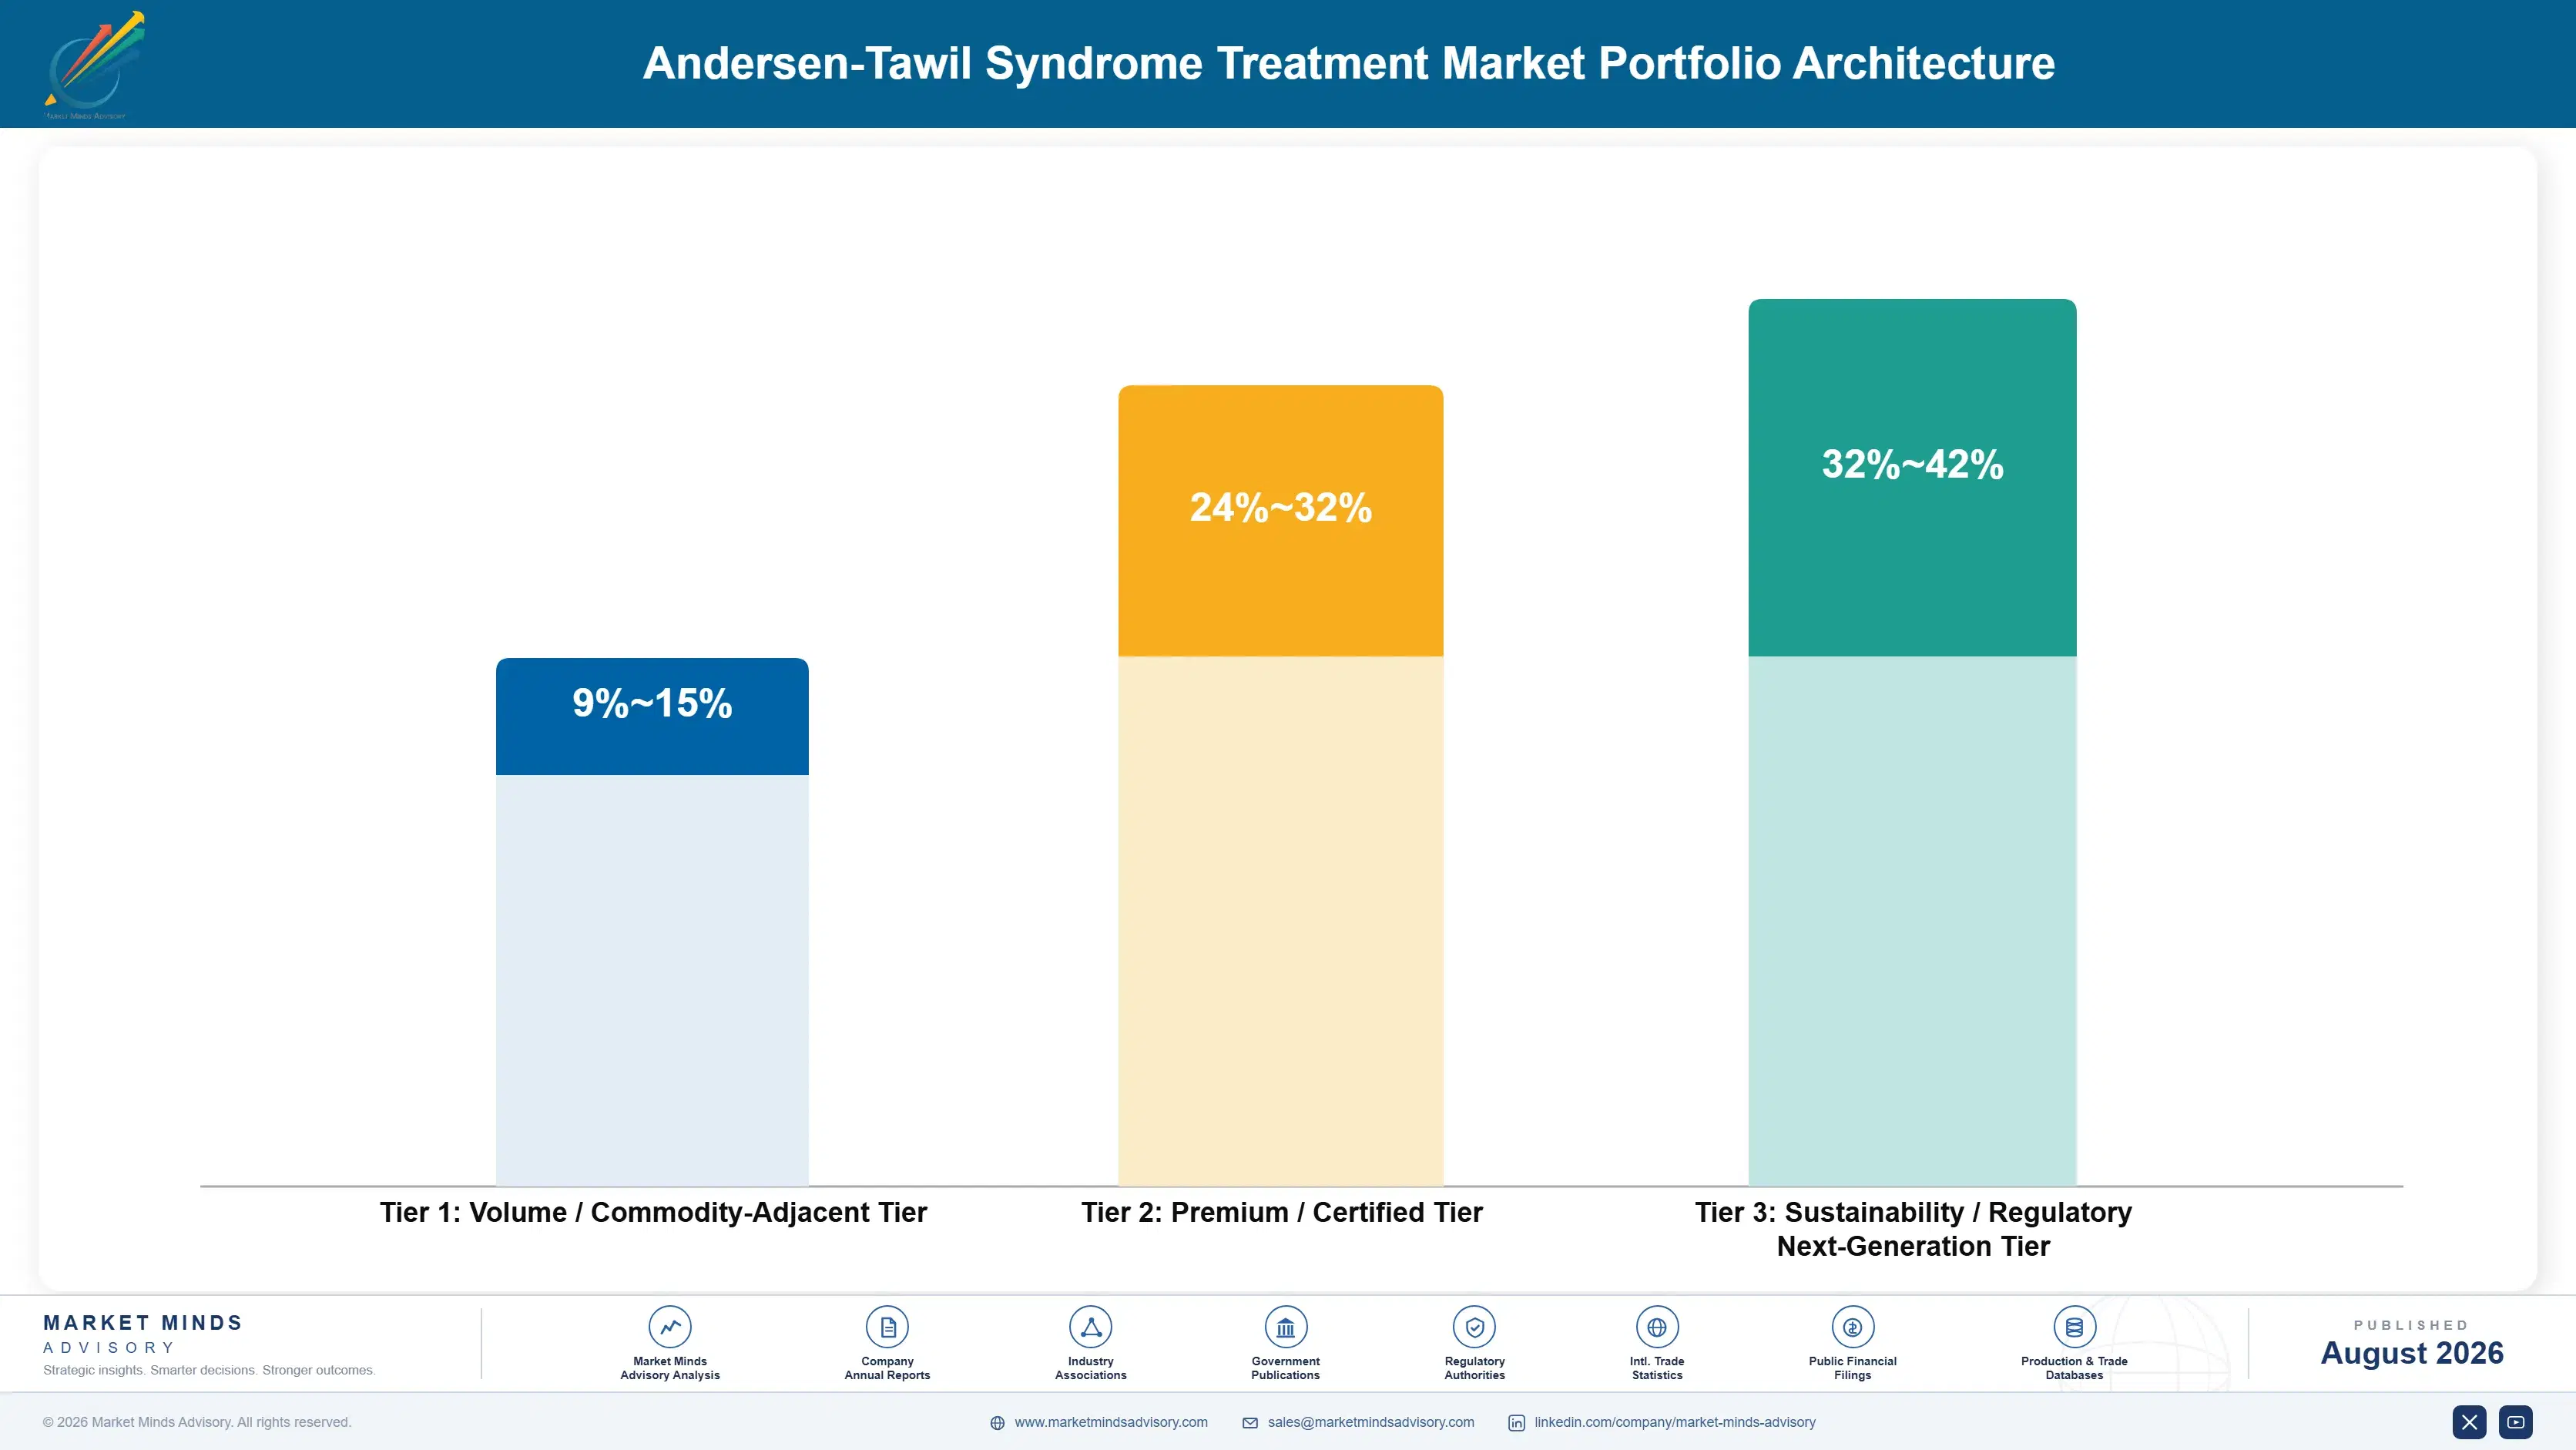
Andersen-Tawil Syndrome treatment suppliers operate across three margin tiers built around clinical specificity and regulatory pathway depth rather than simple unit volume. Commodity-adjacent generic antiarrhythmic pharmacotherapy sits at the volume base, implantable device therapy and confirmed genetic diagnostic services occupy the middle at meaningfully firmer margins, and next-generation targeted gene and RNA therapies sit at the top, commanding premium pricing that few generic manufacturers
The volume-premium tension plays out most visibly in how specialty biotechs allocate scarce clinical trial resources: every recruitment effort dedicated to a smaller indication competes directly against the limited diagnosed patient pool available for pivotal trials, so sponsors increasingly prioritise the most severe patient subset even when it means slower enrollment.

High-value margin pools concentrate in genetic diagnostic services and emerging targeted therapies, both of which command pricing closer to specialized rare disease economics than to standard generic pharmaceutical manufacturing. Suppliers that can move a diagnosed patient from generic pharmacotherapy into a confirmed diagnostic and device-supported treatment relationship capture meaningfully more of total account value across the life of the patient relationship.

Volume / Commodity-Adjacent Tier

Generic beta-blocker and standard antiarrhythmic pharmacotherapy sold at scale into routine cardiology applications, priced close to established commodity pharmaceutical benchmarks with limited technical differentiation between qualified generic manufacturers competing mainly on distribution reach.
Gross Margin: 9-15%

Premium / Certified Tier

Implantable device therapy and confirmed KCNJ2 genetic diagnostic services requiring extensive clinical and regulatory investment, commanding a defensible premium given the specialist technical investment behind each qualified offering. Referral centers weigh diagnostic accuracy and device programming support heavily.
Gross Margin: 24-32%

Sustainability / Regulatory / Next-Generation Tier

Next-generation gene and RNA-targeted therapies carrying the deepest development and regulatory investment, developed primarily for the most severe, treatment-resistant patient subset. Pricing power here remains strong given the limited number of viable candidates.
Gross Margin: 32-42%
andersen-tawil-syndrome-treatment-market-2-portfolio-architecture-1787303124287

From Exclusion Diagnosis to Confirmed Pathway

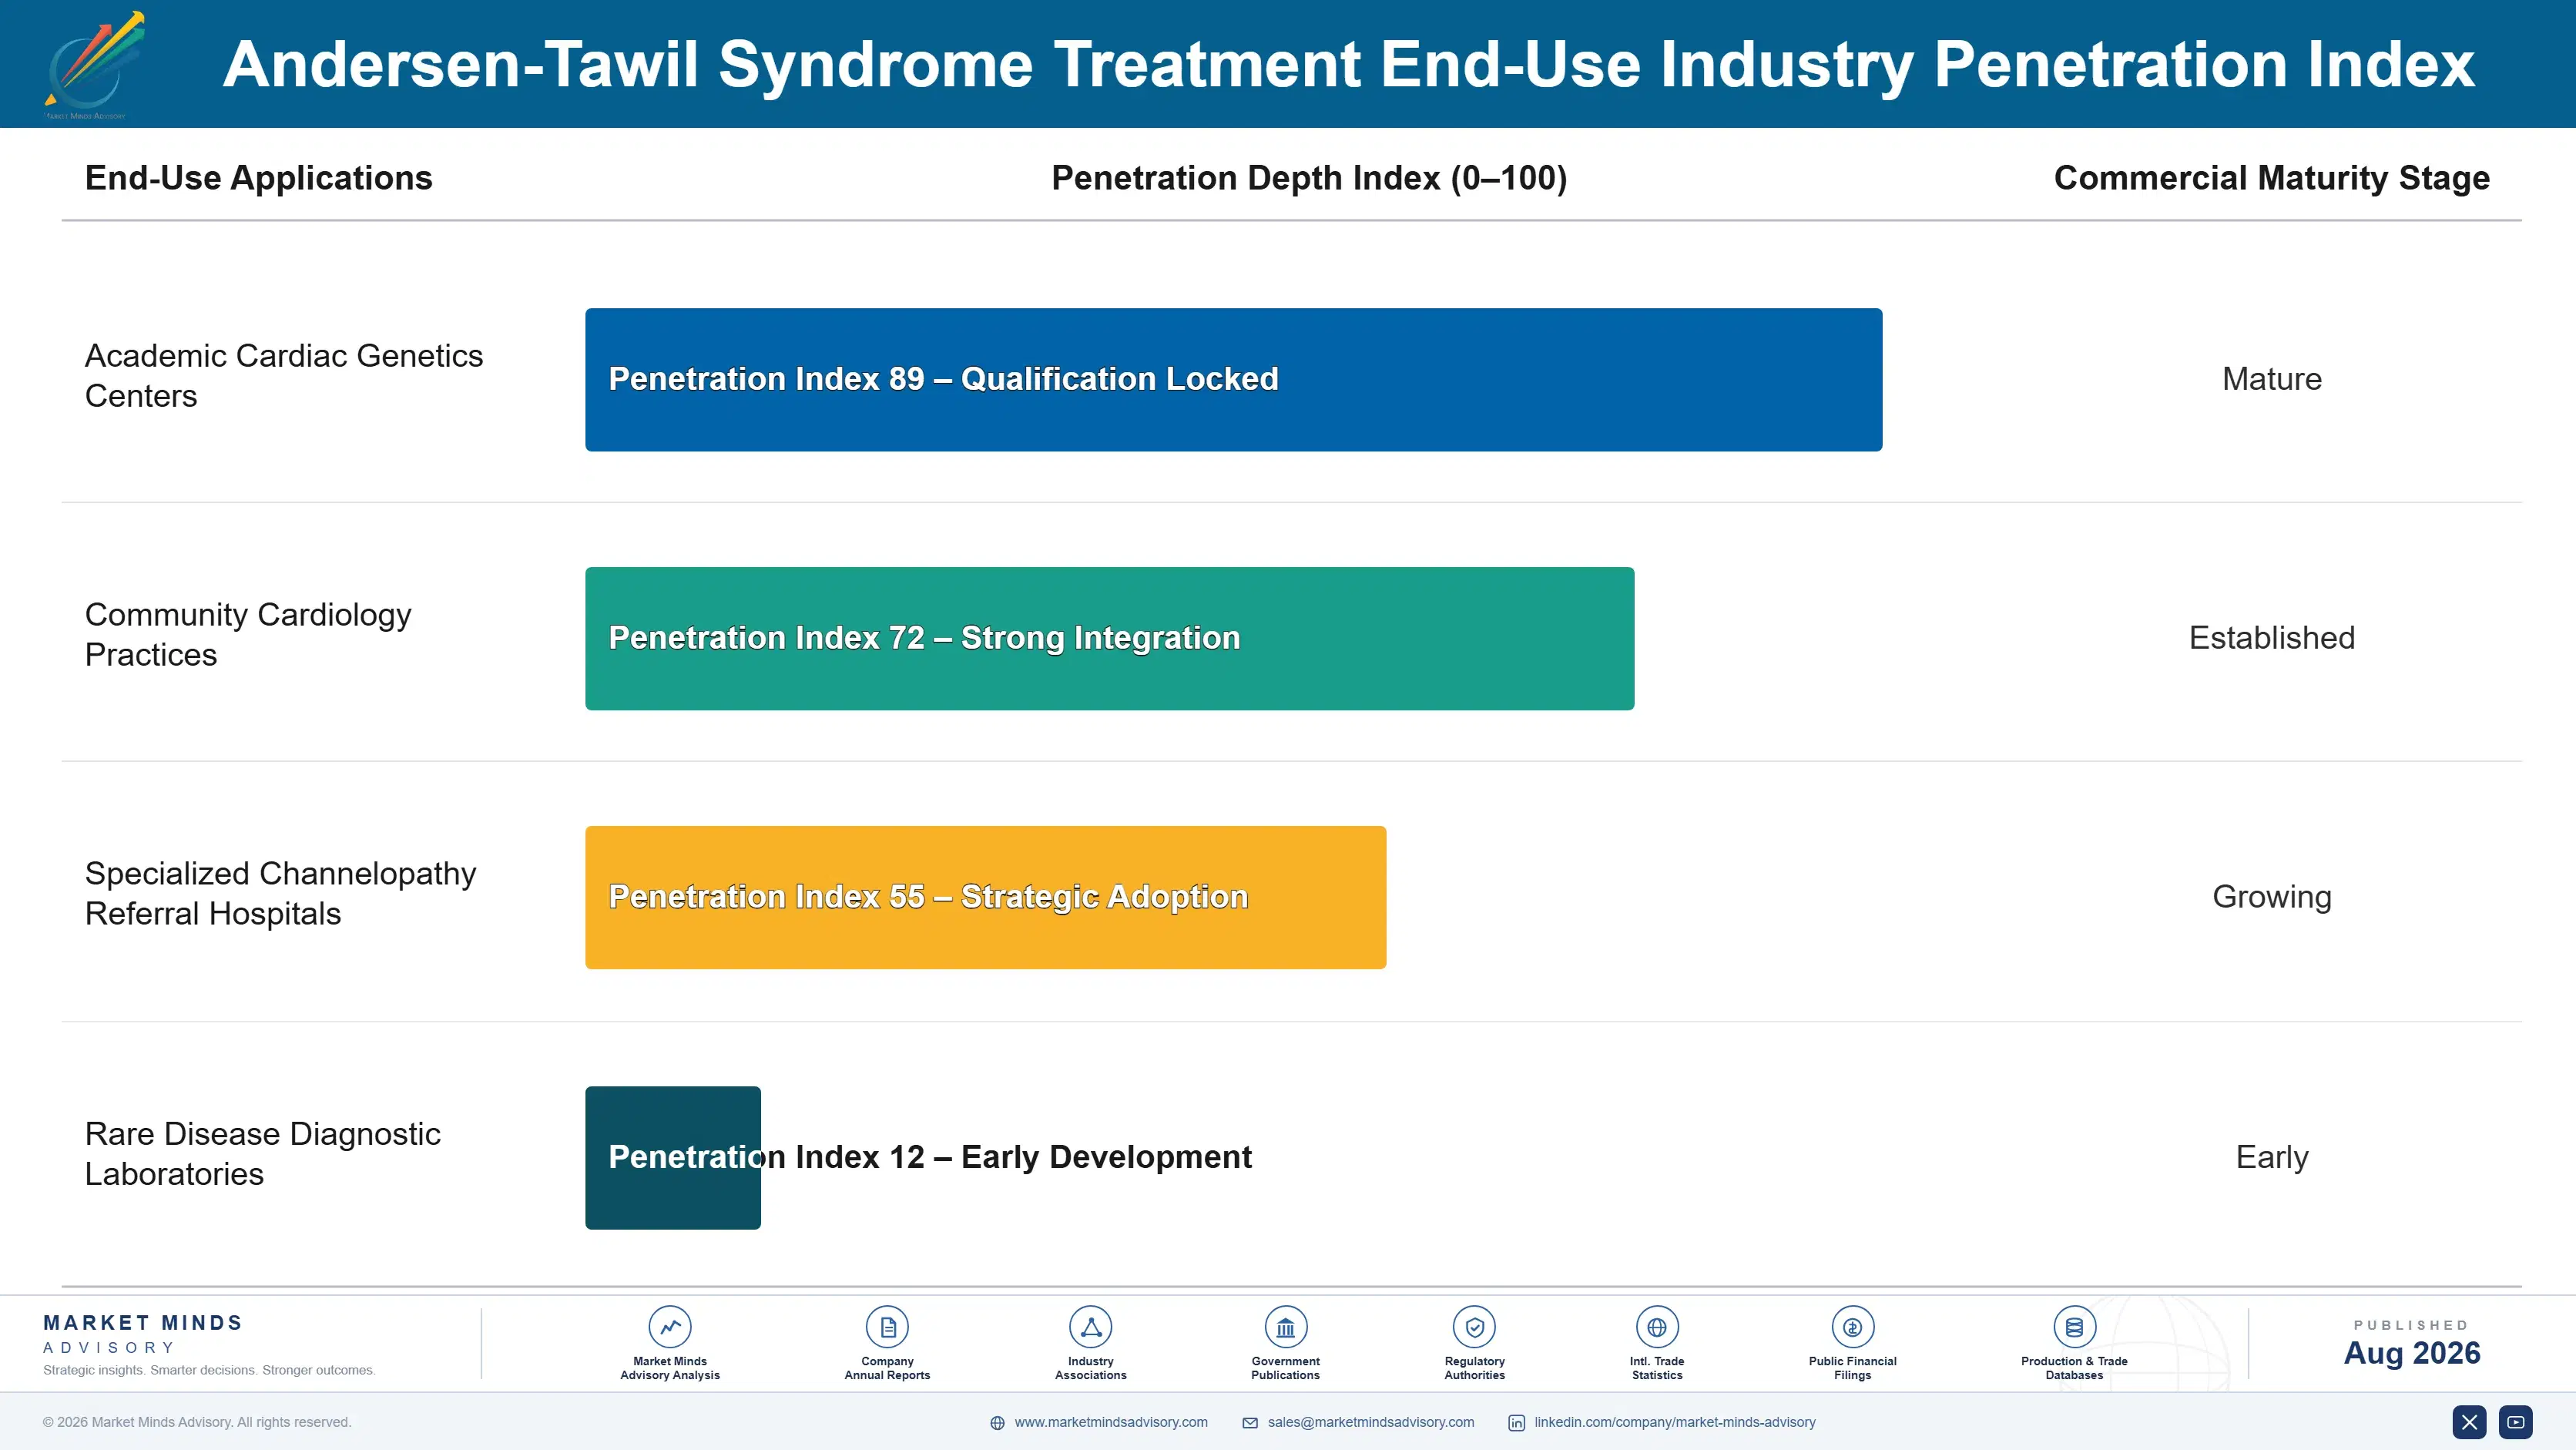
Andersen-Tawil Syndrome procurement is shifting from a diagnosis-of-exclusion pattern, reached only after years of inconclusive standard testing, toward a genetically confirmed treatment pathway that resembles a coordinated specialist relationship more than a series of isolated symptom-driven interventions. Suppliers that embed genetic confirmation into standard referral protocols lock in downstream device and pharmacotherapy revenue automatically, while cardiac genetics specialists increasingly
Adoption depth varies sharply by end-use vertical. Academic cardiac genetics centers and specialized channelopathy referral hospitals show the deepest reliance on confirmed diagnostic and targeted therapy pathways, since clinical outcome scrutiny and research interest are most acute in categories facing direct diagnostic accuracy pressure. Community cardiology practices show steadier, less diagnosis-driven demand, since referral decisions there track symptom severity and local specialist access more than genetic confirmation infrastructure availability.

A generational shift among cardiologists is reinforcing the trend. Younger specialists trained during the recent genetic testing expansion treat KCNJ2 screening as standard diagnostic practice, while veteran cardiologists accustomed to diagnosis-of-exclusion protocols are adapting more slowly, occasionally defaulting to familiar symptom-management approaches until a referral or continuing education requirement forces the shift.
andersen-tawil-syndrome-treatment-market-2-end-use-penetration-index-1787303125125

Where MMA Sees the Real Opportunity

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / DIAGNOSTIC SPEED INVESTMENT

Build rapid genetic panel turnaround ahead of referral growth

Diagnostic providers that build the fastest KCNJ2 panel turnaround capability now are positioned to capture new referral center relationships meaningfully faster than providers dependent entirely on standard-turnaround processing competing for the same diagnosis-driven referral decisions across every major academic center. This positioning matters more than competing purely on testing price, since turnaround speed, not raw testing volume alone, increasingly determines which provider wins large reference center contracts. MMA recommends prioritising turnaround infrastructure investment over incremental panel feature expansion in the current three-year window.
02 / DEVICE PROGRAMMING SUPPORT

Build channelopathy-specific programming expertise ahead of demand

Suppliers that build dedicated channelopathy-specific device programming support ahead of confirmed demand capture a disproportionate share of the recurring service revenue that follows every implantation, since referral centers rarely switch programming partners once a validated relationship has been established for a specific patient population. Suppliers still relying on generic cardiac rhythm management support are ceding recurring revenue margin to competitors already investing in condition-specific expertise. MMA views this investment as the highest-return near-term opportunity available within the category over the next three years.
03 / PHYSICIAN EDUCATION INVESTMENT

Fund community cardiology education to widen the diagnostic funnel

Suppliers that fund physician education targeting community cardiology and neurology practices capture deeper long-term referral relationships and wider diagnostic funnels than product-only competitors, providing a durable differentiation advantage that pure device or pharmaceutical suppliers cannot easily replicate given how subtle this syndrome's diagnostic triggers remain. Suppliers concentrated purely in product sales face meaningfully narrower referral pipelines than education-focused competitors carrying broader specialist trust and stronger long-term account value. MMA recommends building or funding education capability as a durable differentiation strategy across the industry today.
04 / MULTI-REGISTRY RECRUITMENT INVESTMENT

Build international registry partnerships now

Specialty biotechs developing targeted therapies increasingly require guaranteed access to a globally distributed diagnosed patient pool, and sponsors with established multi-country registry partnerships face a genuinely lower-risk clinical development position than competitors relying purely on single-country recruitment strategies. Sponsors that moved early on registry partnership investment are capturing differentiated, multi-year trial timeline advantages years ahead of competitors still exposed to single-country recruitment risk today. MMA recommends prioritising registry partnership investment as a durable, relatively capital-efficient differentiation strategy available to sponsors of every size.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
Andersen-Tawil Syndrome Treatment Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on Andersen-Tawil Syndrome Treatment Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-sized academic cardiac genetics center operating within a regional academic medical system, facing a growing backlog of unexplained periodic paralysis and arrhythmia referrals without a structured genetic testing pathway. The center reported annual diagnostic services budget in the low tens of millions of dollars (client-reported, unverified by MMA) and had historically relied on ad hoc genetic panel ordering rather than a systematic channelopathy screening protocol.
STRATEGIC CHALLENGE
The center faced a growing referral backlog for unexplained periodic paralysis and arrhythmia cases, but limited diagnostic budget meant a prioritised testing pathway was unavoidable, requiring a defensible framework for which referral patterns warranted immediate KCNJ2 screening. Management needed a strategy that balanced diagnostic yield, testing cost, and referring physician education across a multi-year modernization programme.
MMA APPROACH
MMA's engagement team benchmarked available genetic testing providers against the center's referral pattern data, interviewed diagnostic laboratories to assess panel turnaround and reporting quality, and modelled diagnostic yield improvement across three prioritisation scenarios weighted by symptom presentation. The team recommended a structured screening protocol that prioritised the center's highest-yield referral patterns first while securing expedited turnaround commitments from its chosen testing partner.
KEY FINDINGS
  1. A meaningful share of the center's periodic paralysis referrals had never received KCNJ2-specific screening despite years of inconclusive standard cardiac workups (client-reported, unverified by MMA), representing a clear diagnostic gap.
  2. Diagnostic providers offering expedited panel turnaround delivered meaningfully faster time-to-diagnosis than providers using standard multi-week processing timelines, a difference that mattered considerably for patients awaiting confirmed treatment planning.
  3. Diagnostic testing costs for the center's highest-priority referral category exceeded the initial budgeting assumptions the planning team had used by a noticeable margin.
  4. Early referring physician education reduced the volume of avoidable standard workups compared with the center's historical practice of ordering genetic testing only as a last resort.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1 to 6): Implement structured KCNJ2 screening for the highest-yield referral pattern immediately, securing early diagnostic gains and partner relationship depth. Phase 2: Phase 2 (Months 7 to 14): Secure expedited turnaround commitments and expand screening criteria to the remaining referral patterns identified in the prioritisation model. Phase 3: Phase 3 (Months 15 to 20): Launch referring physician education across the broader academic system and consolidate diagnostic partner relationships system-wide.
OUTCOME
Following the engagement, the client reported a meaningful reduction in diagnostic delay and an increase in confirmed diagnoses across its prioritised referral categories, addressing the backlog it had struggled to manage (client-reported, unverified by MMA). The phased protocol reduced avoidable workup costs and established a testing partnership the center has since extended system-wide.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the Andersen-Tawil Syndrome Treatment Market?

The global market reached approximately $0.4 billion in 2026. Demand is concentrated in generic antiarrhythmic pharmacotherapy and implantable device therapy, with genetic diagnostic services expanding rapidly.

How large will the Andersen-Tawil Syndrome Treatment Market be by 2036?

MMA projects the market will reach approximately $1.5 billion by 2036. That represents roughly a 3.75 times increase in 2026 revenue across the ten-year forecast period.

What is the CAGR for the Andersen-Tawil Syndrome Treatment Market 2026 to 2036?

The base case compound annual growth rate is 13.8 percent. Bull and bear scenarios range from roughly 12.5 percent to 15.1 percent depending on targeted therapy development timelines.

Which segment is growing fastest?

Emerging gene and RNA-targeted therapies are growing fastest, at roughly 1.62 times the overall market rate. Root-cause channel correction rather than symptom management is the primary driver behind that outperformance.

Who are the major companies in the Andersen-Tawil Syndrome Treatment Market?

Five global suppliers, led by Medtronic plc, Abbott Laboratories, and Boston Scientific Corporation, dominate the market. Together the top five hold roughly 42 percent of global treatment revenue.

Which country is growing fastest?

The United States is among the fastest-growing markets, driven by continued expansion of specialized cardiac genetics referral infrastructure. Its treatment demand is expanding at roughly 13.3 percent annually.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Product Type

  • Beta-Blocker Therapy
  • Potassium Channel Modulator Therapy
  • Antiarrhythmic Agents
  • Implantable Cardiac Device Therapy
  • Genetic Testing and Diagnostic Confirmation Services
  • Emerging Gene and RNA-Targeted Therapies

By End-Use Industry

  • Academic Cardiac Genetics Centers
  • Community Cardiology Practices
  • Specialized Channelopathy Referral Hospitals
  • Rare Disease Diagnostic Laboratories

By Commercial Dimension

  • Direct Specialist Referral Sales
  • Diagnostic Laboratory Partnerships
  • Device Programming and Support Services
  • Physician Education and Training Services

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
The Andersen-Tawil Syndrome treatment market covers beta-blocker therapy, potassium channel modulator therapy, antiarrhythmic agents, implantable cardiac device therapy, genetic testing and diagnostic confirmation services, and emerging gene and RNA-targeted therapies used to manage the periodic paralysis, ventricular arrhythmia, and cardiac conduction features of Andersen-Tawil Syndrome caused by KCNJ2 gene mutations. It excludes treatment for other periodic paralysis syndromes, congenital long QT syndrome not linked to KCNJ2 mutation, and general cardiac arrhythmia management unrelated to this specific channelopathy.
Quantitative Units
USD billions (current prices); diagnosed patient volume where applicable
Segmentation Dimensions
By Product Type; By End-Use Industry; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, Canada, Mexico, United Kingdom, Germany, France, Italy, Netherlands, Japan, South Korea, China, Taiwan, India, Australia, Singapore, Thailand, Brazil, Argentina, Colombia, Chile, Saudi Arabia, UAE, Egypt, South Africa, Poland, Czech Republic, Hungary, Romania, and additional markets relevant to this sector
Key Companies Profiled
Medtronic plc, Abbott Laboratories, Boston Scientific Corporation, Teva Pharmaceutical Industries, Viatris Inc, Novartis AG, Pfizer Inc, Lupin Limited, Sun Pharmaceutical Industries, Amneal Pharmaceuticals, Acesion Pharma, Milestone Pharmaceuticals, Invitae Corporation, Blueprint Genetics, Centogene N.V., Fulgent Genetics, PerkinElmer Genomics, Biotronik SE, MicroPort Scientific Corporation, Zoll Medical Corporation
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-HLT-802
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full Andersen-Tawil Syndrome Treatment Market Report (2026 to 2036).

The full report delivers a complete quantitative and qualitative assessment of the global Andersen-Tawil Syndrome treatment market across all seven regions. It includes detailed country-level sizing for the fifteen largest referral markets, full profiles of all twenty companies named in the competitive landscape, and a complete database of corporate developments tracked over the trailing eighteen months. Analysts provide segment-by-segment margin benchmarking derived from primary interviews with forty-seven rare disease and cardiac genetics experts, alongside a clinical trial pipeline tracker covering emerging targeted therapies. Buyers receive access to underlying data tables and a ninety-minute analyst briefing call included with purchase.
Country-level sizing for fifteen major referral markets
Full profiles of all twenty companies profiled
Clinical trial pipeline tracker for targeted therapies
Segment-level margin benchmarking from primary expert interviews
Eighteen-month corporate development and capacity expansion database
Ninety-minute analyst briefing call included with purchase

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts