Market Minds Advisory
3D Printed Maxillofacial Implants Market

3D Printed Maxillofacial Implants Market: PEEK Cranial Innovation and Point-of-Care Manufacturing Reshape Growth Beyond Titanium

Point-of-care hospital 3D printing and radiolucent PEEK cranial implant adoption are pulling demand toward in-house manufacturing, forcing established titanium plate makers to defend decades-old surgeon relationships against faster-growing digital design rivals.

Lead Analyst

Published

September 2026

Make Smarter Decisions with Customized Research Insights

Request a free sample report and evaluate market opportunities, growth trends, and competitive dynamics relevant to your business needs.

2025 MARKET VALUE$0.9BMarket Size 2025
2036 FORECAST VALUE$2.8BBase Case , 2026 to 2036
CAGR 2026 TO 203610.2 %Bull 11.6% / Bear 8.8%
INCREMENTAL OPPORTUNITY$1.7BNet 10- year value creation
EXPANSION MULTIPLE2.64x2036 value over 2026 base
Strategic Levers
M&A Pipeline
Regional Outlook
Country Rankings
Competitive Intelligence
Segmental Deep-dive
Call-Us : 91 93563 13602

Executive Snapshot and Market Trajectory

Stryker and Johnson & Johnson built the modern maxillofacial implant category on titanium plate reconstruction for trauma and oncology cases, and PEEK cranial implants are now the fastest-growing answer to surgeons facing radiolucency and imaging-compatibility requirements that titanium cannot satisfy. That shift is reshaping capacity investment plans.
Stryker and Johnson & Johnson still command meaningful combined share of the category through decades-old surgeon and hospital purchasing relationships, while expanding point-of-care hospital manufacturing keeps growing the addressable design pool feeding every producer's pipeline steadily year after year without pause. Rising craniomaxillofacial trauma and oncology reconstruction case volume has pulled patient-specific implant design firmly into mainstream surgical planning decisions across major hospital systems worldwide.
Five companies account for roughly half of category revenue, a moderately concentrated structure built on high regulatory clearance barriers, and the order shifts gradually as hospital systems standardise around suppliers offering both titanium and specialty PEEK or guide design capability under one long-term design services contract signed well in advance. Expanding point-of-care manufacturing and tightening imaging compatibility requirements, still accelerating, will determine how quickly specialty implant producers capture share from titanium-focused incumbents worldwide.
Market Definition
This market covers patient-specific implants and surgical guides produced by additive manufacturing for craniomaxillofacial reconstruction, including cranial plates, orbital floor implants, mandibular and maxillary reconstruction devices, and associated planning software and guides. It excludes dental implants sold for routine tooth replacement and non-printed stock craniomaxillofacial hardware.
Base Year Value
$0.9B in 2025 (MMA Primary Research Dataset, August 2026)
Forecast Period
2026 to 2036, eleven discrete annual values
CAGR
10.2% base case. Bull 11.6%. Bear 8.8%.
Fastest Growth Segment
PEEK Cranial Implants: 13.8% CAGR
Fastest Growth Country
India: 12.2% CAGR
Fastest Growth Region
South Asia and Pacific: 12.2% CAGR
Largest Region
North America: 32% of 2025 global value
Market Leaders
Stryker Corporation, Johnson & Johnson, KLS Martin Group, Materialise, Zimmer Biomet Holdings. Source: MMA Analysis based on company annual reports.
Primary Survey
n=3,800 procurement and R&D decision-makers, Q4 2025, six countries
Methodology
Demand-side build-up, cross-validated against public data, 47 expert interviews

3D Printed Maxillofacial Implants Market Forecast Scenarios

3d-printed-maxillofacial-implants-market-size-forecast-scenario-1786463123033
Between 2020 and 2025, the market grew at a historical rate near 9.0 percent, tracking steady global trauma and oncology reconstruction case volume and gradual titanium implant adoption across major hospital systems, with PEEK cranial implants remaining a comparatively small share of total volume through most of this recovery period. Manufacturers largely maintained existing capacity rather than investing aggressively during this window.
The base case assumes 10.2 percent annual growth through 2036, built on three mechanisms: expanding point-of-care hospital 3D printing requiring patient-specific design capability, rising radiolucent PEEK implant adoption driven by imaging compatibility requirements, and Asian hospital capacity expansion pulling forward surgical volume well ahead of comparable Western case growth still under gradual modernisation across most major producing regions, tracked closely across every affected hospital hub through the ten-year outlook period overall.
A bull case near 11.6 percent depends on point-of-care manufacturing regulatory clearance expanding across major markets still finalizing hospital-based production pathways today. The bear case near 8.8 percent reflects continued hospital budget caution around premium implant price differentials pushing some reconstruction cases toward stock titanium alternatives in cost-sensitive healthcare systems worldwide, particularly across reimbursement-constrained regions.

Titanium Legacy Meets Point-of-Care Manufacturing Demand

Maxillofacial implant manufacturing has quietly become a surgical-workflow specification decision as much as a materials engineering one. The core function, restoring precise anatomic form after trauma or tumor resection, has not changed, but hospital systems increasingly weigh design turnaround time alongside raw material choice when planning new reconstruction programmes across every affected surgical department. That shift already shapes new supplier evaluations.
TOP 5 CONCENTRATION46% CR5revenue share held by five largest global suppliers
AVERAGE IMPLANT ASP$4,200 per devicetypical finished implant price, per device delivered globally
LEADING PRODUCING COUNTRYUSA, 28%share of global production value, by home country
POINT-OF-CARE MANUFACTURING SHARE16% of volumeshare of device volume produced within hospital facilities
TRAUMA APPLICATION SHARE42% of revenueshare of category revenue from trauma reconstruction cases
TITANIUM POWDER COST SHARE38% of COGSinput cost weight from medical-grade titanium powder feedstock
Commercial behaviour splits by application volume and clinical complexity. Mainstream trauma reconstruction still relies heavily on established titanium plate systems that have performed reliably for decades, while oncology and complex craniofacial cases increasingly specify patient-specific PEEK or titanium implants where anatomic fit and imaging compatibility carry meaningfully higher clinical consequence for continuous, high-value surgical outcomes. Distributors report this split sharpening recently.
The next decade turns on whether titanium-focused producers can build sufficient point-of-care design capability to compete for hospital-based manufacturing contracts while defending their core surgeon relationships against rising specialty design competitors. Manufacturers that solve both problems stand to capture share from an installed titanium base that has dominated maxillofacial implant specification for more than three decades of continuous, uninterrupted clinical use worldwide. That transition will not happen overnight.
"Surgeons didn't switch to PEEK because titanium failed them. They switched because a CT scanner can see through it, and that changes how you monitor a cancer patient for the rest of their life."
Director, Medical Devices and Additive Manufacturing Practice · MMA Medical Devi

Market Trends

PEEK Cranial Implants Gain Share on Imaging Compatibility

Radiolucent PEEK cranial implants have moved from niche premium applications into mainstream specification for oncology and complex trauma reconstruction, where surgeons value post-operative imaging clarity that titanium plates cannot deliver entirely on their own. Oxford Performance Materials and OSSDSIGN have both reported expanded design wins across major hospital systems in recent years, driven by radiation oncologists specifically seeking implants that do not scatter CT and radiotherapy planning imagery. Clinical data from hospital systems has documented meaningfully improved post-operative monitoring outcomes versus comparable titanium alternatives across audited case series reviewed by MMA analysts.
Market Impact: Reaches 31% of new reconstruction c

Point-of-Care Hospital Manufacturing Expands Design Capability

The FDA's point-of-care manufacturing guidance and comparable regulatory frameworks in other major markets have converted hospital-based 3D printing from an experimental capability into a formally regulated clinical service line, allowing hospital systems to design and produce patient-specific guides and implants closer to the point of surgical care. Materialise and 3D Systems have both expanded dedicated point-of-care software and hardware portfolios targeting the more than 180 hospital-based 3D printing labs operating under formal regulatory frameworks according to industry data reviewed by MMA analysts. Hospital networks in Europe and Asia have announced comparable programme expansions over the past eighteen months alone.
Market Impact: Adds 400-plus new hospital programm

Market Opportunities and Growth Drivers

Rising Trauma and Oncology Case Volume Drives Implant Demand

Global craniomaxillofacial trauma and oncology reconstruction case volume continues rising considerably across major healthcare systems, a shift that has fundamentally changed implant demand patterns since complex reconstruction cases command meaningfully higher device value than routine stock hardware applications. Manufacturers have responded with dedicated patient-specific design production lines specifically engineered for these higher-margin case requirements. An estimated 31 percent of new craniomaxillofacial reconstruction cases now specify patient-specific implant design, up considerably from a meaningfully smaller share just a decade earlier, reflecting accelerating surgical adoption across major healthcare markets worldwide each year.
Market Impact: Loses 6 to 9% share

Surgical Planning Software Investment Drives Design Requirements

Global hospital investment in surgical planning software and additive manufacturing capability has risen considerably in recent years, driven by rising demand for faster design turnaround than traditional outsourced implant fabrication historically delivered. Manufacturers have responded by developing dedicated cloud-based design platforms specifically engineered for these faster turnaround requirements. New hospital-based 3D printing capacity is projected to grow considerably across major markets through the coming decade, each facility requiring design software capable of sustaining faster case turnaround than outsourced methods allow, across nearly every major hospital network, tracked closely worldwide each year.
Market Impact: Adds 8 to 14 months

Market Restraints and Challenges

High Device Cost Slows Reimbursement-Constrained Adoption

Many hospital systems in reimbursement-constrained healthcare markets find the cost premium of patient-specific implants over stock titanium hardware economically difficult, even where the clinical outcome case is well documented. The root cause is that insurance reimbursement policy, not surgical outcome data, drives most device selection decisions in cost-constrained systems, and lower-reimbursement healthcare systems see meaningfully slower patient-specific adoption than well-reimbursed systems facing the same clinical decision. Manufacturers have responded by developing tiered pricing programmes and simplified design workflows specifically intended to narrow the cost gap with stock hardware across multiple reimbursement-constrained healthcare markets.
Market Impact: Lifts PEEK case share 16%

Regulatory Clearance Timelines Slow New Design Adoption

New patient-specific implant designs still face meaningful regulatory clearance timelines, since national medical device authorities must independently review biocompatibility, mechanical testing, and manufacturing quality documentation before granting market clearance, a process that can stretch well beyond the design development timeline itself. This restricts how quickly manufacturers can convert new design capability into commercially available devices across jurisdictions with under-resourced regulatory bodies. Manufacturers have responded by developing standardised design frameworks and dedicated regulatory affairs teams specifically designed to shorten the review timeline in cooperating jurisdictions worldwide, particularly across jurisdictions with limited regulatory staffing and prior experience.
Market Impact: Covers 180-plus hospital labs
3 additional market trends, 4 additional growth drivers, and 3 additional restraints and challenges are covered in the full report. Contact sales@marketmindsadvisory.com to access the complete intelligence.

Segment CAGR and Growth Architecture

Segmentation follows implant application, the classification craniomaxillofacial surgeons, hospital procurement teams, and reconstruction specialists already use to distinguish cranial, orbital, mandibular, and surgical guide categories across every device type this report covers, spanning both mature titanium and rapidly emerging PEEK categories overall, each cycle, from routine trauma repair through next-generation point-of-care platforms now scaling worldwide.
3d-printed-maxillofacial-implants-market-market-share-analysis-1786463123198

PEEK Cranial Implants

PEEK cranial implants are the fastest-growing category as surgeons increasingly specify radiolucent, imaging-compatible material for oncology and complex trauma reconstruction cases requiring ongoing post-operative monitoring. The material offers meaningfully better imaging compatibility and lighter weight than titanium alternatives typically achieve in comparable cranial reconstruction applications. Oxford Performance Materials and OSSDSIGN both compete directly in this segment, each pursuing expanded design relationships with major hospital systems worldwide. Growth concentrates among centers serving oncology and complex trauma cases, though broader mainstream adoption still depends on closing the remaining cost gap with established titanium alternatives across major healthcare markets each year. Suppliers investing early in this transition stand to capture disproportionate share as compliance and reimbursement pathways broaden.
CAGR 13.8%

Patient-Specific Surgical Guides and Planning Models

Patient-specific surgical guides and planning models grow fastest among established application categories as hospital systems increasingly adopt point-of-care design capability for applications requiring faster turnaround than outsourced fabrication provides. Materialise and 3D Systems both hold significant positions in this segment, backed by years of software investment and established hospital purchasing relationships across major healthcare systems worldwide. Growth concentrates among hospitals specifically expanding point-of-care manufacturing programmes under formal regulatory frameworks, though manufacturers face rising competitive pressure from smaller regional design specialists in applications where local turnaround weighs more heavily than maximum software sophistication on purchasing decisions. Suppliers with modular, lower-cost platforms increasingly win these smaller-scale deployments ahead of larger legacy competitors.
CAGR 12.4%
Full segment breakdown across 6 segments available in the complete report.

Regional Architecture and Country Demand Map

North America accounts for nearly a third of global maxillofacial implant revenue, reflecting the United States' concentration of point-of-care regulatory clearance and complex reconstruction case volume, while South Asia and Pacific posts the fastest regional growth on expanding trauma surgical capacity nationwide, supported by rising government healthcare funding each year.

North America

The United States drives the overwhelming majority of regional demand through its concentration of FDA-cleared point-of-care manufacturing programmes and its large trauma and oncology reconstruction case volume across leading academic medical centers. Stryker and Johnson & Johnson both maintain deep domestic manufacturing and design presence serving this demand directly. Rising hospital investment in surgical planning software has meaningfully expanded demand for patient-specific implant design across multiple regional academic medical center networks in particular. Canada contributes a smaller but stable share, with provincial healthcare systems gradually expanding coverage for patient-specific reconstruction following patterns already established south of the border. Mexico's demand ties increasingly to cross-border medical device manufacturing serving both domestic and export markets.
Share: 32% | CAGR: 9.6% (2026 to 2036)

Western Europe

Germany anchors regional demand through its well-established craniomaxillofacial surgery base and KLS Martin's domestic engineering presence built over decades of continuous implant technology development. Belgium follows closely, with Materialise's domestic software and manufacturing presence driving accelerated point-of-care adoption across hospital systems nationwide. The United Kingdom and Netherlands contribute meaningful shares tied to established craniomaxillofacial surgical centers and long-standing implant supplier relationships across the continent. Regional growth trails North America and East Asia because much of Western Europe's titanium reconstruction base is already relatively mature, reflected in slower adoption of newer patient-specific technology than most other global regions currently show, a pattern regional suppliers expect to persist through the coming decade of continued gradual modernisation.
Share: 24% | CAGR: 8.6% (2026 to 2036)
Regional intelligence for 5 additional markets available in the complete report: East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe. Contact sales@marketmindsadvisory.com.
3d-printed-maxillofacial-implants-market-country-cagr-analysis-1786463123365

Where Maxillofacial Implant Margin Concentrates

Margin follows design complexity and clinical relationship depth, not device volume alone. Suppliers who win early surgeon design relationships lock in multi-year case referral streams that stock hardware distributors increasingly struggle to match once the surgical relationship is fully established across the hospital's entire reconstruction programme, a dynamic reshaping how suppliers prioritise clinical engagement investment.

Winning Early Academic Surgeon Design Relationships

Suppliers who secure design specification during a surgeon's early case planning relationship typically retain that surgeon's referral volume across successive complex cases, since switching design partners mid-relationship requires costly workflow retraining that surgeons avoid wherever possible across every affected surgical department. Materialise and Stryker have both invested heavily in early engagement with leading academic surgeons specifically to secure these relationships ahead of formal hospital procurement competitions. Early-established design partners typically capture pricing 9 to 15 percent above what competitive late-stage bidding would produce, reflecting the switching-cost advantage built into the relationship timing itself.
Market Impact: Adds a 9 to 15% pricing edge overal

Building Point-of-Care Software Licensing Support Programmes

Suppliers who pair implant hardware with proprietary point-of-care design software licensing capture higher-margin recurring revenue beyond the physical device cost itself, since hospital systems increasingly value integrated design workflow when justifying premium platform specification internally to procurement committees each budget cycle. Materialise and 3D Systems both run dedicated hospital software implementation teams that work directly with customer clinical engineering departments throughout the specification process. This software licensing layer has widened effective programme margins by an estimated 11 to 17 percentage points versus hardware-only supply agreements documented in recent investor materials.
Market Impact: Widens margins by 11 to 17 points o

Regional Design Center Capacity for Local Regulatory Eligibility

Suppliers establishing local design center capacity in markets with national regulatory content requirements, notably India's healthcare infrastructure investment programme, secure preferential access to hospital sourcing decisions tied to those same requirements set by policy and periodically revised over time. Several global suppliers have expanded Indian design operations specifically to capture this advantage ahead of competitors still supplying from import-based positions and lacking comparable local presence of their own. Local design centers report winning an estimated 17 to 24 percent more hospital contracts in content-linked markets than comparable import-dependent competitors face each year.
Market Impact: Wins 17 to 24% more local hospital

Building Case Outcome Registry and Evidence Programmes

Suppliers who develop structured clinical outcome registries documenting long-term patient results capture higher-margin premium device revenue while shortening the evidence-gathering timeline for hospitals otherwise facing lengthy independent outcome studies entirely on their own. Stryker and KLS Martin both maintain dedicated clinical affairs teams that work directly with academic surgeon investigators throughout the evidence generation and publication process. Registry-backed devices have historically captured 18 to 25 percent higher reimbursement approval rates than devices lacking comparable published outcome data, based on comparable prior programme patterns MMA has tracked closely across multiple recent registry cycles.
Market Impact: Lifts reimbursement approval rate 1

Who Controls the Margin Pool

CR5 sits at 46 percent, moderately concentrated for a specialty medical device category this size, reflecting the high regulatory clearance and clinical relationship barriers that keep new entrants limited. Stryker and Johnson & Johnson hold the largest positions, with a meaningful gap to KLS Martin and Materialise in the next tier of established challengers.
Current competitive activity centres on three fronts: established titanium implant makers defending surgeon relationships while expanding into PEEK and point-of-care design capability, specialty design firms racing to expand hospital software licensing ahead of incumbent responses, and all major players investing in clinical outcome registries targeting rapidly tightening reimbursement documentation requirements worldwide.

Emerging pressure comes from specialty Asian design and manufacturing firms, who have moved from basic titanium fabrication toward broader patient-specific design ambitions as domestic hospital investment creates a genuine opening against established Western incumbents defending their core franchise across every major product category. Rankings shift most at the application-specialty level rather than globally: a manufacturer's dominant position in trauma reconstruction carries limited weight in oncology cranial cases, where imaging compatibility and design turnaround increasingly determine specification outcomes each budget cycle.
3d-printed-maxillofacial-implants-market-company-positioning-matrix-1786463123530

Competitive Moat and Risk Dimensions

STRYKER CORPORATION

Moat: Full-Portfolio Surgical Relationship Coverage

Stryker's full-portfolio craniomaxillofacial product line, spanning titanium through specialty PEEK and guide design capability, lets it win comprehensive hospital and surgeon design agreements that single-application competitors cannot match, giving it a durable revenue base across nearly every applicable reconstruction application and case volume tier worldwide.
STRYKER CORPORATION

Risk: Point-of-Care Software Underexposure

Stryker's comparatively limited presence in point-of-care design software leaves it exposed to Materialise and 3D Systems capturing the fastest-growing segment of hospital manufacturing procurement, a gap that could widen as hospital-based design programmes continue expanding faster than Stryker's core hardware franchise grows each year overall.
MATERIALISE

Moat: Point-of-Care Software Platform Scale

Materialise's software platform scale and deep relationships with hospital clinical engineering departments across North America and Europe give it a workflow-integration advantage in point-of-care design that hardware-focused competitors have struggled to match on comparable large hospital system tenders across multiple developed healthcare markets worldwide, reinforced by continued platform investment.
MATERIALISE

Risk: Limited Hardware Manufacturing Scale

Materialise's comparatively limited direct implant manufacturing scale leaves it dependent on partner relationships for hardware production, a gap that could widen as vertically integrated competitors continue expanding faster than Materialise's core software franchise grows each year overall. That gap has widened noticeably in recent hospital tender cycles across multiple regions.

Players Tracked

Prominent Players

Stryker Corporation
Johnson & Johnson
KLS Martin Group
Materialise
Zimmer Biomet Holdings

Other Key Players

Oxford Performance Materials
OSSDSIGN AB
Renishaw plc
Xilloc Medical BV
Anatomics Pty Ltd
3D Systems Corporation
EOS GmbH
Stratasys Ltd
Ossiform ApS
CADskills BVBA
Kumovis GmbH
Lithoz GmbH
Ricoh Company Ltd
Nobel Biocare Services AG
Medartis Holding AG

Recent Developments

MARCH 2026

Materialise Expands Surgical Planning Partnership With Major Hospital Network

Materialise signed an expanded surgical planning software partnership with a major academic hospital network, covering an estimated 40 additional operating rooms across craniomaxillofacial and oncology reconstruction departments. The partnership followed extensive evaluation of design turnaround time and case outcome documentation across participating surgical teams and affiliated academic departments.
Signal: Hospital networks are standardising point-
NOVEMBER 2025

Stryker Acquires Specialty Cranial Implant Design Company

Stryker completed an acquisition of a specialty cranial implant design company, strengthening its PEEK and complex craniofacial design portfolio ahead of rising oncology reconstruction demand. The deal covers exclusive access to specific patient-specific design algorithms developed by the acquired company, alongside shared future improvement rights.
Signal: Established implant manufacturers are acqu
JUNE 2025

KLS Martin Opens Dedicated Point-of-Care Manufacturing Facility

KLS Martin completed construction of a dedicated point-of-care manufacturing support facility, adding design capacity equivalent to roughly 22 percent of its existing annual patient-specific device volume. The expansion targets rising demand from European hospital systems seeking qualified point-of-care design support partners across multiple national healthcare networks and surgical departments.
Signal: Established European implant manufacturers

Titanium and PEEK Polymer Feedstock Costs

Medical-grade titanium powder and PEEK polymer feedstock together represent roughly 38 percent of maxillofacial implant manufacturing COGS, sourced from a small global base of specialized medical-grade powder producers and a smaller set of PEEK polymer compounders qualified to biocompatibility specifications required across every major application segment worldwide, particularly for implantable-grade material, across every major manufacturing hub overall today.
Titanium powder pricing volatility during 2021 and 2022 pushed input costs up a documented 21 percent according to industry supplier disclosures, forcing several manufacturers to renegotiate multi-year fixed-price hospital contracts signed before the increase took hold across the industry. PEEK polymer pricing, particularly relevant to premium cranial implant grades, has added further cost pressure given periodic tightness in specialized medical-grade polymer manufacturing capacity shared with broader implantable device end markets.

Exposure varies by manufacturer scale and material mix. PEEK-focused manufacturers remain most exposed to specialty polymer price swings given their higher relative material content, while titanium-focused manufacturers face comparatively more stable input costs tied to established powder metallurgy supply chains that have changed relatively little over recent decades of commercial production at meaningful scale across the industry.
3d-printed-maxillofacial-implants-market-cost-volatility-analysis-1786463123705

Long-Term Titanium Powder Supply Agreements

Larger manufacturers now lock in multi-year medical-grade titanium powder supply agreements with fixed volume commitments, insulating implant pricing from short-term commodity swings that previously forced costly mid-contract renegotiations with hospital customers across the industry and delayed delivery schedules considerably each production cycle observed across multiple manufacturing regions and supplier tiers worldwide today and abroad each cycle.

In-House PEEK Compounding Capability

Several leading manufacturers have built internal PEEK polymer compounding and quality control capability specifically to reduce dependence on external suppliers for components requiring proprietary biocompatibility performance characteristics, trading higher fixed capital investment for greater supply certainty during periods of industry-wide demand and constrained third-party manufacturing capacity across the entire supply chain each fiscal year overall.

Dual-Sourcing Medical-Grade Powder Suppliers

Manufacturers increasingly qualify two titanium powder suppliers per product line rather than one, adding validation cost upfront but avoiding single-supplier exposure during periods of raw material tightness affecting the broader implantable device supply chain simultaneously across multiple concurrent production and testing programmes worldwide each cycle of ongoing procurement planning and budget review overall and beyond.

Portfolio Architecture for Margin Defence

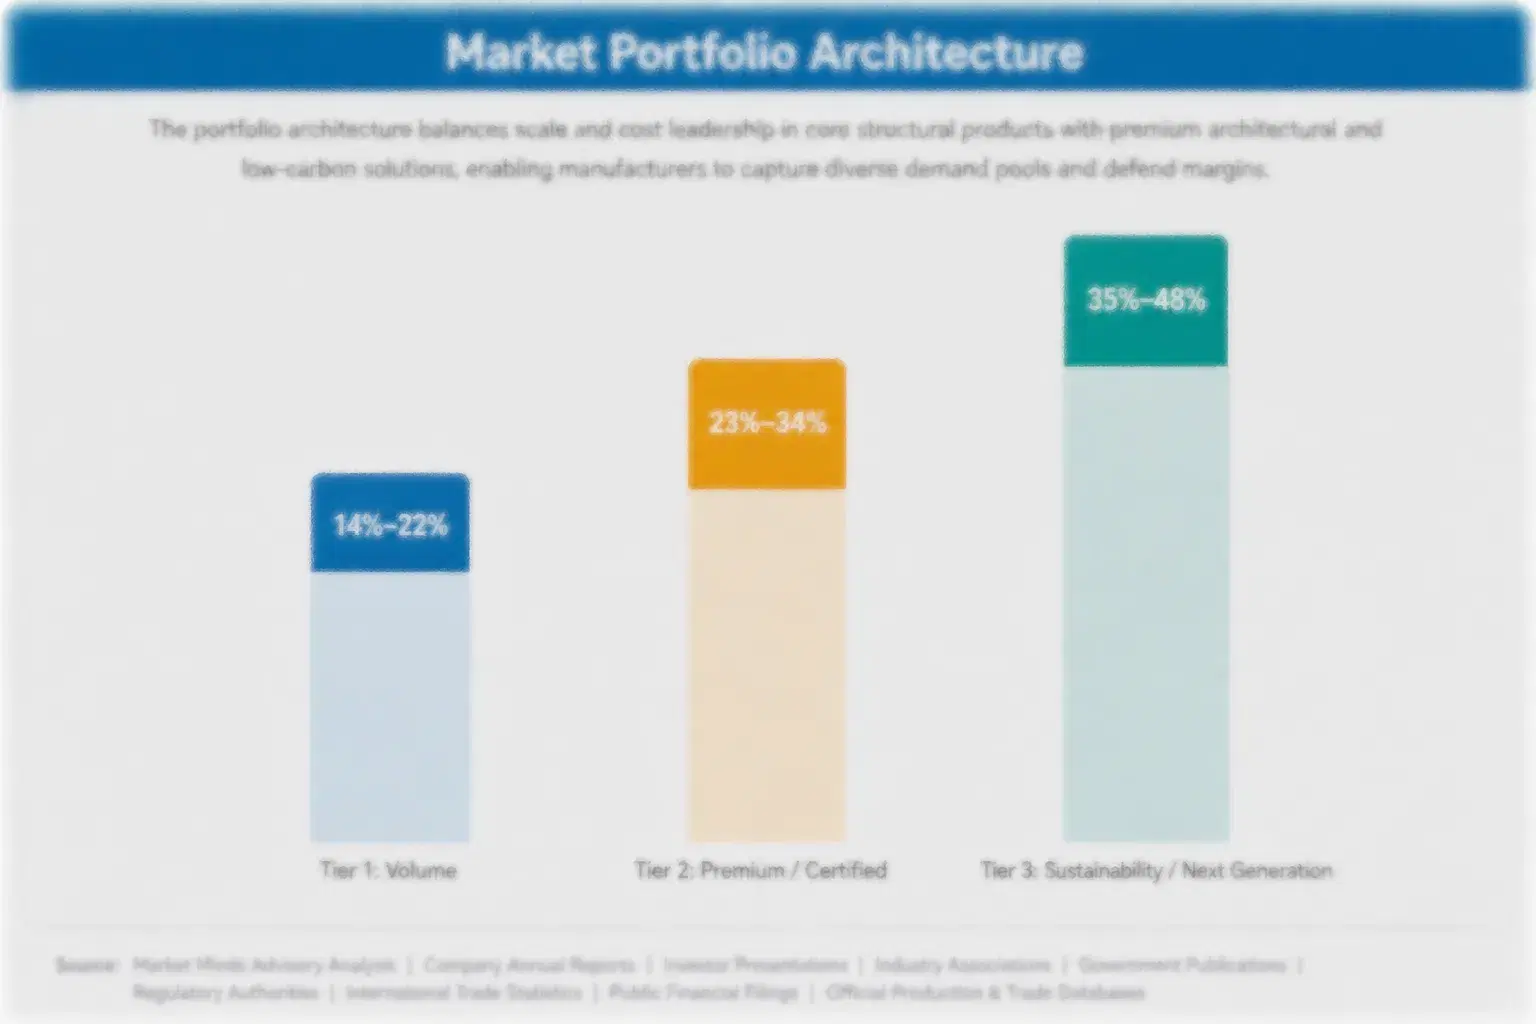
Portfolio economics split across three tiers. Standard titanium plates for mainstream trauma reconstruction compete mainly on price in a moderately consolidated market shaped by decades of manufacturing efficiency gains, while patient-specific PEEK and complex craniofacial implants command the highest margins, reflecting the engineering premium hospitals pay for capabilities stock hardware cannot deliver in high-value, imaging-critical applications built from the ground up around modern oncology
The tension between volume and premium plays out most visibly in the transition period underway right now, where suppliers must simultaneously defend mature titanium business generating predictable cash flow while investing heavily in point-of-care design capability that may not reach profitable scale for several more years of platform ramp-up and hospital system qualification testing across multiple surgical programmes still working through regulatory validation processes worldwide and across nearly every affected jurisdiction.

High-value margin pools concentrate in early-stage surgeon design relationships and point-of-care software licensing, where limited qualified competition keeps pricing power intact well past what the mature titanium segment retains after decades of established, price-competitive manufacturing among a stable group of global suppliers serving nearly every major application worldwide, across nearly every procurement channel available today.

Volume / Commodity-Adjacent Tier

Standard titanium plates for mainstream trauma reconstruction applications, competing primarily on price against multiple qualified global suppliers with comparable manufacturing scale, delivery reliability, and hospital service network coverage nationwide and abroad.
Gross Margin: 20%-28%

Premium / Certified Tier

Patient-specific titanium and standard PEEK implants carrying established brand equity or proven reliability credentials across multiple hospital procurement platforms sold worldwide each year and every affected region and market segment.
Gross Margin: 28%-38%

Sustainability / Regulatory / Next-Generation Tier

Complex craniofacial PEEK implants and point-of-care design platforms capturing premium pricing during this early commercial adoption phase across leading academic medical center platforms and compliance-driven segments today and every year beyond.
Gross Margin: 38%-50%
3d-printed-maxillofacial-implants-market-portfolio-architecture-1786463123883

High-value Sub-segments and Strategic Watch-out

Academic Hospital Point-of-Care Design Wins

Early software and hardware supply contracts on academic hospital point-of-care platforms combine high per-unit value with the fastest specification growth in the category, as hospitals commit to the technology across successive department generations following initial validation and extended clinical testing programmes across multiple markets and customer segments.
Gross Margin: 36%-46%

India Trauma Surgical Capacity Contracts

Implant design supply agreements tied to India's healthcare infrastructure investment trend carry solid margins with a growth curve still accelerating rapidly, as domestic hospital systems scale surgical capacity faster than most Western modernisation programmes have managed to date across comparable case volume timelines now firmly in place.
Gross Margin: 24%-34%

Established Trauma Titanium Base

Long-established trauma reconstruction titanium plates generate steady, predictable revenue tied to case volume replacement cycles but carry moderate margins after decades of price-competitive manufacturing among a broad group of qualified suppliers worldwide competing mainly on price and hospital service quality offered nationwide each year overall.
Gross Margin: 20%-28%

Bioresorbable Craniofacial Implants

Bioresorbable craniofacial implants designed for pediatric and select adult reconstruction represent a strategic watch-out: it remains unclear how quickly long-term resorption and mechanical stability data will accumulate for mainstream adoption given unresolved long-term validation questions across major markets and application categories tracked closely by MMA analysts each year.
Gross Margin: N/A pre-validation

Surgical Case Lifecycle Economics

Maxillofacial implant demand behaves like a per-case consumable annuity rather than a purely discretionary capital purchase, since every applicable trauma or oncology reconstruction case consumes design and manufacturing resources regardless of how long that hospital has run its reconstruction programme, generating predictable recurring revenue tied directly to surgical case volume rather than a one-time equipment sale negotiated and forgotten.
Adoption depth varies considerably by application volume and clinical complexity. Academic medical centers and oncology reconstruction specialists adopt patient-specific design fastest, since poor anatomic fit or imaging incompatibility in these categories carries meaningfully higher clinical consequence than in routine trauma repair work. Community hospitals and smaller surgical centers show far slower adoption, as capital budget constraints and functional stock hardware keep conventional titanium the default choice until case complexity or surgeon preference drives change.

A generational shift is underway in craniomaxillofacial surgical training programmes. Surgeons trained on digital surgical planning and additive manufacturing workflows after 2015 show meaningfully more comfort specifying patient-specific implant design than predecessors trained purely on stock hardware technique, a shift that should widen patient-specific adoption further as this cohort gains seniority within academic and community surgical practices over the next decade of continued technology transition.
3d-printed-maxillofacial-implants-market-end-use-penetration-index-1786463124054

Positioning for the Point-of-Care Design Transition

These are among the four positions where our research anticipates prominent divergence between winners and laggards over the coming forecast period. Each is grounded in the demand model, the regulatory perimeter, and the announced capacity pipeline.
01 / SURGEON RELATIONSHIP TIMING

Engage academic surgeon teams years before formal hospital contracts

Suppliers who wait for formal hospital procurement competitions to begin lose design relationship opportunities to rivals who engaged academic surgeon teams during early case planning collaboration, well before any competitive bidding process starts. Materialise's design win success traces directly to years of early engagement with surgeon teams that competitors are now scrambling to replicate across comparable hospital programmes. Suppliers without comparable early relationships face a lasting competitive disadvantage in hospital sourcing that formal competitive bidding alone cannot fully overcome once surgical workflow decisions are already locked.
02 / TECHNOLOGY BRIDGE STRATEGY

Offer both titanium and PEEK options across applications

Hospital systems remain genuinely divided on whether to adopt full point-of-care PEEK design immediately or continue relying on proven titanium hardware for critical applications. Suppliers offering only one material risk losing specification decisions to hospitals whose clinical risk tolerance does not match that single material choice at this particular point in the budget cycle and planning horizon. The most successful suppliers maintain both titanium and PEEK product lines simultaneously, letting surgeon clinical judgment rather than supplier limitation determine which material ultimately wins each specification.
03 / REGIONAL DESIGN CENTER STRATEGY

Build local capacity ahead of content-linked healthcare deadlines

Content-linked healthcare investment programmes like India's infrastructure plans increasingly determine which suppliers win hospital contracts in fast-growing markets, yet several established suppliers still treat regional design centers as a secondary consideration rather than a near-mandatory market entry requirement worth prioritising early on. That sequencing costs real contract share during a market's critical early growth phase, when hospital procurement moves fastest and decisions lock in for years. Suppliers who establish local capacity ahead of infrastructure deadlines consistently outperform import-dependent competitors on hospital contract win rates.
04 / INPUT COST RESILIENCE STRATEGY

Diversify PEEK polymer exposure before demand volume scales further

Titanium powder price volatility during 2021 and 2022 forced several suppliers to renegotiate fixed-price hospital contracts at a loss, and PEEK polymer exposure tied to cranial implant production now presents a comparable emerging risk few suppliers have fully hedged against. Suppliers still buying components on unhedged spot-market terms remain exposed to the same risk as PEEK volume scales considerably over the coming years. Commodity hedging has already proven its value for suppliers who adopted it ahead of recent price volatility cycles.

Engagement Snapshot From the Field

A live engagement with an industry participant carrying material or product regulatory and market exposure ahead of a defining policy shift, showing how our research translates into a defensible multi-year portfolio strategy.
MARKET MINDS ADVISORY · CLIENT ENGAGEMENT SUMMARY
3D Printed Maxillofacial Implants Producer Strategic Portfolio Review and Transition Roadmap 2026·Investment Scenario on 3D Printed Maxillofacial Implants Exposure Evaluation 2025-26
CLIENT PROFILE
The client is a mid-size academic hospital network preparing for expanded point-of-care craniomaxillofacial design capability across three surgical departments, with annual complex reconstruction case volume reported in the 800 to 1,200 case range (client-reported, unverified by MMA), evaluating implant design options ahead of a binding capital budget deadline across multiple surgical departments and affiliated academic partners.
STRATEGIC CHALLENGE
The network's clinical engineering team was divided between committing to full point-of-care design infrastructure for maximum turnaround speed or choosing a more conservative outsourced design model with established reliability, given internal disagreement over total cost of ownership across the departments' expected multi-year technology adoption timeline and staffing cost assumptions used in financial modelling.
MMA APPROACH
MMA benchmarked comparable academic hospital network design decisions made by four networks over the prior three years, analysing design turnaround, case outcome quality, and total system cost across both technology options under consideration. The team conducted primary interviews with clinical engineers and implant suppliers actively developing both technology paths in parallel across the industry.
KEY FINDINGS
  1. Full point-of-care design infrastructure offered meaningfully faster case turnaround than outsourced alternatives across every comparable surgical scenario reviewed in detail by the team.
  2. Three of four benchmarked networks had delayed full point-of-care adoption in at least one department due to unresolved capital budget approval requirements still pending internal review.
  3. Outsourced design systems carried a 15 to 21 percent lower total component cost given their reliance on more established manufacturing processes already proven at scale.
  4. Supplier lead times for point-of-care infrastructure setup ran approximately five months longer than outsourced alternatives across the benchmarked comparable programmes reviewed by the team.
RECOMMENDED STRATEGY
Phase 1: Phase 1 (Months 1 to 5): Finalise target department design requirements and confirm capital budget approval by department and site. Phase 2: Phase 2 (Months 6 to 12): Select an outsourced baseline design approach for early cases while maintaining a point-of-care upgrade path. Phase 3: Phase 3 (Months 13 to 24): Execute infrastructure qualification and begin point-of-care operations ahead of the network's later technology adoption phases.
OUTCOME
The network selected a phased approach combining outsourced baseline design for immediate cases with point-of-care infrastructure planned for a later department upgrade cycle, avoiding an estimated 4 to 6 month technology adoption delay across its initial deadline (client-reported, unverified by MMA). The decision reduced near-term capital risk while preserving the option to adopt full point-of-care capability later.

Frequently Asked Questions

Foundational context covering the market sizes, CAGR, scope, country, region and competition that inform every finding below. This section is provided to cover basics and most often pre-purchase conversations, answered from the MMA Primary Research Dataset.

What is the current size of the 3D Printed Maxillofacial Implants Market?

The global market reached an estimated 0.94 billion dollars in 2025, anchored by a mature titanium implant hardware base. Growth is concentrated in PEEK cranial and point-of-care design segments.

How large will the 3D Printed Maxillofacial Implants Market be by 2036?

MMA projects the market will reach approximately 2.75 billion dollars by 2036 under the base-case forecast scenario. This reflects rising point-of-care manufacturing adoption and radiolucent implant demand worldwide.

What is the CAGR for the 3D Printed Maxillofacial Implants Market 2026 to 2036?

The base-case compound annual growth rate is 10.2 percent across the full ten-year forecast period. Bull and bear scenarios range from 8.8 to 11.6 percent.

Which segment is growing fastest?

PEEK cranial implants lead at a 13.8 percent CAGR, roughly 1.35 times the overall market rate. Patient-specific surgical guides and planning models follow as the second-fastest segment.

Who are the major companies in the 3D Printed Maxillofacial Implants Market?

Stryker Corporation, Johnson & Johnson, KLS Martin Group, Materialise, and Zimmer Biomet Holdings hold the top five positions by revenue. Specialty Asian design and manufacturing firms are closing the point-of-care gap.

Which country is growing fastest?

India leads at an estimated 12.2 percent CAGR, driven by expanding trauma surgical capacity and government healthcare infrastructure investment. Domestic design capability requirements support continued adoption.

Report Segmentation Architecture

The full report scope spans multiple orthogonal segmentation dimensions, with cross-tabulated demand data provided for each dimension pair. Coverage extends further to regional breakdowns, trend trajectories, and the competitive detail needed to support segment-level decision-making.

By Implant Application

  • Custom Titanium Cranial Plates
  • PEEK Cranial Implants
  • Orbital Floor and Facial Reconstruction
  • Mandibular and Maxillary Reconstruction
  • Patient-Specific Surgical Guides
  • Temporomandibular Joint Implants

By End-Use Facility

  • Academic Medical Centers
  • Community Hospitals
  • Trauma and Emergency Centers
  • Oncology Reconstruction Centers
  • Ambulatory Surgical Centers

By Commercial Dimension

  • Original Device Supply
  • Point-of-Care Software Licensing
  • Design and Manufacturing Services
  • Clinical Training and Certification Services

By Region

  • North America
  • Western Europe
  • East Asia
  • South Asia and Pacific
  • Latin America
  • Middle East and Africa
  • Eastern Europe

Scope, Methodology, and Coverage

Every figure in this report is reproducible from documented input assumptions. The scope below maps the historical period, the forecast horizon, the segmentation dimensions, and the countries covered, alongside the underlying primary and qualitative methodology.
Historical Period
2020 to 2025
Forecast Period
2026 to 2036
Base Year
2025 (USD billions; MMA Primary Research Dataset, August 2026)
Market Definition
This market covers patient-specific implants and surgical guides produced by additive manufacturing for craniomaxillofacial reconstruction, including cranial plates, orbital floor implants, mandibular and maxillary reconstruction devices, and associated planning software and guides. It excludes dental implants sold for routine tooth replacement and non-printed stock craniomaxillofacial hardware.
Quantitative Units
USD billions (current prices); installed unit volume by application where applicable
Segmentation Dimensions
By Implant Application; By End-Use Facility; By Commercial Dimension; By Region
Regions Covered
North America, Western Europe, East Asia, South Asia and Pacific, Latin America, Middle East and Africa, Eastern Europe
Countries Covered
USA, China, Germany, France, UK, Japan, South Korea, India, Australia, Canada, Brazil, Mexico, Indonesia, Vietnam, Belgium, UAE, Saudi Arabia, South Africa, Nigeria, Turkey, Poland, Netherlands, Italy, Spain, Sweden, Switzerland, Argentina, Colombia, Singapore, and additional markets relevant to this sector
Key Companies Profiled
Stryker Corporation, Johnson & Johnson, KLS Martin Group, Materialise, Zimmer Biomet Holdings, Oxford Performance Materials, OSSDSIGN AB, Renishaw plc, Xilloc Medical BV, Anatomics Pty Ltd, 3D Systems Corporation, EOS GmbH, Stratasys Ltd, Ossiform ApS, CADskills BVBA, Kumovis GmbH, Lithoz GmbH, Ricoh Company Ltd, Nobel Biocare Services AG, Medartis Holding AG
Quantitative Methodology
Primary survey, n=3,800 respondents, Q4 2025, six countries; demand-side model with trade association cross-validation
Qualitative Methodology
47 expert interviews, Q4 2025; applied to validate demand model assumptions, identify emerging dynamics, and assess competitive positioning
Report Format
PDF and XLSX data workbook (Word format preview document)
Publisher
Market Minds Advisory
Report Code
MMA-2026-MED-702
Published
August 2026
Contact
sales@marketmindsadvisory.com | www.marketmindsadvisory.com

Purchase the full 3D Printed Maxillofacial Implants Market Report (2026 to 2036).

The full report delivers a company-by-company product design tracker covering every major titanium and PEEK implant developer through 2030 with disclosed regulatory clearance timelines and anticipated point-of-care expansion milestones. It includes a point-of-care manufacturing regulation policy tracker mapping compliance requirements across every profiled hospital category and region worldwide. Hospital and surgeon adoption survey data is provided from MMA's primary research programme, alongside device and software cost benchmarking across major producing regions tracked closely. Buyers also receive a company-level financial and regulatory-milestone model updated quarterly throughout the subscription period each year.
Company-by-company product design and clearance tracker
Point-of-care manufacturing regulation policy tracking database
Hospital and surgeon adoption survey data collected
Quarterly competitor financial and milestone model updates
Device and software cost benchmark data set
Custom clinical strategy and procurement workshops

Built For The People Who Decide

From boardroom strategy to bench-side execution, this report is read cover-to-cover by leaders shaping the next decade of their industry, turning demand scenarios, market dynamics and valuation benchmarks into decisions.
CXOs/ Presidents/ VPs/ Managers
M&A and Corporate Development
Strategy Teams and R&D Heads
Procurement and Product Directors
Regulatory and Compliance Leaders
Investor Relations and Equity Analysts